
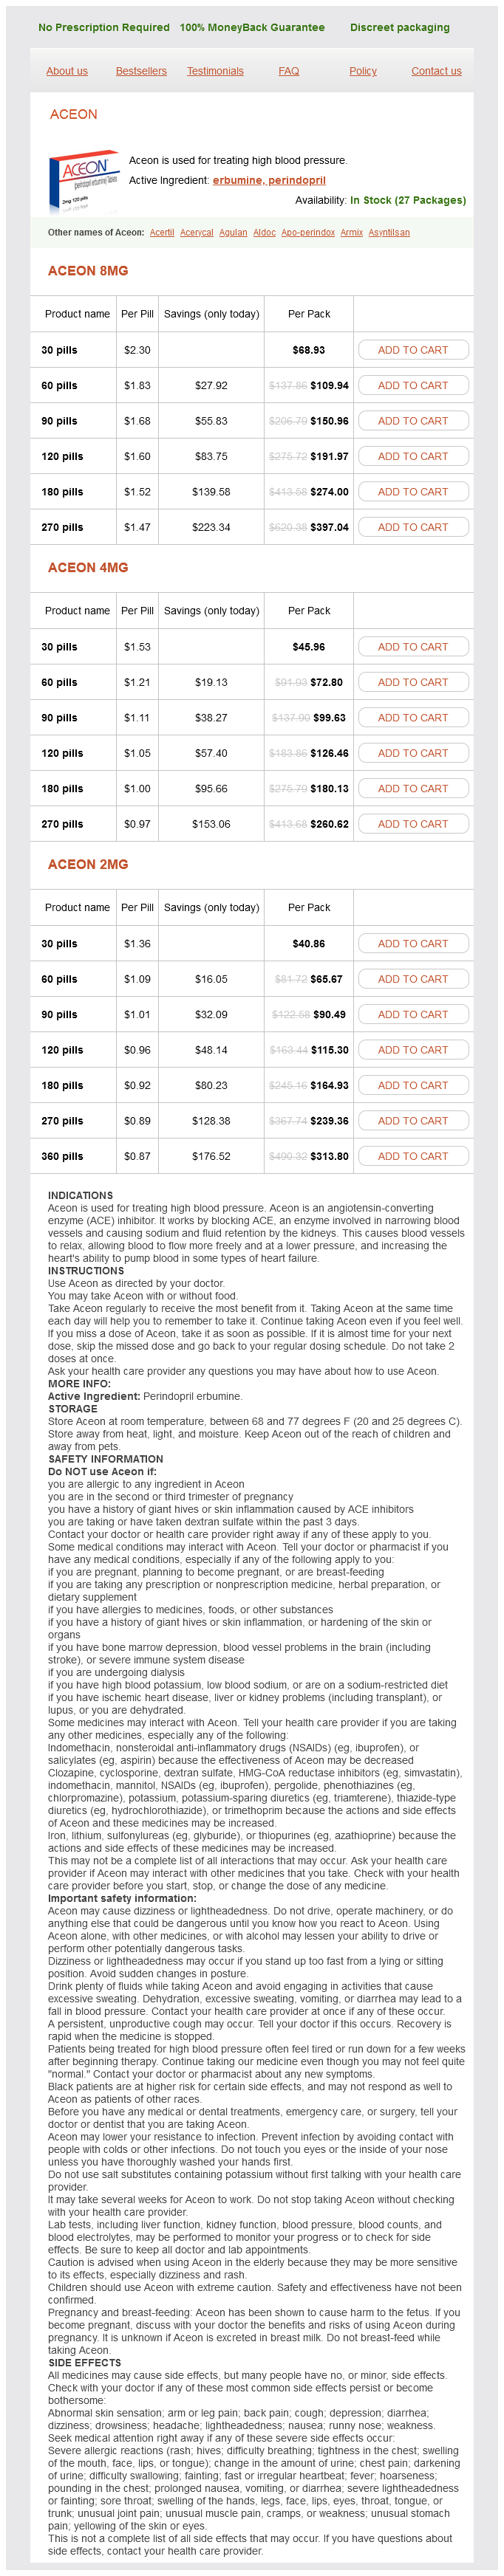
Aceon
Aceon 8mg
- 30 pills - $68.93
- 60 pills - $109.94
- 90 pills - $150.96
- 120 pills - $191.97
- 180 pills - $274.00
- 270 pills - $397.04
Aceon 4mg
- 30 pills - $45.96
- 60 pills - $72.80
- 90 pills - $99.63
- 120 pills - $126.46
- 180 pills - $180.13
- 270 pills - $260.62
Aceon 2mg
- 30 pills - $40.86
- 60 pills - $65.67
- 90 pills - $90.49
- 120 pills - $115.30
- 180 pills - $164.93
- 270 pills - $239.36
- 360 pills - $313.80
Aceon dosages: 8 mg, 4 mg, 2 mg
Aceon packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 911
Only $0,93 per item
Description
Technique Horizontal transposition flaps arteriographic embolization aceon 4 mg buy without a prescription, needed for lid stabilization and based on the canthus within the higher lid hypertension 30 year old male aceon 8 mg cheap with amex, are outlined after subciliary incisions have been made within the lower lid blood pressure medication problems 8 mg aceon visa. C and D blood pressure medication without hair loss discount 2 mg aceon amex, Transposition and suturing of the flaps at the medial and lateral canthi. For patients with more distinguished eyes, tightening or stiffening of the lower lid by the previously described methods can produce a clotheslining impact on the lid. For these sufferers, a spacer graft mixed with lateral horizontal tightening can be utilized in the posterior eyelid lamella to prevent clotheslining and to keep away from an externally seen pores and skin graft. An incision is made beneath the inferior tarsus by way of the conjunctiva and inferior retractors, that are separated to produce the desired lid elevation. A spacer (ear cartilage or other) is then sutured into the created defect, which produces elevation of the lower lid to the specified degree. This technique, when combined with supraplacement of the lateral canthal tendon, should correct lower lid retraction in a prominent eye. These complicated instances of ectropion are commonly seen after surgical procedures for orbital eyelid trauma. Contracture of the orbital septum and capsulopalpebral fascia is often an essential issue within the pathogenesis of complex cicatricial ectropion. In most of these instances, malposition of the lower lid can be corrected only with grafting of each the exterior and inside eyelid lamella. If enough muscle tissue is current, it could be interposed between the grafts to provide an adequate blood supply. Chapter 30 � Cicatricial Ectropion and Entropion 887 Technique A posterior incision is made on the inferior tarsal edge, and the adhesions are dissected with upward retraction. The inferior incision must be under the inferior marginal artery, leaving the nasal blood provide intact to make sure the survival of the margin. Next, an incision is made across the subciliary area, with dissection of the skin or skin-muscle flap away from the lid. B, Correction of a bilevel contracture with a bilevel internal spacer and pores and skin grafting (or vertical recruitment of exterior skin). B, the affected person after a number of procedures of bilevel grafting with spacer insertion. Technique A full-thickness blepharotomy is made on the bottom fringe of the segment wanted for rotation. He is a candidate for pores and skin replacement of the external lamella in a standard ectropion repair. The affected person is a candidate for skin replacement of the exterior lamella in a standard ectropion restore, however he can also want resection of the damaged eyelid margin. This affected person might benefit from decrease lid reconstruction procedures, in addition to pores and skin grafting. However, a histologic management excision of the basal cell carcinoma with eyelid reconstruction procedures is indicated. The presentation of this situation is usually essentially the most hanging in older people. Cicatricial Entropion Cicatricial entropion is the inward turning of the eyelid margin. Caused by a contracture of the internal lamella of the eyelid, the condition results in the margin of the eyelid and lashes turning against the globe. Cicatricial entropion can happen in either the higher or the lower eyelid, and may develop after surgery, trauma, chemical injury, or inflammatory processes, together with ocular pemphigoid and Stevens-Johnson syndrome. Conditions commonly seen in these patients embrace the epidermalization of the mucosal floor of the internal eyelid margin and tarsoconjunctiva, which causes persistent epithelial irritation of the cornea. Elements of laxity or involutional entropion may be mixed with those of cicatricial adjustments, particularly after earlier surgical procedure or a quantity of traumas to the eyelids. The eyelid structures could additionally be fused, or the retractor fascia could also be attached in an uncommon means, inflicting an entropic position that may require additional procedures for correction. It is important to acknowledge these complicating elements in entropion as a end result of they could be surgically unresponsive to a normal procedure. Before considering surgical correction in a affected person presenting with entropion, the surgeon should try to categorize the entropion into one of many above classes. Other coexisting problems corresponding to epiblepharon, epicanthal folds, and margin deformities after tarsorrhaphy have to be famous. Likewise, any uncommon anatomic anomalies, such as adhesions between the inferior rectus muscle and the capsulopalpebral fascia and indirect muscle after inferior orbital trauma, have to be detected and corrected to prevent continued irregular traction on the lower lid constructions. B, Lid eversion reveals scarring and contracture of the conjunctiva and inside lamella. C, the identical patient after the placement of a spacer graft to right the cicatricial entropion. Chapter 30 � Cicatricial Ectropion and Entropion 893 Technique Canthotomy and cantholysis are performed, and the lid is everted. On the posterior floor, the tarsus is incised three mm under the eyelid margin and dissected until the lid assumes a normal position. There are a number of supplies used for posterior lamellar grafts, including ear cartilage, nasal chondromucosa, palatal mucoperichondrium, and full-thickness buccal mucous membrane; all have been used with success. In the immediate postoperative period after ear cartilage has been used for a posterior lamellar graft, a procedure that leaves the interior surface naked, instructing the patient to use steroidal or antibiotic eye drops will scale back ocular irritation. Nasochondromucosa is one other different; nonetheless, because the cartilage could be very thick and brittle and the nasal mucosa may be epidermalized, it may not be the perfect alternative in this scenario. Palatal mucoperichondrium makes an excellent internal lamellar alternative, as a end result of it offers a easy mucous membrane floor with some rigidity. If severe lid atrophy is present, the surgeon might consider an eyelid reconstructive procedure. B, A decrease lid spacer graft was positioned, and C, a Mitek anchor was inserted to support the scarred cheek. Transverse tarsotomy is most often used either together with a horizontal tightening process or in circumstances of mixed laxity and cicatricial entropion. Although it was initially meant to treat laxity entropion, it has turn into extensively used for mild circumstances of cicatricial entropion. Technique the horizontal tightening process is first performed to appropriate any laxity current. For a rotational impact, and to evert the lid margin in cases of gentle residual inturning, a full-thickness horizontal blepharotomy incision is made below the inferior fringe of the lower lid tarsal plate; ideally, the incision must be 4 to 5 mm from the margin. This procedure is performed in two steps, first with an external skin-muscle incision after which with a buttonhole incision into the fornix, which is enlarged with scissors. Sutures are handed from the decrease edge of the inner incision to the superior fringe of the exterior incision for a rotational impact. Worldwide, the most typical cause is trachoma; in the United States, nevertheless, the most common causes are scars from chronic blepharoconjunctivitis, Stevens-Johnson syndrome, and burns. Some circumstances could produce or mimic an entropion variant, but they behave differently from the true entropion. Floppy lid syndrome, congenital tarsal kink, and epicanthal folds-congenital or otherwise-may produce an entropion-like condition. The upper lid entropion could also be accompanied by a damaging illness of the margin, causing modifications that require particular procedures to be treated. In more extreme cases, the deficient posterior lamella have to be restored with a posterior lamellar graft. The origins of many upper lid entropion procedures stem from remedies for trachoma. Worldwide, this is the commonest process used for the correction of higher lid ectropion. C, Pretarsal skin tightening and tarsal fracture combined with a graft (mucous membrane). The anatomic basis of the procedure is a transverse tarsotomy with marginal rotation. A, the skin incision exposes the tarsus, where a wedge-shaped excision is carried out. Technique A lid crease incision is made with elevation of the myocutaneous layer from the tarsal plate.
Bardana (Burdock). Aceon.
- How does Burdock work?
- Are there safety concerns?
- Are there any interactions with medications?
- Dosing considerations for Burdock.
- Fluid retention, fever, anorexia, stomach conditions, gout, acne, severely dry skin, and psoriasis.
- What is Burdock?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96153
The anatomic layers and the course of the temporal nerve branches of the facial nerve relative to the sentinel vein department blood pressure jumps around order aceon 2 mg line. Mendelson and colleagues have described the retaining ligaments of the upper orbit and temporal line of fusion Table 6-1) heart attack 4 blocked arteries aceon 2 mg purchase mastercard. These are osteocutaneous ligaments arteria pulmonar 8 mg aceon purchase fast delivery, which stabilize the higher outer orbital zone and require launch to change the position of the brow and lateral eyebrow blood pressure jump order 8 mg aceon with visa. Moss described a temporal ligamentous adhesion that is a confluence of a quantity of retaining ligaments, together with the orbicularis-temporal ligament described by Knize, the superior temporal septum described by Moss, and the lateral orbital thickening described by Muzaffar. In addition to stabilizing the gentle tissue and floor anatomy, these ligaments separate the superficial fat compartments of the temporal area, mainly the center brow compartment from the lateral temporal compartment and the lateral orbital compartment. Table 6-1 Nomenclature of Facial Ligaments within the Literature Orbitomalar ligament (Kikkawa et al) Superficial lateral canthal tendon (Knize) Zone of adhesion (Knize) Orbital ligament (Knize) Orbicularis-temporal ligament (Knize) Anterior platysma-cutaneous ligament (Furnas) Platysma-auricular ligament (Furnas) Platysma-auricular fascia (Mendelson) Orbicularis retaining ligament (Muzaffar et al) Lateral orbital thickening (Muzaffar et al) Superior temporal septum (Moss et al) Temporal ligamentous adhesion (Moss et al) Inferior temporal septum (Moss et al) Masseteric cutaneous ligament (Stuzin et al) Parotid cutaneous ligament (Stuzin et al) Note that the nomenclature in each row describes ligamentous structures that occupy the same anatomic location however were given completely different names by various authors. The forehead rhytids, the glabellar rhytids, and the place of the hairline are evaluated to prevent elevation of the hairline. Box 6-1 Details to Consider Preoperatively Sex and ethnicity points History of prior brow carry or upper blepharoplasty procedures Eyebrow place and stability: brow-lash distance Brow symmetry and animation Upper eyelid ptosis Compensated brow ptosis Position of the hairline; brow contour Presence of brow, glabellar, and lateral orbital rhytids EyEbrow Position and stability An aesthetically desirable forehead place differs based on gender and ethnicity. The medial forehead is usually lower than the lateral brow, but the arch of the eyebrow is highly variable based on gender, age, and ethnicity. The peak of the forehead (E) is superior to the lateral corneoscleral limbus (D) rather than the tip or tail of the brow (C), which is seen in some ethnic variations. Point A is the lateral alar base, which marks the lateral forehead passing over the lateral canthus and the medial brow passing over the medial canthus. B is the vertical line from level A previous the medial canthus to the apex of the upper lid crease. The line from the lateral oral commissure (F) to the lateral limbus (D) identifies the line for placement of the endoscopic incision in the hairline for a less verticle lift. B, A normal brow place requires sufficient area between the forehead hairs and the lashes and eyelid. B, Six months after a brow lift, her brow-lash distance is improved and steady. However, brow asymmetry is a standard presenting signal of unilateral upper lid ptosis, as a result of arching the forehead on the facet of the underlying ptosis opens the ptotic lid. Although the eyebrow seems greater, sufferers with this condition incessantly have contralateral brow ptosis. Rather than performing a contralateral brow lift to elevate what appears to be a ptotic brow, the proper surgical procedure contains correcting the upper lid ptosis with reevaluation of the forehead position, which is usually normalized with correction of the forehead asymmetry with no forehead surgery. All sufferers presenting with brow asymmetry ought to be fastidiously evaluated for higher lid ptosis. For sufferers with unilateral brow ptosis, an eye fixed pad should be used during the scientific examination to patch the unilateral ptotic eyelid closed. After 5 to 10 minutes of analysis, the forehead place will normalize in patients with unilateral ptosis. Therefore a patch cover test is very useful for evaluating ptosis and compensatory brow asymmetry. B, She is shown after surgical procedure, which included correction of forehead asymmetry with an higher blepharoplasty and differential early overelevation with an endoscopic brow raise. Most will dislike the extra, though minimal, elevation of their hairline after traction of the forehead behind the hairline. Furthermore, a high hairline requires placement of the endoscopic incisions extra posteriorly inside the hair, which often makes the surgical process more difficult. The introduction of a straight fiberoptic endoscope is more difficult in sufferers with marked forehead convexity. They embody a pretrichial biplanar procedure, which elevates the forehead and lowers the hairline simultaneously. In some sufferers the forehead skin could be tightened extra by stress-free incisions in the periosteum and probably in the galea at the midforehead stage. In some men with deep transverse furrows in the midforehead skin, elevating the forehead and smoothing the forehead are achieved. GlabEllar rHytids Paired vertical lines and a transverse wrinkle in the glabellar area outcome from contraction of the paired corrugator supercilii and procerus muscles. This space can be improved by partial excision of the muscles, combined with superior elevation and redraping performed with an endoscopic forehead raise. The endoscopic view offers clear visualization of the procerus and corrugator muscles and the supraorbital and supratrochlear neurovascular bundles. This facilitates partial myectomy of the muscles throughout the midbelly of the muscle, while preserving the nerves and preventing bleeding. Once the brow is elevated with fixation vertically and laterally, improvement of the glabellar rhytids is clear. The temporal line of fusion is launched deep to the temporal parietal fascia on the superficial layer of the deep temporal fascia, beneath direct imaginative and prescient from lateral to medial to forestall dissection beneath the temporalis muscle. The subperiosteal or preperiosteal plane is connected to the lateral temporal dissection to release the retaining ligaments of the temporal brow. The sentinel vein is visualized and preserved by avoiding the situation of the temporal branch of the facial nerve. If a subperiosteal dissection is performed, the periosteum is split lateral to the supraorbital nerve. This facilitates release and elevation of the tail of the forehead and excision and fixation of the scalp to the deep temporal fascia. In patients with a receding hairline or a distinguished forehead, endoscopic visualization could additionally be difficult due to the space and angle that the endoscope needs to traverse. Traction on the forehead and scalp tissues turns into a lot much less effective the farther posterior the incisions are made. The decrease the forehead hairline and the less the curvature of the brow, the easier the endoscopic technique. It is extensively performed due to surgeon choice and/or lack of expertise or gear required for an endoscopic brow carry. Because the coronal incision usually extends laterally, it additionally includes a temporal forehead carry generally. Shortcomings of a coronal brow raise embody a bent for overcorrection, more hair loss, numbness posterior to the scar, a extra invasive surgical process with an extended scar across the complete scalp, and less patient acceptance. For these reasons, endoscopically assisted brow lifts are preferred in most sufferers. This process also elevates the brows and improves the glabellar frown traces with a partial myectomy of the procerus and corrugator muscular tissues. In these circumstances, a pretrichial coronal incision with elevation on the subcutaneous stage provides higher entry for endoscopic visualization whereas preserving the sensory branches to the forehead and scalp. A biplanar carry prevents further hairline elevation and can be utilized to lower the hairline while elevating the forehead. This procedure is primarily of historical interest, as a outcome of the scar is positioned in the heart of the forehead. It could be reserved for elderly male patients with vital forehead ptosis that decreases the superior visible area. It is performed via an incision posterior to the hairline, with dissection within the subgaleal plane deep to the temporoparietal fascia. The process can elevate the tail of the brow and proper lateral orbital rhytids or smile strains. It is helpful for revising insufficient temporal elevation after an endoscopic brow lift or face carry. A temporal carry is also helpful as an adjunct to appropriate residual lateral rhytids and laxity after an higher blepharoplasty or a midface lift. A direct forehead raise requires a short incision just above the central forehead hairs; it produces minor scar visibility, though normally no worse than present brow wrinkles. Those with a lower, unstable forehead require some brow elevation to stop downward pulling on the forehead by an upper blepharoplasty. The benefit of an inside browpexy over a direct forehead lift is that the procedure is performed via the lateral aspect of the higher blepharoplasty incision. Preperiosteal dissection is performed 10 to 15 mm above the superior orbital rim lateral to the supraorbital nerve. A everlasting suture is placed 10 mm above the supraorbital rim within the periosteum and to the deep subcutaneous and dermal tissue at the inferior side of the peak of the brow.
Specifications/Details
This seems to be effective blood pressure medication exercise 8 mg aceon visa, although it has inherent problems of extrusion and in many cases must be thought of a temporary process hypertensive urgency discount aceon 8 mg online. In most circumstances blood pressure band aceon 8 mg buy amex, all gadgets that drive upper lid closure could cause vital ptosis of the higher lid arteria cerebral media 8 mg aceon generic with mastercard. Morel-Fatio Palpebral Spring the palpebral spring seems to be the least profitable of the units for improving closure of the upper lid. There is an inclination for the spring to erode and extrude over time, and it is rather tough to fine-tune the quantity of closure desired. Incisions are made within the medial canthus, exposing the anterior reflection of the medial canthal tendon and within the lateral canthal space exposing the bony lateral rim. A 1 mm silicone rod is threaded from the lateral canthal area within the suborbicularis airplane in the pretarsal space to the internal canthus. It is then introduced via a drill gap on the lateral canthal area via the orbital rim and fixated in those two areas. To achieve extra closure, one should sacrifice opening of the upper lid when the individual is awake in primary gaze. There is usually a tendency for erosion of the silicone through the tarsal plate with time; however, many sufferers have had the silicone implant in position for a variety of years with out complications. The 1 mm silicone rod is much like the rods used in frontalis suspension for ptosis. The curved Keith needle is handed as near the lid margin as potential (ideally, 2 to 3 mm). A slight to moderate ptosis should be created, as a end result of 1 to 2 mm of ptosis is required in the final end result to give enough protection. Closure is made in layers to hold the silicone deep to the orbicularis so that the lids abut the globe. C and D, After placement of an Arion silicone rod within the upper lid, as described in text. Subcutaneous migration of the rod can happen in the medial area if the rod is simply too superficial nasally or not well behind the medial limb of the medial palpebral tendon. Undercorrection is commonest and happens because of failure to Chapter 31 � Facial Nerve Palsy 931 apply enough pressure to the silicone rod. Gold Weight Implant (Lid-Loading) this system is extra in style than the silicone implant because of the convenience of implantation. In the upright position, gravity acts on the gold implant in the upper lid and assists higher lid closure when the levator muscle relaxes. The weight is positioned in the higher lid with the affected person under local anesthesia, sustaining lid motion and patient cooperation. In most circumstances of facial paralysis of long-standing duration (1 yr or more), contraction of the antagonist levator muscle occurs, causing retraction of the higher lid. This situation is almost at all times current, but in some instances it may be masked by brow ptosis or by a beforehand positioned tarsorrhaphy. A common process used is placement of the gold weight on the superior tarsal border in combination with recession of the levator aponeurosis. This has supplied optimal closure with fewer unwanted facet effects than might end result with heavier weights. One approach entails inserting the burden just above the lashes to cut back the quantity of weight wanted and to increase the leverage of closure. Side results of this method, which can occur in some circumstances, are erosion of the higher lid, entropion of the lashes, and an unsightly look. C, Placement of a gold weight connected to the supratarsal edge and the recessed levator aponeurosis. Chapter 31 � Facial Nerve Palsy 933 Lid-loading by insertion of gold weights has been utilized in milder circumstances of lagophthalmos; this not solely reduces corneal drying symptoms but in addition produces a extra aesthetic eyelid movement. This reduces the closure impact on the higher lid and requires a heavier weight than if the load were to be placed within the standard pretarsal position. A direct suprabrowpexy with excision of a strip of skin is the most typical method to right this problem. This is a variation of the method used for Chapter 31 � Facial Nerve Palsy 937 browpexy in sufferers undergoing cosmetic surgery; the distinction is that the forehead is sutured to the galea rather than the frontalis muscle. The technique additionally has the advantage of utilizing the same temporalis muscle phase to attach the fascia strip to the lower face to improve mouth and facial sagging, which is unpleasant and can intrude with eating and talking. The authentic process was thought to restore movement to the eyelids and lower face with mechanical impact of temporalis contracture transmitted through the fascia strips. It may be very possible, however, that a number of the eyelid animation really comes from myoneuritonization of the eyelid muscular tissues from the temporalis muscle itself. E, Attachment of fascia strips to the canthal space and to the reflected temporalis muscle flap. Incisions are also made in the medial canthus for attachment of the fascia strips. The temporalis muscle flap to be elevated is marked on the temporalis fascia and incised with the slicing Bovie and is developed in a downward vector. Autologous fascia lata strips are fashioned and threaded within the submuscular aircraft from the lateral incision to the medial canthal tendon and fixated to the tendon or in the neighborhood of the tendon. The patient may additionally be provided an added good thing about improved mouth and lip function with additional fascia strips to the upper lip and mouth area. Additional strips of fascia lata may be threaded to the nasolabial fold space after which hooked up to the temporalis muscle flap for lip elevation and motion, or just attached to the zygoma as a static sling for the lip and mouth. I, Fascia strips in place, and upper and lower lids with fascia tab to be sutured to the temporalis muscle. B, Closeup view exhibiting fascia strip attachment to the upper lip through an incision within the nasolabial crease. B, Same patient after placement of a fascia strip to the eyelids and the left higher lip with temporalis muscle attachment. C, Increased tone in the lids is obvious on repose after insertion of fascia strips with eyelids connected to the temporalis muscle. D, the patient shows clenching of the jaw with improved closure of eyelids from temporalis muscle contracture. B, the patient in repose after fascia strips to the higher and lower lid are connected to the temporalis muscle. C, the patient exhibits eyelid closure with contracture of the temporalis muscle with jaw clenching. Myoneurotization Flaps of adjoining muscles of mastication (temporalis) can reinnervate the facial muscles; nonetheless, the innervation is anomalous and contraction only takes place with chewing actions. Attachment of the temporalis muscle to the eyelids together with fascia strips to the decrease face has been performed. Even a purely static facial sling with fascia lata may be useful for the decrease face in extreme circumstances. If the facial muscle tissue have atrophied after extended denervation time, neurotized gracilis muscle transplantation in conjunction with a sural nerve cross-facial graft can restore some innervation or tone. The results of these procedures are unpredictable, and it may take so long as three to 4 years to produce any discernable outcomes. However, it has much much less of an effect on the eyelids and causes a useful deficit in the use of the tongue with hemiglossal atrophy. Splitting the hypoglossal nerve by no more than 40% minimizes the quantity of resulting motor deficit to the tongue whereas offering adequate reinnervation to the facial nerve. For sufferers with extended denervation time (greater than 6 months), a partial hypoglossal to facial nerve anastomosis can "babysit" the facial nerve to forestall atrophy and lack of motor endplates while axonal development from cross-facial nerve grafting is accomplished. Use of the masseter nerve also avoids functional deficits and atrophy of the tongue. Compensatory eyeLid sUrgery Reinnervation procedures give hope for the longer term within the rehabilitation of sufferers with facial paralysis. As a practical matter, nevertheless, the eyelids appear notably unresponsive, and most sufferers in the end undergo eyelid procedures to assist improve eyelid closure or position. Compensatory eyelid surgery entails three areas: the lower lid, higher lid, and eyebrow.
Syndromes
- Ulcerative colitis
- Treat high blood sugar aggressively with diet, medications taken by mouth, or insulin.
- Meglitinides
- Persistent, unexplained fever
- Cobra
- Dry skin and mucus membranes
- Hay fever or other allergies
- Hepatitis
- Bleeding or rupture of cysts
Related Products
Additional information:
Usage: p.o.
Tags: order aceon 4 mg without a prescription, order 4 mg aceon, order aceon 2 mg on line, buy aceon 8 mg lowest price, order aceon 4 mg on-line, buy 8 mg aceon visa, aceon 8 mg order, aceon 4 mg cheap without a prescription, purchase aceon 4 mg overnight delivery, order 8 mg aceon amex, aceon 2 mg without a prescription, discount 8 mg aceon with amex, 2 mg aceon generic with mastercard, purchase 2 mg aceon with visa, safe aceon 8 mg, cheap aceon 8 mg mastercard
8 of 10
Votes: 327 votes
Total customer reviews: 327
Customer Reviews
Killian, 30 years: If the brow-lash distance is less than 5 mm in men, the presence of eyebrow and brow ptosis must be assessed more intently. Several circumstances of tumorlike amyloidosis associated with Bence Jones proteinuria and different laboratory parameters of plasma cell dyscrasias have been described. B, the higher lid was discovered at the scene of the accident; it was placed in a saline and antibiotic resolution and was sent with the patient. C and D, Low energy photomicrograph showing microscopic features of metastatic rhabdomyosarcoma infiltrating fatty marrow.
Aila, 63 years: C, Despite superficial radiotherapy, the lesion progressed and required exenteration that included the eyelids and globe however spared the muscle tissue. Another benefit of ultrasound-based therapy is the associated visualization of blood vessels earlier than the supply of vitality, which limits vessel trauma and potential bruising. Transposition Flaps Single Z-plasty Transposition Single Z-plasty transposition may be useful in folds which might be less severe and span the vertical or greater a half of the eyelid. Blocking the sphenopalatine ganglion will tremendously diminish tear production however not eliminate it totally.