
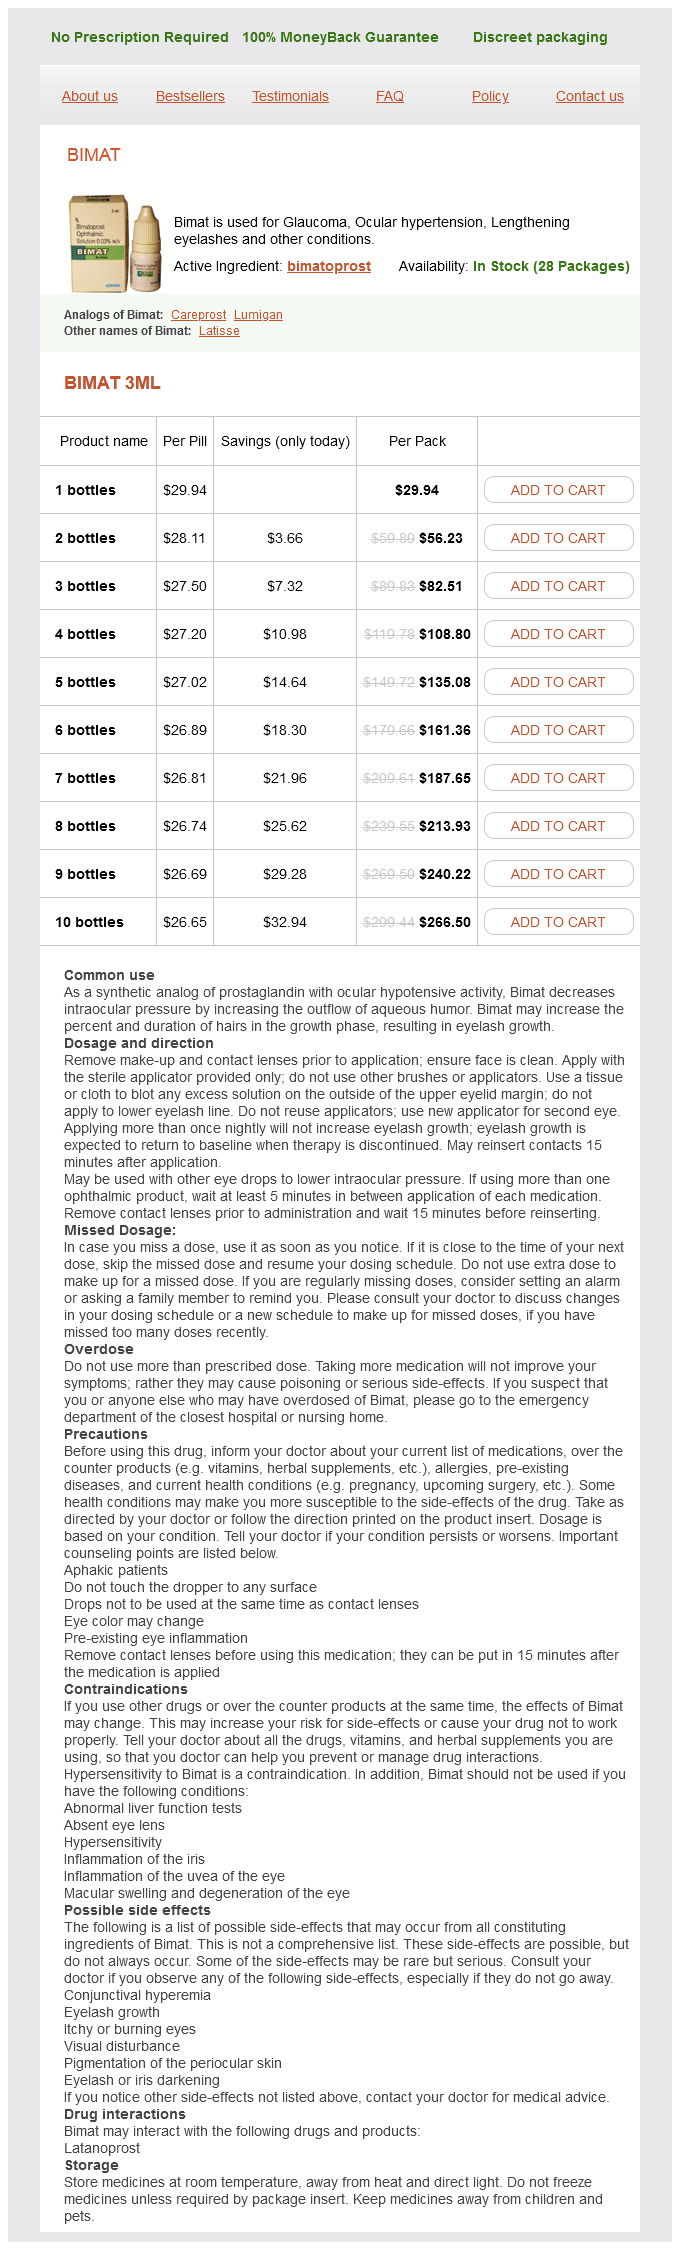
Bimat
Bimat 3ml
- 1 bottles - $29.94
- 2 bottles - $56.23
- 3 bottles - $82.51
- 4 bottles - $108.80
- 5 bottles - $135.08
- 6 bottles - $161.36
- 7 bottles - $187.65
- 8 bottles - $213.93
- 9 bottles - $240.22
- 10 bottles - $266.50
Bimat dosages: 3 ml
Bimat packs: 1 bottles, 2 bottles, 3 bottles, 4 bottles, 5 bottles, 6 bottles, 7 bottles, 8 bottles, 9 bottles, 10 bottles
In stock: 684
Only $28,32 per item
Description
Additional sutures are placed to stop angulation of the anastomosis or herniation via the mesocolon shinee symptoms 3 ml bimat buy visa. Laparoscopic lateral pancreaticojejunostomy was first described in the late 1990s treatment ulcer 3 ml bimat order amex. One prospective study evaluating 7 robotic lateral pancreaticojejunostomy to 19 open circumstances demonstrated that robotic cases and comparable morbidity and reduced median hospital stay by 2 days medicine number lookup bimat 3 ml cheap mastercard. Lateral pancreaticojejunostomy is mostly profitable in appropriately chosen patients with dilated main pancreatic duct and lack of an inflammatory mass within the head of the pancreas medications causing dry mouth safe 3 ml bimat. In most series, up to 90% of sufferers have instant ache reduction after recovering from the surgery, and about 60%�80% have a long-term pain aid. Stones impacted in the head of the pancreas may be addressed by intraoperative electrohydraulic lithotripsy and ductoscopy utilizing a flexible choledochoscope down the pancreatic duct across the ampulla. Islet auto-transplantation Endoscopic and surgical administration of continual pancreatitis 43 Dominant head mass Resection of the pancreatic head could additionally be indicated for sufferers with continual pancreatitis associated with a dominant inflammatory mass in the head of the pancreas, with or with out intensive calcifications or duct stones. Pancreatic head resection may or might not embrace resection of the duodenum and can be combined with extended lateral pancreatic duct drainage procedure. The commonest choices embody pancreaticoduodenectomy (with or without pylorus preservation), Beger procedure (or associated Berne modification), and the Frey process. Occasionally, pancreaticoduodenectomy can additionally be appropriate for intrapancreatic bile duct stricture with evidence of biliary obstruction, or for suspicion of malignancy. Access is often gained by way of midline laparotomy or bilateral subcostal incisions. A thorough examination of the peritoneum and surface of the liver must be carried out firstly of the operation, with biopsy and frozen-section evaluation of any suspicious lesions. The base of the transverse mesocolon and ligament of Treitz is inspected for fibro-inflammatory contracture or tumor involvement. The hepatic flexure of the colon is mobilized, and an extended Kocher maneuver is performed. The head of the pancreas and related mass are palpated to decide their relation to surrounding vessels and feasibility of a secure resection. Cholecystectomy is carried out and the frequent bile duct is isolated from the anteromedial facet portal vein. The widespread hepatic artery is recognized, normally on the anteriorlateral aspect of the portal vein. The gastrohepatic ligament is inspected for the presence of an adjunct or replaced proper hepatic artery, and, if present, is isolated and guarded. Extensive peripancreatic inflammation may render definition of this retropancreatic venous "tunnel" difficult or dangerous. Extensive distortion of tissue planes or encasement of vessels could preclude protected resection once in a while, although typically the question of resectability for inflammatory pancreatic head plenty may be answered with cheap certainty based mostly on preoperative imaging. Following profitable definition of the retropancreatic tunnel, resection can proceed. The widespread bile duct is controlled proximally with a bulldog clamp after which divided. A 5 French pediatric feeding tube can be utilized as a pancreatic duct stent when closing a two-layered end-to-side pancreaticojejunostomy. Reprinted with permission from Ahmad Syed A, Wray Curtis J, Rilo Horacio R, et al. Nonreplacement therapy of persistent pancreatitis In a normal pancreaticoduodenectomy, the larger omentum is split up to the greater curvature of the stomach at roughly the junction of the right and left gastroepiploic arcades. The lesser omentum is divided simply proximal to the incisura angularis, controlling the anterior and posterior branches of the vagus nerve, and associated left gastric arterial branches. The stomach is then divided at the stage of the incisura of the lesser curvature with two firings of a linear gastrointestinal stapler. For pylorus preservation, the duodenum is split a minimum of two cm distal to the pyloric ring. The ligament of Treitz is then taken down, protecting the inferior mesenteric vein, and the proximal jejunum is divided with a linear stapler at a suitably lax vascular arcade sometimes about 15�20 cm distal to the ligament of Treitz. The mesojejunal vessels of the proximal jejunum are fastidiously divided until the dissection reaches the duodenojejunal junction. The proximal jejunum is then passed posteriorly behind the superior mesenteric vessels into the supracolic compartment. Hemostatic stay sutures are placed on either facet of the transection line of the neck at both the superior and inferior border of the pancreas. As the pinnacle is gently retracted, the small venous tributaries from the uncinate process are ligated together with the inferior pancreaticoduodenal artery and small branches of the superior mesenteric artery. The transected jejunum is advanced via the transverse mesocolon through both side of the middle colic vessels. A two-layer anastomosis is mostly preferred, and quite lots of methods have been described. One such technique involves an outer layer of interrupted or continuous seromuscular jejunal sutures to the pancreatic capsule and an inner layer of interrupted duct-to-mucosa sutures from pancreatic duct to a small enterotomy within the antimesenteric side of the jejunum. Ten to twenty centimeters distal to the pancreaticojejunostomy, an endto-side choledochojejunostomy is constructed utilizing a duct-to-mucosa approach. The jejunal limb is secured to the transverse mesocolon are closed to prevent herniation. An antecolic loop two-layer end-to-side gastrojejunostomy is then constructed so that the afferent limb of the jejunum is toward the lesser curvature and the efferent limb is toward the higher curvature. Alternatively, an end-to-side duodenojejunostomy is used for pyloricpreserving procedures. Beger procedure and Berne modification Pancreatic head resection with preservation of the duodenum is possible in sufferers with a dominant inflammatory pancreatic head mass with out suspicion of malignancy and may have advantages of preserving gastroduodenojejunal continuity with respect to luminal mixing, digestive effectivity, and postprandial metabolic response. This operation was developed by Beger within the 1970s with the assumption that preserving the duodenum may spare patients of some of the digestive sequelae of pancreaticoduodenectomy such as delayed gastric emptying. The lesser sac is entered via the gastrocolic ligament, the transverse mesocolon is mobilized from the top and decrease border of the pancreas, and the duodenum and pancreatic head are elevated by way of a Kocher maneuver. The inflammatory head mass is then cored out utilizing electrocautery, leaving a small rim of pancreas connected to the duodenum and around the bile duct. The specimen is submitted to pathology for frozen section evaluation to exclude malignancy. A duct-to-mucosa pancreaticojejunostomy is constructed using a two-layered handsewn approach at the neck margin to the top of the jejunum. A lengthy enterotomy is made on the facet of the jejunum contralateral to the primary anastomosis. The pancreatic margin is then sewn to the enterotomy to assemble a second pancreaticojejunostomy. If the distal widespread bile duct is inadvertently entered during excavation of the pancreatic head, it might be unroofed and allowed to drain laterally into this second anastomosis. The Berne modification was developed to avoid complete division of the pancreatic neck anterior to the portal vein. For sufferers with fibroinflammatory pancreatic head mass related to a large duct disease as a end result of pancreatic duct stricture and intraductal stones, a combined resection and drainage process developed by Frey may be applicable. This approach combines duodenumpreserving pancreatic head resection with longitudinal pancreaticojejunostomy. In this process, the pancreas is totally uncovered alongside its length from head (via Kocher maneuver) to tail (via prolonged opening of the lesser sac). The preliminary steps to excavate the pancreatic head are carried out just like the Beger and Berne procedures, typically including cholecystectomy and cannulation of the cystic duct. After excavation of the pancreatic head, the main pancreatic duct is unroofed longitudinally to the tail utilizing electrocautery. Izbicki and colleagues described a associated approach typically termed the Hamburg procedure to deal with patients with an inflammatory head mass with intensive small duct fibroinflammatory illness (<3 mm) in the body and tail of the pancreas. In this operation, the body and tail are unroofed by a V-shaped wedge after which enterically drained via lateral pancreaticojejunostomy as in the Frey procedure. Results of medical trials There have been a quantity of small randomized management trials from Europe which have compared these strategies. One research in contrast 20 sufferers handled with the Beger process to 20 patients handled with pylorus preserving pancreaticoduodenectomy. The solely difference in quality of life measurements was a better incidence of appetite loss after pancreaticoduodenectomy. Nonreplacement therapy of continual pancreatitis evaluate of studies comparing the Beger procedure to pancreaticoduodenectomy concluded that size of keep may be shorter in for patients handled with the Beger procedure, however the total quality of the evidence is insufficient to detect significant variations in mortality, antagonistic events, or quality of life. The study in contrast 31 sufferers treated by Frey process and 30 sufferers by pancreaticoduodenectomy with 7-year follow-up.
Anurine (Thiamine (Vitamin B1)). Bimat.
- How does Thiamine (vitamin B1) work?
- Poor appetite, ulcerative colitis (UC), chronic diarrhea, stomach problems, brain conditions, AIDS, heart disease, alcoholism, stress, aging, canker sores, improving athletic performance, preventing cervical cancer, and other conditions.
- What other names is Thiamine (vitamin B1) known by?
- Kidney disease in people with type 2 diabetes.
- Treatment and prevention of thiamine deficiency, including a specific thiamine deficiency disorder called Wernicke-Korsakoff syndrome.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96927
Advances in micro and nano-fabrication symptoms 6dpo bimat 3 ml purchase free shipping, materials science and membrane development have the potential to enhance macroencapsulation medications made from plants generic bimat 3 ml otc. Additionally treatment wetlands 3 ml bimat generic overnight delivery, improvements in engineering physiologically related tissue microenvironment and the event of a renewable medications canada bimat 3 ml order with mastercard, different insulin-producing cell supply could additional move the sector ahead. Given their promising potential, future improvement of successful macroencapsulation gadgets will be contingent upon synergistically leveraging applied sciences from the fields of genetic and bioengineering, materials science, and nanotechnology. Phase 3 trial of transplantation of human islets in Type 1 diabetes difficult by extreme hypoglycemia. A selective lower within the beta cell mass of human islets transplanted into diabetic nude mice. Bioengineering and regeneration of the endocrine pancreas References 343 within the bioartificial pancreas Air to sufferers with sort 1 diabetes mellitus. An Open Label, Pilot Investigation, to Assess the Safety and Efficacy of Transplantation of Macro-Encapsulated Human Islets within the Bioartificial Pancreas Beta-Air in Patients with Type 1 Diabetes Mellitus (ClinicalTrials. Subcutaneous medical islet transplantation in a prevascularized subcutaneous pouch- preliminary experience. Islet cell transplantation for the remedy of kind 1 diabetes: Recent advances and future challenges. Cell encapsulation: overcoming obstacles in cell transplantation in diabetes and past. Pancreas progenitors the fetal and grownup biliary tree included both stem cells and committed pancreatic progenitors. The pancreas itself contains a minimal of three classes of cells which will act as a supply of new cells: remnant cells, non-endocrine cells (acinar/ductal; via reprogramming), and progenitor cells (differentiation via mature fates). It must be famous that the cell reprogramming can be termed transdifferentiation, and is as a phenotypic conversion of cells of one tissue into cells of another via ectopic expression of specific transcription factors. Substantial regeneration of each the endocrine and exocrine pancreas happens after a 90% partial pancreatectomy within the young adult rat; in this situation the replication of preexisting islets and exocrine cells is enhanced three to fourfold. Indeed, while a constant islet cell proliferation happens after birth, this turnover turns into slow in maturity. Pancreatic tissue homeostasis and the response to minor injuries have achieved by the proliferation of preexisting cells of the identical lineage. The existence and distribution of the pancreatic progenitors, notably in people, raised the open question about an upstream contribution of multipotent populations of stem/progenitor cells to the -cells pool participating to ongoing regeneration in adulthood. Interestingly, proliferation was seen first in the frequent pancreatic duct and sequentially in smaller ducts of the ductal tree. These small ductules differentiate into new pancreatic islets and exocrine tissue, forming new lobules of pancreas which are indistinguishable from the preexisting ones. This second pathway of rapid regeneration recapitulates embryonic improvement, in its pattern of ductal proliferation and subsequent differentiation. Thus, these studies provide proof of the presence of precursor/stem cells in the grownup pancreas. These results advised that terminally differentiated cells retain a significant proliferative capability in vivo. Although -cell mass is extremely variable between individuals, the -cell mass expands by a number of fold from start to adulthood, rising in dimension somewhat than in quantity during this transition. These knowledge suggest that the regulation of -cell replication throughout infancy plays a serious position in -cell mass in adult humans. The most characterised technique developed to increase human islet cells (specifically cells), which have been dissociated from islets into single cells, is predicated on culturing strategy which culminate right into a process of dedifferentiation. Thereafter, expanded dedifferentiated cells are redifferentiated in tradition with components which recapitulate the traditional embryological improvement and differentiation of cells, corresponding to activin A, exendin-4, nicotinamide, and excessive glucose concentrations. Indeed, in response to pathological situations, buildings with heterogeneous ductal phenotypes increase within the pancreas. In the mannequin 1, cells outside the basement membrane of the duct epithelium proliferate, differentiate, and coalesce to type the islet. However, ultrastructural analysis, in each embryonic and postnatal pancreas, which showed hormone-positive cells within the basement membrane/lamina of the ductal epithelium, and subsequent lineage-tracing studies, dominated out this model for the bulk of recent islet formation. In Model 2, progenitor cells inside the epithelium, proliferate, delaminate from the epithelium with transforming of the plasma membrane, and coalesce into islets. Model 2 is unlikely in the pancreatic regeneration after partial pancreatectomy (Px), although this mannequin might theoretically occur in some situations, especially the more difficult ones due to the advanced stage of the illness state. In Model 3 (transdifferentiation), through cell replication the ductal epithelial cells regress to a much less differentiated stage and may then perform as progenitor cells, which reply to native stimuli to differentiate into islet cells. The authors instructed that these biliary bushes derived stem cells and their community contribute to pancreatic progenitor cells structure in the pancreas. Pancreas progenitors the position of pancreatic acinar cells the flexibility of the pancreatic acinar cells to give rise to liver52 and ductal cells53 demonstrated their excessive plasticity. This observation highlighted a time extra how -cell communication is important to stimulate glucose-mediated insulin secretion. Indeed, the transient administration of epidermal progress issue and ciliary neurotrophic issue to adult mice with chronic hyperglycemia efficiently stimulated the conversion of terminally differentiated acinar cells to -like cells. Newly generated -like cells resulted epigenetically reprogrammed, useful and glucose responsive, and they reinstate regular glycemic management for as a lot as 248 days. The regenerative course of relied on Stat3 signaling and required a threshold variety of Neurogenin 3 (Ngn3)expressing acinar cells. However, the variety of insulin-positive cells increased solely within the exocrine cells grown initially in suspension earlier than 3D tradition. Long-term engraftment into immunocompromised mice increased the efficiency of reprogramming to insulinpositive cells. These information demonstrated that exocrine cells from human pancreas can be reprogrammed to transplantable insulin-producing cells that purchase functionality. Its rostral half comprises the endodermal tissue which will give rise to liver and the common hepatic duct. The caudal part of the hepatic diverticulum, linked to the foregut, gives rise to the extrahepatic biliary tree and ventral pancreas. The panel highlights the distribution, location, and composition of stem/progenitor cell niches within the biliary tree, liver, and pancreas under regular situations. Dorsal and ventral pancreatic primordia derive from Pdx1+/Ptf1a+ pancreatic stem/progenitors. Tip progenitors on the ends of tubules (Ptf1a+, Hes1+, Gata4+, and Sox9+) subsequently commit to exocrine lineages and differentiate into acinar and ductal cells. In the central duct area, Ngn3+ trunk progenitors decide to islet endocrine fates. Pancreas progenitors injuries, whereas the replication of mature parenchymal cells ensures physiological turnover and restoration of parenchyma after minor injuries. Although some stories claim the existence of multipotent stem cells throughout the pancreas,25, 26 most recommend that these cells are rare or absent within the postnatal pancreas. A massive physique of work suggests that in maturity new pancreatic cells come up primarily from preexisting cells of the identical lineage. In rodent fashions, lineage-tracing studies confirmed that preexisting acinar cells give rise to acinar cells however not islets. Bioengineering and regeneration of the endocrine pancreas Pancreatic duct gland because the niche of pancreatic progenitors 353 pancreatitis, presenting traits of mucinous intestinal metaplasia and pancreatic intraepithelial neoplasia. Moreover, upstream maturational occasions could happen in stem/progenitor cell niches of the biliary tree community, and this additionally could end result into architectural modifications that would precede pancreatic transforming. Also at this degree the percentage of the duct space (area fraction) maintained stability with respect to the principle pancreatic duct. Notably, cells within intercalated but not in intralobular ducts have been diffusely constructive for Sox9. Accordingly, centroacinar cells (the terminal-end duct cells interfacing with acini) had been optimistic for Sox9, Pdx1, and Ngn3. Nevertheless, intercalated ducts have been observed in direct continuity with clusters of insulin+ cells organized in small pancreatic islet-like constructions. Moreover, with transitioning from ducts to islets, cells lost nuclear Sox9 positivity. In the development of the pancreas, the expression of Sox9 is essential for the upkeep of the pancreatic progenitor cell pool and has a key function in controlling the bipotential (ductal and endocrine) progenitor cell inhabitants.
Specifications/Details
Islet auto-transplantation Endoscopic and surgical administration of persistent pancreatitis 39 is technically challenging and extra investigation is required previous to medications not to crush bimat 3 ml generic with amex widespread implementation medicine man bimat 3 ml buy cheap on line. Morbidity associated to pancreatic stent placement contains acute pancreatitis treatment locator 3 ml bimat purchase amex, pancreatic infection symptoms you have diabetes bimat 3 ml safe, pseudocyst formation, duct damage, stone formation, and migration. Patients must be recommended on these risks, as properly as the probably want multiple procedures. There have been several revealed collection documenting the outcomes of endotherapy for pancreatic duct strictures. Immediate relief from painful attacks has been documented in 88%�94% of patients, and longterm pain relief has been achieved in 54%�70% of patients19, 33�38 (Table 2). Some of these research additionally reported on decreased oral narcotic use and hospital readmission, in addition to increased weight gain after stent placement. The pancreatic duct downstream of stones can turn into more and more dilated, cause elevated intraductal pressure leading to ductal disruption and improvement of pseudocysts, ascites, and pleural effusions. The elevated pancreatic duct strain downstream of obstructing stones with or without strictures can also be theorized to contribute to the multifactorial etiology of ache in persistent pancreatitis. This is supported by studies demonstrating that elimination of the stones can enhance the outflow of pancreatic enzyme secretions, decrease intraductal pressure, and enhance pain management. However, greater than half of stones are unamenable to routine endoscopic extraction alone and both require fragmentation or surgery. In instances of pancreas divisum or continual pancreatitis induced pseudo-divisum, a minor papilla sphincterotomy would be required for stone extraction. In instances of sigmoid shaped or looped pancreatic ducts, baskets, and single-operator cholangioscopes are technically challenging to advance safely and require preparation for various approaches. In the circumstances of larger or impacted stones, endoscopic mechanical or probe-based (electrohydraulic or laser) lithotripsy may be attempted. Mechanical and probebased lithotripsy is technically more difficult to perform successfully in pancreatic stones compared to bile duct stones, and are associated with one-third greater number of issues. This procedure uses electromagnetic shock waves to fragment calculi to less than 3 mm. Management of benign biliary strictures Biliary strictures could develop in 3%�46% of sufferers with advanced persistent pancreatitis. The present normal of endoscopic therapy for benign biliary strictures is the location of a number of, sideby-side plastic biliary stents, growing in number or size with exchanges roughly every three months over a 12-month period. Temporary, multiple plastic stent placement is technically profitable in higher than 90% of patients with long-term success rates have been reported to be 62% in patients with simultaneous, multiple plastic stents vs 32% in sufferers with single plastic stents. Surgical administration of continual pancreatitis Most sufferers with chronic pancreatitis should initially be handled medically for pain management and symptomatic relief of exocrine and endocrine insufficiency. A subset of these sufferers the place pain is associated with pancreatic duct obstruction by stone or stricture may amenable to endotherapy. Islet auto-transplantation Endoscopic and surgical management of persistent pancreatitis 41 for endotherapy may be eligible for surgical intervention, and there are scattered sequence of assorted quality that compare these approaches. Other sufferers require surgical resection and/or drainage for biliary stricture, duodenal stenosis, pseudocyst, or suspected neoplasm. The major objectives of surgical procedure are the relief of pain and preservation of as much residual exocrine and endocrine perform as attainable. There are two prospective, randomized research comparing endoscopic remedy to surgical administration of large-duct illness (Table 3). There was also a considerably larger proportion of sufferers that gained weight within the surgical group compared to the endoscopic group (47% vs 29%). While these research have limitations, they do present proof that surgical therapy supplies more durable pain relief for sufferers with large-duct chronic pancreatitis. The timing of surgical procedure for persistent pancreatitis stays an essential but unanswered medical question. A latest metaanalysis instructed that early surgical procedure, normally outlined as inside 3 years of onset of signs, is associated with increased opportunity for full postoperative ache reduction in addition to reduced risk of pancreatic insufficiency and lower charges of re-intervention. The risk of intraoperative and postoperative complications is appreciable and includes danger of hemorrhage, an infection, anastomotic leakage, and fistula formation. Many patients with continual pancreatitis have important protein-calorie malnutrition and vitamin deficiencies that increase the risk of postoperative morbidity and mortality. A preoperative effort period of nutritional repletion together with counselling, dietary supplementation, and pancreatic enzyme therapy may help improve a preoperative standing prior to surgical procedure. In addition, the involvement of a specialized pain administration team might assist optimize a postoperative ache control. High charges of readmission are reported after surgery for chronic pancreatitis, and the majority of readmissions are for ache administration. Large duct disease "Large duct illness" refers to persistent pancreatitis related to dilation of the principle pancreatic duct to no less than 7 mm. Such patients may be candidates for inside drainage of the dilated duct, normally right into a defunctionalized (Roux-en-Y) jejunal limb. Nonreplacement remedy of chronic pancreatitis and stones resulting from stasis and precipitation of calcium carbonate, polysaccharides, and proteins. Puestow was the first to describe a lateral pancreaticojejunostomy in addition to the distal pancreatectomy and splenectomy to drain a dilated pancreatic duct. Roux-en-Y lateral pancreaticojejunostomy (Puestow procedure) Exposure for the Puestow process is often by way of midline laparotomy. The peritoneal lining laterally adjoining to the second portion of the duodenum is incised, together with the hepatic flexure of the proper colon. The Kocher maneuver mobilizes the pinnacle of the pancreas by creating the retroperitoneal aircraft alongside the lateral and posterior borders of the duodenum with electrocautery and blunt dissection. The third portion of the duodenum is free of the base of the transverse mesocolon. The anterior portion of the pancreas is examined to verify the absence of dominant mass lesions suspicious for malignant transformation, utilizing biopsy and frozen part analysis as appropriate. A dilated primary duct can typically be identified by palpation via the anterior floor of the pancreatic body the place it can be easily confirmed by a fine-needle aspiration. Intraoperative ultrasound may also be used to find the dilated main pancreatic duct. To assemble a Roux jejunal conduit, the jejunum is split with a linear secure about 15�30 cm from the ligament of Treitz at a handy mesojejunal arcade. A minimal of 50 cm downstream from the divided jejunum, intestinal continuity is established with a side-to-side jejunojejunostomy using both a handsewn or stapled technique. The Roux limb is brought by way of the transverse mesocolon usually to the left of the middle colic vessels. The limb ought to enable for at least 40 cm of defunctionalized intestinal length between the pancreatic anastomosis and jejunojejunostomy to forestall reflux of enteric contents to the pancreatic duct. A lateral jejunostomy is then created along the antimesenteric border and carefully prolonged to match the length of the pancreatic ductotomy. The anastomosis between the jejunostomy and pancreas is sutured with a running absorbable suture with full-thickness bites by way of the jejunum and partial thickness bites through the pancreatic capsule and fibrotic pancreas, extending to the pancreatic duct epithelium as potential. Because the medical trials carried out to date are small and highly variable with respect to design, surgical approach, inclusion standards, and endpoints, no skilled consensus has but emerged. In general, the selection of operation should continue to use preoperative imaging to outline the anatomic circumstances. Patients with a dominant fibroinflammatory head mass with out primary pancreatic duct dilatation or biliary obstruction and no suspicion of malignancy are candidates for either pancreaticoduodenectomy or duodenum-preserving pancreatic head resection by the Beger process or Berne modification. For sufferers with a dominant head mass and a dilated main pancreatic duct, pancreaticoduodenectomy or Frey process are cheap choices. Although some patients obtain a long-term pain aid and sustained enchancment in high quality of life, the result of traditional surgical approaches to continual pancreatitis also remains variable, unpredictable, and infrequently suboptimal. The scientific and radiological traits of focal mass-forming autoimmune pancreatitis: comparability with continual pancreatitis and pancreatic most cancers. Prospective analysis of the diagnostic accuracy of secretin-enhanced magnetic resonance cholangiopancreaticography in suspected persistent pancreatitis. Effect of cessation of alcohol use on the course of pancreatic dysfunction in alcoholic pancreatitis. Beyond stomach ache: ache beliefs, ache affect, and distress as determinants of high quality of life in sufferers with persistent pancreatitis. Ameliorating impact of antioxidants and pregabalin combination in pain recurrence after ductal clearance in persistent pancreatitis: outcomes of a randomized, double blind, placebo-controlled trial. Conclusion Chronic pancreatitis is a progressive fibroinflammatory course of usually associated with persistent pain that leads inexorably to exocrine and endocrine insufficiency. A multidisciplinary strategy and early diagnosis are key to efficient and sturdy remedy outcomes.
Syndromes
- Swollen glands
- Damage to nearby organs in the body
- What do you do during the few hours before you go to bed?
- Angioplasty and stent placement (also called percutaneous coronary intervention)
- Between their late 20s and late 40s
- Erythrocyte sedimentation rate (ESR)
- Liver tumor
- Acute unilateral obstructive uropathy
Related Products
Additional information:
Usage: q.h.
Tags: generic 3 ml bimat with amex, buy cheap bimat 3 ml line, bimat 3 ml discount online, bimat 3 ml online, generic bimat 3 ml free shipping, cheap 3 ml bimat with mastercard, 3 ml bimat for sale, bimat 3 ml cheap online, bimat 3 ml cheap with visa, cheap bimat 3 ml with visa, 3 ml bimat order with visa, 3 ml bimat, 3 ml bimat with amex, cheap bimat 3 ml overnight delivery, purchase bimat 3 ml with mastercard, bimat 3 ml discount mastercard
9 of 10
Votes: 294 votes
Total customer reviews: 294
Customer Reviews
Rune, 59 years: However, if a Roux-en Y anastomosis was performed this can be considerably tougher. Insulin-secreting cells derived from embryonic stem cells normalize glycemia in streptozotocin-induced diabetic mice. There are three sets of tonsils: A single pharyngeal tonsil (also called adenoids) sits on the wall of the pharynx, simply behind the nasal cavity. The above blots are a consultant image taken from two independent experiments (n = 2).
Steve, 29 years: Intercellular Ca2 + waves sustain coordinate insulin secretion in pig islets of Langerhans. The iliac regions lie within the lower portion of the abdomen, to the best and the left of the hypogastric area. The uterus sits between the urinary bladder and the rectum, held in place by the broad ligament. Local immunomodulation with Fas ligand-engineered biomaterials achieves allogeneic islet graft acceptance.
Asam, 50 years: The chart beside it lists some (but not all) of the organs present in each quadrant. Blastocyst complementation was first tested between cells and embryos of a single species, Mus musculus. However, because of the mutation, the switch is impaired; this causes exocrine cells to secrete profuse quantities of thick, sticky mucus. Islet autotransplantation to forestall diabetes after pancreatectomy for benign disease of the pancreas.
Bufford, 52 years: Placenta and Umbilical Cord About 11 days after conception, the embryo develops a disc-shaped, pancake-like organ referred to as the placenta. Based on their assembly pathways, pili of gram-negative micro organism are divided into four groups. The dubious worth of cerebrospinal fluid adenosine deaminase measurement for the prognosis of tuberculous meningitis. In sufferers with persistent pancreatitis and cholelithiasis, signs in a single study reflected complications that resulted from cholelithiasis: jaundice, diarrhea, and abdominal ache, to name a number of.
Tangach, 30 years: Called edema, this accumulation of fluid appears as swelling within the ankles, fingers, stomach, or face. Tiamides: Ethionamide (Eto), protionamide (Pto) Bactericidal or bacteriostatic relying on susceptibility and concentrations attained at infection website. Such a -cell replacement gadget should result in improved islet viability, and subsequently a reduction within the quantity of donor organs needed for transplantation. A surface-associated trypsin-activated Giardia lectin (taglin) could additionally be necessary for G.