
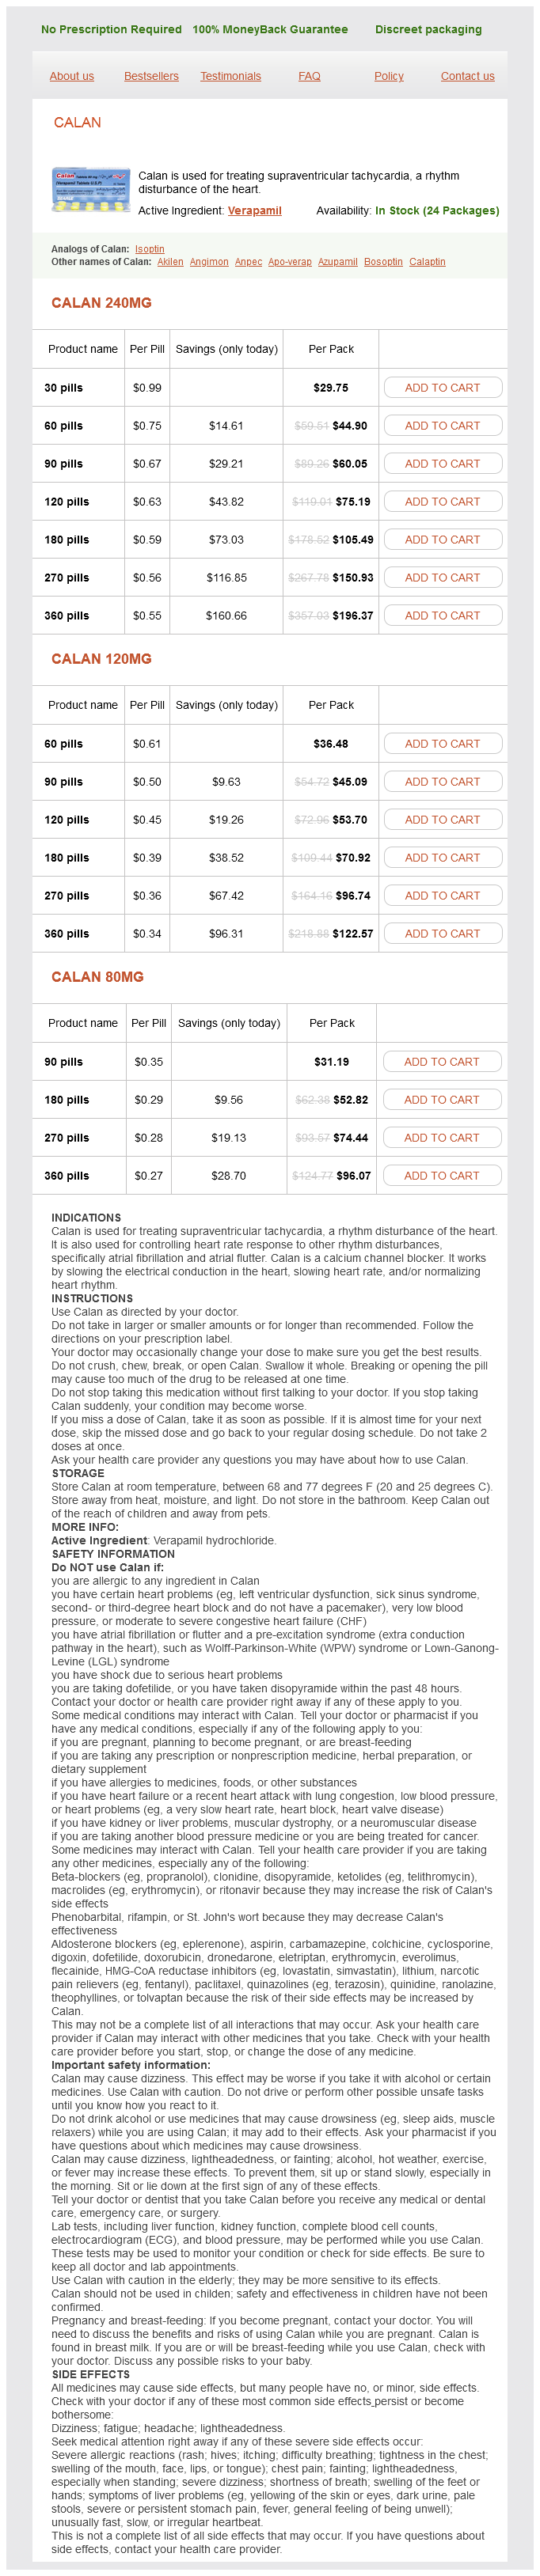
Calan
Calan 240mg
- 30 pills - $29.75
- 60 pills - $44.90
- 90 pills - $60.05
- 120 pills - $75.19
- 180 pills - $105.49
- 270 pills - $150.93
- 360 pills - $196.37
Calan 120mg
- 60 pills - $36.48
- 90 pills - $45.09
- 120 pills - $53.70
- 180 pills - $70.92
- 270 pills - $96.74
- 360 pills - $122.57
Calan 80mg
- 90 pills - $31.19
- 180 pills - $52.82
- 270 pills - $74.44
- 360 pills - $96.07
Calan dosages: 240 mg, 120 mg, 80 mg
Calan packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 968
Only $0,28 per item
Description
At this point blood pressure quitting drinking discount calan 80 mg without a prescription, the ventilator can be turned off - arrhythmia 240 mg calan cheap fast delivery, besides in circumstances the place the lungs are procured prehypertension causes calan 120 mg generic visa. A complete midline incision blood pressure by age chart discount 120 mg calan fast delivery, from suprasternal notch to pubis, is made for multiple organ procurement; and the sternum is break up. If necessary, cruciate abdominal incisions are added to facilitate exposure of the intraabdominal organs. After elimination of the guts and/or lungs, the liver could be removed, adopted by the pancreas, small intestines, and kidneys. After the organs are eliminated, spleen and lymph nodes for tissue typing are obtained from the stomach and thoracic cavities; and due to the potential need for vascular reconstruction within the recipients, bilateral iliac veins and arteries are removed. The total time for multiorgan procurement is ~4 h, although the anesthesia time sometimes ends with aortic crossclamping. Variant procedures: During the "rapid-flush" technique used by some procurement teams, the dissection of individual belly organs is minimized and an en bloc resection is completed after clamping the aorta below the diaphragm and flushing preservation solution by way of the distal aorta. The en bloc organs are then dissected ex vivo, usually on the transplant heart, in preparation for transplantation. A second variant process, developed in response to the chronic shortage of transplantable organs, is the use of non-heart-beating donors. Depending on the regional regulations, this cannula may be placed before cardiac death or immediately following the declaration of cardiac demise. After the preservative flush is initiated, the stomach is entered as quickly as potential, the peritoneal cavity is filled with ice, and the organs are removed expeditiously. The drawback of this strategy is that there could be significant warm ischemia from the time the life-sustaining therapy is stopped to the time that cardiac dying is reached. A declaration of mind dying by physicians not participating within the organ procurement should be documented. This documentation, together with certification of dying and familial consent, must be verified by the anesthesiologist earlier than organ procurement. There should be no proof of disease or trauma involving the organs targeted for donation, and normally, the affected person ought to be hemodynamically secure with minimal inotropic requirements. After brain demise has been declared, you will need to shift the emphasis away from cerebral resuscitation efforts and to focus as an alternative on the maintenance of adequate tissue perfusion and oxygenation. Brain demise is frequently adopted by a collection of pathophysiological events that will complicate the management of those sufferers. However, in most establishments, an anesthesiologist is current within the operating room as a member of the latter group webinars. After withdrawal of life help has been initiated and the patient meets standards for cessation of cardiopulmonary operate, organ removing is initiated as quickly as attainable to limit warm ischemia time and potential injury to the organs to be eliminated. The objectives of intraop administration with regard to respiratory, cardiovascular, hematologic, and neurologic status are identical to these mentioned beneath preop issues earlier. The preliminary evaluation and management consists of the first survey and resuscitation. Breathing and air flow are assessed, paying attention to any chest injuries that can impair enough fuel change. Conditions similar to pressure pneuomothorax, large hemothorax, flail chest, and open pneumothorax ought to be identified and handled. Supplemental oxygen must be delivered and oxygenation must be monitored with pulse oximetry. In trauma, the presence of shock is often as a outcome of hemorrhage, and definitive management of bleeding and substitute of intravascular volume are essential. Patients with severe neurologic damage might require definitive airway management or urgent neurosurgical analysis. Exposure includes undressing the affected person to determine another life-threatening injuries whereas maintaining the patient heat. Airway patency can be compromised by obtundation, severe facial injuries, bleeding or vomiting, or obstruction from neck or airway accidents. The need for air flow or oxygenation is indicated by apnea, respiratory distress, severe closed head damage, or hemodynamic instability. Airway maneuvers such because the chin-lift or jaw-thrust maneuver are helpful methods to enhance airway patency in unconscious or obtunded sufferers, though they must be performed with out extending the neck and probably exacerbating a cervical backbone damage. Oraltracheal intubation, with the usage of applicable neuromuscular blockade and cricoid stress, is the popular approach. The method is fast, however a minimal of three persons are required to carry out it safely within the affected person with suspected C-spine injury. In-line stabilization of the neck is performed to reduce neck and backbone actions. Because a failed intubation may drive operative airway intubation, gear for cricothyrotomy should be instantly accessible. Fiberoptic help and different methods for endotracheal intubation together with video laryngoscopy may be used in the steady affected person with a troublesome airway. Patients in respiratory distress with extreme facial or neck trauma or unstable cervical spine harm require a surgical airway. An airway positioned in transport ought to be immediately assessed for position and adjusted to a definitive airway when appropriate. Nasotracheal intubation, used only in spontaneously respiratory trauma patients, can be carried out with out the utilization of pharmacologic agents or special gear. In the intoxicated affected person with a depressed stage of consciousness, the success rate may be as little as 65%. Blind nasal intubation is contraindicated in patients with unstable midface fractures, penetrating neck trauma, or significant neck hematomas. The essential anatomic landmarks of the superior and inferior borders of the thyroid and cricoid cartilages are palpated. The cricothyroid membrane lies very superficially, lined solely by the skin and platysma muscle. A: Identification of the cricothyroid membrane by palpation and incision of the membrane transversely. A tracheostomy can be achieved through the same incision, prolonged caudally, if laryngeal damage is discovered (see p. In such circumstances, it could be essential to intubate the distal end of the airway via the wound. Right thoracotomy provides entry to the distal intrathoracic trachea (see Chest Trauma, p. For sufferers who reach the hospital, correct management is essential as a outcome of many deaths can be prevented. Early deaths are because of airway obstruction, tension pneumothorax, massive hemothorax, flail chest, cardiac tamponade, and open pneumothorax. The demise price in hospitalized sufferers with isolated chest injury is 4�8%; this will increase to 10�15% when one different organ system is concerned and to 35% if multiple extra organs are injured. Blunt trauma can induce injury by three distinctive mechanisms: direct blow, deceleration damage, and compression injury. Fracture of the upper ribs (1st�3rd), clavicle, or scapula implies high-energy impact and is related to the next probability of major vascular injury. Life-threatening accidents attributable to penetrating trauma are distinctly totally different from those caused by blunt trauma. In penetrating chest accidents, pneumothorax is type of all the time current, and hemothorax is present in 80% of instances. Hemodynamic instability in penetrating chest harm usually heralds a serious intrathoracic vascular harm. Loss of lung quantity on the ipsilateral aspect and subsequent compression of the contralateral side leads to Emergency Tube Thoracostomyimpaired air flow and hypoxia. The presence of respiratory misery and absent or diminished breath sounds warrant quick needle decompression (14�16-ga catheter by way of the 2nd intercostal space, midclavicular line), adopted by subsequent tube thoracostomy. In the hemodynamically secure affected person, nonetheless, suspicion of a pneumothorax must be confirmed by x-ray. A small, simple pneumothorax (< 10%) with no respiratory compromise could additionally be observed.
Xysmalobium undulatum (Uzara). Calan.
- Are there any interactions with medications?
- Are there safety concerns?
- How does Uzara work?
- Dosing considerations for Uzara.
- What is Uzara?
- Diarrhea and other conditions.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96129
The ache must be unresponsive to conservative therapies prehypertension yahoo 240 mg calan purchase with visa, corresponding to rest and oral medicines blood pressure and heart rate proven 240 mg calan, together with nonsteroidal anti-inflammatory medicines blood pressure medication natural 120 mg calan order otc. A results of 90% ache aid or higher in the area focused is taken into account "constructive" for that joint heart attack 30 year old woman purchase calan 80 mg on line. With a medial branch block, facetogenic pain is usually solely relieved during the native anesthetic, making the block a primarily diagnostic device. C2/3 C3/4 C4/5 C5/6 C6/7 A concordant response was considered to be one in which the patients skilled long-lasting aid when bupivacaine was administered, and shortlasting reduction when lignocaine was administered, with the relief in each cases not lasting longer than the expected period of motion of the anesthetic used. A extended concordant response was similar, besides that the length of relief from the bupivacaine, the lignocaine, or each, exceeded the expected period of motion. A discordant response was characterised as one by which lignocaine introduced longer aid than bupivacaine, but reduction in either case conformed to the expected length of action. A discordant extended response was comparable, besides that the aid in either case exceeded the anticipated duration of motion. A minimal of two sequential blocks is often thought-about necessary to firmly establish the diagnosis of facetogenic ache. However, a painful and "concordant" intra-articular injection with confirmatory 208 Head and Neck medial department block (control) could suffice in lieu of dualcontrol medial branch blocks. On a cautionary note, lack of capsular integrity verified in contrast leakage (medially more than laterally) would render the injection void of diagnostic validity based mostly on loss of target specificity. Diagnostic intracapsular joint injections require advanced talent in deciphering results as distinction medium may reveal the articular construction without stressing the synovial capsule to the point of ache provocation. Additionally, unintentional or inadvertent blocking of an adjacent facet as a outcome of lateral or medial spread of native anesthetic would possibly happen and thus invalidate the test. Rotation of the hub facilitates steering without the necessity to withdraw the needle, creating extreme tissue trauma, pain, and in the end confusing the results of the block with procedural ache. Anticoagulation medicine should be suspended for an acceptable interval previous to the conduct of blocks. The solely validated research with constant long-term outcomes was demonstrated by Lord et al. With two to three lesions produced alongside the anterolateral and lateral side of the pillar, the complete size of the nerve is coagulated utilizing the method whereas bearing in mind the variable positions of the nerve. This electrode is capable of producing giant circumferential lesions, when carried out precisely as per the protocol, thermocoagulates a zone that covers all variable neural pathways of the goal department, thus accounting for the consistent long-term pain aid. The described method should hopefully cover the majority of area underneath which all neural pathways might exist. Technical success is maximized when parallel needle placement is used, larger needles are used, and a number of lesions are performed to account for variable nerve topography. Because lesion shapes are elliptical, with the greatest effectiveness on the perimeters of the electrode, needles ought to be positioned parallel to the goal nerve. Facet pain referral patterns ought to be frequent information, and can help the practitioner in approximating the level(s) to be tested. Caution have to be exercised in concluding whether or not pain is of facetogenic or discogenic origin since their pain referral patterns do overlap. Palpation of the suspected facet(s) combined with axial loading strategies might assist in localizing painful segments. Deep, aching pain, extending beyond the immediate neighborhood of the joint, is to some degree referred pain. Pain from the atlanto-occipital joint (C0-C2) is referred unilateral to the suboccipital space. Pain from the atlantoaxial joint (C1-C2) is unilateral, centered on the occipitocervical junction, and radiating to the postauricular area. Patients may have limited head rotation, set off points confined to the occipital area, palpable cervical crepitus, and abnormal head place. Pain from the C2-C3 joint, generally referred to as "third occipital headache," is situated in the upper cervical area and extends a minimum of to the occipital and typically into the head, towards the eye, vertex, or forehead. The C4-C5 aspect joint pain involves a triangular space, with two sides consisting of the posterior midline and posterolateral border of the neck and its base operating parallel to the spine of the scapula muscle. It extends craniad so far as the suboccipital region after which caudad over the posterolateral side of the neck without getting into the region of the shoulder girdle. The C5-C6 aspect joint produces ache in a triangular distribution with the apex directed towards the midcervical area posterior; the main space draped over the top of the shoulder girdle, both front and back; and the base coinciding with the backbone of the scapula. The C6-C7 side joint will refer pain over the supraspinous and infraspinous fossae, periscapular areas, and the medial aspect of the shoulder. Distinctive higher, decrease, and "pancervical" neck pain syndromes have been described for cervical aspect joints. If excessive affected person nervousness may forestall smooth performance of technique, sedation could additionally be used judiciously. The choice to administer sedation should be tempered with the possibility that the postinjection ache diary may not mirror the true situation. If the objective is to entry the length of reduction, the affected person should be instructed to avoid pain medications until the standard ache returns. The process could be uncomfortable; however, most patients tolerate 18-gauge needles when prior infiltration of posterior cervical spine muscle tissue has been enough. However, the patient must have the power to talk with the practitioner all through the process, probably reporting unexpected signs or discomfort. In every case, obtaining a true lateral picture is important, securing a set of sharp pictures with multiple views, documentation of appropriate needle joint access, interpretation of contrast patterns, and postinjection "washout" movies must be saved. In the lateral-oblique approach, the affected person could also be positioned supine, lateral, or susceptible. The lateral position requires placement of foam bolster beneath the head to maintain a neutral place of the top with the thoracic spine. In the posterolateral method, the affected person is inclined with a assist or wedge beneath the chest enhancing flexion of the cervical spine, thus enhancing visualization of the facet joints, as well as the articular pillars. Creating a 25-degree bending of the needle bevel for added control will facilitate easier placement with out removing of the entire needle for repositioning. The needle is advanced till bony contact is made with both the superior articular course of or the inferior articular course of near the joint. The reader will be taught the most secure and most exact elements of this technique, and thus reading the guidelines is very inspired. Once entry into the outer capsule is suspected, the needle should then be walked off into the aspect joint. A minute quantity of distinction might then be injected into the joint-just enough to consider joint morphology, unless this is a purely diagnostic injection. If the injection is therapeutic, confirmation requires simply enough distinction to affirm appropriate needle placement. Care have to be taken to not overpressurize the joint injection, as a capsular tear could also be created. Since the diagnostic worth on this case is negligible, dual-controlled medial department blocks have to be performed. It is changing into broadly accepted (although debated) that a diagnostic, wellcontrolled, contrast-enhanced intra-articular injection is predictive of facetal pathology and may be used as the first controlled block solely under essentially the most stringent situations. Concordant pain provocation, containment of injectate, and 80�90% ache relief in the distribution of that joint would represent a constructive initial diagnostic injection. If the patient states that the injection reproduced solely a fraction of original pain, adjacent levels should bear injection until either concordant ache is completely reproduced or discordant pain is elicited. The reader is encouraged to develop an understanding of an algorithmic therapy of the conduct of synovial joint injections for the remedy of cervical backbone ache. This view allows for visualization of the facet joint, and additional oblique manipulations of the fluoroscope could additionally be useful in higher After final needle placement and following injection of contrast medium, pictures have to be saved and documented. For cervical intra-articular aspect injections, three pictures are required: (1) initial needle placement, (2) contrast-enhanced arthrogram, and (3) final "washout" movie. The key element to success in performing this block is meticulous attention to element in that a near-perfect, true lateral view of the cervical spine is obtained. Sterility It is essential that the goal level is at the middle of the x-ray beam so as to appear on center display. A true lateral view will eliminate any threat that the needle is aimed towards the contralateral facet of the neck. This is performed by tilting the x-ray beam around the lengthy axis of the patient till the silhouettes of the articular pillars at every segmental stage are completely superimposed. Because the medial branches of the cervical dorsal rami vary in position at each segmental level, the practitioner have to be conversant in these variations.
Specifications/Details
This procedure is performed within the susceptible position by way of a posterior midline incision centered over the affected vertebrae heart attack vol 1 pt 3 discount calan 240 mg without a prescription. The paraspinal muscle tissue are retracted subperiosteally on both sides to expose laminae and facet joints blood pressure chart age 60 120 mg calan buy otc. Facet joints and the superior half of the concerned pedicle are drilled out to expose the lateral limits of the thecal sac and the nerve roots blood pressure 80 60 calan 240 mg purchase otc. If required blood pressure is highest in the order calan 240 mg with mastercard, complete elimination of the pedicle is finished to facilitate enough bony decompression. Posterior instrumentation by pedicle screws, sublaminar wiring with rods, or a hook-rod construct could additionally be performed. The lateral extracavitary approach is a modification of a costotransversectomy and supplies entry to the anterior and posterior components of the spine, thereby avoiding the necessity for a thoracotomy. A midline skin incision is made three ranges above and beneath the involved vertebrae. A myocutaneous flap is developed by dissecting the scapular muscles (trapezius, rhomboids, and so forth. Paraspinal muscles are free of the spinous processes and dorsal spinal parts to allow retraction, which exposes the whole rib cage and dorsal vertebral components. Subperiosteal resection, from its costovertebral tip to the posterior bend of the suitable rib is done. The parietal pleura are gently separated from the ribs and the vertebrae to expose the posterolateral aspect of the vertebral bodies. The transverse process, pedicle, and laminae are eliminated, as required, to permit direct visualization of the twine throughout decompression of the vertebral physique. Discectomy/corpectomy, vertebral reconstruction, and instrumentation are carried out as required. Complete spondylectomy and anterior reconstruction is feasible with this strategy with minimal retraction to the wire. Combined anterior-posterior instrumentation can be utilized to leverage off each other for deformity correction. At the tip of the process, the operative area is full of saline to examine for any evidence of air leak. Thoracic pedicle screws have largely replaced the older hook-rod construct and Harrington rods as the fixation of choice. These could be technically challenging as a result of the thoracic pedicles are probably to be rather slender and variable. Potential complications include harm to surrounding nerves, spinal wire, blood vessels (both native and nice vessel), and lung parenchyma. Most procedures allow short-segment instrumentation of the backbone, which regularly obviates the need for subsequent posterior fixation. The most significant disadvantage of those procedures entails the danger of harm to the nice vessels; thus, these procedures are commonly carried out in affiliation with a vascular or common surgeon. There can be threat of harm to the peritoneal contents and the neural plexus across the lumbosacral backbone. Anterior instrumentation systems generally fall into three classes: (a) plating systems. After publicity of the disc space, the exact midline of the house is marked and verified with fluoroscopy. A spacing guide determines the precise place for pilot holes, and a partial discectomy is carried out by way of these pilot holes, that are distracted and later reamed. Bone or cage is then hooked up to a specialized implant driver for insertion beneath fluoroscopic steering. Harvested bone chips and different fusion enhancers are positioned into the cages or across the bone dowel. Anterior lumbar interbody fusion offers quick mechanical stability and long-term load assist, with the flexibility to heal by way of the disc space. Accurate placement of this disc is absolutely critical to the success of this process. These include a screw and screw/plate mixture to buttress the graft from falling out. These add time to the anterior case and run the danger of hardware failure, but have the advantage of potentially enhancing the overall fusion rate and reducing the graft associated problems. Exposure of L4-L5 disc areas requires mobilization of the aorta and inferior vena cava, together with its bifurcations. Variants of the transperitoneal method: A laparoscopic transperitoneal method usually is used on the L5-S1 stage. With the affected person supine, Trendelenburg place is used to transfer the small gut away from the operative field. The process is performed by way of one 10-mm portal for a 30� endoscope, two 5-mm portals for retraction, and one 20-mm working portal for devices. For entry to the L5-S1 level, the posterior peritoneum is incised at the base of the sigmoid mesocolon with endoscopic scissors. Laparoscopic interbody fusion and instrumentation is performed as required, using specifically designed long-alignment tubes, distraction plugs, and a reamer, as in the open procedure. The main advantages of this system are associated to the minimal manipulation of stomach viscera required and minimal trauma to the stomach wall. Variants of the retroperitoneal strategy: A lateral retroperitoneal strategy supplies a wonderful exposure of the lumbar spine from L1-S1 by way of a flank incision. The pores and skin incision is produced from the lateral border of the paravertebral muscular tissues on the midlumbar degree to the lateral border of the rectus abdominis. The incision is angulated below the umbilicus for publicity of the lower lumbar and lumbosacral junction and is carried all the means down to the peritoneum. The supine retroperitoneal method is achieved through a left paramedian incision, and the peritoneum and stomach contents are retracted. Ligation of lumbar intersegmental arteries and tributaries of the iliac vein could also be required to enable a direct anterior exposure from L3-S1. An approach surgeon trained in vascular or general surgery can usually expose much more. With blunt dissection, the peritoneum is peeled off the lateral and posterior abdominal walls, diaphragm, and iliopsoas, exposing the anterior aspect of the lumbar backbone. During this procedure, the nice vessels, ureter, and sympathetic trunk have to be protected. Monopolar cautery is averted as a end result of it can trigger harm to the presacral plexus, which can lead to retrograde ejaculation. A laparoscopic retroperitoneal approach can be utilized for performing an anterior lumbar interbody fusion following discectomy in sufferers with lumbar segmental instability. A 10� 12 mm port is made in the posterior axillary line halfway between the 12th rib and iliac crest, and a trochar is superior into the peritoneum. Retroperitoneal dissection is achieved by balloon inflation, with 1,000 mL of air or saline, through a trochar. Decompressive laminectomy can be utilized to treat compression of the cauda equina, often 2� degenerative disease, congenital stenosis, neoplasm, and, often, trauma. Through a vertical midline incision, the lumbodorsal fascia is exposed, and then the paraspinal muscle tissue are dissected off the spinous course of and lamina of the segments intended for decompression. The surgeon may want a Valsalva-like maneuver (sustained inspiration at 30�40 cm H2O) carried out to take a look at the integrity of the restore. More commonly, there may be troublesome epidural bleeding, which can be troublesome to control and will necessitate transfusion. Under radiographic steering, a sequence of soppy tissue dilators are inserted over a beforehand positioned guide wire to create an operative hall through the paraspinous musculature. A tubular retractor is inserted over the dilators and connected to a versatile assist arm meeting. Endoscope or microscope is used to perform laminotomy and discectomy and/or decompressive laminectomy. As the retractor is withdrawn at the end of the process, the paraspinal muscular tissues resume their normal anatomic position, obliterating the dead house. Although all the most important dangers of surgery are still current, the blood loss, postoperative pain, and hospital stay are lowered. In principle, less trauma to the paraspinous muscle tissue compromises less the post-operative function of the spine.
Syndromes
- Vomiting
- Complications in both men and women may include:
- Eat a healthy, well-balanced diet and drink plenty of water throughout the day.
- Through blood -- via blood transfusions (now extremely rare in the U.S.) or needle sharing
- High blood pressure in the lungs (pulmonary hypertension)
- Do you have any other symptoms?
- Bathe or shower often
- Take the drugs your doctor told you to take with a small sip of water.
- Thermometer
Related Products
Additional information:
Usage: q.h.
Tags: buy calan 240 mg on line, calan 120 mg buy with mastercard, buy calan 120 mg free shipping, cheap calan 240 mg, 80 mg calan generic mastercard, calan 80 mg purchase mastercard, calan 240 mg buy cheap on line, calan 240 mg buy low cost, buy 240 mg calan visa, discount calan 80 mg without a prescription, order 240 mg calan with visa, discount 120 mg calan free shipping, purchase calan 80 mg without prescription, 80 mg calan generic free shipping, generic calan 240 mg line, 80 mg calan generic otc
8 of 10
Votes: 177 votes
Total customer reviews: 177
Customer Reviews
Ilja, 54 years: The terminal branch of the inferior alveolar nerve is the psychological nerve, which exits the mandible through the psychological foramen and supplies sensory innervation to the chin and to the skin and mucous membrane of the decrease lip. Stated above, Streptococci an infection also induces release of enzymes such as hyaluronidases, or serine proteases that would additionally contribute to a loss of normal mucosa integrity (Benchtrit et al.
Emet, 63 years: Some older sufferers exhibit apathetic thyrotoxicosis, which is often mistaken for hypothyroidism. Bare sclera excision could be began from the corneal apex or by incising around the conjunctival body of the pterygium.
Gamal, 42 years: Preparation for cardiopulmonary bypass is often similar to the adult heart transplant affected person, and the implantation process can be related. Anticoagulation medicine ought to be suspended for an acceptable interval previous to the conduct of blocks.