
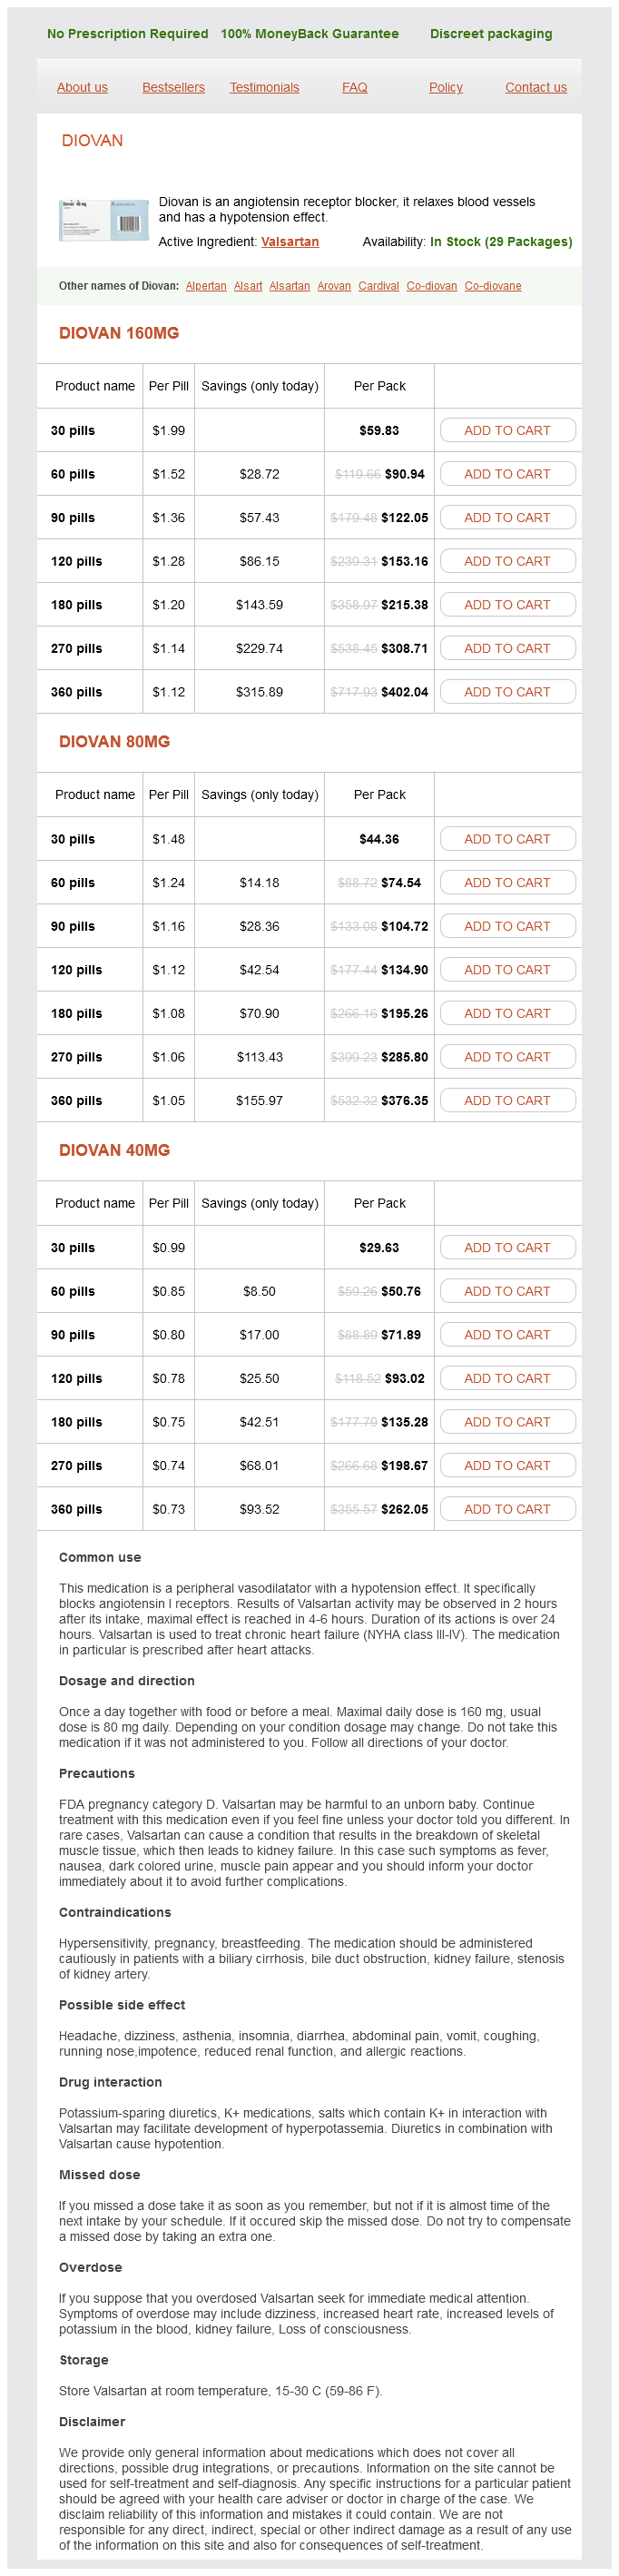
Diovan
Diovan 160mg
- 30 pills - $59.83
- 60 pills - $90.94
- 90 pills - $122.05
- 120 pills - $153.16
- 180 pills - $215.38
- 270 pills - $308.71
- 360 pills - $402.04
Diovan 80mg
- 30 pills - $44.36
- 60 pills - $74.54
- 90 pills - $104.72
- 120 pills - $134.90
- 180 pills - $195.26
- 270 pills - $285.80
- 360 pills - $376.35
Diovan 40mg
- 30 pills - $29.63
- 60 pills - $50.76
- 90 pills - $71.89
- 120 pills - $93.02
- 180 pills - $135.28
- 270 pills - $198.67
- 360 pills - $262.05
Diovan dosages: 160 mg, 80 mg, 40 mg
Diovan packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 664
Only $0,77 per item
Description
More than one acquisition via the liver is now potential in a single breathhold arrhythmia nausea buy discount diovan 160 mg. Thinner collimation improves decision and will increase detection of small hepatic lesions by as a lot as arteria 7ch cheap diovan 40 mg visa 46% (Weg et al arrhythmia management institute of south florida 160 mg diovan discount fast delivery, 1998) blood pressure jokes diovan 160 mg fast delivery. At current array sizes (most fashionable scanners now use a minimum of 64 to 128 detector rows), decision considerably below 1 mm is now out there in all planes. Scan decision equal in all planes-perfect cubes of imaging information or "voxel isotropy" (which was achieved by the era of 16-detector scanners in 2002)-yields smoother images when the info acquired in the axial plane are reformatted in the coronal, sagittal, and oblique planes. Scrolling quickly by way of overlaid adjoining picture slices ("cine" viewing) aids appreciation and evaluation of tubular and other constructions whose course is skewed to the axial aircraft, such as dilated bile ducts and hepatic vessels. The ability to magnify photographs and alter their contrast and brightness on the fly also tremendously facilitates image interpretation. A major downside stays utilization of ionizing radiation, with a pattern in previous a long time toward increasing exposure of the affected person inhabitants to nontrivial doses, a problem attracting rising in style scrutiny and spurring substantial ongoing attention amongst technical innovators. The right hepatic artery (long open arrow)andthelefthepaticartery(small open arrow)originatefromthe properhepaticartery. Three-dimensional reformatted image reveals the course of the left portal vein, which ascends within the umbilical fissure earlier than looping anteriorly and inferiorly (short arrow) to branch into the medial(arrowhead)andlateral(long arrow)sectoralbranches. With more highly effective laptop hardware presently obtainable, newer, beforehand prohibitively processorintensive iterative reconstruction algorithms at the moment are approaching clinical availability. For the liver, biliary system, and pancreas, applications embrace "materialspecific imaging" and "virtual monochromatic imaging" (Morgan, 2014). In the liver, "digital iron images" could also be used for quantitation of hepatic iron deposition without interference from coexisting steatosis (Joe et al, 2012), whereas "digital non-iron pictures" can be created for fat quantitation unbiased of concomitant siderosis (Zheng et al, 2013). Lower-energy digital monochromatic photographs may also present more robust surface-rendered 3D arterial pictures, whereas digital higherenergy images have less obvious metallic artifact around biliary stents and clips (Morgan, 2014). There can be early indication that material-specific iodine imaging improves conspicuity of neuroendocrine lesions and will increase sensitivity for complexity inside cystic lesions (Chu et al, 2012). Chapter 18 Computed tomography of the liver, biliary tract, and pancreas 319 An thrilling methodology called texture analysis, not yet in clinical use, is being brought to bear in interpretation. Preliminary results counsel that certain hepatic texture options can predict survival in colon cancer sufferers (Miles et al, 2009), can establish the presence of colon most cancers hepatic micrometastases not yet visible by commonplace visual image evaluate (Rao et al, 2014), and may preoperatively stratify risk for postoperative hepatic failure in candidates for major hepatic surgical procedure (Simpson et al, 2015). Contrast-enhanced computed tomography reveals a small malignant lesion in segment I abutting the middle hepatic vein (open arrow)andlefthepaticvein(solid arrow)attheirconfluencewith the inferior vena cava (arrowhead). Thesuperior portion of the hepatic parenchyma has been eliminated to reveal the course of the hepatic veins through the liver substance as they drain into the inferior vena cava. Right lobe atrophy as a result of an infiltrative tumor involving the proper portal pedicle (arrow). Because visualization of the surgical area is often restricted in sufferers with prior surgery, weight problems, hepatobiliary malignancy, and native inflammation, preoperative data of variant celiac anatomy can assist in surgical planning (see Chapters 2, 103, and 104), facilitate dissection, and help the surgeon avoid iatrogenic injury (Winston et al, 2007). Late arterial-phase photographs (included in the "triphasic" examination, in contrast to early arterial images) are obtained for detection and delineation of hypervascular hepatic lesions. Because most neoplasms involving the liver are hypovascular relative to adjacent regular liver parenchyma, routine abdominal imaging generally makes use of solely the portal venous section, in which these are most conspicuous. Thinner photographs may be requested by the radiologist on any sort of examination in problem-solving situations, supplied the uncooked picture data are still extant on the scanner, usually for a day or two after the acquisition. Differential enhancement of varied types of lesion relative to background hepatic parenchyma dictates which timing or "phase(s)" to use in the analysis. Different strategies are available to determine the time of maximal arterial enhancement for each patient (which is dependent upon elements corresponding to cardiac operate and state of hydration) (Sica et al, 2000), together with fastened timing, timing bolus (Kalra et al, 2004), and commercially out there autoattenuation detection. Images are acquired at about 20 to 30 seconds after injection initiation to present maximal distinction enhancement of the arteries, preserving veins and stomach organs nearly unopacified. The late arterial section used to evaluate hypervascular lesions is normally acquired at about 40 seconds after the beginning of injection. Hepatic neoplasms usually have excessive water content material and are thus slightly hypoattenuating relative to regular liver parenchyma, as are the unenhanced portal veins and bile ducts. Steady steady injection is crucial to picture quality, requiring a devoted energy injector. Arterial and portal venous phase pictures as a part of a triphasic examination in a affected person with metastatic renal cell carcinoma. Normal noncirrhotic hepatic parenchyma enhances maximally at approximately 70 seconds after injection initiation. At this time, referred to because the portal venous section of enhancement, maximal contrast differential between typical hypovascular liver lesions and the encompassing parenchyma is achieved, as well as clear delineation of the portal and hepatic veins. Although that is typically seen in the routinely acquired portal venous section, it could solely be appreciated on further delayed imaging (Iannaccone et al, 2005; Liu et al, 2012). Some intrahepatic cholangiocarcinomas could additionally be inconspicuous on the standard elements of the triphasic examination, and significantly delayed imaging may be added when this entity is suspected (see Chapter 50). No particular optimum timing for this indication has been firmly established, however a delay of 5 to 12 minutes is usually used. Carrying the ligamentum teres and a few surrounding fat, it defines the inferior aspect of the border between the medial and lateral segments of the left liver. Rather, the left portal scissura runs alongside the course of the left hepatic vein, defining the superior aspect of the border between left medial and lateral segments. Vascular Anatomy After following the portal scissurae tracing the boundary between the hepatic sectors, the hepatic veins have a short extrahepatic course (Blumgart et al, 2001). The portal vein is shaped by the junction of the splenic vein and superior mesenteric vein instantly posterior to the neck of the pancreas. Covey and colleagues (2004) reported variant portal venous anatomy in 35% of a gaggle of 200 patients. The proper hepatic artery divides into right and left hepatic arteries before getting into the liver, but the precise location of the bifurcation varies. Segmental Anatomy A surgically helpful practical scheme similar to the liver anatomy has been described (Bismuth, 1982), and the 1957 Couinaud description is schematically reproduced in Chapter 2. The 4 sectors, every receiving its own separate portal venous and hepatic arterial supply and excreting to a separate bile duct, are separated by the portal scissurae following the three main hepatic veins. The interlobar scissura, following the center hepatic vein, divides the liver into right and left lobes. The proper lobe is further divided into two sectors by the best portal scissura following the best hepatic vein, and the left liver is divided equally by the left portal scissura following the left hepatic vein. The fissure for the ligamentum teres varieties the boundary between the medial and lateral sectors of the left liver and generally follows an inferior projection of the course of the left hepatic vein. The inferior boundary between the best anterior and posterior sectors has no clear anatomic or vascular landmark and have to be estimated by extrapolating an inferior projection of the course of the proper hepatic vein onto lower sections. Biliary Anatomy Ductal anatomy and its variants are discussed quite extensively in Chapter 2. Along the anterior aspect of the main portal venous bifurcation, the left and right hepatic ducts be part of to type the widespread hepatic duct, which courses caudally and posteriorly towards the left throughout the hepatoduodenal ligament, at all times sustaining its position anterolateral to the portal vein. It is considered dilated at higher than or equal to 9-mm caliber beneath normal conditions, although a diameter of seven to 10 mm is usually noticed in aged sufferers, and this caliber is typical postcholecystectomy. Mistaking an incidental benign lesion for a malignant mass has important implications in affected person management. Benign Tumors and Tumor-Like Conditions of the Liver Cyst (See Chapters 75 and 90B) Hepatic cysts are frequent, occurring in no much less than 2% to 7% of the inhabitants (Horton et al, 1999), and are sometimes discovered by the way with no malignant potential. The extra widespread congenital selection could symbolize malformed bile ducts that have lost communication with the rest of the biliary tree; their singlelayered cuboidal or columnar epithelial lining fills them by secreting serous fluid (Blumgart et al, 2001). The acquired sort of hepatic cyst normally arises as a sequela of irritation, trauma, or parasitic illness. Sometimes adjacent enhancing liver parenchyma compressed by a cyst could mimic the looks of an enhancing wall, causing diagnostic ambiguity. Coronal reformatted picture of the confluence of the proper (solid arrow) and left (open arrow) hepatic ducts reveals bilobar intrahepatic biliary ductal dilation. Coronal reformatted image created from axial computed tomographic information acquired after intravenous administration of contrastmedium. Hemangioma (See Chapter 90A) Hemangiomata are the most common stable tumors of the liver (Blumgart et al, 2001). Usually detected by the way, their prevalence has been reported at 7% total in an autopsy collection (Karhunen, 1986), extra frequent in ladies (Horton et al, 1999). Hemangiomata are variable-sized lesions (<1 cm to >40 cm); larger examples are referred to as big hemangiomata (Blumgart et al, 2001). Composed of endothelium-lined vascular spaces separated by fibrous septa, they derive their blood provide from the hepatic artery (Horton et al, 1999). Note the discontinuous peripheral nodular, clumplike enhancement (arrow)withinthehemangioma.
Thorn-apple (Jimson Weed). Diovan.
- Asthma, cough, nerve diseases, causing hallucinations and elevated mood (euphoria), and other uses.
- Dosing considerations for Jimson Weed.
- How does Jimson Weed work?
- What is Jimson Weed?
- Are there any interactions with medications?
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96885
This is partially as a result of blood pressure variability normal diovan 80 mg discount on-line earlier and more practical detection based on familiarity with procedure-specific problems and advances in high-quality imaging arrhythmia synonym diovan 80 mg order overnight delivery. Another cause is the shift in management from operative reexploration to interventional and endoscopic methods which are efficient with much much less added morbidity (Sohn arrhythmia quiz diovan 160 mg cheap with mastercard, 2003; Vin et al hypertension 40 years order 80 mg diovan mastercard, 2008). Interventional radiologists now make up an indispensible a part of the multidisciplinary team caring for patients undergoing advanced hepatopancreatobiliary procedures and their experience in the minimally invasive remedy of anastomotic leaks, intraabdominal abscesses, and postoperative bleeding is responsible for considerably improved patient outcomes (Mezhir, 2013; Sohn, 2003). This article will provide an outline of probably the most commonly reported postoperative problems associated with main pancreatic and hepatic resections, including a evaluate of the current definitions and grading methods used for reporting. It will then provide an in depth dialogue of the appropriate management of every complication in accordance with probably the most present literature and with an emphasis on interventional methods. The reported morbidity and mortality following pancreatic resection in a quantity of giant collection reported since 2000 is offered in Table 27. Pancreatic resection is related to a bunch of problems, a lot of that are procedure particular and happen on the operative site (hemorrhage, leak, obstruction), whereas others happen remotely as a consequence of main surgical procedure somewhat than the particular type of surgery (deep venous thrombosis, cardiac arrhythmia, pneumonia). This article is primarily involved with the most typical severe issues directly related to the technical features of the operation itself. The reported frequencies of these problems are listed within the reported frequencies for these problems in several giant collection since 2000 are presented in Table 27. Defining and Grading Complications After Pancreatectomy Postoperative problems are notoriously troublesome to research because of the inconsistent definitions and imprecise terminology used to designate them (see Chapter 66). They comprise three overlapping manifestations of the identical underlying concern, which is breakdown and leakage on the pancreatic anastomosis (or pancreatic closure site for distal and central pancreatectomies). For example, an intraabdominal fluid collection requiring drain placement could reasonably be reported as an abscess. If the drainage was studied and found to be amylase rich, it could be considered a leak. If drainage from the leak endured throughout a time frame, it could also be thought of a fistula. However, the absence of any standardized, quantifiable measures for reliably differentiating these from one another meant that the same complication could be reported in three other ways. They generated 4 consensus definitions consultant of these mostly used in the literature and utilized every to the same management group of pancreatectomies. Using these 4 definitions, the incidence of pancreatic fistulae various throughout the same group of sufferers from 10% to 29%. This lack of consistency is mirrored in the literature, the place the precise reported incidence of pancreatic fistulae varies equally from 2% to 29% (Braga et al, 2011; B�chler et al, 2000; Muscari et al, 2006; Reid-Lombardo et al, 2007). Regardless of the difficulty inherent in defining problems, correct measurement and documentation in a standardized manner is vital to improving quality of care by allowing significant comparisons between procedures, institutions, and even particular person surgeons. This method supplies a simplified, unifying definition for every complication, with grades of accelerating severity based mostly upon the medical impression of the complication and the invasive of the required treatment. Note that the grade of the complication increases only when a new, more invasiveness or aggressive remedy is required for administration. An example of this within the surgical literature is the event of the Clavien-Dindo classification of surgical issues. Clavien and colleagues (1992) acknowledged the inconsistency in reporting surgical issues in 1992 and proposed a definition and classification system for grading them in a standardized fashion. A complication, as defined by Clavien, is any deviation from the normal postoperative course and is differentiated from a sequela, which is an "after-effect" of surgical procedure inherent to the procedure. The system was up to date in 2004 because the ClavienDindo classification, which is a graded system of accelerating severity determined by the presumed long-term consequences of a given complication in addition to the invasiveness, level of care, and sources required for the intervention needed to appropriate it (Dindo et al, 2004). The system is made up of five grades, two of which have subgroups, and a suffix "d" class that may be appended to any grade. Modified from Winter J, et al, 2006: 1423 pancreaticoduodenectomies for pancreatic most cancers: a single-institution expertise. Finally, the suffix "d" may be applied to any of the primary four grades to point out the presence of incapacity on the time of discharge. In latest years, this technique has turn out to be widely used within the surgical literature to help improve the consistency with which surgical issues are reported. Moreover, many surgical subspecialties have tailored this strategy to meet the particular needs of figuring out and reporting complications inside their respective fields. There were fifty three sufferers with confirmed fistulae (30% incidence), of which 26 (49%) have been grade A, 21 (40%) have been grade B, and 6 (11%) were grade C. Patients with grade A fistulae had shorter hospital stays and fewer secondary complications than sufferers with grade B and C fistulae, although the overall rate of secondary problems was not considerably different between grades B and C (76% vs. Also, 5 of the 6 sufferers with a grade C fistula had been discharged to a rehabilitation facility, which was significantly more regularly than sufferers with grade A and B fistulae. In terms of cost burden, a constructive correlation between elevated well being care prices and improve in fistula grade was identified. Suspicion for it begins with any deviation from the conventional postoperative course, together with nonspecific indicators and symptoms corresponding to belly discomfort, nausea, tachycardia, and fever. It has a variety of presentations that embody transient anastomotic leak, intraabdominal abscess, and frank fistula formation. Given the numerous morbidity associated with affected person outcomes once a fistula has developed, a substantial amount of research has been dedicated to developing methods for prevention. One of essentially the most extensively studied is pharmacologic therapy using somatostatin analogues, which has yielded combined results. Pancreatic fistula is defined as drain output of any measurable volume of fluid on or after postoperative day three with amylase content material higher than thrice regular serum exercise. Uncomplicated low-output fistulae can be managed conservatively, which includes enough drainage of intraabdominal collections (see Image-Guided Abdominal Drainage) (see Chapter 30), restriction of oral consumption, and dietary help (see Chapter 26). With conservative administration, spontaneous fistula closure will occur in as many as 90% of cases, normally within 4 weeks (Machado, 2012). Erythromycin, a macrolide antibiotic, acts as a motilin agonist and binds its receptors to stimulate gastric emptying. To exclude mechanical causes of abnormal gastric emptying, the patency of both the gastrojejunostomy or the duodenojejunostomy ought to be confirmed by endoscopy or higher gastrointestinal gastrographin collection. Beane and colleagues (2014) reported that when supplemental diet was initiated by postoperative day 10, sufferers resumed an everyday food plan sooner (day 24 vs. It is reported to happen after 1% to 8% of all pancreatic resections and accounts for 11% to 38% of total mortality (Wente et al, 2007b). Its presentation is extremely heterogeneous as a result of bleeding might occur from numerous potential websites with variable severity and time of onset. The definition is split into grades A, B, and C primarily based on time of onset (early or late), location (intraluminal or extraluminal), and severity (mild or severe) (Wente et al, 2007b). Grade B is the world of overlap and consists of the two remaining groups, early extreme and late delicate bleeding episodes. Endoscopy should be carried out when signs of intraluminal bleeding are present (melena, hematemesis, or blood loss through nasogastric tube). Time of onset could also be inside 24 hours of surgery (early) or anytime thereafter (late). Early hemorrhage is normally indicative of a technical failure to achieve sufficient hemostasis in the operating room, whereas late hemorrhage often occurs within the setting of inflammatory intraabdominal processes (pancreatic leaks, abscesses, fistulae, and anastomotic ulceration) that trigger vascular erosion or the formation of arterial pseudoaneurysms (Rajarathinam et al, 2008; Wellner et al, 2014; Welsch et al, 2011). The severity of hemorrhage is classified as gentle or severe depending on the diploma to which it impacts the postoperative course. Extraluminal bleeding originates from peripancreatic vessels, pseudoaneurysms, external staple/suture strains, and uncooked surfaces within the operative subject. This type of bleeding may be evident from the wound and stomach drains, or there may be no exterior signs of bleeding. It is important to observe that an extraluminal supply of bleeding could present as intraluminal bleeding should it originate in the setting of an anastamotic failure, such as a pancreatic dehiscence. With this in mind, a quantity of validation research narrowed the scope of their evaluations by applying the definition only to extreme bleeding, delayed bleeding, and/or bleeding from the surgical website (Correa-Gallego et al, 2012; Gr�tzmann et al, 2012; Rajarathinam et al, 2008; Yehuda et al, 2014). Mortality amongst these affected ranges from 3% to 29%, of which the overwhelming majority (71% to 100%) happens in affiliation with grade C hemorrhage. In many cases, patients had bleeding, transfusions, and mortality unrelated to their surgical procedure that resulted in frequent false positives. Despite these shortcomings, each studies reported that the definition did effectively segregate sufferers based on general disease severity, medical impact, and mortality. This is because early and late hemorrhages outcome from totally different causes, which have implications for overall survival. Early bleeding is usually an isolated problem of inadequate hemostasis because of a technical error.
Specifications/Details
During the incision blood pressure chart elderly 160 mg diovan discount visa, warning must be taken to avoid injuring the posterior wall of the duct arrhythmia treatment diovan 160 mg cheap with mastercard. The size of the choledochotomy will rely upon the diameter of the duct and dimension of stones present with the lumen but is generally 1 to 2 cm pulse pressure map diovan 160 mg on line. Another consideration regarding the placement of this incision is proximity to duodenum; in the occasion that a choledochoduodenostomy should be required for acceptable drainage blood pressure chart heart foundation buy 160 mg diovan with mastercard, every effort must be made to place the incision distally enough to allow a tension-free anastomosis to the proximal duodenum. Chapter 31 Bile duct exploration and biliary-enteric anastomosis 539 After choledochotomy, flushing of the duct (distally toward the ampulla) with saline irrigation can end result in expulsion of stones. Following this, a deflated Fogarty balloon catheter is passed distally through the ampulla into the duodenum. Once the tip of the catheter is palpated within the duodenal lumen, the balloon is inflated and the catheter is withdrawn until resistance is encountered, indicating that the balloon is positioned against the sphincter of Oddi. At this level, the balloon is fastidiously reinflated, and the catheter is swept proximally, sweeping retained stones up toward the cholodochotomy. The catheter is then passed proximally to retrieve any stones inside the widespread hepatic duct and intrahepatic biliary tree. Rigid devices corresponding to clamps or stone forceps can cause harm to the bile duct and are subsequently usually best averted. These may be captured with basket retrieval, during which the basket is handed beyond the stone, opened, and pulled again to ensnare the stone. At the conclusion of duct exploration, confirmation of proximal and distal duct clearance is carried out either utilizing choledochoscopy or completion cholangiography (Verbesey et al, 2008). The tube is inserted via the choledochotomy, and the rest of the duct is closed with fantastic absorbable sutures around the tube. Care should be taken to depart enough redundancy within the intraperitoneal portion of the tube to avoid tension (and possible tube dislodgement) in the occasion of great postoperative stomach distension. Postoperatively, the T-tube is positioned to dependent drainage till decision of postoperative papillary edema permits physiologic circulate of bile into the duodenum. If persistently elevated output or drainage around the tube occurs, investigation through cholangiography can identify malfunction, dislodgement, or distal obstruction secondary to retained stone. If a repeat cholangiogram at approximately 2 to 3 weeks is normal, the T-tube may be removed. If choledocholithiasis persists, the T-tube may be clamped to promote stone passage. If indicators or symptoms of cholangitis happen, the tube can be unclamped and repeat imaging is obtained. Residual obstruction could additionally be amenable to stone extraction through T-tube or endoscopic or percutaneous entry. Even in high-risk sufferers, open surgical intervention has comparable mortality (4% vs. A 2- to 4-cm longitudinal incision on the lateral side of the second portion of the duodenum can allow visualization of the ampulla. Placing the incision at this location within the ampulla minimizes the prospect of pancreatic duct harm, which is generally positioned opposite the deliberate sphincterotomy web site. Once again, a catheter is passed to ensure resolution of obstruction, and choledochoscopy or cholangiography is used to verify the absence of residual stones. Disadvantages embody tube migration, obstruction, and bile leak following elimination. Although closure over a T-tube is often the preferred approach, a latest analysis instructed that the duct can be closed primarily without elevated morbidity or mortality (Gurusamy et al, 2013). If a T-tube is used, size 14 Fr or larger will permit cholangiography and choledochoscopy. These include identification of a wholesome phase of bile duct tissue proximal to the positioning of obstruction; preparation of a phase of alimentary tract such as duodenum or, more commonly, Roux-en-Y jejunal limb; and development of a mucosa-to-mucosa anastomosis. It is subsequently essential to use preoperative imaging to clearly delineate the biliary anatomy prior to endeavor operative intervention for biliary decompression. Cross-sectional imaging with magnetic resonance imaging/magnetic resonance cholangiopancreatography, and even thin-cut computed tomography scans, can accurately characterize the anatomy of the biliary tree and underlying pathology (see Chapter 19). Invasive imaging of the biliary tree with endoscopic or percutaneous cholangiography allows stent placement, which can facilitate intraoperative identification of proper and left hepatic ducts (see Chapters 20, 29, and 30). It is also necessary to recognize that instrumentation of the biliary tree introduces bacterial contamination that, in a setting of biliary stasis, can end result in cholangitis, periductal irritation, and a better threat of postoperative infections. Caution should also be exercised to keep away from percutaneous drainage whether it is unlikely that the stent may be handed throughout the obstructing lesion. These complexities underscore the important importance of an skilled multidisciplinary staff reviewing and treating advanced biliary obstruction, particularly on the biliary confluence. Depending on the underlying pathology, there are a number of choices for restoration of biliary continuity with the alimentary tract. For occasion, choledocholithiasis refractory to native exploration could require choledochoduodenostomy. Other benign etiologies, such as iatrogenic bile duct harm, strictures from earlier biliary-enteric operations, choledochal cysts, or inflammatory strictures, may require restoration with Roux-en-Y choledochojejunostomy or hepaticojejunostomy. Additionally, benign proximal biliary strictures in addition to malignancy (cholangiocarcinoma) could require anastomosis between intrahepatic ducts and jejunum. Finally, the gallbladder can also be utilized to facilitate drainage (cholecystoduodenostomy and cholecystojejunostomy). Although nonoperative measures can be utilized in most situations, familiarity with the various surgical techniques can allow acceptable restoration of biliary-enteric continuity when the situation calls for (see Chapter 42). Caution have to be exercised within the setting of long-standing biliary obstruction or situations related to ipsilateral hepatic atrophy and contralateral hypertrophy. In the state of affairs of marked right hemiliver atrophy, the liver hilum and portal structures will become rotated in a counterclockwise method. In instances of very profound right liver atrophy, entry to the biliary confluence might require a thoracoabdominal incision. Hepaticojejunostomy Despite the need for a further anastomosis (at the jejunojejunostomy), Roux-en-Y hepaticojejunostomy is the commonest surgical reconstruction for biliary obstruction. The jejunum is often anastomosed to the widespread hepatic duct simply distal to the confluence of the best and left hepatic ducts. Disadvantages embrace necessity for two anastomoses and exclusion of bile from the duodenum. Access to the best portal pedicle containing the proper hepatic duct could be achieved by isolating the pedicle in an extrahepatic location or by exposing the pedicle via intrahepatic dissection. By continuing this airplane of dissection to the right (onto the cystic plate), the best hepatic duct may be uncovered (Strasberg et al, 2008). If the extrahepatic portion of the proper hepatic duct is too brief to be visualized in this method (as is often the case), the intrahepatic strategy could also be used. This requires hepatotomies in the caudate course of just posterior to the porta hepatis and along the bottom of the gallbladder fossa. Incision and Exposure A proper subcostal incision with or without an higher midline extension or a left subcostal extension followed by upward elevation and cephalad retraction of the costal margin provides adequate exposure for building of any biliary-enteric anastomosis. The ligamentum teres is ligated and divided, and the falciform ligament is split to its most cephalad extent on the diaphragm. If direct decompression of the gallbladder is not to be undertaken, cholecystectomy could be advantageous for identification of the cystic duct, which may be dissected to its level of insertion onto the frequent hepatic duct. Cholecystectomy may also expose the cystic plate, which runs in continuity with the hilar plate. Because of its longer extrahepatic course, the left hepatic duct is the popular target. After ligation of the ligamentum teres with a agency tie, retraction is utilized to elevate the left hemiliver. This could be achieved by exposing the biliary drainage of the left hemiliver within the umbilical fissure (Blumgart, 1987; Jarnagin et al, 1998; Voyles et al, 1983). If the left hemiliver has not atrophied from long-standing biliary obstruction, unilateral left-sided biliary decompression will effectively relieve obstructive jaundice and restore hepatic function even when the biliary drainage of the excluded right hemiliver stays obstructed. To put together for biliary-enteric anastomosis, the duct should be dissected free for 1. A defunctionalized jejunal loop is then brought up in a retrocolic trend and ready for anastomosis.
Syndromes
- Rigid or stiff muscles, often beginning in the legs
- Recurrent infection
- Female: 12-150 ng/mL
- Colds or the flu
- Centipedes
- Has the memory loss been developing over weeks or months?
- Abdominal ultrasound
Related Products
Additional information:
Usage: p.o.
Tags: buy diovan 160 mg free shipping, diovan 40 mg overnight delivery, order diovan 160 mg line, buy cheap diovan 40 mg on line, buy 160 mg diovan visa, discount diovan 80 mg overnight delivery, buy generic diovan 40 mg, diovan 80 mg order without prescription, diovan 160 mg order with mastercard, 160 mg diovan order with mastercard, purchase 40 mg diovan visa, cheap diovan 80 mg with mastercard, cheap 80 mg diovan amex, diovan 160 mg buy generic, diovan 40 mg generic, discount diovan 40 mg with mastercard
10 of 10
Votes: 132 votes
Total customer reviews: 132
Customer Reviews
Olivier, 59 years: If the drainage was studied and found to be amylase rich, it could be considered a leak. Infectious cysts can also communicate with the biliary tree, however, such as with advanced cysts from echinococcal illness.
Esiel, 38 years: Decompensated liver failure leads to the development of encephalopathy, jaundice, ascites, fatigue, polydipsia, easy bruising, temper fluctuation and sometimes is marked by dietary depletion. For less complicated cases, complete removing of the stones and dilation or bypass of all strictures combined with vigilant follow-up can forestall illness recurrence.
Barrack, 28 years: Bile duct injuries are problems associated with laparoscopic cholecystectomy, for example, with a reported fee of occurrence starting from zero. Portal vein thrombosis might outcome from technical issues at surgery, prior portal vein thrombosis, elevated downstream resistance.
Cruz, 47 years: First, they confirmed the notion that patients in whom a pancreatic fistula develops have a higher fee of postoperative wound an infection and intraabdominal abscess. Biopsies obtained during endoscopy can assess for dysplasia or unsuspected carcinoma, though malignancy may be missed in as much as 30% of tumors when forceps biopsy specimens are obtained (Elek et al, 2003).
Gunnar, 51 years: Using these four definitions, the incidence of pancreatic fistulae varied within the identical group of sufferers from 10% to 29%. In addition, some authors famous a powerful inverse correlation between biliary harm and nonperformance of cholangiography (Torkington et al, 1999).
Tyler, 54 years: Although bile from the gallbladder and bile ducts is normally sterile, in the presence of frequent bile duct stones or different obstructing pathology, the incidence of positive cultures will increase; likewise, instrumentation of the biliary tree additionally significantly will increase rates of bile colonization. If gallstones and sonographic indicators of cholecystitis are absent, hepatobiliary scintigraphy might be pursued to determine cystic duct obstruction, which is the standard etiology of acute calculous or acalculous cholecystitis in adults.
Samuel, 41 years: The use of largerdiameter biliary stents could be restricted by the dimensions of the working channel of the endoscope, and even smaller caliber accessories could also be troublesome to advance through the channel when the longer endoscope is torqued or looped in the surgically altered bowel. Bleeding Complications See "Angiography, Embolization, and Covered Stent Placement," earlier.