
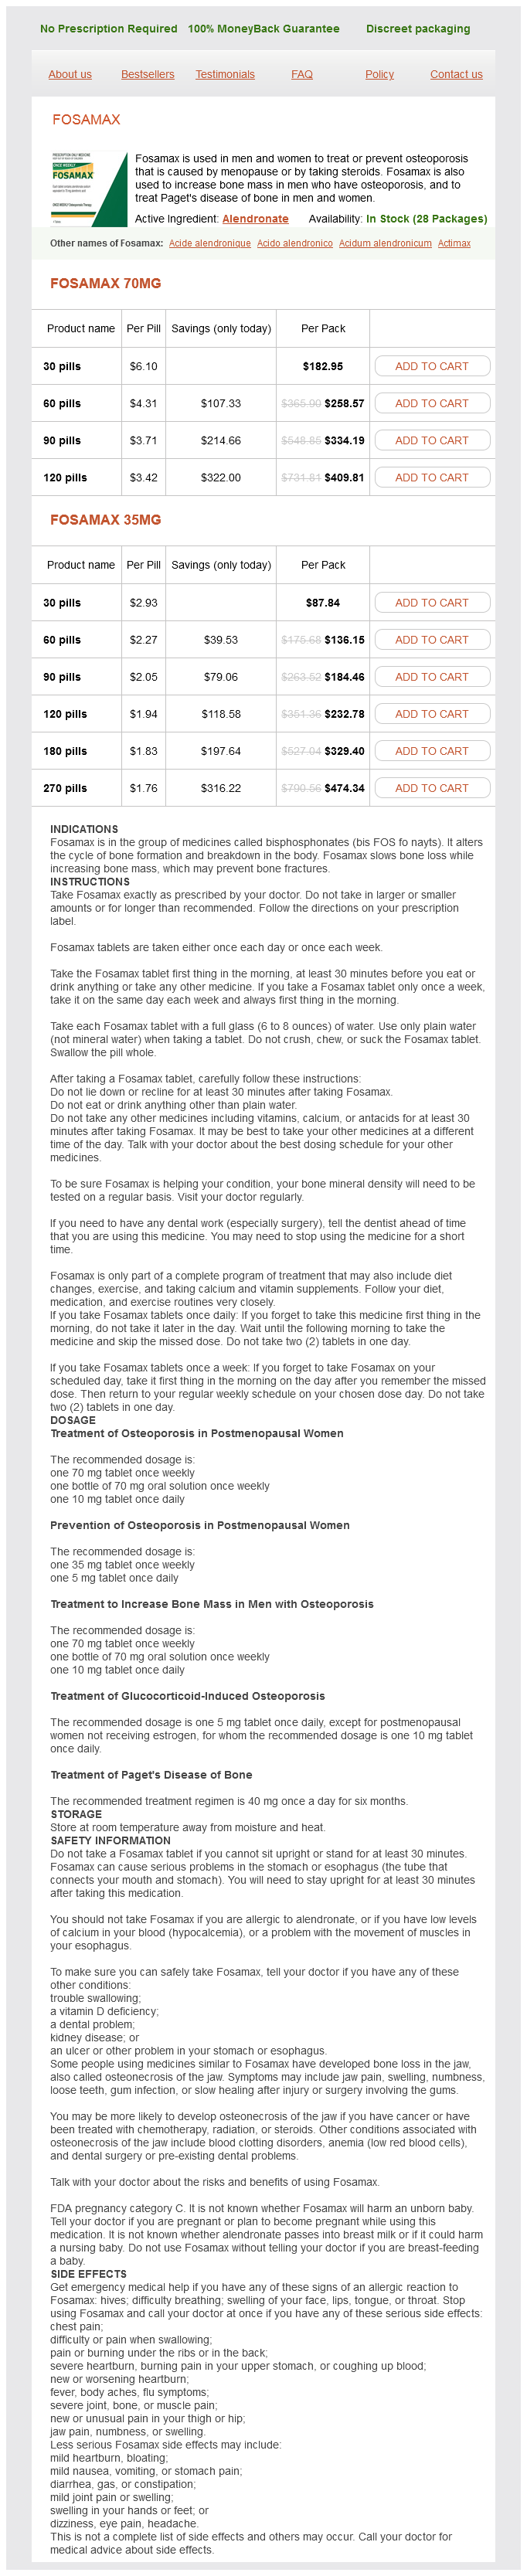
Fosamax
Fosamax 70mg
- 30 pills - $182.95
- 60 pills - $258.57
- 90 pills - $334.19
- 120 pills - $409.81
Fosamax 35mg
- 30 pills - $87.84
- 60 pills - $136.15
- 90 pills - $184.46
- 120 pills - $232.78
- 180 pills - $329.40
- 270 pills - $474.34
Fosamax dosages: 70 mg, 35 mg
Fosamax packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills
In stock: 746
Only $0,49 per item
Description
False-negative immunoassay outcomes are most likely in patients with isolated pulmonary or low-grade/early renal illness women's health center logansport in purchase fosamax 35 mg on-line. Rare non-IgG antibodies are identified by direct immunofluorescence studies of the renal biopsy women's health issues forum fosamax 70 mg buy online. False-positive assays might sometimes be seen in states of polyclonal activation together with different autoimmune situations history of women's health issues 70 mg fosamax quality. Other serologic exams similar to anti-streptolysin O womens health center 95th western 70 mg fosamax order visa, antinuclear antibodies, serum immunoglobulin and complement levels, rheumatoid factor, cryoglobulins, and circulating immune advanced are both unfavorable or normal. In such condition, the immunofluorescence could display segmental linear deposits or completely negative. Role of endothelial damage and restore, induction of autologous phase, and kinetics of antibody deposition in Lewis rats. Anti-glomerular basement membrane glomerulonephritis: a morphologic study of eighty cases. Anti-glomerular basement membrane antibody disease in Japan: part of the nationwide rapidly progressive glomerulonephritis survey in Japan. Comparison of four enzyme immunoassays for the detection of immunoglobulin G antibody towards glomerular basement membrane. Therapy of anti-glomerular basement membrane antibody disease: evaluation of prognostic significance of clinical, pathologic and remedy components. Antiglomerular basement membrane antibody-mediated nephritis with regular pulmonary and renal operate. Alveolar hemorrhage syndromes: diffuse microvascular lung hemorrhage in immune and idiopathic issues. Long-term outcome of anti-glomerular basement membrane antibody illness treated with plasma trade and immunosuppression. The medical information and light microscopic findings should help make this distinction. Fibrillary glomerulonephritis: an entity with uncommon immunofluorescence options. Rapidly progressive glomerulonephritis: analysis of prevalence and medical course. Antibasement membrane antibody illness with out medical proof of renal illness. Characteristics and prognosis of Chinese patients with anti-glomerular basement membrane illness. Characteristics and outcome of anti-glomerular basement membrane disease: a single-center experience. The immunopathological spectrum of crescentic glomerulonephritis: a survey of 106 sufferers in a single Chinese heart. Anti-glomerular basement membrane disease: role of enzyme-linked immunosorbent assays in analysis. IgA antiglomerular basement membrane disease associated with bronchial carcinoma and monoclonal gammopathy. Glomerulonephritis with coexistent immune deposits and antibasement membrane activity. Henoch-Schonlein purpura and pulmonary hemorrhage: a report and literature review. Binding of anti-basement membrane antibody to alveolar basement membrane after intratracheal gasoline instillation in rabbits. However, it appeared that much less severely affected people did relatively well with out plasma trade. Retrospective analyses primarily based on a lot of sufferers provide helpful data (Couser, 1988; Cui et al. The kidney outcome for this cohort was strongly influenced by kidney operate at presentation. However, amongst sufferers who wanted dialysis at presentation, affected person and kidney survival have been reduced to 65% and 8% at 1 12 months, respectively. Compared to almost one hundred pc mortality from pulmonary haemorrhage and kidney failure in historical sequence, this therapy technique represent a major improvement and is widely adopted in a quantity of centres. In a retrospective evaluation involving 221 patients Beijing, it was demonstrated that, as compared with corticosteroids alone and corticosteroids plus cyclophosphamide, the mixture of plasma exchange, corticosteroids and cyclophosphamide has an general useful impact on patient and kidney survival. Using immunoadsorption against staphylococcal protein A to adsorb circulating IgG antibodies (Bygren et al. Cytotoxic and immunosuppressive agents Cyclophosphamide was first used successfully by Couser in 1974 (Couser, 1974), and is a important element of therapy. Alternative immunosuppressive agents have been tried in only a few instances, including azathioprine, ciclosporin, mycophenolate mofetil, and the anti-B-cell antibody rituximab (Pepys et al. Couser (1988) reviewed 22 printed uncontrolled studies involving 186 patients, and reported a beneficial impact of plasmapheresis on pulmonary disease in round 90% of sufferers, and a beneficial effect of plasmapheresis Outcomes and prognostic factors Outcomes of the Hammersmith cohort (Levy et al. Add 150�300 mL contemporary frozen plasma on the end of each pheresis session if sufferers have pulmonary haemorrhage, or have had recent surgery, including kidney biopsy. Deciding to not deal with the kidney prognosis of dialysis-dependent sufferers with 100 percent crescents in enough biopsy pattern is extraordinarily poor. It has been advised that, in the absence of pulmonary haemorrhage, aggressive immunosuppression must be withheld, for the risks of remedy outweigh the potential advantages (Flores et al. These sufferers emphasize the worth of an urgent renal biopsy even when the diagnosis has been established serologically. Cyclophosphamide Plasmapheresis from the United States, Europe, China, and Japan, patient survival at 6�12 months is roughly 67�94%, and kidney survival is about 15�58% (Johnson et al. Predictors of kidney survival are serum creatinine at presentation, the need for dialysis at presentation, and the share of glomerular crescents (Johnson et al. Serum creatinine at presentation is an unbiased predictor for renal failure (Cui et al. Patients who required dialysis at presentation might not be able to come off dialysis, despite aggressive treatment (Levy et al. The most optimistic examine noticed that no patients with a mix of dialysis at presentation plus one hundred pc crescents on kidney biopsy recovered kidney function sufficiently to come off dialysis (Levy et al. A survey of several studies reveals dialysis dependence at analysis in a median of 55% (range 12�83%) of patients, 100% crescents on kidney biopsy in 20. The use of less aggressive methods or merely supportive treatment Relapse and recurrence In the early phase, immunological relapse should be distinguished from haemodynamic adjustments or drug effects, and from exacerbation of damage in association with infection. Autoantibodies seem to disappear spontaneously after 12�18 months (Wilson and Dixon, 1981; Levy et al. Recurrences of pulmonary haemorrhage over a few years are described within the literature (Dahlberg et al. Treatment of recurrences is identical to that of preliminary illness and doubtless has a better likelihood of success. It is attributable to the development of antibodies to antigens that are lacking or altered in the recipient. Enumeration of lymphocyte populations in complete peripheral blood of sufferers with antibody-mediated nephritis during treatment with cyclosporin A. Antiglomerular basement membrane antibody mediated illness within the British Isles 1980-4. Complete restoration of renal operate in a dialysis-dependent affected person with Goodpasture syndrome. Rapidly progressive glomerulonephritis: classification, pathogenetic mechanisms, and remedy. Anti-glomerular basement membrane illness: outcomes of different therapeutic regimens in a large single-center chinese language cohort research. Goodpasture syndrome: re-exacerbations related to intercurrent infections, Revista Clinica Espa�ola, 195, 761�4. Recurrence of circulating anti-glomerular basement membrane antibody three years after immunosuppressive remedy and plasma change. Loss of tolerance with the consequent growth of autoimmune illness requires both an underlying genetic susceptibility and exposure to an environmental set off. The genetic basis of that is proven to be owing to a copy number polymorphism of Fcgr3 (Aitman et al.
Drudenfuss (European Mistletoe). Fosamax.
- Pancreatic cancer.
- How does European Mistletoe work?
- Are there safety concerns?
- Head and neck cancer.
- Reducing the side effects of chemotherapy and radiation therapy, breast cancer, colorectal cancer, gastric cancer, bladder cancer, high blood pressure, internal bleeding, hemorrhoids, seizures, high cholesterol, gout, depression, sleep disorders, headache, menstrual disorders, and many other conditions.
- Dosing considerations for European Mistletoe.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96882
These sufferers sometimes have a really low urine sodium focus and high urine osmolality (Table 28 pregnancy jokes cartoons fosamax 35 mg purchase with mastercard. One exception is vomiting menopause signs and symptoms 70 mg fosamax visa, in which urine sodium is larger because alkalosis-induced bicarbonaturia causes natriuresis womens health network fosamax 35 mg buy with amex. A higher parameter in this setting is urinary chloride menopause groups 70 mg fosamax cheap mastercard, which is often very low, as a end result of hydrogen chloride is misplaced with vomiting. Renal insufficiency Several causes of hyponatraemia are also related to acute or persistent kidney illness, together with extrarenal sodium loss, heart failure, liver cirrhosis, hepatorenal syndrome, renal artery stenosis, and salt-losing nephropathy. In these issues, hyponatraemia is normally caused by baroreceptor-mediated vasopressin release, while renal insufficiency is commonly of prerenal origin. Therefore, the calculation of the fractional sodium excretion is useful, which is often low (< 1%) besides in salt-losing nephropathy. A more separate and uncommon entity is the hyponatraemic hypertensive syndrome, by which unilateral renal artery stenosis causes significant hypertension, hyponatraemia, hypokalaemia, polydipsia, and polyuria. This syndrome is most often seen in asthenic elderly girls who smoke, but it has also been reported in youngsters with fibromuscular dysplasia (Agarwal et al. Chronic kidney illness also can play a causal position in the pathogenesis of hyponatraemia. When the glomerular filtration fee may be very low, or if sufferers are already present process renal replacement remedy, free water clearance is limited or absent. A recent study confirmed that hyponatraemia in this setting was associated with poor outcome, as a result of a lower pre-dialysis serum sodium was associated with an elevated risk of dying (Waikar et al. Hyponatraemia can be comparatively common among sufferers undergoing peritoneal dialysis and may be related to hyperglycaemia, depending on the composition of dialysis fluid used, or a catabolic state with potassium depletion (Zevallos et al. All these settings are usually characterized by the intake or administration of a appreciable quantity of electrolyte-free water in a brief period of time, with vasopressin acting concurrently to forestall excretion. By introducing a hypertonic answer into the extracellular space, water might be attracted from the intracellular house. This will cut back the cell swelling related to acute hyponatraemia and is effective in treating cerebral oedema. Several formulae are available to assist predict the rise in serum sodium when therapy with hypertonic saline is commenced. The Adrogu�Madias formulation predicts what the rise in serum sodium might be when 1 L of a given resolution is administered to a affected person. A simpler strategy was lately proposed as preliminary emergency therapy for acute hyponatraemia, particularly a bolus infusion of 3% sodium chloride (100 mL or 2 mL/kg, repeated as much as two times) (Moritz and Ayus, 2010). Notably, whatever approach is used, the serum sodium focus should be measured regularly during remedy with hypertonic saline (preferably each 2�4 hours). Treatment and end result General principles the remedy of hyponatraemia relies on the next rules: acute hyponatraemia must be handled instantly whatever the trigger, whereas therapy ought to be directed in course of the underlying trigger in chronic hyponatraemia, whereas avoiding rapid or over-correction. Because the time at which hyponatraemia developed is incessantly unknown, the decision whether hyponatraemia is acute or continual typically is dependent upon the evaluation of symptoms, but should assumed to be persistent, if onset and period are unclear. Although severe neurological signs corresponding to seizures and coma ought to all the time point within the course of acute hyponatraemia, more subtle signs can happen in each acute and chronic Auto-correction and over-correction It is important to concentrate on the potential for auto-correction or over-correction in the course of the therapy of hyponatraemia. Auto-correction often happens when the stimulus for vasopressin release abruptly abates, which is then adopted by the fast excretion of a dilute urine. Within minutes after the development of hypotonicity, water acquire causes swelling of the brain and a decrease in osmolality of the mind. Partial restoration of brain volume happens within a couple of hours because of cellular lack of electrolytes (rapid adaptation). The normalization of mind volume is accomplished within several days by way of lack of organic osmolytes from brain cells (slow adaptation). Proper correction of hypotonicity re-establishes regular osmolality with out risking harm to the brain. Overly aggressive correction of hyponatraemia can result in irreversible mind harm. Conversely, over-correction usually happens throughout remedy with hypertonic saline when the actual rise in serum sodium Box 28. The maximum correction rates characterize limits and will due to this fact not be the objective of therapy. Acute and/or symptomatic hyponatraemia could initially be corrected sooner with 1�2 mmol/L/hour. If hyponatraemia is unquestionably continual or if there are danger components for the osmotic demyelination syndrome (see Table 28. Auto-correction and overcorrection must be anticipated in the course of the treatment of hyponatraemia by frequently monitoring the serum sodium concentration, urine osmolality, and urine output. If urine manufacturing will increase and urine tonicity decreases, this suggests the onset of a water diuresis with the chance of a speedy rise in serum sodium. If the maximum correction price is exceeded throughout auto-correction or over-correction, measures ought to be taken to curtail the rise in serum sodium focus. In experimental animals, re-induction of hyponatraemia after speedy over-correction of hyponatraemia reduces mortality (Gankam-Kengne et al. The therapy modalities for the totally different causes of hyponatraemia are proven in Table 28. Some of the remedies are simple, corresponding to discontinuation of the offending drug, or treatment with steroids or thyroid hormone in hyponatraemia as a outcome of hypocortisolism or hypothyroidism. These treatments are directed to restricting the intake of electrolyte-free water or selling its excretion and include fluid restriction, loop diuretics, urea, and demeclocycline. The upper formula can be utilized to predict the rise in serum sodium ([Na]s) when 1 L of a given infusate is run. When potassium is added to the infusate, this concentration must be included within the formula ([Na + K]inf). The lower method can be used to calculate the quantity of the infusate essential to achieve the specified rise in serum sodium (Desired [Na]s) by dividing this number with the calculated change in serum sodium concentration in the higher part of the formulation ([Na]s). Loop diuretics inhibit the technology of a focus gradient in the renal medulla and promote the excretion of sodium and water. Urea causes an osmotic diuresis, which also promotes the excretion of electrolyte-free water. Demeclocycline is an antibiotic with nephrogenic diabetes insipidus as a facet effect; this effect could be exploited throughout hyponatraemia to induce a water diuresis. In many sufferers, particularly the elderly, low solute intake performs a contributory position in the improvement of hyponatraemia. Therefore, fluid restriction or loop diuretics could also be mixed with increased dietary consumption of sodium and protein (or alternatively sodium chloride tablets). However, there might be causes of persistent hyponatraemia that stay troublesome to treat and in which extra focused therapy would be desirable. The advocate fluid consumption could be calculated on the basis of the ratio between the urinary tonicity (urinary sodium plus urinary potassium concentration) and the serum sodium focus. The really helpful fluid consumption is < 500 mL/day for a ratio > 1500�700 mL/day for a ratio near 1, and < 1 L/day for a ratio < 1. Vasopressin receptor antagonists Vasopressin receptor antagonists are non-peptide molecules that competitively inhibit a quantity of of the human vasopressin receptors V1a, V1b, or V2. The proposed molecular mechanism of vasopressin receptor antagonists is that they penetrate deeper and more selectively into the binding pocket of the vasopressin receptor sort 2 than native vasopressin, but without activating the receptor (Decaux et al. Conivaptan is a mixed V1a/V2 receptor antagonist for intravenous use, whereas tolvaptan, mozavaptan, and lixivaptan are orally energetic V2-selective receptor antagonists. This impact is mainly attributed to inhibition of the V2 receptor in the accumulating duct, which prevents vasopressin from recruiting aquaporin-2 water channels to enhance water reabsorption. Co-inhibition of the V1a receptor, which is situated in vascular smooth muscle, may be helpful in decreasing coronary vasoconstriction, myocyte hypertrophy, and vascular resistance in sufferers with heart failure, however definitive research on this are lacking (Goldsmith, 2006). In all trials, vasopressin receptor antagonists successfully raised serum sodium and helped to right hyponatraemia. In addition, a optimistic impact on some secondary endpoints was noticed, including an improved mental state and reductions in physique weight, dyspnoea, and ascites (Schrier et al. Thus, vasopressin receptor antagonists are efficient for the correction of hypervolaemic or euvolaemic hyponatraemia, as was additionally confirmed by a meta-analysis (Rozen-Zvi et al. Hyponatremic-hypertensive syndrome with renal ischemia: an underrecognized dysfunction. Hyponatremia: a prospective analysis of its epidemiology and the pathogenetic position of vasopressin. Hyponatremia, convulsions, respiratory arrest, and everlasting mind harm after elective surgical procedure in healthy women. Secretion of mind natriuretic peptide in sufferers with aneurysmal subarachnoid haemorrhage.
Specifications/Details
While acidaemia could also be extreme womens health pavilion fosamax 70 mg buy otc, injury to the brain is the main concern in these sufferers women's health center wooster ohio cheap 35 mg fosamax. As a outcome womens health 3 week abs purchase fosamax 70 mg otc, there might be a sudden rise in the manufacturing of H+ and L-lactate anions in areas of the mind where the metabolic rate is extra speedy and/or ones that have the lowest reserve of thiamine women's health issues research inequality fosamax 35 mg cheap on-line. Treatment is obviously to administer thiamine early in the middle of remedy earlier than the ketoacids concentration in plasma falls. A continual regular state of L-lactic acidosis is commonly current and the causes are a low fee of elimination of L-lactic acid often related to issues with the liver as a end result of hepatitis, substitute of normal liver cells. In sufferers with a malignancy and hepatic metastases, the mechanisms that contribute to the L-lactic acidosis are the alternative of a considerable number of liver cells with tumour cells to impair L-lactic acid elimination or manufacturing of metabolites by tumour cells such because the amino acid tryptophan, which can inhibit the conversion of pyruvate to glucose within the liver, and/or the truth that ischaemic tumour cells will produce more L-lactic acid. There are two potential mechanisms whereby anti-retroviral agents might trigger L-lactic acidosis. Second, these medication may lead to substitute of liver parenchyma with storage fats (steatosis) (Coghlan et al. Methanol is transformed to formaldehyde by alcohol dehydrogenase within the liver, but a excessive concentration of methanol is required for rapid charges of oxidation. Later, when methanol is transformed to formaldehyde by retinol dehydrogenase, blurred vision and blindness might develop. Ethylene glycol is converted to glycoaldehyde by alcohol dehydrogenase within the liver, the affinity of this enzyme for ethylene glycol is near one hundred instances lower than for ethanol; thus, the speed of metabolism of ethylene glycol is speedy solely when its focus is excessive. Glycoaldehyde is further metabolized to glycolic acid by hepatic aldehyde dehydrogenase, which is the major acid that accumulates in ethylene glycol poisoning (Oh et al. One per cent or less of glycolic acid is transformed to oxalic acid, mainly by the action of the enzyme lactae dehydrogenase. Virtually all oxalate produced is precipitated as calcium oxalate, contributing to acute renal failure and hypocalcaemia. The major finish product of glycolic acid metabolism is glycine through transamination with alanine; vitamin B6 is a cofactor. After a latent interval of about 4�12 hours, patients develop nausea, vomiting, hyperventilation, elevated blood pressure, tachycardia, tetany, and convulsions. The tetany is most probably attributable to hypocalcaemia, which is believed to be the outcome of deposition of calcium oxalate crystals. Renal failure is frequent and normally develops 36�48 hours after the ingestion of ethylene glycol; glycoaldehyde appears to be the primary toxin. The ideas of therapy of methanol or ethylene glycol poisoning are virtually identical. They embody administration of ethanol to obtain blood concentrations of about 20 mmol/L to cut back metabolism, and elimination of these poisonous alcohols and their metabolites by haemodialysis. One may administer fomepizole, an inhibitor of hepatic alcohol dehydrogenase, as an alternative of ethanol. Salicylate intoxication the main issue with an overdose of aspirin is the toxicity associated to the impact of salicylate anions in cells (Oh et al. It is also potential that this natural acid uncouples oxidative phosphorylation (Miyahara and Karler, 1965). A modest degree of uncoupling of oxidative phosphorylation can enhance the production of ketoacids in the liver. In extreme intoxications, the diploma of uncoupling of oxidative phosphorylation may be extreme. Hypoglycaemia is common in sufferers with salicylate intoxication, which probably displays elevated utilization of glucose by the mind (due to uncoupling of oxidative phosphorylation) and/or impaired gluconeogenesis (Oh et al. Treatment is initially aimed at stopping the buildup of salicylates in mind cells. When the inhalation of toluene stops, finally the manufacturing of hippuric acid might be diminished, however there can be a lag of 1�3 days, due to the big volume of distribution of toluene. Dialysis ought to be instituted if the salicylate blood level exceeds 6 mmol/L (90 mg/dL). If the salicylate blood stage exceeds four mmol/L (60 mg/dL), dialysis should be thought-about, particularly if additional absorption is anticipated. In sufferers with an unexplained decreased level of consciousness, dialysis ought to be began, even at decrease ranges of salicylate in blood, due to the poor prognosis. Haemodialysis is more environment friendly for the removing of salicylate, but peritoneal dialysis could also be thought of if there might be a long delay earlier than haemodialysis may be initiated. Furthermore, sufferers with salicylate intoxication might have increased capillary permeability and be in danger for pulmonary oedema and cerebral oedema following extreme fluid administration. Acetazolamide, a carbonic anhydrase inhibitor, could additionally be useful in the remedy for salicylate intoxication to improve excretion of salicylate anions in the urine. There is some experimental proof in people to suggest that 250 mg of acetazolamide has a tubular effect that lasts for roughly sixteen hours (Bayoumi et al. Therefore, one may use a low dose of acetazolamide instead of alkali therapy in a patient with a excessive blood pH. Patients who sniff glue for its intoxicating properties absorb a significant amount of toluene (methylbenzene). Toluene is metabolized by way of a series of reactions in the liver to hippuric acid (Carlisle et al. Although people lack the enzyme D-lactate dehydrogenase, metabolism of D-lactate happens via the enzyme D-2-hydroxyacid dehydrogenase. There are three further factors that should be noted with respect to D-lactic acidosis. Insulin may be helpful by reducing the rate of oxidation of fatty acids and therefore allowing a higher rate of oxidation of these organic acids. Diet alkali: the alkali load is derived mainly from dietary fruit and vegetables. Because patients with renal insufficiency are often placed on a low K+ food regimen, they eat much less alkali and, as a result, are extra probably to turn into acidaemic. Experimental proof from research in rats strongly suggests that acidaemia is a catabolic signal in uraemia, though proof from human data is less robust (Weinstein et al. It is now recommend that acidaemia in patients with persistent kidney disease must be corrected. From a therapeutic standpoint, the acidaemia in these patients is normally delicate and problems because of the acidosis are minor, which argues towards alkali therapy in adults. For remedy, one must first identify and deal with emergencies that could be present on admission. The rationalization could also be that these sufferers developed worsening acidaemia with the administration of saline, which outcomes in venoconstriction and an acute improve in central blood volume. Enhancing the absorption of NaCl secreted by the intestinal tract diminishes the volume of diarrhoea fluid. Amphotericin B could cause a low web H+ secretion within the distal nephron, due to a back-leak of H+ into -intercalated cells. Because of the medullary interstitial disorder, these patients may have a reduced urinary concentrating capability. Hyperkalaemia could additionally be current if the disease course of additionally includes the distal cortical nephron. The issues regarding alkali remedy had been discussed above within the subgroup with diminished net H+ secretion and apply in this setting too. For persistent hyperkalaemia to be current, the disease course of must involve the late cortical distal nephron, the main web site of K+ secretion. The following concepts are central to our understanding of why metabolic alkalosis develops (Halperin et al. They also provide the idea for our scientific strategy to this diagnostic category, and to the design of optimal remedy. Concept: electroneutrality should be present in each body compartment and within the urine. Four aspects of the clinical image in a patient with metabolic alkalosis advantage cautious consideration and include the medical historical past. The first step is to rule out the frequent causes of metabolic alkalosis such as vomiting and use of diuretics. A primary respiratory acidosis could also be current if respiratory muscle weakness outcomes from hypokalaemia.
Syndromes
- Extra fingers or toes (polydactyly)
- Neurological conditions
- Bone pain
- Kidney failure
- Fluphenazine (Prolixin)
- Wheezing
- Recent cognitive decline in an elderly person, even without a history of brain injury
- Joint swelling
- Familial CJD occurs when a person inherits the abnormal prion from a parent (inherited CJD is rare)
Related Products
Additional information:
Usage: gtt.
Tags: generic 35 mg fosamax visa, generic 35 mg fosamax with amex, fosamax 35 mg buy cheap line, fosamax 70 mg purchase online, fosamax 35 mg cheap free shipping, 35 mg fosamax cheap fast delivery, purchase fosamax 35 mg amex, purchase fosamax 35 mg without a prescription, order 70 mg fosamax with visa, order fosamax 70 mg amex, buy 70 mg fosamax overnight delivery, fosamax 35 mg cheap fast delivery, buy 35 mg fosamax visa, buy discount fosamax 70 mg line, order fosamax 70 mg free shipping, fosamax 70 mg discount line
9 of 10
Votes: 161 votes
Total customer reviews: 161
Customer Reviews
Connor, 54 years: It is beneficial that a optimistic strip check is followed by a quantitative willpower (American Diabetes Association, 1994). Further phenotypic refinement led to the recognition of two syndromes: Bartter syndrome and Gitelman syndrome (Gitelman et al.
Goose, 39 years: Inspection Colour Normal urine colour varies from almost clear to darkish yellow as a end result of urobilin pigment. A mathematical equation to differentiate overload proteinuria from tubulo-interstitial involvement in glomerular illnesses.
Felipe, 46 years: Despite the identified limitations, methods based mostly on the Jaffe response are still extensively used for measuring serum creatinine. Ionizing radiation may be electromagnetic radiation such as X-rays or gamma rays or particulate radiation similar to alpha particles, beta particles, Introduction In 1895, the German physicist Wilhelm Conrad R�ntgen discovered X-rays when he noted that a fluorescent display screen began to glow while he was experimenting with a vacuum tube.
Jorn, 63 years: Epitopes on the hinge area now uncovered in the absence of galactose are recognized by IgG and IgA1 with antiglycan specificities (Suzuki et al. Conservative management is due to this fact applicable for the great majority of sufferers, as is remaining open to an alternate diagnosis.
Mason, 43 years: Behavioral problems in the frontal and temporal variants of frontotemporal dementia. To verify the hyperosmolar state, and to determine if different substances are involved within the hypertonic state (such as glucose), plasma osmolality must be measured.