
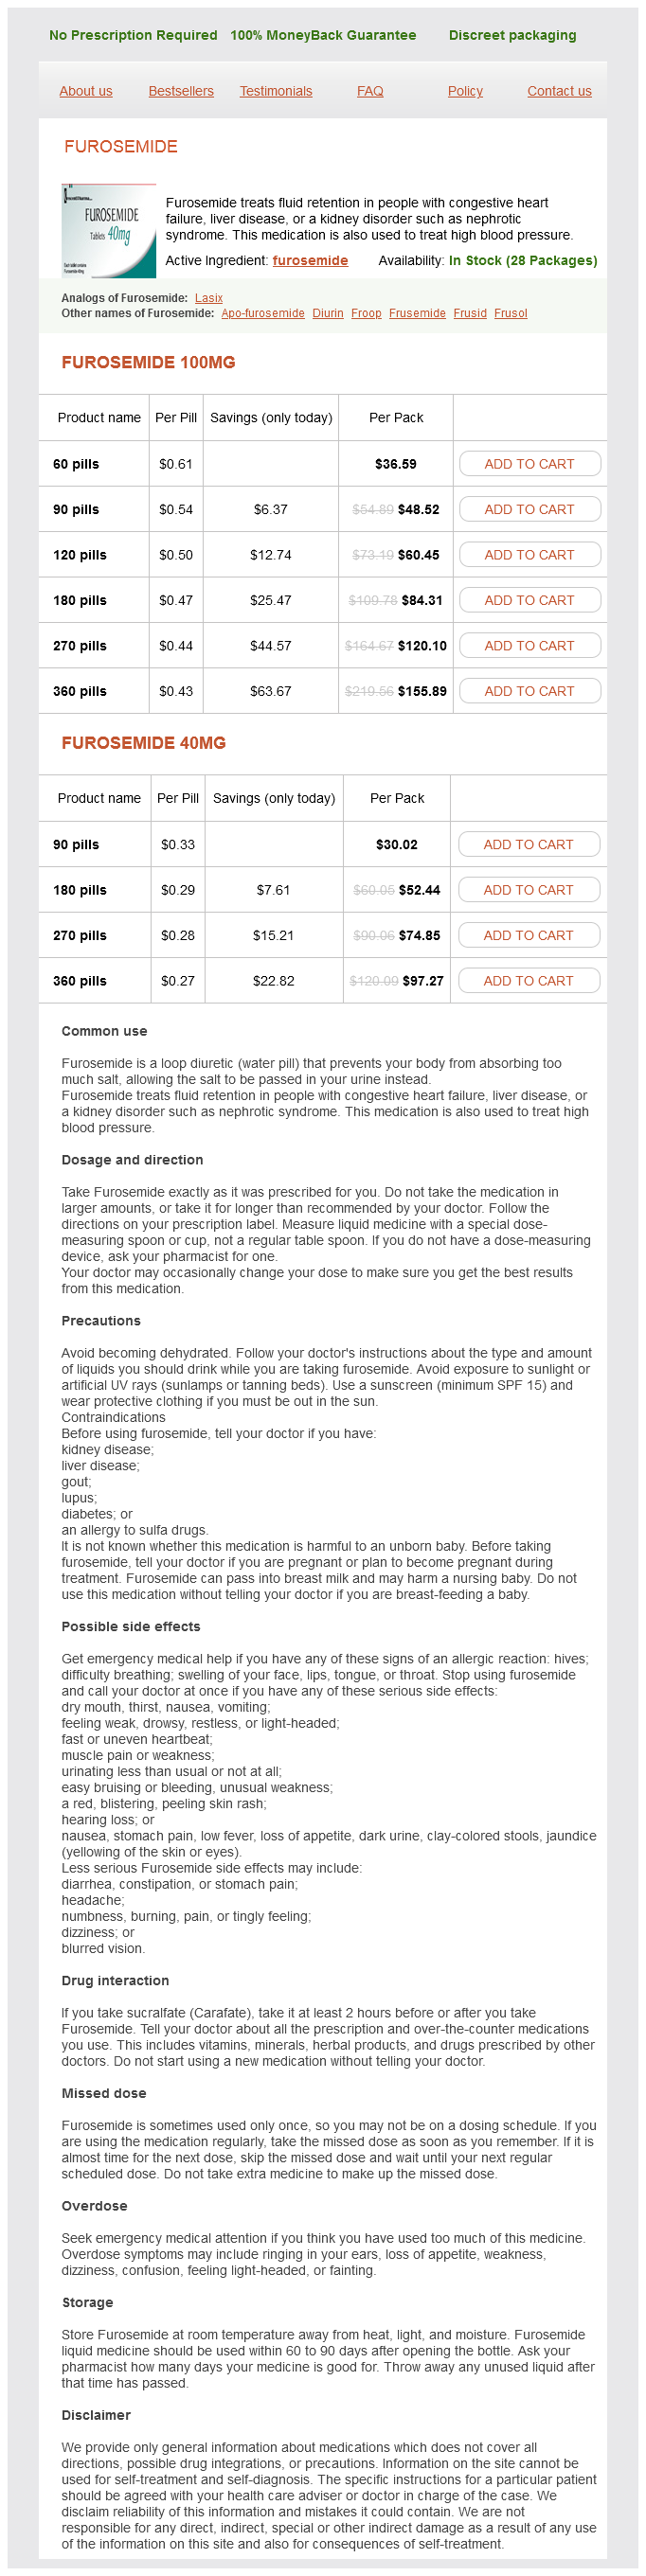
Furosemide
Furosemide 100mg
- 60 pills - $36.59
- 90 pills - $48.52
- 120 pills - $60.45
- 180 pills - $84.31
- 270 pills - $120.10
- 360 pills - $155.89
Furosemide 40mg
- 90 pills - $30.02
- 180 pills - $52.44
- 270 pills - $74.85
- 360 pills - $97.27
Furosemide dosages: 100 mg, 40 mg
Furosemide packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 712
Only $0,29 per item
Description
Case report: incisional hernia as a complication of utmost lateral interbody fusion heart attack demi lovato mp3 furosemide 40 mg without a prescription. The posterior transpedicular strategy for circumferential decompression and instrumented stabilization with titanium cage vertebrectomy reconstruction for spinal tumors: consecutive case sequence of fifty sufferers hypertension causes and treatment 40 mg furosemide cheap with visa. Transpedicular partial corpectomy with out anterior vertebral reconstruction in thoracic spinal metastases arteria iliaca interna purchase 100 mg furosemide fast delivery. Technique and clinical outcomes of minimally invasive reconstruction and stabilization of the thoracic and thoracolumbar spine with expandable cages and ventrolateral plate fixation blood pressure is lowest in generic furosemide 40 mg amex. Traumatic thoracolumbar spinal injury: an algorithm for minimally invasive surgical administration. Minimally invasive spine surgery in the therapy of thoracolumbar and lumbar backbone trauma. Minimally invasive corpectomy and posterior stabilization for lumbar burst fracture. Minimally invasive thoracic corpectomy: surgical methods for malignancy, trauma, and sophisticated spinal pathologies. Sagittal stability and spinopelvic parameters after lateral lumbar interbody fusion for degenerative scoliosis: a case-control examine. Anterior lumbar interbody fusion as compared with transforaminal lumbar interbody fusion: implications for the restoration of foraminal height, native disc angle, lumbar lordosis, and sagittal steadiness. A radiological comparison of anterior fusion rates in anterior lumbar interbody fusion. Supplementary stabilization with anterior lumbar intervertebral fusion�a radiologic review. Enhancing the stability of anterior lumbar interbody fusion: a biomechanical com- 56. Biomechanical evaluation of anterior lumbar interbody fusion with an anterior lumbosacral fixation screw-plate: comparison to stand-alone anterior lumbar interbody fusion and anterior lumbar interbody fusion with pedicle screws in an unstable human cadaver mannequin. In vitro biomechanical comparability of an anterior and anterolateral lumbar plate with posterior fixation following single-level anterior lumbar interbody fusion. Anterior lumbar interbody fusion with stand-alone interbody cage in treatment of lumbar intervertebral foraminal stenosis: comparative research of two several types of cages. In 1911, Hibbs2 launched the noninstrumented osseous fusion to stabilize the deformed spine. Fritz Lange,three in the 1900s, internally splinted the spine using metal wires (later coated with tin) and mounted them to the spinous processes with a paraffin-sublimate silk. He adopted this advance with the development of the hook-rod system, which was supplemented with osseous fusion to appropriate idiopathic, neuromuscular, or acquired deformities. Long constructs have been required, leading to occasional loosening of the instrumentation. In some circumstances, using distraction instrumentation in the thoracolumbar backbone for correction of coronal plane deformities led to the lack of lumbar lordosis and flat-back syndrome4; fusions all the means down to the sacrum and pseudarthrosis had been additionally risk factors for flat-back syndrome. Challenges of the system included the need for long constructs and the increased incidence of neurological complications. Likewise, using translaminar side joint screws was first described by Magerl13 in 1984. In the 1970s, Roy-Camille and associats14,15 described using posterior plates with sagitally positioned screws by way of the pedicles and articular processes. The easy approach for pedicle screws, as opposed to the anatomic method, was a modification made by Roy-Camille however popularized by Suk and colleagues. Nonetheless, in the yr 1977, Magerl17 revealed his "fixateur externe" for decrease thoracic and lumbar spine, and after some years, Dick and colleagues18 launched the "fixateur interne. Pedicle screws appeared superior to other posterior instrumentation being used at the time (hooks and sublaminar wires) in respect to their pullout strength and load-sharing capacity. They also supplied threecolumn fixation, which might be used to distract, compress, and rotate the spine. The backbone, as the osseous axis of the physique, may be divided into four sections: cervical, thoracic, lumbar, and pelvic or sacrococcygeal. The thoracic vertebral body has comparable sagittal and transverse diameters, and its posterior portion is excavated because of the spinal cord. On both sides of the vertebral body, proximal to the anterior border of the pedicle, lie two semicircular articular surfaces for the rib heads. The spinous processes, leaning caudally, are long and triangular though not as bifid as those within the cervical spine. The transverse processes begin at the posterior a part of the pedicle and follow obliquely each posteriorly and laterally. Anteriorly, each has a small articular surface for the tuberosity of the corresponding rib. They face posteriorly and laterally, whereas the inferior articular processes face frontally and medially. Study of the bony anatomy is crucial within the consideration of pedicle screw insertions, notably the relationship between the transverse and articular processes and the pedicles in sawbones and cadavers. There are numerable variations within the dimensions and angulation of the thoracic pedicles. General anatomic considerations to be famous are as follows: � the width of the pedicle decreases from T1 to T4, and will increase from T4 to T12. At T1 via T2, the angle is 15 to 20 degrees; at T3, 10 to 15 degrees; and at T4 through T12, 5 to 15 degrees. In the lower thoracic spine, the sides have a extra sagittal orientation, offering more stability in opposition to rotation. The entry points of the thoracic pedicles are completely different within the higher, middle, and decrease areas of the thoracic spine. From T1 to T3 and from T10 to T12 the pedicle entry point for screw fixation is roughly on the intersection of a horizontal line passing alongside the midline of the transverse process and a vertical line passing through the center to lateral aspect of the facet. If the overlying inferior side of the superior vertebra covers the superior articular strategy of the vertebra to be instrumented, the aspect can be resected (except on the higher end of a assemble to keep away from destabilization). In the center thoracic spine, from T4 to T9, the entry level for the pedicle is cranial to the transverse course of. For the sagittal trajectory of the screws within the thoracic spine, a general tip is to drill perpendicular to the spinal curvature at the given level. In this system, the screw placement is managed with intraoperative fluoroscopy. The entry point in each vertebra is approximately on the level of the mammillary course of: lateral to the extent of the superior articular process at the intersection with the transverse course of. The path for the pedicle screws in the lumbar vertebrae in the transverse plane angles from lateral toward medial. The angular improve from L1 to L5 is 5 levels at every progressive stage, starting with 10 to 15 levels at L1. For L1 to L5, the direction of a pedicle screw in the sagittal plane should be parallel to the superior finish plate of the vertebra. The course in the sagittal aircraft for S1 must be slightly ascending towards the superior end plate (Table 329-1) in order to try to capture the sacral promontory with the screw tip. Muscular layers are shaped by the following three planes: � Superficial layer: � Trapezius muscle between C2 and T12 � Latissimus dorsi muscle between T6 and the lumbosacral fascia � Rhomboid muscles: minor between C7 and T1 and major between T2 and T5 � Intermediate layer: serratus posterior muscle � Deep layer: sacrospinal, semispinal, multifidus, and rotator muscle tissue Knowledge of the anastomotic terminal branches of the segmental arteries are essential in the dissection for thoracolumbar fusion. Interarticular, inferior, and superior articular arteries are common sources of profuse bleeding and should be coagulated promptly. The anterior transverse artery, which travels under the transverse course of with the exiting nerve root, must be preserved. Illustration exhibiting some morphometric characteristics of the thoracic vertebrae from T1 to T12. The pedicle entry points (+) and their relationship to the transverse processes, laminae, and facets are proven within the center. However, this strategy could be problematic in sufferers with anatomic variation in the variety of ribs or with transitional anatomy and in very overweight sufferers, in whom the ribs are unclear on radiographs. For open surgical procedures, the T12 rib and the L1 transverse process can be palpated although a midline incision. Several key biomechanical questions have to be addressed within the planning of thoracic and lumbar instrumentation; a few of them are still a matter of debate, as follows: � There must be a stability between minimizing the number of concerned segments and providing enough stabilization.
Branched-Chain Amino Acids. Furosemide.
- Reducing muscle breakdown during exercise.
- Enhancing exercise or athletic performance.
- Decreasing symptoms associated with mania.
- What other names is Branched-chain Amino Acids known by?
- What is Branched-chain Amino Acids?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96966
Nimodipine may be effective in lowering the neurological consequences of vasospasm after head damage hypertension follow up furosemide 100 mg sale. However heart attack and vine cover furosemide 40 mg buy without a prescription, the one subgroup of head-injured patients that has been found to benefit are these with subarachnoid hemorrhage heart attack 8 trailer 40 mg furosemide generic free shipping. If the affected person is still symptomatic after quantity enlargement arrhythmia multiforme buy furosemide 100 mg amex, then a pressor agent must be added to elevate blood strain. The selection of pressor brokers is controversial, as mentioned beforehand beneath Treatment of Secondary Ischemic Processes: Cerebral Ischemia. Information about cardiac output, obtained from the Swan-Ganz catheter, could be helpful in this decision. If cardiac output is normal or elevated, then a pressor agent similar to phenylephrine or norepinephrine is prone to be more practical in raising blood stress. In a report of vasospasm related to blast damage, sufferers obtained medical administration and aggressive endovascular interventions (endovascular nicardipine and/or angioplasty); though there was no early improvement in neurological perform, there was a transparent improvement in bloodflow velocities measured by transcranial Doppler. Brain Trauma Foundation, American Association of Neurological Surgeons, Congress of Neurological Surgeons, et al. Early induction of hypothermia for evacuated intracranial hematomas: a post hoc evaluation of two clinical trials. Regional cerebrovascular and metabolic results of hyperventilation after extreme traumatic mind damage. The "Lund Concept" for the remedy of severe head trauma-physiological ideas and clinical application. Effect of erythropoietin and transfusion threshold on neurological recovery after traumatic brain damage: a randomized medical trial. Rotterdam computed tomography score as a prognosticator in head-injured patients present process decompressive craniectomy. Predicting end result after traumatic mind damage: growth and validation of a prognostic rating primarily based on admission characteristics. Mortality prediction in head trauma sufferers: performance of Glasgow Coma Score and common severity systems. Regional variations in affected person characteristics, case administration, and outcomes in traumatic mind damage: experience from the tirilazad trials. A multicenter trial on the efficacy of utilizing tirilazad mesylate in circumstances of head injury. Immediate coma following inertial brain damage dependent on axonal damage in the brainstem. Importance of a dependable admission Glasgow Coma Scale score for determining the need for evacuation of posttraumatic subdural hematomas: a prospective research of 65 sufferers. Acute subdural hematoma: severity of damage, surgical intervention, and mortality. Intraoperative jugular desaturation during surgery for traumatic intracranial hematomas. Intraoperative monitoring of substrate supply throughout aneurysm and hematoma surgery: initial experience in 16 patients. Preemptive craniectomy with craniotomy: what function within the management of severe traumatic mind harm Outcome after acute traumatic subdural and epidural haematoma in Switzerland: a singlecentre expertise. The epidemiology of surgically handled acute subdural and epidural hematomas in sufferers with head accidents: a population-based examine. Acute traumatic intracerebral haematomas: determinants of end result in a retrospective sequence of 202 cases. Moderate posttraumatic hypothermia decreases early calpain-mediated proteolysis and concomitant cytoskeletal compromise in traumatic axonal injury. Effect of hyperventilation on cerebral blood circulate in traumatic head damage: scientific relevance and monitoring correlates. Intravascular coagulation: a serious secondary insult in nonfatal traumatic brain harm. Excitotoxic mechanisms and the position of astrocytic glutamate transporters in traumatic brain injury. Measuring the burden of secondary insults in head-injured sufferers during intensive care. Outcome in 200 consecutive cases of extreme head injury handled in San Diego County: a prospective evaluation. Cerebral blood circulate, arteriovenous oxygen distinction, and consequence in head injured sufferers. Traumatic subarachnoid hemorrhage on the computerized tomography scan obtained at admission: a multicenter assessment of the accuracy of analysis and the potential impression on patient outcome. Transiently increased basilar artery circulate velocity following severe head harm: a time course transcranial Doppler study. Transcranial Doppler monitoring in head injury: relations between kind of injury, move velocities, vasoreactivity, and outcome. Evaluation of posttraumatic cerebral blood circulate velocities by transcranial Doppler ultrasonography. A comparative analysis of multi-level computer-assisted choice making methods for traumatic injuries. Relationship of aggressive monitoring and treatment to improved outcomes in severe traumatic mind injury. Goal directed mind tissue oxygen monitoring versus standard administration in traumatic mind injury: an evaluation of in hospital recovery. The effect of intracerebral hematoma location on the chance of brain-stem compression and on medical consequence. Middle cerebral artery blood circulate velocity and steady xenon-enhanced computed tomographic blood flow throughout balloon check occlusion of the internal carotid artery. Correlation of transcranial Doppler sonography imply flow velocity with cerebral blood move in sufferers with intracranial pathology. Cerebral vasospasm diagnosis by means of angiography and blood velocity measurements. Evaluation of a model new fiberoptic catheter for monitoring jugular venous oxygen saturation. Evaluation of a regional oxygen saturation catheter for monitoring SjvO2 in head injured sufferers. Validation of the Edslab dual lumen oximetry catheter for steady monitoring of jugular bulb oxygen saturation after severe head injury. Monitoring of cerebral oxygen metabolism within the jugular bulb: reliability of unilateral measurements in severe head injury. Cerebral venous oxygen saturation studied with bilateral samples in the internal jugular veins. Does adherence to therapy targets in kids with extreme traumatic mind injury avoid brain hypoxia Thrombotic, infectious, and procedural complications of the jugular bulb catheter within the intensive care unit. Brain tissue oxygen, carbon dioxide, and pH in neurosurgical sufferers in danger for ischemia. Reduced mortality price in patients with severe traumatic mind harm treated with mind tissue oxygen monitoring. Analyses of cerebral microdialysis in sufferers with traumatic mind damage: relations to intracranial pressure, cerebral perfusion strain and catheter placement. Cerebral blood move and metabolic fee early and late in prolonged epileptic seizures induced in rats by bicuculline. The role of spreading depression, spreading depolarization and spreading ischemia in neurological illness. Clinical relevance of cortical spreading melancholy in neurological problems: migraine, malignant stroke, subarachnoid and intracranial hemorrhage, and traumatic brain injury. Autoregulation of cerebral blood circulate after experimental fluid percussion damage of the mind.
Specifications/Details
Electrical bone stimulation was first described as a method of selling fusion in long-bone fractures blood pressure 9862 discount furosemide 40 mg line. Pulsed electromagnetic field stimulation and capacitively coupled electrical stimulation are two types of externally utilized electrical stimulation that maybe less effective than direct present stimulation in that the latter creates a extra centered region of electromagnetic present throughout the meant fusion mattress prehypertension facts furosemide 40 mg cheap visa. The posterior components are underneath tensile pressure blood pressure medication beginning with r buy cheap furosemide 40 mg on-line, whereas the anterior column is underneath compressive forces blood pressure up 100 mg furosemide safe. Correction of positive sagittal imbalance is crucial when treating patients with pseudarthrosis. Numerous longterm studies have demonstrated that degenerative changes within the movement segments cranial or caudal to a fusion are radiographically demonstrable in roughly 25% to 45% of patients,125-134 with some studies reporting an incidence as high as 60% to 90%. Adjacent phase disease, however-which is outlined as the development of signs of myelopathy, radiculopathy, or mechanical ache referable to pathology of an adjoining motion segment-occurs in solely a minority of sufferers with radiographic evidence of adjoining section degeneration. Accordingly, radiographically demonstrable adjoining section degeneration has been poorly correlated with long-term medical outcomes across multiple studies. Although the precise explanation for adjacent section degeneration remains a subject of debate, accelerated degenerative modifications occurring at motion segments above or under a fusion may be the result of increased biomechanical stress and the resultant hypermobility of movement segments cranial and caudal to a fusion. Preoperative lateral (A) and anteroposterior (B) radiographs of a 42-year-old man who had a 1-year historical past of intractable center and decrease again ache and loss of bowel continence. Imaging demonstrated a thoracolumbar kyphotic deformity of 16 degrees with proof of screw pullout at L3 and fracture of L2. Radiolucencies surrounding the L3 pedicle screws are seen on the anteroposterior radiograph (arrows in B) and are in maintaining with nonunion and failure of the instrumentation. Postoperative lateral radiograph (C) and sagittal reconstructed computed tomography scan (D) after posterior decompression of L2-L3 was carried out, followed by pedicle subtraction osteotomy at L2. Bone purchase and assemble strength were improved by placement of bigger diameter pedicle screws and a caudal extension of the construct to L4. New screw entry factors and trajectories had been used at L3 bilaterally to enhance bone buy. The previous L3 screw trajectory is visible superior to the model new L3 pedicle screw trajectory. The patient reported important enchancment in his decrease again ache and bowel function. Preoperative anteroposterior (A) and lateral (B) radiographs and an axial computed tomography image (C) of a 32-year-old girl who had undergone T11-S1 posterior fusion for degenerative scoliosis 2 years earlier. Imaging demonstrated a proximal junctional kyphosis of 37 degrees above the fusion assemble, a compression fracture of T10, and a thoracic scoliotic deformity. Pseudarthrosis of T11-T12 was demonstrated by the presence of halo-shaped radiolucencies surrounding the T11 pedicle screws. The affected person had a history of osteoporosis for which she was handled with recombinant human parathyroid hormone for 1 yr before revision surgical procedure. Postoperative anteroposterior (D) and sagittal (E) reconstructed computed tomography scans. After elimination of the T11 pedicle screws, revision of the T11-T12 fusion, inner discount of the T10-T11 kyphoscoliotic deformity, T5-T12 posterior fusion, and screw-rod stabilization were performed. In general, symptomatic adjoining section illness is most commonly observed to occur from 2 to 15 years after the index fusion procedure. In the lumbar spine, the avoidance strategies have centered on changing the biomechanical profile of the instrumentation and avoidance of adjacent-level soft tissue disruption. Total disk replacement arthroplasty,162 dynamic fixation,163 and percutaneous posterior instrumentation164 have been utilized in an try to keep away from adjoining section illness. Characteristically, many patients with adjoining phase disease report a symptom-free interval, adopted by the development of new progressive symptoms, in many circumstances several years after the index fusion process. Accordingly, detailed information from earlier medical evaluations should be reviewed and in contrast with the current symptomatology. Objective indicators of a progressive neurological deficit, similar to radiculopathy or myelopathy localizable to adjoining movement segments, are suggestive of adjacent section illness. A complete synthesis of the information obtained from the history and neurological examination, imaging research, and data of previous operations is required to formulate a detailed remedy plan. Indications for operative intervention include radiographic evidence of compression of neural parts with correlative indicators of myelopathy or radiculopathy. Progressive or severe spinal deformity with mechanical instability are extra, however much less widespread, indications for operative intervention. The ideas of treatment and the surgical objectives relating to adjacent section illness are just like these of revision backbone operations normally. Of paramount importance is avoidance of further mechanical destabilization and adjacent segment degeneration by preserving the adjoining supporting buildings, such as the aspect joints, facet capsules, and interspinous ligaments. Comprehensive understanding of spinal biomechanics is important in formulating an optimum surgical strategy that minimizes the risk for additional adjacent phase degeneration and spinal deformity. Cervical laminectomy is a standard procedure that includes resection of the spinous processes, laminae, and interspinous and supraspinous ligaments with few immediate issues. The muscular attachments of the paraspinal muscles are disrupted and the erector spinae muscle tissue are weakened because of partial denervation. In these patients, either the event of radiculopathy or myelopathy, development of the deformity, or the event of axial pain could warrant corrective surgery. Techniques for the correction of cervical postlaminectomy kyphosis embrace a dorsal approach, a ventral strategy, or a mixed dorsal and ventral approach. Some surgeons elect to place screws on this setting with the assist of image guidance. Strong anchor points at the cranial and caudal ends of the instrumentation assemble, similar to pedicle screws, are more fascinating in patients with kyphosis because of their elevated energy. Thus, the assemble may be prolonged to embrace the C2 or C7 pedicles on the cranial and caudal ends in chosen cases to supplement the power of the hardware assemble at points at which elevated pullout energy is required. The technique of "overbending" the rods or plates with an enhanced curvature in the sagittal plane allows additional discount of the deformity. When performing this method, a persuading gadget is used to ship the pedicle or lateral mass screws toward the overcontoured rods or plates. This maneuver have to be used judiciously as a outcome of it considerably preloads the instrumentation, which may improve the danger for instrumentation failure. Because substantial pulling pressure can be positioned on the pedicle or lateral mass screws, this maneuver have to be used judiciously in patients with low bone mineral density or in those with suboptimal screw purchase. After screw tightening, crossconnectors are placed to enhance the torsional stability. Once the instrumentation has been positioned, autologous bone graft is applied to the decorticated aspect joints and lateral gutters. We routinely place 1 g of vancomycin powder over the instrumentation, after which a surgical drain, before closure. Ventral decompression may be performed in patients with important neural compression by ventral bony elements, prolapsed intervertebral disks, and osteophytic ridges. In such cases, ventral decompression is required earlier than any procedure for correction of the kyphotic deformity is performed as a outcome of the appliance of corrective distraction forces will improve ventral compression of the spinal wire and should result in spinal wire injury. The ventral strategy affords the additional alternative to perform ventral release of the longus colli muscles, the anterior longitudinal ligament, and the anterior anulus, thereby facilitating further anterior reduction of the kyphotic deformity. Gardner-Wells traction is applied and a shoulder roll is positioned beneath the scapulae to encourage cervical lordosis. Intraoperative lateral fluoroscopy is valuable in assessing alignment of the cervical spine and centering the incision above the degrees to be operated on, and during the placement of instrumentation. Either a transverse skin incision or, alternatively, an oblique incision alongside the anterior border of the sternocleidomastoid muscle (when publicity of three or more spinal segments is required) is carried out. The traditional method of anterior cervical spinal publicity as described by Cloward is then carried out. Distraction is applied alongside the Caspar pins to place the pins in DorsalApproach A dorsal surgical strategy is commonly used for patients in whom the kyphotic deformity is both utterly or satisfactorily reducible with neck extension and the structural integrity of the ventral bony components is maintained. After publicity of the suitable spinal ranges, additional decompression of the neural elements could also be performed as needed. Lateral fluoroscopy is used to verify adequate cervical lordosis after manual reduction. A, Sagittal T1-weighted magnetic resonance image of an 11-year-old woman with neurofibromatosis kind 2 and a recurrent intramedullary ependymoma. Four months previous to this image, she had a suboccipital craniectomy and C1-C5 laminectomies.
Syndromes
- Urine culture (catheterized specimen)
- Something stuck in the throat (for example, fish or chicken bones)
- Learning how to select the right foods and when to eat them (diabetes diet)
- Complete blood count (CBC)
- Shock
- The type of bone marrow transplant
- Biological -- made of human or animal tissue. These valves last 10-12 years. You may not need to take blood thinners for life.
- Fever and chills
- Breathing support, including a breathing tube
- Muscle biopsy
Related Products
Additional information:
Usage: p.o.
Tags: 40 mg furosemide buy otc, 100 mg furosemide order, 40 mg furosemide discount visa, furosemide 100 mg buy cheap on-line, order furosemide 40 mg without a prescription, furosemide 100 mg generic fast delivery, furosemide 40 mg discount overnight delivery, discount 100 mg furosemide with visa, buy furosemide 40 mg without prescription, 40 mg furosemide purchase mastercard, furosemide 100 mg generic without a prescription, 40 mg furosemide for sale, furosemide 40 mg free shipping, 100 mg furosemide buy visa, furosemide 40 mg buy mastercard, furosemide 100 mg buy lowest price
8 of 10
Votes: 54 votes
Total customer reviews: 54
Customer Reviews
Bozep, 48 years: In addition, when astrocytic membranes are stretched, they develop a dysfunctional cation present as opposed to an osmoregulatory anion present.
Tarok, 54 years: The "hit and run" model during which a truncated Bcl-2 protein, tBid, "hits" Bak to induce an oligomeric change, then "runs" from the Bax/Bak heterodimer, was initially proposed by Wei and colleagues as the mechanism.
Bradley, 55 years: Pelvic obliquity might outcome from an intrinsic sacropelvic deformity, leg size discrepancy, or a mixture of the both.