
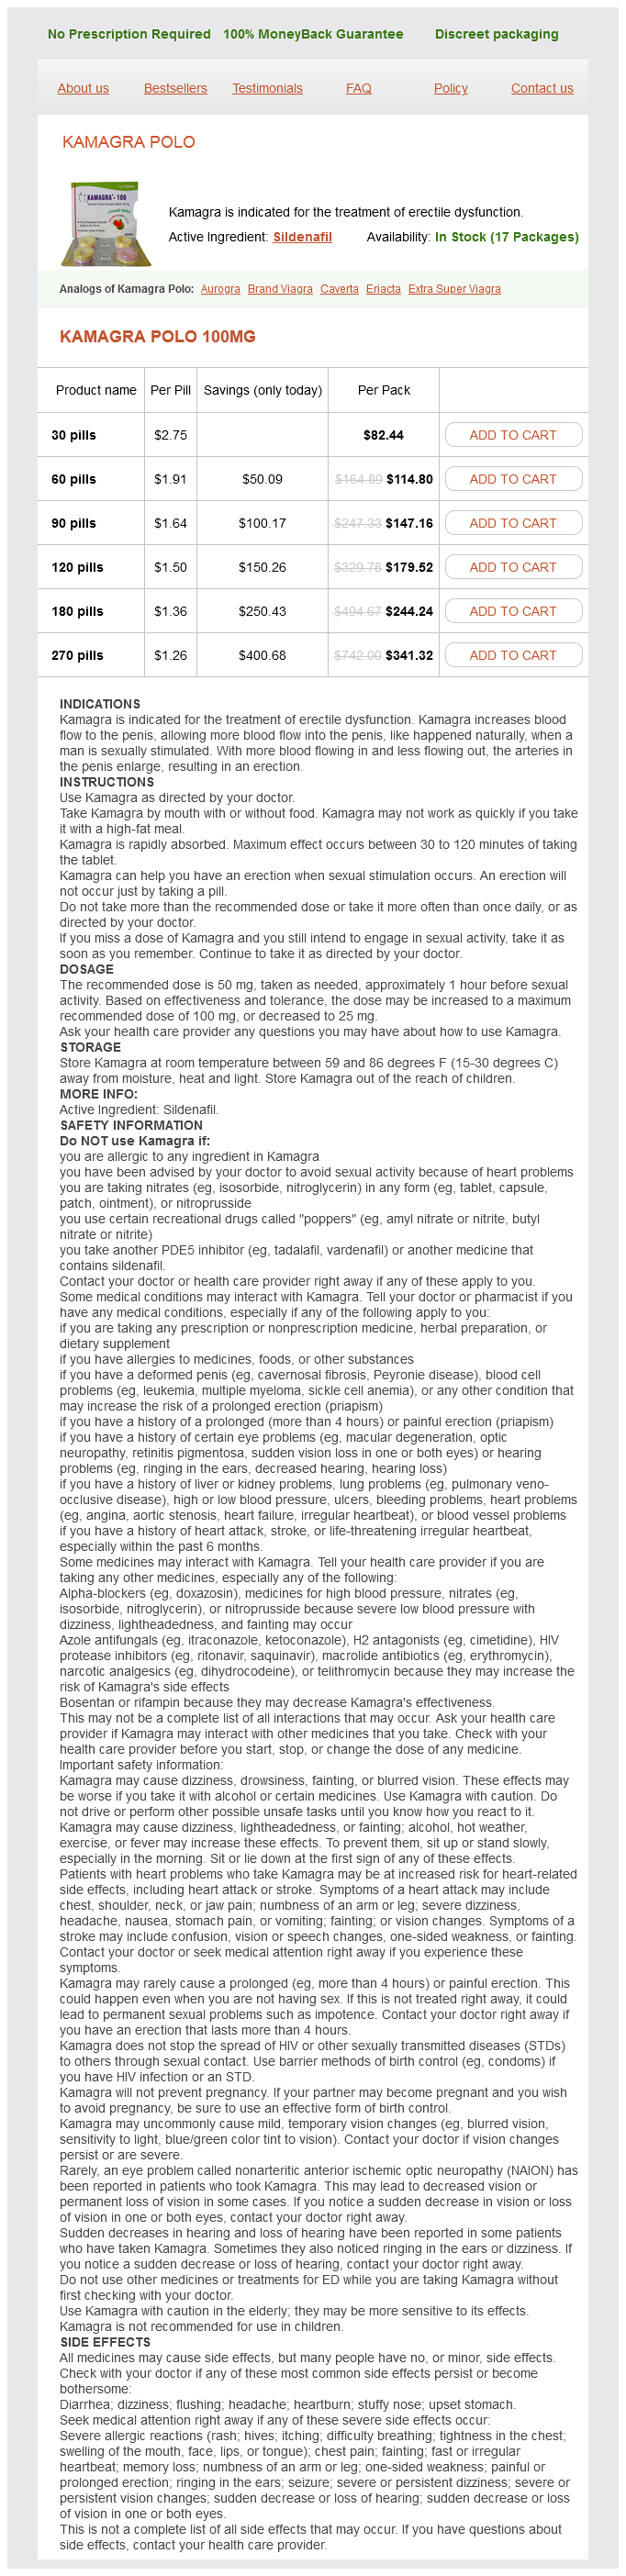
Kamagra Polo
Kamagra Polo 100mg
- 30 pills - $82.44
- 60 pills - $114.80
- 90 pills - $147.16
- 120 pills - $179.52
- 180 pills - $244.24
- 270 pills - $341.32
Kamagra Polo dosages: 100 mg
Kamagra Polo packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills
In stock: 552
Only $1,34 per item
Description
One is used for visualization with the arthroscope and the opposite for instrumentation erectile dysfunction causes cures cheap kamagra polo 100 mg free shipping. Arthroscopic surgery has been used to correct many intracapsular derangements such as displacements erectile dysfunction doctors in cincinnati 100 mg kamagra polo purchase, hypomobility because of how erectile dysfunction pills work order kamagra polo 100 mg online fibrosis or adhesions erectile dysfunction beat purchase kamagra polo 100 mg mastercard, and so on. Computed Tomography Computed tomography supplies excellent visualization of the complete joints. Threedimensional computed tomography offers glorious threedimensional view of the joint, but continues to be very expensive and never available to all the centers. Postauricular Approach the incision lies behind the auricle and extends into the temporal area. Magnetic Resonance Imaging Magnetic resonance imaging has a distinct advantage over different strategies that it offers visualization of the delicate tissues that fill the articular house. It is quick changing into an essential software to diagnose the intracapsular joint problems. Endaural Approach the endaural strategy avoids the transection of the auditory canal. The incision runs just medial to the tragus, starting from the Temporomandibular JoinT disorders incisura terminalis under, to the purpose between the meatus and the upper fringe of the auricle. The incision then runs superiorly in the temporal region, similar to the postauricular incision. The advantage of this strategy is nice publicity of anterior, lateral and posterior part of the joint. A submandibular incision is taken 1 cm under the lower border and posterior to the posterior border if needed. The dissection is carried out below the platysma muscle and later along the mandible to expose the condylar course of. It is, nonetheless, tough to reach the upper joint compartment with this strategy and an extra preauricular incision is commonly wanted. Various incisions have been described, however the one described by Al Kayat and Bramley15 is well accepted and utilized. The skin incision is question mark-shaped and begins within the temporal region anteriorly and superiorly to the pinna. It curves backward and inferiorly, posterior to the branches of the temporal vessels until it meets the superior attachment of the ear, it then follows the anterior attachment of the auricle and ends at the inferior attachment of the ear. The nerve filaments run in superficial fascia and are thus reflected with the temporal flap which is completed with by blunt dissection above the temporal fascia to a degree about 2 cm above the zygomatic arch. At this level, the temporal fascia splits into superficial and deep lamina to enclose the zygomatic arch. A 4 cm lengthy incision is made into the superficial lamina of the temporal fascia, from the basis of the zygomatic arch, running anteriorly and superiorly at an angle of 45� to the arch. Further dissection inferiorly is carried out deep to the superficial lamina to keep away from the branches of the facial nerve which run in the superficial lamina. During wound closure, the incised superficial lamina of the temporal fascia is closed with out rigidity before closing the wound. The temporal extension is commonly made shorter, simply sufficient to hide it behind the hairline. Bony ankylosis of the temporomandibular joint- follow-up of 70 patients handled with arthroplasty and acrylic spacer interposition. Trial of a sternoclavicular entire joint graft as a substitute for the temporomandibular joint. Increased Compartment Content � Bleeding � Major vascular injury � Bleeding issues � Anticoagulant therapy � Increased capillary permeability � Postischemic swelling � Exercise, seizure and eclampsia � Trauma � Burns � Intraarterial medication � Orthopedic procedures: Osteotomy, discount, fixation � Increased capillary stress � Exercise � Venous obstruction � Muscle hypertrophy � Infiltrated infusion � Nephrotic syndrome � Leukemic infiltration � Viral myositis � Acute hematogenous osteomyelitis � Diabetes � Hypothyroidism � Crush syndrome � Ruptured ganglia and cyst � Snake chunk � Popliteal cyst. Introduction Compartment syndrome is characterized etiologically by swelling arising from diverse causes leading to compromise of the blood supply of tissues within a confined osseofascial area. Such a state of affairs causes necrosis that may involve not solely the muscle tissue and nerves but in addition even the pores and skin inflicting blisters and ulcers. The most typical websites are the volar compartment of the forearm and the anterior compartment of the leg (anterior tibial syndrome). Etiology Increased pressure inside a confined space could cause obliteration of the circulation leading to gangrene in severe cases and necrosis of tissues in milder instances when the stress is sufficient to obliterate solely the smaller vessels. Matsen (1980)1 has categorised the trigger of elevated stress leading to compartment syndrome as follows: Decreased Compartment Size � Surgical closure of fascial defects. Compartment Syndrome Most Common Fracture � Tibial diaphyseal � Distal radial and forearm diaphyseal. A vicious selfperpetuating cycle Flow chart 1 will get established which until interrupted both by cessation of causes and/or surgical decompression, will result in tissue necrosis because of the reduction of oxygen pressure from a discount within the perfusion of the compartment. Theories for Acute Compartment Syndrome Pathogenesis � Critical closing pressure theory � Arteriovenous gradient principle � Microvascular occlusion theory. Reperfusion syndrome is a gaggle of problems following reestablishment of blood flow to ischemic tissues and might occur after fasciotomy and restoration of muscle blood flow in acute compartment syndrome. Reperfusion is followed by an inflammatory response within the ischemic tissue, which can cause further tissue harm; the period of muscle ischemia dictates the amount of necrosis although some muscle fibers are extra weak than other to ischemia. For instance, the muscle of anterior compartment of leg include kind 1 fibers or red slow twitch fibers and gastrocnemius contain mainly sort 2 or white fast twitch fibers type 1 fibers depend on oxidative and are more weak to oxygen depletion. This is a distinct sort of syndrome labeled as compression ischemia by the author and is due to application of tight splints by quacks within the villages. It affects the tissues within the space of tight splintage and as distally in a round style (the flexor and extensor muscle tissue and in the extreme instances the nerves). The increased strain within a compartment results in decreased Clinical Features Increased stress inside the compartment will compress nerves and vessels that course via it. Following trauma (or as a result of different causes enumerated previously) intractable deep pain develops. The basic indicators of ischemia are pain, pallor, paresthesia, pulselessness and finally paralysis. Waiting for all or most of these to develop is likely to show disastrous, and a decompressive procedure must be done earlier than paralysis has developed. Late decompression after paralysis had occurred is followed by recovery solely sometimes (Bhalla, Lobo, Aggarwal, 1982). Pulselessness and paralysis are rare, only occurring after an arterial injury or after a substantial period of time has elapsed. Physical indicators are sometimes few however there may be a firm, wooden feeling on deep palpation. Reduced twopoint discrimination or vibration sense could also be discovered within the early stages; if a significant sensory deficit is obvious the syndrome is already far advanced. The wick retains the orifice of the catheter open and permits steady monitoring, thus, the effect of train on the pressures may be monitored. Mubarak and Owen (1977)6 have nonetheless, beneficial that decompression must be accomplished as soon as strain reaches 30 mm Hg. Depending upon the anatomical location of the compression, difficult forms of syndromes may be identified. Pressure Studies When a excessive index of suspicion exists, strain studies are necessary to determine whether or not the contents of compartment are threatened. The brachial vessels could additionally be injured by the sharp fringe of a supracondylar fracture and by swelling consequent to the fracture. The radial vessels and the widespread interosseous branch of the ulnar artery, which divides into the anterior and posterior interosseous vessels move beneath the pronator teres. The anterior interosseous artery passes distally on the interosseous membrane and provides the flexor digitorum profundus and flexor pollicis longus muscle tissue. The volar side of the forearm is swollen, red and warm, and exquisitely tender on palpation. Distal hypoesthesia and even anesthesia in the median nerve territory, and in additional severe circumstances, in the ulnar nerve territory may occur. Peripheral pulses may be absent from the start if the trigger is occlusion of the brachial artery, but their absence is often a late characteristic occurring in a severely swollen limb. Immediate elevation, release of constricting dressings, gentle enchancment in the place of the fractures, administration of sublingual or injectable fibrinolytic and proteolytic enzyme preparations may result in some improvement.
Two-Eyed Berry (Squawvine). Kamagra Polo.
- How does Squawvine work?
- Anxiety, depression after childbirth, diarrhea, menstrual disorders, heart or kidney problems, nipple soreness, water retention, and other conditions.
- Dosing considerations for Squawvine.
- What is Squawvine?
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96727
The best pore dimension for a bioceramic material must be just like erectile dysfunction symptoms kamagra polo 100 mg discount without a prescription that of spongious bone generic erectile dysfunction drugs online kamagra polo 100 mg buy visa. It has been demonstrated that microporosity (pore dimension <10 mm) allows body fluid circulation; whereas macroporosity (pore dimension >50 mm) supplies scaffold (pore size 100�200 mm and porosity 60�65%) for bone-cell colonization impotence grounds for divorce in tn cheap kamagra polo 100 mg line. A ceramic with larger porosity and lower density construct provides larger surface space for vascularization impotence exercise kamagra polo 100 mg buy amex, and bony ingrowth. Ceramic materials have additionally been used to coat and enhance osseointegration of implants. After the powder and solvent have been combined, the ensuing ceramic is a paste-like materials that could be injected or molded into a nonweight-bearing defect with a setting time of approximately 10�30 minutes, depending on formulation. By various the proportions of sodium oxide, calcium oxide, and silicon dioxide, all range of forms can be produced from soluble to nonresorbable. If resorbed early, the bone formation has no time, if it is too late greater than a yr. Prior to implantation, this paste is supplemented with autogenous bone marrow aspirate. In a randomized, potential study at multiple trauma centers in the United States, the efficacy of collagraft was in comparability with autogenous cancellous bone graft. Calcium Sulfate Calcium sulfate (plaster of Paris) has been used as a synthetic graft materials for properly over 100 years. Calcium sulfate has no weight-bearing capacity, and it resorbs comparatively quickly, in as little as 6 weeks after implantation. It is clear that a pore size of no less than a hundred microns and fewer than 600 microns is necessary to get bone formation. The perfect pore dimensions may depend on the particular scientific indications for this synthetic bone graft substitute. The chemical composition and crystallinity of the fabric has a profound effect, not solely on the speed of bone regeneration, but also on the rate of bioresorption of the material. The brittle, mechanical properties of those artificial graft supplies are being improved by means of composites. Whether these composites will be adequate to permit these materials to be subjected to main loading throughout bone regeneration is but undetermined. Finally, and most significantly, the opposed effect of those materials on bone remodeling is being studied. Until strategies are developed to augment the resorption of the ceramic materials, their deleterious impact on bone remodeling will severely restrict their medical purposes. Polymer-Based Bone Graft Substitutes11 the ultimate group of bone graft substitutes is the polymer-based group. For occasion, many polymers which are potential candidates for bone graft substitutes symbolize completely different physical, mechanical, and chemical properties. These polymers used at present can be loosely divided into pure polymers and synthetic polymers. Polymer-ceramic composite consisting of collagen fibers have been coated with hydroxyapatite and used for spinal fusions. The profit of having the implant resorbed by the physique is that the body is ready to completely heal itself with no overseas bodies remaining. To this end, corporations have used degradable polymers such as polylactic acid and polylactic-co-glycolic acid as stand-alone units and as extenders to autografts and allografts. An elevated understanding will permit for more indicative use of this increasingly popular therapy. It has attracted worldwide consideration not solely as a outcome of the ethical debates associated with the destruction of human embryos and the clinical potential of embryonic stem cells in regenerative and reparative therapies. The possible clinical application as a end result of their a number of potential has focused immense research on this field. The research is on to overcome problems with quantity, security, price and find various sources and novel approaches for cell harvesting, in vitro expansion and subsequent implantation, and to establish novel cell-based and composite bone graft substitutes. Percutaneous autologous stem cell grafting is an environment friendly, minimal invasive and protected methodology of therapy of noninfected atrophic nonunions. There are several advantages to a one step clinical application of bone marrow focus. In addition, the chance for an infection is lowered by lowering the ex vivo time period. Bone marrow processed stem cells injected both within the nonunion gap and across the bones, confirmed union in many of the patients (9 out of 12). The mechanism by which it induces new bone formation in experimental fashions is a relevant matter for future studies. Bone-marrow-derived mononuclear cells are in a place to elicit formation of latest blood vessels by the presence of endothelial cell progenitors or hemangioblasts in this cell fraction. This could additionally be due to the availability of each progenitor cells and angiogenic cytokines produced by bone-marrow cells. Endothelial progenitors can actively interact in vasculogenesis in tissue devoid of vessels and in neoangiogenesis from the pre-existing capillaries. Apart from the era of latest capillaries, the rising endothelia improve the mobilization and development of mesenchymal progenitors by way of the angiopoietin1-Tie2 pathway, which generates pericytes and vascular mural cells required for model new vessel development and stabilization. A broad capacity of differentiation of perivascular mesenchymal cells has been shown, and participation of perivascular mesenchymal progenitors in the repair of adjacent tissues has been described in each experimental models and humans. Although varied stem cell sources have been investigated for bone repair, few comparative stories exist, and mobile distribution and viability submit implantation remain key points. To do so, stem cells are cultured in the presence of various components corresponding to dexamethasone, ascorbic acid, and -glycerophosphate to direct the undifferentiated cell toward the osteoblast lineage. The morphogenesis of bone in replicas of porous hydroxyapatite obtained from conversion of calcium carbonate exoskeletons of coral. Biological and physical properties of autogenous vascularized fibular grafts in canines. Vascularized autografts for reconstruction of skeletal defects following lower extremity trauma. Fresh autogenous and osteochondral allografts for the therapy of segmental collagen in osteonecrosis of the hip. Proceeding of the Confer-ence on Rehabilitation of Articular Joints by Biological Resurfacing. The fate of cancellous and cortical bone after transplantation of contemporary and frozen tissue-antigen-matched and mismatched osteochondral allografts in canine. New Materials and Approaches11 Despite the many advances in bone graft substitutes, new supplies and approaches to bone therapeutic proceed to be investigated. One exciting area is tissue engineering, which could be outlined as the appliance of biological, chemical, and engineering ideas to the restore, restoration, or regeneration of living tissues by using biomaterials, cells, and components alone or together. Applying the philosophy of tissue engineering to the healing of bone, Laurencin laboratories has developed biocompatible biodegradable matrices that possess lots of the properties important to successful healing. This fundamental design has also been mixed with a ceramic to kind a composite matrix. The strategy behind the composite would enable the benefits of each supplies to be included in a single design. By utilizing both previously synthesized hydroxyapatite and calcium phosphate synthesized throughout the matrix itself, the polymer-ceramic composite fosters the mineralization of newly forming bone. Bone Banking Bone banking has radically modified in the United States during the last 25 years. Strict donor choice criteria and processing pointers for bone, cartilage, and connective tissues, originally provided as voluntary suggestions of the American Association of Tissue Banks, have now turn into necessary. Effects of freezing and freeze-drying on the biomechanical properties of rat bone. Bone ingrowth and mechanical properties of coralline hydroxyapatite 1 yr after implantation. It additionally reviews early scientific results and supplies a rationale for contemporary fracture take care of the multiply injured affected person. Minimally invasive surgical methods such as external fixation are used initially. Damage management focuses on control of hemorrhage, administration of soft-tissue harm, and achievement of provisional fracture stability, whereas avoiding extra insults to the patient. During Nineties, more was learned about the parameters related to opposed outcomes in multiply injured sufferers and about the systemic inflammatory response to trauma. This modified prevailing practice of that point and a more selective method to fracture fixation was launched; nevertheless, early fixation was still carried out generally. Two reviews described momentary exterior fixation of femoral shaft fractures in severely injured sufferers.
Specifications/Details
The outer layer of stockinet is split and turned around over the knee and integrated inside the finishing layers of plaster erectile dysfunction 32 kamagra polo 100 mg effective. Now erectile dysfunction at 65 buy kamagra polo 100 mg without a prescription, the central screw of hinge is tightened erectile dysfunction treatment massachusetts 100 mg kamagra polo purchase visa, and plaster is allowed to set for no less than 24 hours erectile dysfunction pills in store safe kamagra polo 100 mg. Patient is allowed to stand and bear weight and walk with crutches after forty eight hours. The posterior and superior portion of the solid is moulded to produce a triangular shape on the high. It is firmly moulded over patellar tendon and popliteal fossa in order to produce a contour similar to that of patellar tendon bearing prosthesis. The posterior portion of the forged is minimize right down to the level of midpopliteal area. The distal portion of the solid is trimmed to preserve snug moulding of the forged across the lateral and medial malleoli for allowing full plantar and dorsiflexion of the ankle. The medial upright of the joint is carefully placed exactly reverse to the apex of medial malleolus, and lateral upright is placed slightly posterolateral so that standard toe out of 10� is maintained throughout walking. Contraindications � � � � � � If fracture is wobbling Upper third shaft femur fractures Subtrochanteric fractures Supracondylar fracture shaft femur Bilateral fractures shaft femur Floating knee. Technique Thigh sleeve is utilized normally 4 weeks after the harm when the fracture has turn out to be sticky and intrinsic stability has been achieved. After spreading antifungal powder, stockinet is rolled up from under the knee up to the groin. The sleeve is strengthened by incorporating four slabs (anterior, posterior, medial and lateral). The sleeve is firmly moulded within the higher thigh by applying pressure anteroposteriorly and side-to-side by the assistance of an assistant. In the decrease a part of the thigh, sleeve is properly moulded over patella and femoral condyles. Clearance of about half an inch is allowed on brim of the sleeve a medial aspect to prevent the impingement on the perineum. Follow-up Once the affected person has started full weight bearing without help, skiagram is taken to verify the place of fragments after weight bearing. Patients are inspired to return to their jobs with the instruction to hold the limbs elevated while sitting. On subsequent visits, patient is examined for vary of actions, and to see whether or not brace is providing sufficient stability to fracture fragments. On rotating the ankle externally or internally and likewise the knee in the same path, produces no pain at fracture site is diagnostic of clinical union. Cast brace is eliminated for scientific and radiological examination at common interval of 4�6 weeks to see progress of union after which reapplied. Postapplication Management After 24 hours of utility of thigh sleeve, patient is suggested to start active knee, hip and leg-raising exercises and is allowed partial weight bearing with axillary crutches. Every four weeks, sleeve is removed, a skiagram taken and fracture site assessed for clinical and radiological union. Sleeve is discarded when the fracture is united clinically as properly as radiologically. Hip Brace Indications � � � � Subtrochanteric fractures Trochanteric fractures Upper one-third femur fractures After intramedullary nailing. Functional Thigh Sleeve12 Application of practical thigh sleeve is a conservative method of treating fractured shaft femur however may also be used as complement after intramedullary nailing. It provides stabilizing influence at fracture website and allows negligible movements at fractures web site, that are desirable. At the same time, it allows early weight bearing and movement at knee and hip joints. Weight is transmitted from femoral condyles to ischial tuberosity and thru quadrangular socket to gentle tissue. More than 60% of weight is transmitted through muscle mass surrounding the fracture site. Technique � the hip brace consists of single uniaxial joint, thigh upright and pelvic upright to which pelvic band is attached. It is applied 4�6 weeks after the injury, throughout which the fracture web site becomes sticky, and intrinsic stability is achieved. Prior to utility of pelvic portion, ample cotton is stored over the abdomen to accommodate the abdominal actions, which occur with respiration. Gradually the patient is encouraged to stroll with a stick and at last all types of external help discarded. Again examine radiograph is to be taken after 1 week if alignment is passable, reexamination ought to be done at 3�4 weeks interval and at each visit of the patient, clinically in addition to radiologically assessment is done. Wrist Brace Indications � Colles fractures � Fracture at lower finish of radius and decrease finish of ulna. Two blades are joined together within the form of uniaxial joint, which is freely cell in a single axis. The plaster is now utilized over the forearm and hand-keeping forearm in full supination/midpronation. The proximal portion of the plaster is utilized over the forearm with a supracondylar extension to prevent supination and pronation, however allowing full elbow flexion motion, full extension restricted up to 30�. A well-applied wrist brace ought to: � permit elbow restricted flexion and extension � forestall supination and pronation � permit full palmar flexion and dorsiflexion of the wrist � allow full range of finger movements. Humeral Sleeve Indications All diaphyseal fractures of humerus especially in center one-third. Give a correct stretch to stockinet and apply cast padding evenly over the bony prominence. Keeping it in useful place with the elbow in 90� flexion, sprinkle an antibiotic/ antifungal powder over the forearm and then roll over the size of stockinet distal to proximal. A layer or two of solid padding is utilized on the proximal end over the olecranon and both the condyles. Over the distal finish simply proximal to the wrist and strip along with subcutaneous border of ulna. Required numbers of plaster bandages are soaked into water, and a forearm cast is quickly utilized leaving the wrist and elbow free. At the proximal finish, the plaster is moulded over both the lateral and medial condyles and over the tip of the olecranon. Particular consideration must be given on this moulding, as this keeps the plaster brace to the limb and is the necessary thing to a successful bracing. The slab nows applied over the dorsal facet of limb and is held in position by plaster bandages. As the forged sets within the sharp edges and pointed ends of the plaster are rounded off with small strips of plaster bandages, the additional stockinet is reduce away and the elbow and hand are cleaned. Technique � A double stockinet is utilized extending from the hand to the shoulder after preparation of pores and skin and dusting mycoderm powder. After Treatment � Active motion of elbow and wrist are commenced after in the future because the plaster becomes completely dry. The brace is anesthetic and because both the elbow and wrist joints are free, patient can perform his/her routine work unhindered. Any breakage or loosening in between requires a repair or elimination and reapplication. Results14 the typical healing time for tibial fracture is 15�16 weeks, which is extra in femoral fracture, i. Similarly almost full actions are achieved in 4 weeks in ankle and subtalar joint after application of ankle brace. But, the problems in brace remedy are notably associated to metallic brace, like loosening, breaking and bending. It avoids the hazard of plaster disease in conservative and infection in surgical treatment. It is appropriate and greatest suited center path regime in the management of fractures in our nation. Prefabricated practical braces for the therapy of fractures of tibial diaphysis. Cast-brace treatment for fractures of the distal part of the femur: a potential controlled study of 100 and fifty patients.
Syndromes
- Deformity of the chest
- Mouth sores
- MRI of abdomen
- Blood glucose level
- Headache
- Epinephrine becomes metanephrine and VMA
- Electrolytes
Related Products
Additional information:
Usage: q.d.
Tags: discount 100 mg kamagra polo with amex, kamagra polo 100 mg cheap visa, 100 mg kamagra polo buy mastercard, 100 mg kamagra polo discount overnight delivery, buy 100 mg kamagra polo, kamagra polo 100 mg purchase online, kamagra polo 100 mg buy lowest price, kamagra polo 100 mg purchase mastercard, buy kamagra polo 100 mg low cost, purchase 100 mg kamagra polo with mastercard, cheap 100 mg kamagra polo visa, cheap kamagra polo 100 mg with mastercard, generic kamagra polo 100 mg online, discount 100 mg kamagra polo free shipping, kamagra polo 100 mg with visa, purchase kamagra polo 100 mg on-line
8 of 10
Votes: 104 votes
Total customer reviews: 104
Customer Reviews
Ayitos, 59 years: The treatment of established case is an early analysis and prompts surgical decompression and debridement repeated if needed on day by day basis. Hope and Cole 27 who reviewed patients at 2�10 years, after the surgery observed a notable incidence of constant morbidity like pain at the healed fracture site (50%), restriction of sporting activity (23%), joint stiffness (23%), beauty defects (23%) and minor leglength discrepancies (64%).
Seruk, 38 years: Studies of strontium-85 uptake in these nonunion point out a poor blood supply within the ends of the fragments. One answer is to bridge the joint using a transarticular external fixator to be replaced by an inner fixation later.
Miguel, 24 years: Majority of the info that exist are on the effect of the epidural anesthesia with local anesthetics that modify the surgical stress response. Gross chromosomal rearrangements can lead to duplication, deletion, translocation of amplification of large segments of the genome.