
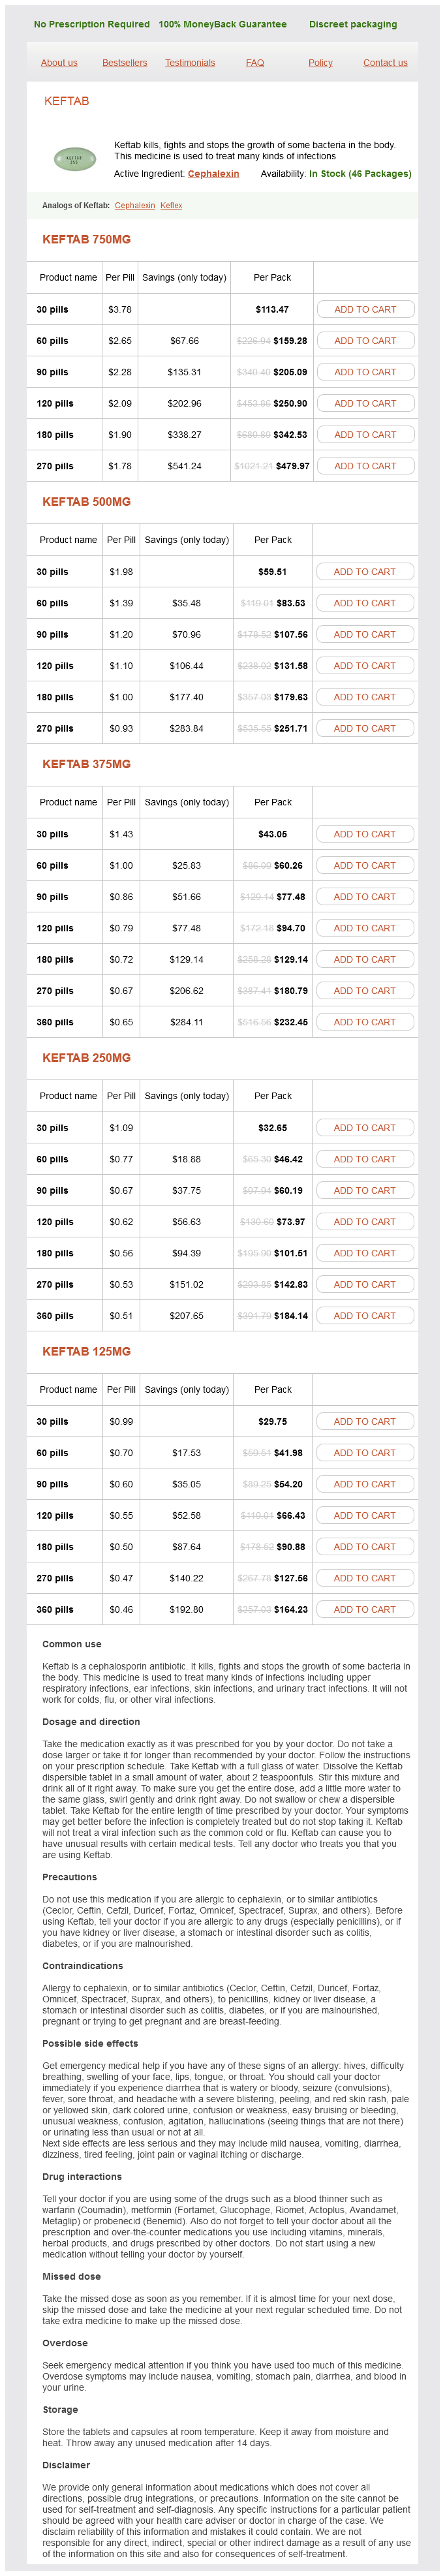
Keftab
Keftab 750mg
- 30 pills - $113.47
- 60 pills - $159.28
- 90 pills - $205.09
- 120 pills - $250.90
- 180 pills - $342.53
- 270 pills - $479.97
Keftab 500mg
- 30 pills - $59.51
- 60 pills - $83.53
- 90 pills - $107.56
- 120 pills - $131.58
- 180 pills - $179.63
- 270 pills - $251.71
Keftab 375mg
- 30 pills - $43.05
- 60 pills - $60.26
- 90 pills - $77.48
- 120 pills - $94.70
- 180 pills - $129.14
- 270 pills - $180.79
- 360 pills - $232.45
Keftab 250mg
- 30 pills - $32.65
- 60 pills - $46.42
- 90 pills - $60.19
- 120 pills - $73.97
- 180 pills - $101.51
- 270 pills - $142.83
- 360 pills - $184.14
Keftab 125mg
- 30 pills - $29.75
- 60 pills - $41.98
- 90 pills - $54.20
- 120 pills - $66.43
- 180 pills - $90.88
- 270 pills - $127.56
- 360 pills - $164.23
Keftab dosages: 750 mg, 500 mg, 375 mg, 250 mg, 125 mg
Keftab packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 752
Only $0,48 per item
Description
A search or the acoustic stapedial re exes with the impedance bridge might show re exes current at normal levels with out evidence o decay in about 18% o the tumors antibiotics while breastfeeding order 375 mg keftab with visa. Presbystasis (Dysequilibrium o Aging) and Cardiovascular Causes Age-related decline in peripheral vestibular unction am 7200 antimicrobial purchase 500 mg keftab free shipping, visible acuity antibiotic quinine order keftab 250 mg without a prescription, proprioception antibiotic resistance webquest keftab 250 mg generic visa, and motor control has a cumulative e ect upon stability and is the most typical trigger o dysequilibrium. They rarely current to the otologist however are seen in consultation with the cardiologist. However, consideration should be given when seeing a model new patient with dysequilibrium. Benign Paroxysmal Positional Vertigo The symptoms embody sudden attacks o vertigo precipitated by sitting up, lying down, or handing over bed. These assaults have been reported to be prompted by sudden movement o the head to the best or le or by extension o the neck when looking upward. The sensation o vertigo is at all times o brief period even when the provocative position is maintained. Diagnosis could be con rmed by positional testing (Dix-Hallpike test), which indicates positional nystagmus with latency and atigability. Etiologies embody degenerative modifications, otitis media, labyrinthine concussion, earlier ear surgical procedure, and occlusion o the anterior vestibular artery. These particles could be repositioned and the symptoms resolved in a high percentage o instances, by canalith repositioning procedure. Internuclear Ophthalmoplegia Internuclear ophthalmoplegia is a disturbance o the lateral actions o the eyes characterized by a paralysis o the internal rectus on one side and weakness o the exterior rectus on the other. In Cha pter 1: Syndromes and Eponyms forty five testing, the examiner has the affected person ollow his or her nger, rst to one facet and then to the other, as when testing or horizontal nystagmus. Internuclear ophthalmoplegia is acknowledged when the adductive eye (third nerve) is weak and the abducting eye (sixth nerve) moves normally and displays a coarse nystagmus ("maybe" vestibular nuclei involvement). Intracranial umors There are a small however de nite quantity o sufferers that present with dysequilibrium associated with primary or secondary intracranial tumors. M�ni�re Disease The signs, when complete and classically present, embrace uctuating sensorineural listening to loss, uctuating tinnitus, and uctuating ullness within the a ected ear. In addition, as the tinnitus, ullness, and hearing loss intensi y, an attack o episodic vertigo ollows, lasting 30 minutes to 2 hours. The course of could spontaneously remit, never happen once more, and go away no residual or maybe a mild hearing loss and tinnitus. However, ought to the second ear turn into involved, it usually happens inside 36 months. Cochlear hydrops, vestibular hydrops, or Lermoyez syndrome have aural ullness because the frequent denominator. Cochlear hydrops is characterized by the uctuating sensorineural listening to loss and tinnitus. Crisis of Tumarkin or drop assault is one other variant o M�ni�re syndrome in which the patient loses extensor powers and alls to the ground abruptly and severely. Audiometric checks present a uctuating low-tone sensorineural hearing loss, and little to no tone decay. During the assault, there could also be active spontaneous nystagmus with direction changing elements even within the midst o caloric testing. The medical therapies are aimed on the signs and embody vestibular suppressants, vasodilators, and diuretics. The surgical therapies are either damaging, or preservative o residual hearing. The latter appears directed at correcting the resultant mechanical or production�reabsorption modifications seen within the histopathology o endolymphatic hydrops within the temporal bone. Cochleosacculotomy is indicated in elderly sufferers, with disabling vertigo, poor listening to, and residual vestibular unction underneath native anesthesia. Glycerol est It is speculated that the administration o glycerol in an oral dose o 1. Within 1 hour o administration, the affected person may sense an enchancment in the listening to loss, tinnitus, and sensation o ullness within the ear with maximum e ects occurring inside 2 to three hours. In this instance, the metabolic actor exaggerates or inter eres with the compensatory mechanisms and brings concerning the signs. Allergic causes are very elusive within the administration o the dizzy patient, however the screening IgE assay may give a clue. Multiple Sclerosis Multiple sclerosis is one o the more common neurologic ailments encountered in a clinical follow. Vertigo is the presenting symptom o multiple sclerosis in 7% to 10% o the sufferers or finally seems during the course o disease in as many as one-third o the cases. Vertical nystagmus, bilateral internuclear ophthalmoplegia, and ataxic eye actions are different clues to this disease. Electronystagmography might show anything rom regular ndings to peripheral ndings to central ndings. Research into an etiology or this disorder is pointing to an autoimmune disorder o the myelin. Oscillopsia (Jumbling o the Panorama) Dandy Syndrome Since our heads bob up and down while strolling, the otolithic system controls eye motion to keep a constant horizon when walking. Otitis Media Suppurative or serous otitis media could have associated vestibular symptoms. In serous otitis media, the presence o uid within the center ear limiting the spherical window membrane, serous labyrinthitis, could also be responsible or the vestibular symptoms. Removing the serous uid either medically or surgically offers rise to remission o the dizziness. In the presence o suppuration there could also be reversible serous labyrinthitis or irreversible suppurative labyrinthitis, and the extra intensive sequestrum with a dead ear and acial nerve palsy. In this instance, judgment concerning the illness and its e ects determines the correct therapy. Otosclerosis (Otospongiosis) There seems to be three areas where otosclerosis might bear relation to dysequilibrium. There may be a change in the uid dynamics o the inner Cha pter 1: Syndromes and Eponyms forty seven ear, giving rise to vestibular signs. A destructive surgical process o labyrinthectomy with or without eighth nerve part is indicated i the vestibular suppressants ail to management the dysequilibrium. The coexistence o otosclerotic oci around the vestibular labyrinth with elevated blood ats or blood glucose abnormalities could give rise to vestibular signs. There can additionally be evidence that an otosclerotic ocus may literally grow through the vestibular nerve. Ototoxic Drugs Ototoxic medication, predominantly aminoglycoside antibiotics, are normally used in li esaving situations where no other antibiotics are judged to be as e ective. The major symptom is oscillopsia and outcomes rom lack o otolithic enter to allow the eyes to preserve a stage horizon. The presence o this rotational unction indicates intact responses in other areas o vestibular sensitivity. In other cases, one is rustrated by an lack of ability to adequately deal with this situation. Perilymph Fistula In the absence o listening to loss, perilymph stula is a trigger o vertigo. The history should be straight orward or impulsive trauma or barotrauma, and the resultant signs clearly ollow. Associated signs o ear ullness, tinnitus, and gentle or uctuating listening to loss assist localize the problem to the ear. The de nitive diagnosis occurs at surgery, but there are situations the place there are equivocal ndings at surgical procedure. Posttraumatic Vertigo Posttraumatic vertigo contains a history o head trauma ollowed by a quantity o attainable signs, such as dysequilibrium. Syphilis: Congenital and Acquired The neurotologic ndings associated with syphilis normally present with bilateral M�ni�re syndrome. The sufferers, as a rule, are in their mid orties; nevertheless, when the onset occurs during childhood, the listening to loss is abrupt, bilaterally symmetrical, and more extreme.
Eastern Red Cedar. Keftab.
- What is Eastern Red Cedar?
- Are there safety concerns?
- Dosing considerations for Eastern Red Cedar.
- Cough, bronchitis, rheumatism, venereal warts, and skin rash.
- How does Eastern Red Cedar work?
- Are there any interactions with medications?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=97062
Intense enhancement of the residual lumen with distinguished section artifact is frequent following contrast administration antimicrobial zinc gel buy keftab 750 mg amex. Subarachnoid Hemorrhage and Aneurysms fusiform antibiotics ringworm buy 250 mg keftab overnight delivery, somewhat irregular contour (6-38) 606 antibiotic discount 375 mg keftab otc. In some cases antimicrobial 2014 keftab 125 mg purchase line, the residual lumen resides inside a bigger mass attributable to mural thrombus. Dolichoectasias are fusiform elongations of vessels-usually within the posterior circulation-without focal fusiform or saccular dilatations. Internal elastic lamina degeneration with myxoid changes and attenuation of the media are described findings at post-mortem. Circumferential involvement of the affected vessels is typical, as is extension into proximal branches. Hemangiomas are categorized as nonmeningothelial mesenchymal tumors and are mentioned in Chapter 22 with meningiomas and other mesenchymal neoplasms. Development of the human fetal vascular system occurs via two associated processes: vasculogenesis and angiogenesis. In vasculogenesis, capillary-like tubes develop first and represent the primary vascular plexus. This main capillary network is subsequently reworked into large-caliber vessels (arteries, veins) and small capillaries. The former are potentially amenable to endovascular intervention; the latter are both handled surgically or left alone. Intranidal aneurysm, feeding artery ("pedicle") aneurysm, and enlarged draining veins are shown. However, current animal studies have demonstrated that endothelial Notch4-induced arteriovenous shunts arise from the enlargement of preexisting capillary-like vessels. Their broadest floor is at or close to the cortex with the apex pointing towards the ventricles. Hemorrhagic residua such as gliosis and secondary ischemic adjustments are common, as are siderotic modifications within the overlying pia. Instead, varying amounts of laminated thrombus, dystrophic calcification, and hemorrhagic residua are often current. Small quantities of mind parenchyma within the nidus are often identified but are sometimes gliotic and nonfunctional. Headache with parenchymal hemorrhage is the most common presentation, occurring in about half of all sufferers. Other options related to bleeding include feeding artery aneurysm and venous outflow restriction. Note adjacent gyral swelling of the insula, left temporal lobe possibly related to vascular steal or postictal state. The broad cortical floor of the lesion is apparent, as are enlarged draining cortical veins. Nontraumatic Hemorrhage and Vascular Lesions one hundred sixty Other imaging findings related to hemorrhage danger include proof of earlier hemorrhage, presence of an intranidal aneurysm, and stenosis or thrombosis of a quantity of "outlet" draining veins. Embolization, surgery, stereotactic radiosurgery, or a mix of therapies are all present options in treating ruptured. Residua of previous hemorrhagic episodes corresponding to dystrophic calcification, gliosis, and blood in different phases of degradation can also complicate its appearance. Findings vary with vascular hemodynamics, the presence (and age) of associated hemorrhage, and secondary changes in the surrounding brain. This produces the appearance of a tightly packed mass or a "honeycomb" of "circulate voids" on each T1 and T2 scans (7-5A). Flow-related angiopathy may be present, starting from easy dilatation to endothelial thickening, stenosis, and occasionally even thrombosis and occlusion. Up to 50% include a minimum of one aneurysmally dilated vessel ("intranidal aneurysm"). The nidus contains little or no mind parenchyma and hence causes no important mass impact on the adjoining mind. Draining veins usually opacify in the mid to late arterial phase ("early draining" veins) (7-6B) (7-6C). Superselective injection of all feeding arteries delineates the nidus and helps define the presence of an intranidal aneurysm. Three-dimensional reconstructions with shaded floor display or 3D-printing fashions may be very useful in surgical planning and endovascular remedy. Revascularization surgical procedure with encephalo-duro-arteriosynangiosis to increase cortical blood provide by recruiting further dural arteries has been performed with some improvement reported in a couple of patients. Gamma knife radiosurgery has also been reported to enhance headache but not the related neurologic deficits. A dense, prolonged diffuse vascular "staining" of the affected parenchyma is frequent. Residual islands of brain parenchyma can normally be discerned in between the arterial network. Although the precise etiology is controversial, native hypoperfusion in a thrombosed dural venous sinus that leads to elevated intrasinus pressure is the most generally cited mechanism. Upregulated angiogenesis inside the dural sinus wall occurs after thrombosis and is considered the most likely etiology. Budding/proliferation of microvascular networks connects to a plexus of thin-walled venous channels, creating microfistulas. Size varies from tiny single vessel shunts to large complicated lesions with a quantity of feeders and arteriovenous shunts in the sinus wall. Multiple enlarged dural feeders converge within the wall of a thrombosed dural venous sinus (7-11). A network of innumerable microfistulas connects these vessels on to arterialized draining veins. Some lesions reveal angiographic development, whereas others stay comparatively secure. Almost 98% of lesions with out cortical venous drainage will comply with a benign medical course. The sinus has partially recanalized, and the distal sigmoid sinus and jugular bulb are partially opacified. Surgical or endovascular occlusion of the fistula or fistulous nidus is the best outcome. At a minimum, disconnection of the feeding vessels and draining veins is performed. Endovascular remedy with embolization of arterial feeders using particulate or liquid brokers with or without coil embolization of the recipient venous pouch/sinus may be performed. Surgical resection of the involved dural sinus wall or stereotactic radiosurgery are different options, used either alone or in combination with endovascular remedy. Hemorrhage is uncommon within the absence of cortical venous drainage or dysplastic venous dilatation. Contrast-enhanced scans may demonstrate enlarged feeding arteries and draining veins. Thrombus is typically isointense with brain on T1 and T2 scans and "blooms" on T2* sequences. The arterial supply to the dura is wealthy, advanced, and is derived from both the internal and exterior carotid techniques. Complete visualization of all carotid and vertebral branches, often together with superselective catheterization of dural and transosseous feeders, is often required to establish all arterial feeders, define the precise fistula web site, delineate venous drainage, and determine pedicle aneurysms (found in 20% of cases). Dural branches may also arise from the inner carotid and vertebral arteries (7-14D). The presence of dural sinus thrombosis, flow reversal with drainage into cortical (leptomeningeal) veins, and tortuous engorged pial veins (a "pseudophlebitic" pattern) should be identified and are extra widespread in patients with progressive mind illness (7-15). The left cerebellar hemisphere is mostly hypointense, reflecting venous stasis. The threat of a low-grade lesion converting to a highgrade sort is relatively low, but change in signs should prompt imaging reevaluation. There could also be little or no evidence for residual clot, and the fibrotic thrombosed sinus enhances strongly, mimicking regular venous filling. A pseudolesion of the jugular bulb, caused by sluggish or asymmetric move, could create inhomogeneous signal within the jugular foramen.
Specifications/Details
Small peripheral foci of diffusion restriction in several different vascular distributions are typical of multiple embolic infarcts (8-52) antibiotic yeast infection yogurt discount keftab 500 mg free shipping. The major differential prognosis of a number of embolic infarcts is hypotensive cerebral infarction (see below) best antibiotic for uti yahoo answers 375 mg keftab purchase with mastercard. Hypotensive infarcts are normally brought on by hemodynamic compromise and tend to involve the deep inner watershed zones antibiotics for acne rosacea buy keftab 750 mg. Signs and symptoms range in severity and include petechial rash antibiotics yellow urine generic 500 mg keftab, headache, seizure, drowsiness, altered mental standing, and coma. Onset is from 2 hours as much as 2 days after trauma or surgery, with a mean of 29 hours. The major differential prognosis of cerebral fats embolism syndrome is multiple embolic infarcts. Lesions are probably to contain the basal ganglia and corticomedullary junctions more than the white matter. Nontraumatic Hemorrhage and Vascular Lesions 226 Cerebral Gas Embolism Pathoetiology. Minor quantities of air within the intracranial venous methods is often iatrogenic, introduced during intravenous catheter placement. Other etiologies of arterial or venous air embolism embody lung biopsy, craniotomy in the sitting position, and angiography. Penetrating trauma, decompression sickness, and hydrogen peroxide ingestion are different causes of gas embolism. In extra severe instances, focal neurologic deficit, coma, seizures, and encephalopathy might ensue. Asymptomatic air following intravenous catheter placement is mostly noticed as an incidental finding, typically as dots of air within the cavernous sinus. If large air embolism happens, cerebral ischemia or diffuse brain swelling usually ensues (8-56). Lacunar Infarcts Terminology the terms "lacuna," "lacunar infarct," and "lacunar stroke" are sometimes used interchangeably. Lacunae are typically referred to as "silent" strokes, a misnomer as subtle neuropsychologic impairment is frequent in these patients. Lacunar stroke means a clinically evident stroke syndrome attributed to a small subcortical or brainstem lesion which will or will not be evident on brain imaging. Lacunae are thought-about macroscopic markers of cerebral small vessel ("microvascular") disease. There are two major vascular pathologies involving small penetrating arteries and arterioles: (1) thickening of the arterial media by lipohyalinosis, fibrinoid necrosis, and atherosclerosis inflicting luminal narrowing and (2) obstruction of penetrating arteries at their origin by massive intimal plaques within the mother or father arteries. Nontraumatic Hemorrhage and Vascular Lesions 228 pallidus, caudate nucleus), thalami, internal capsule, deep cerebral white matter, and pons. Grossly, lacunae seem as small, pale, irregular however relatively well-delineated cystic cavities (8-58). Microscopically, ischemic lacunar infarcts reveal tissue rarefaction with neuronal loss, peripheral macrophage infiltration, and gliosis. Clinical Issues Independent danger components for lacunar infarcts include age, hypertension, and diabetes. Between 20-30% of patients with lacunar stroke expertise neurologic deterioration hours and even days after the initial occasion. The pathophysiology of "progressive lacunar stroke" is incompletely understood, and no treatment has been proven to stop or halt development. Cavitation and lesion shrinkage are seen in additional than 95% of deep symptomatic lacunar infarcts on follow-up imaging. Embolic infarcts are sometimes peripheral (cortical/subcortical) somewhat than the same old central and deep location of typical lacunae. Watershed or "border zone" infarcts grossly resemble lacunar infarcts on imaging studies. However, "border zone" infarcts occur in specific locations-along the cortical and subcortical white matter watershed zones-whereas lacunae are more randomly scattered lesions that primarily affect the basal ganglia, thalami, and deep periventricular white matter. Anatomy of the Cerebral "Border Zones" Watershed zones are outlined because the "border" or junction the place two or more main arterial territories meet. Etiology Two distinct hypotheses-hemodynamic compromise and microembolism-have been proposed because the etiology of hemispheric watershed infarcts. Terminal vascular distributions usually have decrease perfusion stress than primary arterial trunks. Maximal vulnerability to hypoperfusion is biggest the place two distal arterial fields meet collectively. Hypotension with or without extreme arterial stenosis or occlusion can end result in hemodynamic compromise. Anteriorly, they center in the posterior frontal Arterial Anatomy and Strokes lobe close to the junction of the frontal sulcus with the precentral sulcus. Bilateral lesions are often associated to world discount in perfusion strain, often an acute hypotensive occasion. Confluent infarcts are giant, cigar-shaped lesions that lie alongside or just above the lateral ventricles. They resemble a line of beads extending from entrance to again within the deep white matter (8-63B). Nontraumatic Hemorrhage and Vascular Lesions 232 thalami, and pons and seem randomly scattered. Emboli are often bilateral and multiterritorial however also can occur at vascular "border zones. Death or severe lifelong neurologic deficits, together with motor impairment, cognitive deficiency, and developmental delay, are frequent. This part will emphasize the position of ischemia and hypoxia in perinatal brain injury and acknowledge that inflammatory elements. Focal ischemia refers to decreased or absent perfusion in a selected vascular territory. Global ischemia occurs when overall cerebral perfusion drops below the extent required to maintain normal brain perform. From the middle of the third trimester of pregnancy by way of the fortieth postconceptional week, the dorsal brainstem, thalami, basal ganglia, and perirolandic cortex exhibit excessive metabolic activity. Damage is mirrored in the interarterial (watershed) boundary or border zones and cerebral cortex (8-79A). In the 2nd trimester (gestational age of 14-26 weeks), ischemic harm results in liquefaction (8-80F); in the third trimester (27-40 weeks), ischemic injury leads to astrogliosis. Prolonged systemic hypoxemia ends in cardiac hypoxia, which in flip diminishes cardiac output. Focal hemorrhage is demonstrated on the caudothalamic groove, which represents the situation of the greatest aggregation of germinal matrix tissue. Linear accumulations of intraventricular hemorrhage are demonstrated throughout the frontal horns. Arterial Anatomy and Strokes 235 (8-70A) Coronal post-mortem specimen shows expansile clot inside the left lateral ventricle. Note the bihemispheric hypointense halos, representing neurons migrating outward from the germinal matrix. During the interval of early recovery (6-18 hours after insult), lactate and diffusivity abnormalities may transiently "normalize," only to revert to abnormality after 24 hours. This just so happens to complement the current brain cooling protocols that usually conclude on day 4. Normally, blood vessels of the brain constrict when blood pressure will increase and dilate when blood strain decreases. In the term newborn, hypoxia and hypercarbia lead to the lack of cerebral vascular autoregulation. Physiologic monitoring is required, and sedation is commonly wanted to control movement. Cranial sonography is well suited for germinal matrix and intraventricular hemorrhage detection, and follow-up, is low price, requires no sedation, is transportable to the bedside, and uses no ionizing radiation (8-67A). As an example, maternal chorioamnionitis leading to preterm start at 30 weeks (third trimester of pregnancy) with the next discovery of periventricular white matter harm probably represents a perinatal harm, not necessarily a neonatal injury. This nuance of understanding has sensible implications for our neuroimaging reports because of potential obstetrical and fetal maternal drugs authorized penalties.
Syndromes
- Dizziness
- Cyclosporine
- Urinary tract infections
- Acne
- Vasoactive intestinal peptide (VIP) level in the blood
- Overnight oxygen level measurements (oximetry)
- Joint pain or swelling
- Blood tests to see if you have celiac disease or a low blood count (anemia)
Related Products
Additional information:
Usage: gtt.
Tags: buy keftab 375 mg free shipping, discount 375 mg keftab fast delivery, 250 mg keftab order with visa, 500 mg keftab effective, order keftab 375 mg mastercard, generic keftab 500 mg online, discount keftab 125 mg mastercard, keftab 375 mg buy with amex, 375 mg keftab discount, keftab 500 mg order, generic keftab 750 mg with visa, order keftab 250 mg otc, keftab 125 mg generic mastercard, keftab 125 mg purchase online, keftab 375 mg best, purchase keftab 375 mg
8 of 10
Votes: 206 votes
Total customer reviews: 206
Customer Reviews
Chenor, 65 years: Surgical drainage and rapid initiation of empiric intravenous antibiotic therapy (initially vancomycin and a third-generation cephalosporin) has been proven to scale back mortality. Increasing head circumference with tense bulging fontanelles in a lethargic infant with "sundown eyes" is the typical presentation. Superficial components of the brain (cortex, subcortical white matter) are drained by cortical veins (including the vein of Trolard) and superior sagittal sinus (shown in green). Increased intracranial strain caused brain extrusion via a large craniectomy defect.
Ateras, 42 years: Scheibe aplasia Chapter 18 innitus wo categories based mostly on whether or not observer can hear the tinnitus (objective) or not (subjective). Signal depth on T2 is dependent upon the quantity of fibrocollagenous materials present. Rim enhancement-often the unfinished or "open ring" pattern-is seen through the acute inflammatory stage. Skull, dura, and backbone metastases are usually brought on by prostate, breast, or lung most cancers, followed by hematologic malignancies and renal cancers.
Randall, 35 years: The infundibular recess of the third ventricle extends inferiorly into the stalk for a variable distance. Subsequently, sufferers � 2014 MedStudy-Piease Report Copyright Infringements to copyright@medstudy. The virus is abundant within the saliva of the contaminated animal and is deposited in chunk wounds. Glottis (rima glottidis): The house between the ree margins o the true vocal cords i.
Ressel, 34 years: I this search is unrewarding, then the superior gland could be searched or extra in eriorly within the para- and retroesophageal area, extending rom the hyoid all the means down to the posterior mediastinum. Similarappearing neoplasms in the mind parenchyma are much less widespread and are termed extraventricular neurocytoma. Otoacoustic emission testing could additionally be per ormed to doc outer hair cell unction. Loculated and/or a number of unilateral collections are extra frequent than separate bilateral empyemas.
Kan, 28 years: Germ cell neoplasms do happen in different intracranial websites but are mentioned along with pineal parenchymal neoplasms. Note volume loss with enlarged proper frontal horn, gliotic brain surrounding old hematoma. Occasionally, injection into the vertebrobasilar system with manual compression of the ipsilateral carotid artery is critical to decide the fistula site. The threat o carcinoma in a cyst that has persisted a er aspiration makes an attempt ranges rom 10% to 30%.
Einar, 41 years: Fungal Histoplasmosis Incidence/Epidemiology � Caused by Histoplasma capsulatum, a dimorphic ungus ound within the Ohio and Mississippi River Valleys � Airborne transmission o avian or bat droppings Presentation � Will a ect these immunocompromised sufferers. Exceptions are mucinous tumors, cystic metastases, and tumors with large quantities of central necrosis, all of which might appear reasonably hyperintense. The pulmonary bifurcation, ligamentum arteriosum, and left recurrent laryngeal nerve all lie below the arch. Supplementally, a lumbar drain may be positioned to reduce the spinal uid reservoir till tissue is satis actorily sealed although that is rarely needed.
Gunnar, 48 years: Histologically, the intima is markedly thickened by circumferential or eccentric collagen deposition. Selected discussion of the leukodystrophies and nonleukodystrophic white matter issues focuses on abnormal myelin growth, myelin degeneration, and hypomyelination. Arrested pituitary improvement and unchecked proliferation are the probably etiology of this unusual tumor. Routine postoperative care is recommended as with different orbital procedures together with limitation o activity as nicely as nasal precautions.
Trano, 32 years: Any patient who is sent or imaging or suspected epiglottitis should be continuously attended by a physician capable o emergency airway administration. Great care must be taken to preserve the acial nerve, as the normal anatomy could also be somewhat distorted due to the mass e ect and surrounding edema rom the tumor. The most typical imaging sample is that of a cyst with a mural nodule and peripheral enhancement. Similarly, a patient with contralateral peripheral vestibulopathy might not tolerate even minor vestibular complications.