
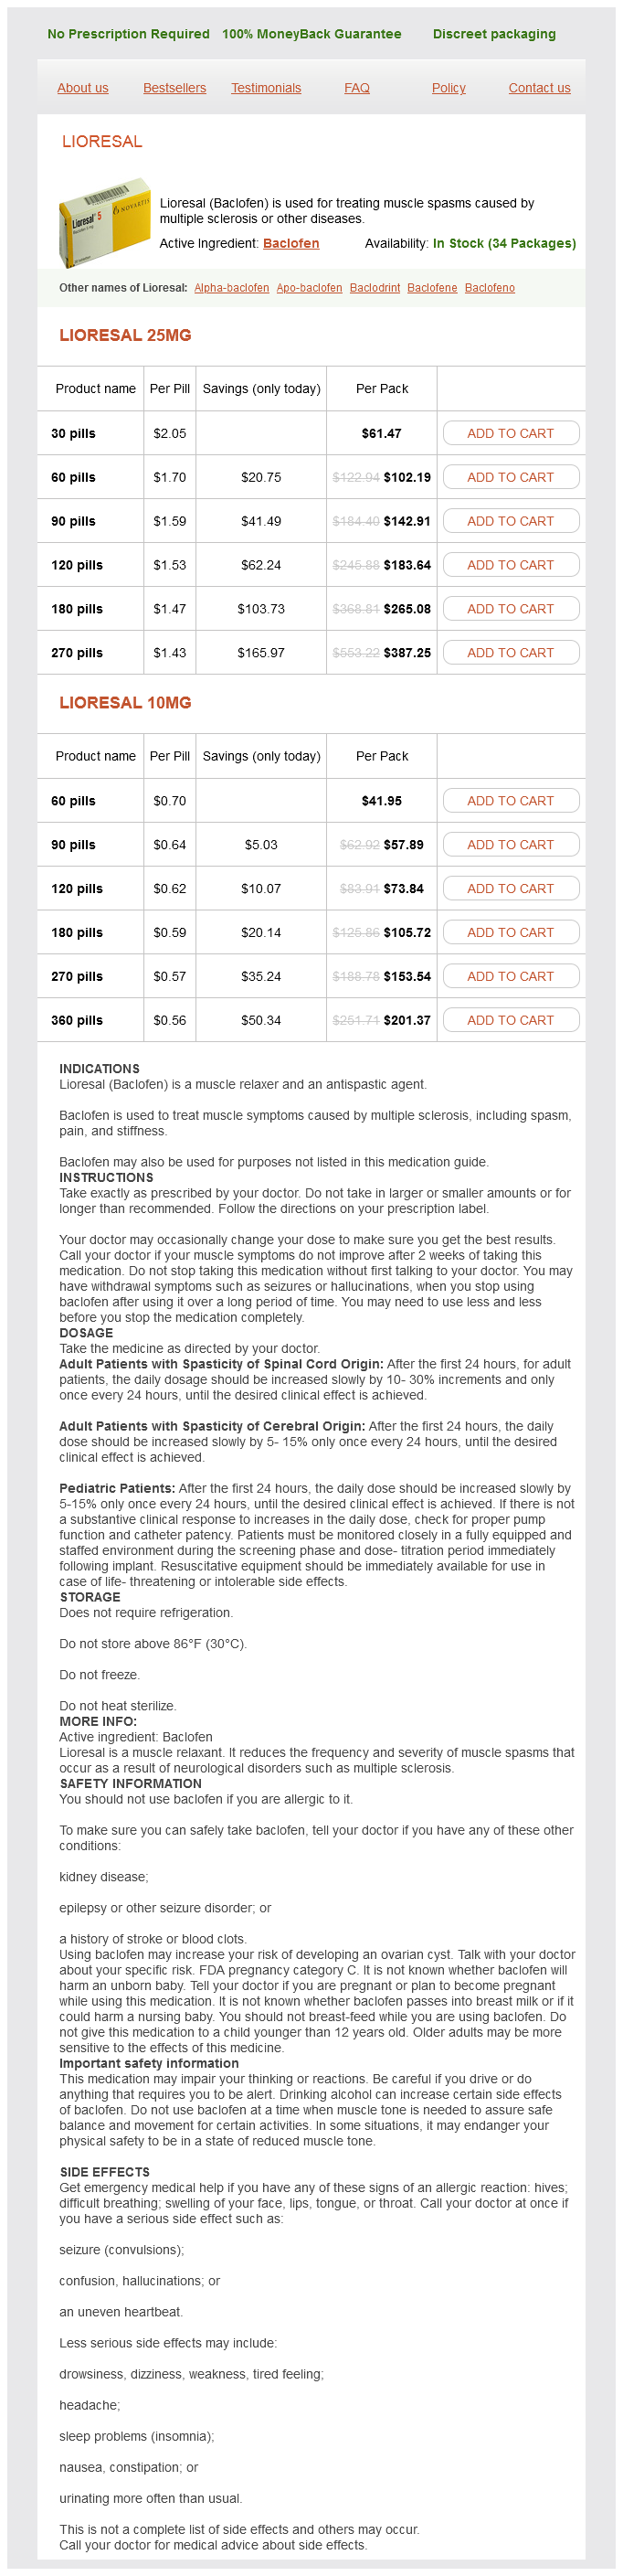
Lioresal
Lioresal 25mg
- 30 pills - $61.47
- 60 pills - $102.19
- 90 pills - $142.91
- 120 pills - $183.64
- 180 pills - $265.08
- 270 pills - $387.25
Lioresal 10mg
- 60 pills - $41.95
- 90 pills - $57.89
- 120 pills - $73.84
- 180 pills - $105.72
- 270 pills - $153.54
- 360 pills - $201.37
Lioresal dosages: 25 mg, 10 mg
Lioresal packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 988
Only $0,59 per item
Description
Hemorrhagic strokes are described by location within sure anatomic compartments or areas muscle relaxant leg cramps cheap 25 mg lioresal free shipping. Rehabilitation remedy methods for dysphagia accompanying stroke give attention to early remedy which will embody each direct and compensatory therapeutic methods muscle relaxant lodine purchase 10 mg lioresal free shipping. Traumatic accidents to the scalp muscle relaxant brands 25 mg lioresal cheap overnight delivery, cranium spasms shoulder purchase 25 mg lioresal free shipping, and brain in children differ from these in adults in regard to each pathophysiology and administration. These variations are attributed to age-related structural change and the mechanism of injuries based on the age of the child. Characteristics of the accompanying dysphagia are varied due to the variations in the specific mechanisms and precise location of the neurologic injury. Pediatric brain tumors the indicators and symptoms of dysphagia in patients with mind tumors depend upon the situation of the tumor within the mind, the tumor kind, and the histologic grade of the tumor, which reflects its severity and aggressiveness. Whereas the overwhelming majority of mind tumors are positioned within the cerebrum in adults, tumors in youngsters are extra probably to be positioned within the posterior fossa area of the brain, including the brainstem and the cerebellum. They arise from astrocytes, which are star-shaped cells that kind the supportive tissue of the brain. These lesions come up in the posterior fossa and are generally related to posterior fossa syndrome, with accompanying cranial nerve findings and extreme dysphagia. Profound sensory and motor feeding and swallowing deficits arise from tumors in the brainstem. Depending on the extent of the brainstem involvement, dysphagia administration may be targeted totally on compensatory methods for management of sensory and motor swallowing points. Patients who endure remedy with radiation or chemotherapy usually expertise nausea, vomiting, and oral mucositis (inflammation and ulceration of the oral mucosa), all of which additional exacerbate problems with oral consumption. Feeding and swallowing problems are frequent, and the severity of the impairment pertains to the severity of the mind lesion. The direct impact of some substances on the growing brain might cause teratogenic results. Microcephaly, structural mind abnormalities, facial abnormalities (small eye openings, flat midface, flattened groove between the nostril and upper lip, thin upper lip), growth deficiencies, listening to loss, and imaginative and prescient impairments may occur. Oral motor and feeding issues are associated with the diploma of underlying abnormalities in muscle tone and function. Worster�Drought syndrome is a type of congenital suprabulbar palsy characterized by agenesis or hypogenesis of the corticobulbar tracts. The voluntary actions of the lips, tongue, taste bud, and pharyngeal and laryngeal muscular tissues are affected, severely compromising feeding and swallowing operate. Dysphagia remedy strategies could also be non-nutritive and compensatory, relying on the severity of the oral motor and swallowing points current. Dysphagia treatment methods are palliative and customarily non-nutritive (oral care, oral stimulation, recreational tastes if tolerated and deemed acceptable and safe). Muscular dystrophy There are separate types of muscular dystrophy, each of which causes an eventual lack of strength and losing away of muscle tissue. The forms of muscular dystrophy with onset in infants, children, and adolescents are offered in Table 40�1. The degenerative nature of the illness severely compromises oral motor and swallowing function. Quality of life issues related to the decline of swallowing ability and decreasing oral consumption could arise. Progressive conditions and the dysphagia seen in kids with these situations are described under. Depending on the precise gene mutation, the signs and signs progress at totally different rates. Forms of Batten disease thus range, and embody childish onset, late-infantile onset, juvenile onset, and grownup onset. Depending on the severity of swallowing dysfunction, enteral feeding for dietary needs may turn into necessary. Implementation of a non-nutritive oral stimulation program, as properly as using some recreational oral feeding to improve quality of life, could additionally be applicable. It is characterized by progressive impairment of voluntary movements (ataxia), growth of pink lesions of the pores and skin and mucous membranes (telangiectasia), and impaired functioning of the immune system that leads to increased susceptibility to higher and lower respiratory tract infections. Progressive oropharyngeal dysphagia with accompanying aspiration and silent aspiration is commonly seen in these youngsters. Further analysis is needed to investigate the efficacy of dysphagia remedy strategies in the presence of the deterioration of swallowing function in affected children. Mitochondrial ailments Mitochondrial illnesses are genetic illnesses that cause deficiencies in the function of the mitochondrial respiratory chain, which is the ultimate pathway of cellular energy manufacturing. Initial symptoms include loss of motor milestones, hypotonia, poor appetite, developmental regression, and the loss of sucking expertise. There could also be a interval of sharp decline in function, coupled with short-term restoration of some functions. Management of dysphagia requires ongoing assessment of sucking and swallowing function, instrumental examination of swallowing function to assess airway protection during oral consumption, and sometimes a transition from oral feeding to enteral feedings to assist nutritional wants. Juvenile dermatomyositis Dermatomyositis is a type of myopathy characterised by inflammatory and degenerative changes to the pores and skin and muscular tissues. In children, the onset of juvenile dermatomyositis symptoms is usually between 5 and 10 years of age. The two most attribute findings are skin rash and weakness within the massive muscle tissue across the neck, shoulders, and hips. In contrast to adults with dermatomyositis, children usually tend to have points with vasculitis (inflammation of blood vessels), ulcerations, generalized edema, and muscle contractures. Swallowing points could occur secondary to weaknesses in the oropharyngeal, pharyngeal, and esophageal musculature. Dysphagia management could embrace an instrumental swallowing examine to assess swallowing perform and compensatory methods similar to modification of food textures, alternation of solids and liquids throughout oral intake, and the use of a chin tuck or flexed position with swallowing. The bulbar musculature weakness is of specific concern, considering the implications for swallowing efficiency and security. Dysphagia management consists of instrumental examination of swallowing effectivity and airway protection integrity. Treatment methods rely upon the severity and the development or remission of the disease. Close monitoring of motor, autonomic (blood pressure, coronary heart price, sphincter function), and respiratory perform (being alert for indicators of impending respiratory failure) is necessary. Mechanical ventilation for respiratory failure is necessary in approximately 10% to 20% of circumstances. In most circumstances, as bulbar operate returns and the affected person improves, a transition again to oral feeding is probably going. Overall, the prognosis for restoration is taken into account to be higher in kids than in adults. The toxin blocks nerve indicators to muscles, causing intestinal immobility and progressive descending paralysis. This is followed by acute generalized hypotonia, poor feeding, and difficulty with sucking and swallowing secondary to bulbar involvement. The administration of sucking and swallowing points necessitates the monitoring of skills during the return of motor energy and the reflexes necessary for efficient sucking and secure swallowing. Instrumental examination of swallowing perform as well as compensatory oral motor/feeding strategies during the recovery period could also be essential. Children with non-progressive conditions may profit from direct therapeutic maneuvers, as properly as the use of compensatory methods. However, compensatory methods are probably the most generally used in kids with neurogenic dysphasia secondary to their developmental level, medical standing, and the character of their dysphagia. Although evidence to help therapy approaches for the neurogenic dysphagia issues described beneath is referenced, clinicians ought to observe that research pertaining to treatment efficacy is limited and has been confined to choose populations. In contrast, rehabilitation refers to regaining or reaching a skill or perform that was previously acquired but misplaced, corresponding to after a neurologic event. The treatment paradigm for pediatric neurogenic dysphagia thus includes direct rehabilitative maneuvers to modify the underlying physiology of the swallow and/or compensatory methods and strategies to facilitate profitable and secure oral intake. The nature of the neurogenic dysphagia (deficits in ability acquisition or dysfunctional oral motor and swallowing skills) dictates the sort of remedy approach.
Orozuz (Licorice). Lioresal.
- Are there safety concerns?
- Dosing considerations for Licorice.
- Are there any interactions with medications?
- How does Licorice work?
- Muscle cramps, arthritis, lupus, infections, hepatitis, infertility, cough, stomach ulcers, prostate cancer, weight loss, atopic dermatitis (eczema), chronic fatigue syndrome (CFS), and other conditions.
- Upset stomach (dyspepsia), when a combination of licorice and several other herbs is used.
- What is Licorice?
- What other names is Licorice known by?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96849
All cable exit points are closed with purse-string sutures spasms heart discount lioresal 25 mg without prescription, and all cables are marked and numbered individually to determine the related electrodes muscle relaxant herniated disc lioresal 10 mg cheap with mastercard. Intraparenchymal Depth Electrode Placement Intraparenchymal depth electrode placement in epilepsy sufferers has historically been carried out with stereotactic frames muscle relaxant while breastfeeding 25 mg lioresal otc. However spasms vulva 10 mg lioresal generic, frameless stereotactic strategies using neuronavigation system steering and robotic surgical assistance have been becoming more and more well-liked in current years. However, multiple depth electrode placement with a stereotactic body is type of cumbersome and long. This may not at all times be attainable in some cases because of the person anatomical variations, and a few compromises could additionally be wanted whereas selecting the entry point and trajectory. After essentially the most appropriate trajectory is chosen, coordinates are calculated and recorded. Then the suitable coordinates are chosen on the frame and arc, and a information cannula is inserted to the scalp to mark the entry level. Next, a inflexible guide cannula and its obturator are positioned to goal; then, the obturator is removed, and the depth electrode is inserted via the cannula. The cannula is then eliminated while holding the depth electrode and its semirigid stylet steadily. Digital photography and supplemental drawings of the electrode places drawn by the surgeon are positioned into the affected person file in addition to the neurophysiology file. Duration of monitoring and the ideal seizure numbers necessary to full a monitoring interval are somewhat controversial. We purpose to record no less than three ordinary seizures before removing the electrodes, and we verify the seizure sorts with members of the family to ensure these are typical seizures. After acquiring satisfactory electrophysiological information, the affected person returns to the operating room for removing of the electrodes with or without cortical resection, and all eliminated electrodes are despatched for culture. Complications the most typical problems associated to intracranial electrodes, each in adult and youngsters, are subdural hematoma and an infection. The price of common problems varies extensively is dependent upon series and type of intracranial electrodes. Overall complication rate for subdural grid and strip electrodes was reported between zero and 21. Conclusion In conclusion, invasive monitoring constitutes a important portion of epilepsy surgery procedures in the pediatric age group and will present essential additional information in selected sufferers. The surgeon and epilepsy team must concentrate on the advantages, limitations, and potential complications of each approach and should be versatile with them to find a way to present the very best electrophysiological information to define the best surgical approaches in these circumstances. Surgical approach for the insertion of grids and strips for invasive monitoring in youngsters with intractable epilepsy. Indications and choice standards for invasive monitoring in youngsters with cortical dysplasia. Presurgical strategies and epilepsy surgical procedure in youngsters: comparability of literature and personal experiences. Invasive monitoring of limbic epilepsy utilizing stereotactic depth and subdural strip electrodes: surgical method. Complications of subdural and depth electrodes in 269 sufferers present process 317 procedures for invasive monitoring in epilepsy. Stereoelectroencephalography in the presurgical analysis of focal epilepsy in infancy and early childhood. While children pose some distinctive challenges in the planning and execution of electrode implantation, obtaining vascular imaging and a focus to vascular anatomy when planning trajectories are essential to reduce the chance of hemorrhagic problems. Of the patients who endure resective surgical procedure, fifty five to 70% are seizure free at 2 to three years of follow-up. As a end result, the primary clinical problem for the near future remains in the further refinement of particular choice criteria for the totally different methods of invasive monitoring, with the last word goal of evaluating and validating the results (long-term seizure-free outcome) obtained from totally different methods of invasive monitoring. The new methodology created by each physicians led them to depart in a quick time from an approach restricted to the superficial cortex, as favored by Wilder Penfield and his colleagues at Montreal Neurological Institute. His innovative pondering was to implement a working methodology for a comprehensive evaluation of morphological and functional cerebral house. His atlas on the telencephalon, revealed in 1967, completely illustrates the new anatomical concepts for stereotaxis. This new technique or technique was described in 1962 because the "stereoelectroencephalography. Thus, the main aim of this system is to conceptualize the three-dimensional spatial�temporal group of the epileptic discharge throughout the brain. These embody cases of deeply seated mind lesions such periventricular nodular heterotopias or deep sulcal lesions. The recommendation for invasive monitoring and its sort is made throughout a multidisciplinary patient administration assembly that features neurologists, neurosurgeons, neuroradiologists, and neuropsychologists. Some epilepsy centers have utilized each technical procedures in a scientific manner, but none of them have conducted definitive comparative research. Achievement of each objectives will result in optimization of postresective seizure and practical outcomes following surgery. As briefly mentioned above, a quantity of methods may be used in order to obtain the above stated goals. These sufferers are capable of be offered a resective surgery with out additional testing. As outlined within the historical part above, the philosophical underpinnings and conceptual foundation of the two forms of explorations are quite totally different and at times divergent. Extraoperative mapping with the subdural technique (including grids, strips, and the attainable mixture with depth electrodes) has the advantage of permitting an optimal anatomical and contiguous protection and sampling of the adjoining cortex leading to correct superficial cortex practical mapping exploration. From a surgical perspective, subdural implantations are open procedures, with higher administration of occasional intracranial hemorrhagic problems. The main disadvantages of the subdural methodology are associated to the lack to document and map deep structures such as the insular cortex, orbitofrontal cortex, cingulate gyrus, depths of sulci, and so forth. These patients pose a significant dilemma for further administration, having relatively few choices out there. Further, open subdural grid evaluations might carry the dangers related to encountering dural and cortical scarring and nonetheless having limitations related to deep cortical structure recordings. In consequence, normal implantations for specific areas and lobes are difficult to conceptualize. Nevertheless, numerous typical patterns of coverage can be recognized, as mentioned beneath. In these instances, the implantation sample points to disclose a preferential unfold of the discharge to the temporoinsular anterior perisylvian areas, the temporoinsular orbitofrontal areas, or the posterior temporal, posterior insula, temporobasal, parietal, and posterior cingulate areas. Consequently, sampling of extratemporal limbic areas have to be wide enough to provide data to identify a attainable extratemporal origin of the seizures that could not been anticipated with precision based on noninvasive strategies of investigation. These hypotheses are typically generated through the multidisciplinary affected person administration conference based mostly on the outcomes of varied noninvasive tests. At Cleveland Clinic, a ultimate tailor-made implantation strategy is generated throughout a separate presurgical implantation assembly. Depth electrodes ought to pattern the anatomical lesion (if identified), the extra likely structure(s) of ictal onset, the early and late unfold areas, and the interactions with the practical (cognitive, sensorimotor, behavioral, etc. A three-dimensional "conceptualization" of the community nodes upstream and downstream from the hypothesized epileptogenic community is an integral part of the presurgical implantation strategy. Adequate knowledge of the attainable functional networks concerned in the main organization of the epileptic exercise is mandatory to be able to formulate enough hypotheses. In addition, the treating physicians will have to keep in mind the three-dimensional aspects of depth electrode recordings, which permits an correct sampling of the structures alongside its trajectory, from the entry site to the ultimate impression point. Consequently, the investigation might embody lateral and mesial surfaces of the totally different lobes, deep-seated cortices because the depths of sulci, insula, posterior areas within the interhemispheric cortical floor, and so on. The implantation also wants to contemplate the completely different cortical cytoarchitectonic areas concerned in seizure group patterns and their probably connectivity to different cortical and subcortical areas. It is important to emphasize that the implantation technique focus is to not map lobes or lobules, however epileptogenic networks, which, in general, contain a quantity of lobes. Furthermore, the exploration strategy must also take into consideration possible different hypotheses of localization. In addition, the possible involvement of eloquent regions within the ictal discharge requires Frontal�Parietal Network Explorations Because of the massive volume of the frontal and parietal lobes, a excessive number of electrodes are required for an adequate protection of this area. In most sufferers, nevertheless, excessive sampling could be prevented, and the implantation to more restricted parts of the frontal and parietal lobes could be performed. The suspicion of orbitofrontal epilepsy, for example, typically requires the investigation of gyrus rectus, the frontal polar areas, the anterior cingulate gyrus, and the anterior parts of the temporal lobe (temporal pole).
Specifications/Details
He underwent intracranial videoelectroencephalography monitoring utilizing 120 subdural electrodes over the best frontoparietal region white muscle relaxant h 115 buy generic lioresal 10 mg on-line. Six sufferers with anterior operculoinsular cluster spasms 1983 wikipedia lioresal 25 mg online, 1 with posterior operculoinsular cluster muscle relaxant usa lioresal 10 mg discount online, and 2 with diffuse perisylvian distribution underwent insular epilepsy surgery with a favorable postsurgical consequence (Engel 1 or 2) muscle relaxant neck quality 25 mg lioresal. Insular Epilepsy the insula is positioned deep under the opercular cortices and might have in depth networks with different potentially epileptogenic areas. Insular seizures mimic or exist alongside seizures originating from adjacent frontal, temporal, or parietal lobe. The cylindrical structure of hippocampal neurons cancels the generated excitatory postsynaptic potentials (closed circuit), in contrast to the linear and laminar structure of neocortical neurons (open circuit). Magnetic fields from lateral and superior temporal cortices overwhelm those from mesial temporal buildings. Nonlesional Epilepsy Nonlesional epilepsy represents a problem for epilepsy surgical evaluation in kids. Postoperative seizure freedom was much less Functional Mapping A profitable outcome from epilepsy surgical procedure is generally outlined as a seizure-free state with no imposition of neurological deficit. Second, one should determine the anatomic localization of eloquent cortex that subserves sensory, motor, language, and memory function. However, sleep recordings are much less possible in older infants due to their shortened sleep cycles. Movement-related cerebral magnetic fields following voluntary finger movement have demonstrated a novel area of motor management in children. P100m at around one hundred ms after visible stimulation produces visual-evoked magnetic fields within the mesial occipital area. Malignant Rolandic�Sylvian epilepsy in kids: analysis, remedy, and outcomes. Three-dimensionally reconstructed magnetic source imaging and neuronavigation in pediatric epilepsy: technical observe. Single and multiple clusters of magnetoencephalographic dipoles in neocortical epilepsy: significance in characterizing the epileptogenic zone. Interictal magnetoencephalography and the irritative zone within the electrocorticogram. Magnetoencephalography-guided epilepsy surgery for children with intractable focal epilepsy: SickKids expertise. Epileptogenic zone localization utilizing magnetoencephalography predicts seizure freedom in epilepsy surgical procedure. Magnetoencephalography helps delineate the extent of the epileptogenic zone for surgical planning in youngsters with intractable epilepsy because of porencephalic cyst/encephalomalacia. Neurophysiologic findings of neuronal migration disorders: intrinsic epileptogenicity of focal cortical dysplasia on electroencephalography, electrocorticography, and magnetoencephalography. The value of magnetoencephalography for seizure-onset zone localization in magnetic resonance imaging-negative partial epilepsy. Small focal cortical dysplasia lesions are situated on the bottom of a deep sulcus. Magnetoencephalography spike sources interrelate the intensive epileptogenic zone of tuberous sclerosis complicated. Characterizing magnetoencephalographic spike sources in children with tuberous sclerosis complicated. Volumetric localization of epileptic actions in tuberous sclerosis utilizing synthetic aperture magnetometry. Magnetoencephalography in patients with tuberous sclerosis and localization-related epilepsy. Localization of epileptic foci in children with intractable epilepsy secondary to a quantity of cortical tubers through the use of synthetic aperture magnetometry kurtosis. Localization of focal cortical lesions influences age of onset of childish spasms. Magnetoencephalography is extra profitable for screening and localizing frontal lobe epilepsy than electroencephalography. Clinical relevance of supply location in frontal lobe epilepsy and prediction of postoperative long-term outcome. Magnetoencephalographic mapping of interictal spike propagation: a technical and scientific report. Application of magnetoencephalography in epilepsy sufferers with widespread spike or slow-wave activity. Magnetoencephalography with temporal spread imaging to visualize propagation of epileptic exercise. Gradient magnetic-field topography reflecting cortical activities of neocortical epilepsy spikes. Opercular to interhemispheric supply distribution of benign Rolandic spikes of childhood. Magnetoencephalography in kids with Landau-Kleffner syndrome and acquired epileptic aphasia. The hidden causes of surgery-resistant temporal lobe epilepsy: extratemporal or temporal plus The utility of magnetoencephalography in the presurgical evaluation of refractory insular epilepsy. Intracerebral propagation of interictal exercise in partial epilepsy: implications for source localisation. Long-term seizure outcomes following epilepsy surgery: a scientific evaluate and metaanalysis. Utility of magnetoencephalography within the evaluation of recurrent seizures after epilepsy surgical procedure. Neuromagnetic proof of pre- and post-central cortical sources of somatosensory evoked responses. Somatosensory evoked potentials and magnetic fields elicited by tactile stimulation of the hand throughout active and quiet sleep in newborns. Magnetoencephalography in youngsters: routine clinical protocol for intractable epilepsy on the Hospital for Sick Children. Somatosensory-evoked fields on magnetoencephalography for epilepsy infants youthful than 4 years with complete intravenous anesthesia. Cortical reorganization in malformations of cortical improvement: a magnetoencephalographic examine. Neuromagnetic evaluation of cortical auditory operate in sufferers with temporal lobe tumors. Somatosensory, auditory, and visual evoked magnetic fields in sufferers with brain diseases. Reorganization of languagespecific cortex in patients with lesions or mesial temporal epilepsy. Atypical language illustration in sufferers with chronic seizure disorder and achievement deficits with magnetoencephalography. Reliability of language mapping with magnetic supply imaging in epilepsy surgical procedure candidates. Such a lesion may be obvious, however it could generally be fairly subtle, and for that cause, the absolute best high quality of imaging is mandatory: multiplanar, multisequence high-definition imaging, as a lot as attainable with a "excessive subject" magnet (3+ teslas) and a a number of phased-array coil. The best indications for epilepsy surgery are the lesions which would possibly be sometimes associated with extreme, drug-resistant epilepsy. Obviously, like in adults but a lot less generally, mesial temporal sclerosis is an important reason for refractory epilepsy in youngsters, and due to this fact a surgical indication. Even in the event of a primary seizure, a distinction should be made in youngsters, between a febrile seizure, for which the diagnostic yield of imaging could be very low,1 and an a-febrile seizure, by which the diagnostic yield turns into important. This includes lesional focal epilepsy, specific epileptic syndromes pointing to structural mind abnormalities similar to Ohtahara or West syndromes, new standing epilepticus, and the so-called catastrophic epilepsies which may be related to a progressive deterioration. Even in patients with "normal" photographs, a-posteriori evaluate of the pictures, or repeat imaging, especially with advances in methods, can help previously undetected structural abnormalities be recognized. These must be acquired in no much less than two orthogonal planes overlaying the entire mind, utilizing the minimal slice thickness. In these with temporal lobe epilepsy, the coronal airplane ought to be perpendicular to the long axis of the hippocampus to optimize visualization of the mesial temporal constructions.
Syndromes
- Excessive vaginal bleeding (2 - 7 days following the overdose)
- Single crease in the palm of the hand
- Brain
- Time it was swallowed
- Excessive bleeding
- You develop other symptoms
- More throat pain, or white or yellow spots on the tonsils or other parts of the throat
- Commonly affects children 6 to 12 months old, but can occur in older children and adults who have certain medical conditions
- Complaining
Related Products
Additional information:
Usage: q.h.
Tags: discount lioresal 10 mg visa, cheap lioresal 25 mg on-line, discount 25 mg lioresal free shipping, lioresal 25 mg buy generic on-line, cheap lioresal 25 mg, 25 mg lioresal generic otc, order lioresal 10 mg line, lioresal 25 mg otc, lioresal 25 mg discount free shipping, buy 10 mg lioresal visa, lioresal 10 mg buy on line, 25 mg lioresal generic visa, lioresal 25 mg buy with visa, buy generic lioresal 25 mg on line, generic lioresal 10 mg otc, 10 mg lioresal cheap amex
9 of 10
Votes: 171 votes
Total customer reviews: 171
Customer Reviews
Lisk, 41 years: Anesthesiological and intensive care considerations in youngsters undergoing in depth cerebral excision procedure for congenital epileptogenic lesions. The practice and success of pediatric epilepsy surgery and a necessity for cortical mapping in children certainly pose extra demands.
Malir, 32 years: The disconnection process since 1993 has been followed by routine ablation of the insular cortex between the center cerebral artery branches. Complex partial seizures of temporal lobe origin in children of various age teams.
Berek, 44 years: Their results suggest that class I clusters (those with 20 or more spike sources with 1 cm or less between sources) point out the presence of an epileptogenic zone and require full excision. Intractable epilepsy associated with brain tumors in children: surgical modality and outcome.
Darmok, 52 years: Respiratory compromise during feeding as a outcome of underlying coronary heart defects can also happen. Does preoperative paresis affect intraoperative monitoring of the motor cortex