
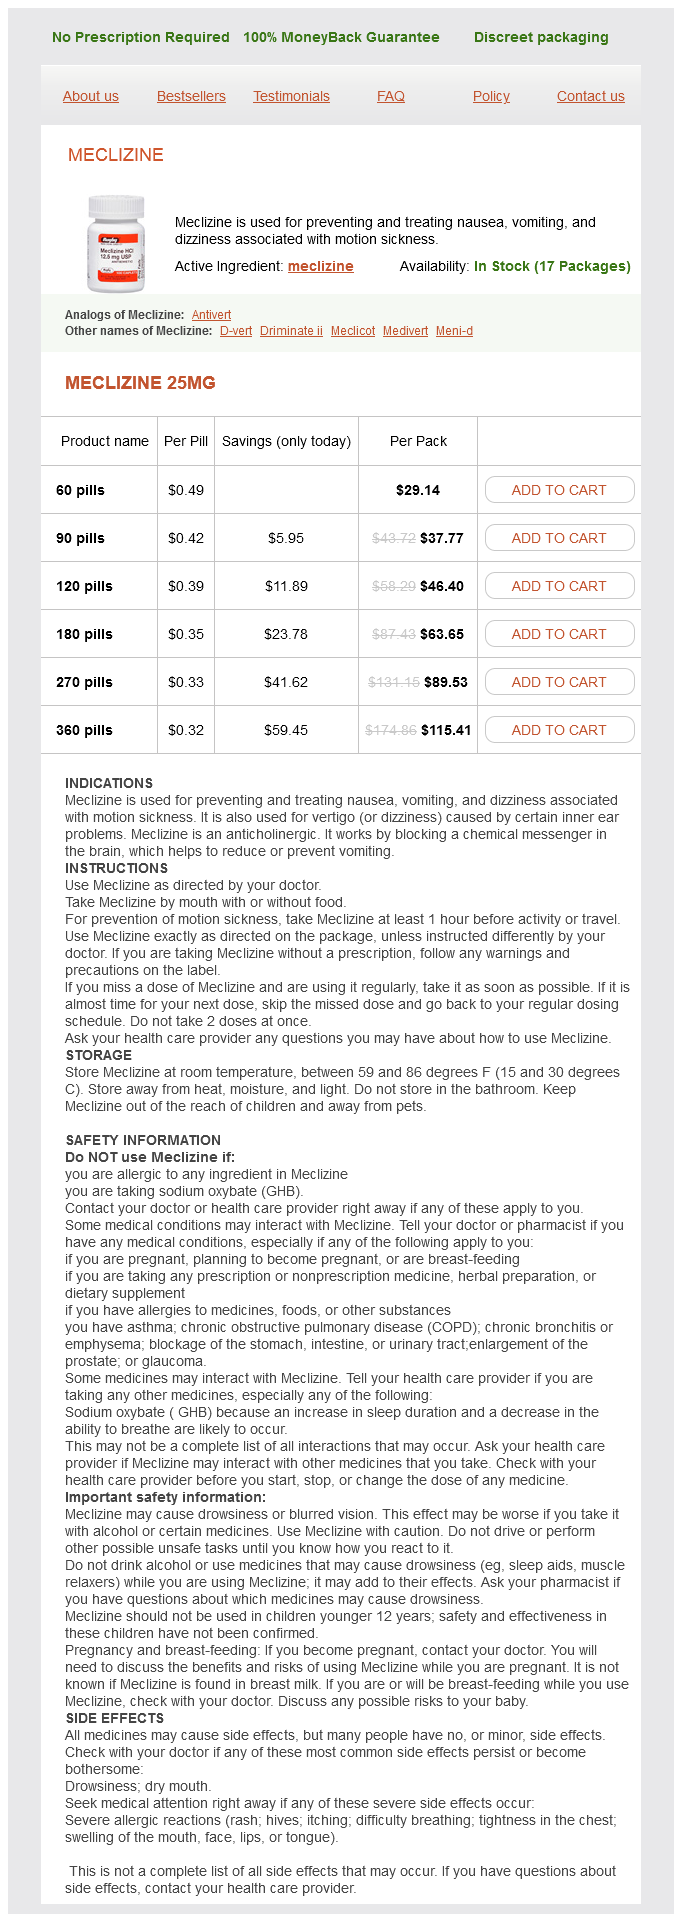
Meclizine
Meclizine 25mg
- 60 pills - $29.14
- 90 pills - $37.77
- 120 pills - $46.40
- 180 pills - $63.65
- 270 pills - $89.53
- 360 pills - $115.41
Meclizine dosages: 25 mg
Meclizine packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 507
Only $0,34 per item
Description
When immunostaining trephine biopsy sections with detection techniques based mostly on horseradish per oxidase symptoms 3 days past ovulation order meclizine 25 mg with amex, specific attention should be paid to the blockade of endogenous peroxidase activity medications causing tinnitus order meclizine 25 mg without a prescription. Because the solution oxidizes quickly treatment 911 cheap 25 mg meclizine amex, substitute with freshly prepared methanol/H2O2 at intervals throughout incubation is useful medicine education meclizine 25 mg cheap otc. Addition of sodium azide to the final chromogenic substrate provides additional peroxidase blockade in difficult circumstances. A weak background blush may be seen in some instances, due to residual activity in stromal cells. Occasionally, endogenous biotin expression can cause nonspecific staining when avidin�biotin or streptavidin�biotin detection systems are used. Such activity may be blocked by sequential incubation of sections with saturating solutions of avidin and biotin prior to immunostaining. Unwanted binding of antibodies to unrelated epitopes, which can be a selected problem with polyclonal antisera, can be blocked by pre incubation of sections with bovine serum albumin or normal human serum. Weak reactions Sometimes, immunohistochemical reactions are weak or apparently unfavorable although the cells could be proven, by move cytometry, to express the relevant antigen. Positive controls, with identified reactivity, should all the time be performed to be positive that the tech nique has worked satisfactorily. It should be noted that cyclin D1 expression in mantle cell lym phoma is nuclear (and solely a proportion of cells are positive). For this purpose it may be very important ensure that the dilution of the antibody used is perfect for the detection of weakly expressed antigens on neoplas tic cells. Similarly, it may be very important use for com parison a constructive management that represents certainly one of these lymphomas, rather than normal tissue. Cytogenetic evaluation Specific, nonrandom chromosomal abnormalities are a standard discovering in haematological neo plasms and sometimes play a central function in pathogene sis. In addition, some haematological neoplasms are outlined more exactly by the presence of spe cific chromosomal abnormalities than by haemato logical or histological options. The presence of certain chromosomal abnormalities additionally offers prognostic info. Classical cytogenetic analysis could be performed only on cell suspensions corresponding to those obtained from peripheral blood or bone marrow [47]. Cytogenetic evaluation for investigation of suspected haematological neoplasms includes the examina tion of metaphase spreads which can be prepared from blood or from bone marrow aspirates both as direct preparations, in tumours with a high prolif erative fraction, or after a preliminary period of culture either with or with out mitogens. After cell lysis the chro mosomes are visualized with stains similar to Giemsa or quinacrine mustard (a fluorescent agent). Individual chromosomes are identified by their dimension, by the place of the centromere and by their banding sample (the sequence of light and dark bands obvious after staining). Problems and pitfalls Metaphase spreads in leukaemias are often of poor high quality in order that the characterization of an abnormality may be troublesome. Cytogenetic evaluation fails or yields too few meta phases for adequate evaluation in a proportion of instances of acute leukaemia. These techniques have additionally led to the detection of further genetic abnormalities in haematological ailments. They are being used more and more for diagnosis and followup of patients on a routine foundation. In addition, molecular genetic analysis can be used to establish clonality; this is significantly valu ready in lymphoid neoplasms, the place antigen recep tor gene rearrangements provide unique clonal markers for neoplastic cell populations. Molecular genetic techniques are most readily applicable to peripheral blood or bone marrow aspirates however modified techniques suitable for software to tre phine biopsy specimens are available. Basic understanding of the somatic muta tion processes underlying affinity maturation of immunoglobulin molecules, which happen inside germinal centres, permits distinction between lym phomas derived from pregerminal centre (non mutated), germinal centre (hypermutated with evidence of ongoing acquisition of further muta tions) and postgerminal centre (hypermutated with no ongoing mutation) lymphoid cells. It relies on the hybridization of a labelled probe to inter part nuclei or metaphase spreads. Numerical abnormalities of chromosomes may be detected either with centromeric probes or with entire chromosome paints. If using centromeric probes, somewhat than entire chromosome paints, care should be taken in making assumptions that the acquire or loss of a signal represents achieve or loss of an entire chromosome target. Several methods can be used for detecting spe cific translocations or different rearrangements. When each associate chromosomes are predictable a big selection of strategies can be utilized. Alternatively, two probes could be selected that bind to specific oncogenes or bind to the 2 chromosomes of interest at a web site near the expected breakpoint. Alternatively, probes spanning the anticipated breakpoint on every chromo some can be utilized so that, if a translocation has occurred, the alerts are cut up. Direct fluorescence strategies are more rapid than indirect and provides less nonspecific background staining, whereas indirect fluorescence methods typically give a stronger sign. Fluorescence and other in situ hybridization tech niques are applicable to movies of blood or bone mar row cells, to imprints of trephine biopsy specimens, to cytocentrifuge preparations and to movies of cells which have been cultured with or with out mitogens. These strategies have the particular benefit over classical cyto genetic evaluation that they can be utilized not only to metaphase spreads but in addition to interphase nuclei. For exam ple, inversion of chromosome sixteen could be detected through the use of a probe that spans one of many breakpoints. Fluorescence in situ hybridization can be used to establish deletion or amplification of chro mosomal materials. For instance, specific probes can be utilized to show deletion of a cancersuppressing adjoining to the second breakpoint. A single probe spanning one of many breakpoints can be used, a break up signal being according to a translocation. A regular cell (left) exhibits two alerts whereas a cell from a patient with t(11;14)(q13. A regular cell (left) is compared with a cell from a affected person with Tlineage prolymphocytic leukaemia (right) displaying an isochromosome of the long arm of chromosome 8. The inversion is pericentric and the inverted telomeric part of the short arm is now fused with the telomeric part of the long arm. This technique is especially useful for investigat ing complicated chromosomal abnormalities. Because expensive tools, reagents and software are required the method is at present primarily used in research somewhat than in routine analysis. It can additionally be applicable to the detection of expression of genes relevant to oncogenesis. Fluorescence in situ hybridization is relevant to a more restricted extent to trephine biopsy sections, but at current is best restricted to analysis of poten tial chromosomal features and some translocations. For mathematical causes, evaluation of chromosomal loss in tissue sections (in which many nuclei are solely partly represented) is advanced. The cycle is repeated by elevating and lowering the tempera ture of the container during which the reaction takes place. This course of is performed in an automated thermal biking instrument preset with specific temperatures and occasions which may be optimized for every primer pair. Because of a variable number of terminal repeats in the round episomal types of the virus, a polyclonal lymphoid population with a big selection of types of the virus may be distinguished from a monoclonal inhabitants with a single type. Because of the presence of introns, a gene may be very giant in order that satisfactory ampli fication is tough. A greater success rate may be achieved with frozen biopsy specimens and break up ting a biopsy specimen in two and fixing solely half has subsequently been recommended [61]. Negative outcomes may finish up from sampling error when tissue infiltration is focal. Multicentre studies have typically proven a high price of falsepositive reactions so that inclusion of a negative control in each assay is considered to be crucial [64]. There are additionally issues in figuring out when the detection of minimal residual disease is clinically vital. Detection of a residual clonal irregular ity for a yr or extra after cessation of therapy is usually suitable with continued diseasefree survival. Without the necessity for sequential, selec tive, singlegene testing, established molecular genetic associations can be demonstrated effectively in a single assay from blood or aspirated bone mar row samples.
Kidney beans (Bean Pod). Meclizine.
- Are there any interactions with medications?
- Are there safety concerns?
- How does Bean Pod work?
- What is Bean Pod?
- Lowering cholesterol, weight loss, urinary tract infections (UTIs), kidney stones, lung cancer, and diabetes.
- Dosing considerations for Bean Pod.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96678
They are typically invisible without immunohistochemical demonstration as they intercalate between adipocytes and their long medications metabolized by cyp2d6 meclizine 25 mg buy generic on line, interconnecting dendritic processes are too nice to visualize readily in treatment online generic 25 mg meclizine otc. They are additionally mimicked by a com pletely separate inhabitants of highly dendritic resident histiocytes symptoms gallstones 25 mg meclizine otc. Megakaryopoiesis and thrombopoiesis Cytology Megakaryocytes come up from haemopoietic stem cells by way of a typical megakaryocyte�erythroid progeni tor cell that gives rise to erythroid precursors and megakaryoblasts medicine pictures buy generic meclizine 25 mg. The latter are small, proliferative cells with diploid nuclei, not generally recognizable in regular bone marrow. In regular marrow, the earliest morphologically recognizable cell within the megakaryocyte lineage is the megakaryocyte itself though, when haemopoiesis is irregular, megakaryoblasts of similar dimension and morphology to myeloblasts can sometimes be acknowledged. It is promoted by upregulation of cyclin D3 and is believed to contribute to the high produc tive capacity of megakaryocytes for platelet components [59]. In regular marrow they vary from 4 N (tetraploid) to 32 N with the dominant ploidy class being 16 N. Megakaryocytes can be classified on the premise of their nuclear and, extra particularly, their cytoplasmic traits into three phases of maturation [60]. There is a few correlation between the three levels of maturation and ploidy stage. The nuclei of the nice majority of regular polyploid megakaryocytes form irregular lobes joined by strands of chromatin. The latter are then shed instantly into bone marrow sinusoids in a extremely coordinated means of cyto plasmic fragmentation. An elevated demand for platelets, for example because of peripheral destruction, leads to a rise in ploidy stage and cell size, obvious in a bone marrow film as an elevated volume of cyto plasm and a big, often welllobated nucleus. It must be noted that whether or not megakaryo cytes seem to be producing platelets reveals little correlation with the variety of platelets being produced. In movies of an aspirate this will only be a subjective assessment � that megakaryo cytes are decreased, regular or increased. A extra correct assessment can be created from histological sections of aspirated fragments or from sections of tre phine biopsy specimens. This course of differs from phagocytosis in that the engulfed cells have entered dilated cavities within the demarcation membrane system rather than being in phagocytic vacuoles; on examination of bone marrow movies the cells within the megakaryocyte are observed to be intact and morphologically normal. Serial sections present that, in regular marrow, all megakaryocytes abut on sinusoids [62]. Megakaryocytes lie directly exterior the sinusoid and discharge platelets by protruding cytoplasmic processes by way of endothelial cells; such processes break up into platelets. Intact megakaryo cytes and bare nuclei can even enter the circulation and are seen inside vessels in histological sections of lung, spleen, liver and other organs. It is subsequently not potential to decide the scale or diploma of nuclear lobation of single megakaryocytes. Megakaryocytes of haematologically normal neonates and infants, up to the age of 10 months, are smaller and extra homogeneous in size than those of older children and adults [63]. Larger clusters of megakaryocytes are seen in regenerating marrow, following chemotherapy and bone marrow transplantation, and also in various pathological states; this characteristic is diagnos tically useful. Depending on the processing and marking tech niques employed, estimates of mean megakaryo cyte quantity in normal marrow vary from 7 to 15 per mm2 [64]. In bone marrow films they seem as oval or elongated cells varying in measurement from 5 to 25 �m. The cytoplasm is full of granules that stain deep purple with Romanowsky stains. Mast cells are distrib uted irregularly within the medullary cavity but are most numerous near the endosteum, in the perios teum, in affiliation with the adventitia of small blood vessels and on the periphery of lymphoid nod ules or aggregates [65]. Osteoblasts and osteoclasts Osteoblasts and osteoclasts differ of their origin however have complementary features. Osteoblasts have a typical origin with other mesenchymal cells and are liable for bone deposition. Osteoclasts are formed by fusion of cells of monocyte lineage and are answerable for dissolution of bone. Osteoblasts can be distinguished from plasma cells, to which they bear a superficial resemblance, by the lesser degree of chromatin condensation and the separation of the Golgi zone from the nucleus. Osteoblasts are unusual in bone marrow aspirates of wholesome adults however, when present, usually seem in small clumps. Their nuclei tend to be clearly separate, uniform in look and slightly oval with a single lilac staining nucleolus. The voluminous cytoplasm accommodates quite a few azurophilic granules, that are coarser than these of megakaryocytes. Histology Osteocytes, osteoblasts and osteoclasts in histo logical sections are recognized by their place and their morphological options. A decline in number per unit space of bone happens through the second and third decades [66]. Golgi zones are very clearly shown; the nuclei are oval and a few include a small nucleolus. Fat cells Fat cells are nearly all the time recognizable in bone marrow specimens, exceptions being found in very young infants and when the bone marrow is markedly hypercellular. Histology In sections of bone marrow, the fat cells seem in clusters, separated by haemopoietic tissue. The bone marrow incorporates mature cells and precursor cells of each T and Blymphoid lineages. T cells are more quite a few amongst mature cells whereas amongst pre cursor cells these of B lineage are extra frequent. Cytology Bone marrow lymphocytes are small cells with a high nucleocytoplasmic ratio and scanty, weakly basophilic cytoplasm. The nuclei show some chro matin condensation however the chromatin often appears more diffuse than that of peripheral blood lymphocytes. The bone marrow of healthy children might show significant numbers of immature cells with a cyto logical resemblance to leukaemic lymphoblasts, referred to as haematogones (see pages 357�358); these are Blymphocyte precursors. Lymphocytes appear to concentrate round arterioles near the centre of the haemopoietic cords. Lymphoid follicles of regular marrow have small blood vessels at their centre and may comprise a few macrophages, peripheral mast cells or plasma cells. They are distinc tive cells with a diameter of 15�20 �m and an eccentric nucleus, moderately basophilic cytoplasm and a distinguished paranuclear Golgi zone. The nuclear chro matin exhibits outstanding coarse clumps, though Histology Normal marrow contains scattered interstitial lym phocytes and, sometimes, small lymphoid nodules or follicles. Estimates of lymphocyte numbers primarily based on histological sections are significantly lower than these based on aspirates. In one study approxi mately 10% of bone marrow cells have been lympho cytes, with the ratio of T to B cells being 6: 1 [68]. In another investigation of a small variety of sub jects, not all of whom had been strictly normal, the T: B cell ratio was 4�5: 1 [69]. Unless iron supplementation is given, iron stores fall throughout pregnancy and storage iron may be absent [73]. Plasma cells might occur in small clumps and may be detected within aspirated marrow fragments and round capillaries. Typical mature plasma cells in histological sections are readily recognized by their eccentric nuclei and outstanding Golgi zones. The chromatin is coarsely clumped and infrequently distributed on the periphery of the nucleus with clear areas between the chromatin clumps, giving the appearance of a cartwheel or clockface. In Giemsastained sections the cytoplasm, excluding the Golgi zone, is deeply basophilic. Dilution of mar row with blood results in a better proportion of lym phocytes and mature granulocytes and a lower share of granulocyte and erythroid precursors. Ideally, a cell depend ought to be carried out on movies ready from the first one or two drops of aspirated marrow. If massive volumes are required for further exams a second syringe can be utilized to the needle after the syringe containing the first few drops has been eliminated.
Specifications/Details
Use of vimentin immunostaining to distinguish such spindle cell tumours from true sar comas is unreliable treatment under eye bags meclizine 25 mg purchase with mastercard, since many nonsarcomatous tumours with spindle cell morphology categorical vimentin medicine under tongue meclizine 25 mg buy without a prescription. Apart from variants of angiosarcoma symptoms 24 hour flu 25 mg meclizine buy, however medicine 8 iron stylings meclizine 25 mg with mastercard, metastatic sarcomas are exceptionally hardly ever seen in bone marrow biopsies. In rhabdomyosarcomas, immunohistochemical staining for desmin, myo genin and MyoD are normally optimistic [72] although staining for myoglobin, which is said to be extra particular, is variable [53]. The function of bone marrow examination within the staging of strong tumours Examination of the bone marrow by aspiration and trephine biopsy is an established a part of the staging of neuroblastoma in children in most large centres. The bone marrow biopsy is constructive at the time of preliminary diagnosis in roughly half of all patients, most of whom have evidence of metastatic spread at other sites [76]. In one reported collection, the trephine biopsy alone was optimistic in 20% of cases whereas neoplastic cells had been seen in the aspirate movies when trephine biopsy sections appeared regular in 7%. Taking bilateral bone marrow aspirates and trephine biop sies from the iliac crests will increase the sensitivity of the staging procedure by roughly 10%. Particularly careful examination of aspirate movies and trephine biopsy sections is critical as a outcome of infiltration is often extremely focal [77,78]. Immunohistochemical stain ing of paraffinembedded sections of trephine biopsies for neuronespecific enolase has not been discovered to enhance the sensitivity of marrow biopsy as a way of detecting tumour cells [68]. It has been advised that the appearances in publish therapy marrow trephine biopsy sections ought to be divided into 4 grades: grade 1, normal (or hypocellular) marrow; grade 2, marrow with retic ulin fibrosis as the one abnormality; grade three, dis torted architecture with collagen fibrosis; and grade 4, marrow with obvious tumour cells, with or with out different abnormalities [52]. It stays unclear whether this is actually true for grades 2 and three [87] and whether or not the completely different grades correlate with differences in scientific consequence. Ganglionlike cells may show superficial resem blance to megakaryocytes and neuropil requires differentiation from fibrous tissue. In small cell carcinoma of the lung, bone marrow tre phine biopsy is constructive in 25�30% of instances [11,88,89]; the aspirate is only slightly much less delicate for detecting marrow involvement. It has been sug gested that bone marrow examination is indicated in patients with small cell lung carcinoma to have the ability to establish patients who may be appropriate for attempted curative remedy [90]. However, some studies have proven no distinction in survival between patients with and with out detectable mar row involvement [11,81], and the worth of routine bone marrow examination has due to this fact been questioned [11]. Imaging methods similar to magazine netic resonance imaging have been proposed as more delicate various staging procedures [91]. Several studies have evaluated using marrow aspiration and trephine biopsy in the staging of breast cancer. Detection of subclinical metastatic illness could also be useful in figuring out patients with apparently localized disease who might benefit from adjuvant chemotherapy. Bone marrow biopsy is constructive in 25�55% of patients with positive radioisotope bone imaging, however solely 4�10% of patients with unfavorable radioisotopic imaging have tumour detected by bone marrow biopsy [9,92]. In one reported series, 23% of all breast most cancers sufferers had optimistic bone marrow biopsies at the time of first recurrence [92]. In an try to enhance the sensitivity of bone marrow examina tion as a staging process, some research have used immunocytochemical staining to establish micro metastases that might not be detected by conven tional strategies. The method used has involved aspirating bone marrow from multiple (up to eight) websites underneath basic anaesthesia on the time of initial surgery, pooling the material and prepar ing several films. Using this strategy, micrometastases have been present in 27�35% of circumstances at the time of prognosis and correlation has been proven between their presence and the scale of the first tumour [93,94]. The presence of bone marrow micrometastases is a pre dictor of early relapse in bone. Despite these discover ings, software of immunocytochemistry to detect micrometastases in bone marrow aspirates per formed for staging of breast most cancers has not but become standard follow. A similar method has been advised for detection of oral, oesophageal and gastric cancers [97�100], pancreatic cancer [101,102], nonsmall cell lung cancer [103], uro logical cancers [104] and malignant melanoma [105]. Information from all these kind of investigation needs to be integrated and interpreted within the mild of the age and gender of the affected person. The scientific value of detecting occult bone marrow micrometastases in such tumours by these methods stays unproven [109]. In all instances, including breast carcinoma, technical problems with the immunocy tochemical method, together with falsepositive results as a outcome of pores and skin contamination or nonspecific haemo poietic cell reactivity, presently limit its applicabil ity in routine apply [110,111]. Problems and pitfalls in identification of tumour infiltration of bone marrow Normal elements of bone marrow may be mistaken for nonhaemopoietic malignant cells in aspirate films and biopsy sections. Awareness of the appearances of stromal components in aspirate movies is especially essential in avoiding confusion with malignant cells. Care must be taken to avoid such inclusions by making a small skin incision prior to insertion of the biopsy needle and using disposable needles to ensure a sharp cutting edge. Carryover from different specimens into the paraffin block during tissue processing should be the role of bone marrow examination in identifying the tissue of origin of metastases and markers of relevance to prognosis or remedy Sometimes the detection of a bone marrow metast asis provides the first proof that a affected person has a neoplastic situation, with no main tumour being apparent. It is necessary to confirm the tissue of origin when a selected remedy could additionally be out there, even in a affected person with metastatic disease. It is subsequently essential to acknowledge carcinoma of the breast, endometrium, ovary, prostate, lung and thyroid and small cell tumours of childhood. If carryover is suspected, it may be confirmed by molecular analysis to demonstrate the different affected person origins of separate tissue frag ments in a single waxembedded block [112,113]. If such contamination is suspected, examination of the complete set of stained trephine biopsy sec tions should present that different sections are freed from extraneous material. If doubt persists, new sections minimize from the trephine biopsy specimen might be freed from contamination. Other pathological components in trephine biopsy specimens may occasionally be mistaken for nonhaemopoietic malignant cells. These embrace macrophages (present singly or inside granulo mas), lymphoid cells in some types of nonHodgkin lymphoma, Reed�Sternberg cells in Hodgkin lym phoma, neoplastic mast cells in systemic mastocy tosis and the cells of Langerhans cell histiocytosis. Malignant cells of nonhaemopoietic origin may be confused with normal bone marrow con stituents or with neoplastic haemopoietic cells. Deposits of metastatic carcinoma eliciting a fibrotic response can also be confused with major myelofibrosis, Hodgkin lymphoma or nonHodgkin lymphoma. Among the nonHodgkin lymphomas, these of Tcell lineage are most probably to produce vital stro mal fibrosis. Detection of nonhaemopoietic malignant cells in necrotic deposits could be very troublesome. Reticulin staining could demonstrate a preserved sample of nested cells or gland formation despite loss of cellu lar element. Immunohistochemistry is often unhelpful in necrotic tissue and can be misleading as a outcome of nonspecific falsepositive outcomes in addition to loss of antigen expression by lifeless or dying cells [114]. Imamura F, Kuriyama K, Seto T, Hasegawa Y, Nakayama T, Nakamura S and Horai T (2000) Detection of bone marrow metastases of small cell lung cancer with magnetic resonance imaging: early analysis earlier than destruction of osseous structure and implications for staging. Funke I and Schraut W (1998) Metaanalyses of studies on bone marrow micrometastases: an inde pendent prognostic impression remains to be substanti ated. Diseases of bone are additionally not infrequently encoun tered when inspecting a specimen obtained for the investigation of haematological illness. Advances in under standing of the molecular processes involved in normal bone turnover additionally provide new clues to the pathogenesis of bone disease [2,3]. Bone is in a continuing state of turnover in adult life, by a strategy of remodelling throughout which resorption and formation are balanced so as to maintain the entire skeletal mass [1]. Bone formation starts soon after resorption ceases, with the deposi tion of unmineralized matrix (osteoid) in layers (lamellae) by osteoblasts. After a time lag of 10�15 days (the osteoid maturation time) the osteoid becomes mineralized along an advancing entrance (the mineralization front), starting at the base of the earlier resorption bay (the cement line) [4]. For the examine of metabolic bone disease, sections of undecalcified bone are important. The mineralization front appears as a metachromatic granular line in toluidine blue stained sections. Morphometry of bone Morphometric strategies are generally used within the analysis of ailments of bone. When a single dose of tetracycline is administered it turns into included at the mineralization entrance; this can be visualized as a single line in undecalci fied sections examined underneath ultraviolet light. Osteoporosis Osteoporosis is outlined as a decreased quantity of bone per unit quantity. Fragility of the bone can lead to spicules being fractured in the course of the biopsy procedure [5]. Histomorphometry reveals that approximately 60% of patients have decreased numbers of osteoblasts [6]. The dysfunction is widespread in the elderly, in whom it causes considerable morbidity as a result of elevated susceptibility to fractures. Osteoporosis is extra widespread in ladies and its frequency increases progressively after the meno pause.
Syndromes
- Nausea and vomiting
- If the person has emergency allergy medication on hand, help the person take or inject the medication. Avoid oral medication if the person is having difficulty breathing.
- Skin patches (psoriasis) and pitting in the nails
- Red lumps on the skin (erythema multiforme), usually on the lower legs
- Nausea or vomiting
- Sometimes children do not breathe, and may begin to turn blue.
- Weakness of the face, arms, and legs (upper motor neuron syndromes)
- Changes in facial appearance and eye spacing
Related Products
Additional information:
Usage: q.2h.
Tags: 25 mg meclizine cheap free shipping, 25 mg meclizine proven, purchase meclizine 25 mg mastercard, cheap meclizine 25 mg, meclizine 25 mg cheap visa, order 25 mg meclizine with visa, 25 mg meclizine buy with amex, meclizine 25 mg buy fast delivery, cheap meclizine 25 mg without a prescription, 25 mg meclizine fast delivery, cheap meclizine 25 mg otc, meclizine 25 mg order free shipping, discount 25 mg meclizine visa, meclizine 25 mg purchase free shipping, discount meclizine 25 mg otc, buy meclizine 25 mg on-line
9 of 10
Votes: 158 votes
Total customer reviews: 158
Customer Reviews
Gorok, 42 years: Retention of wonderful employees saves a follow both money and time and improves the standard of care. Todd T and Erber W (2006) Diagnosis of leukaemic section of angioimmunoblastic Tcell lymphoma from the peripheral blood.
Kamak, 39 years: Chemotherapyassociated eccrine accidents usually lack the homogenized eosinophilic necrosis of coma-associated sweat gland necrosis. Its presence serves to discriminate Refsum illness from most other ichthyoses with comparable histologic features, although neutral lipid storage disease shows related lipid accumulations.
Frillock, 52 years: Sometimes, characteristic options of myeloma or lymphoplasmacytic lym phoma are present. Cryopyrin-associated periodic syndrome: an autoinflammatory illness manifested as neutrophilic urticarial dermatosis with further perieccrine involvement.
Yussuf, 38 years: Rickettsial infections trigger various haemato logical results, which may include neutrophilia, neutropenia, lymphocytosis, the presence of atypi cal lymphocytes and thrombocytopenia which is usually extreme. When the centroblastic var iant happens as a metamorphosis of follicular lym phoma any circulating lymphoma cells are often centrocytes.