
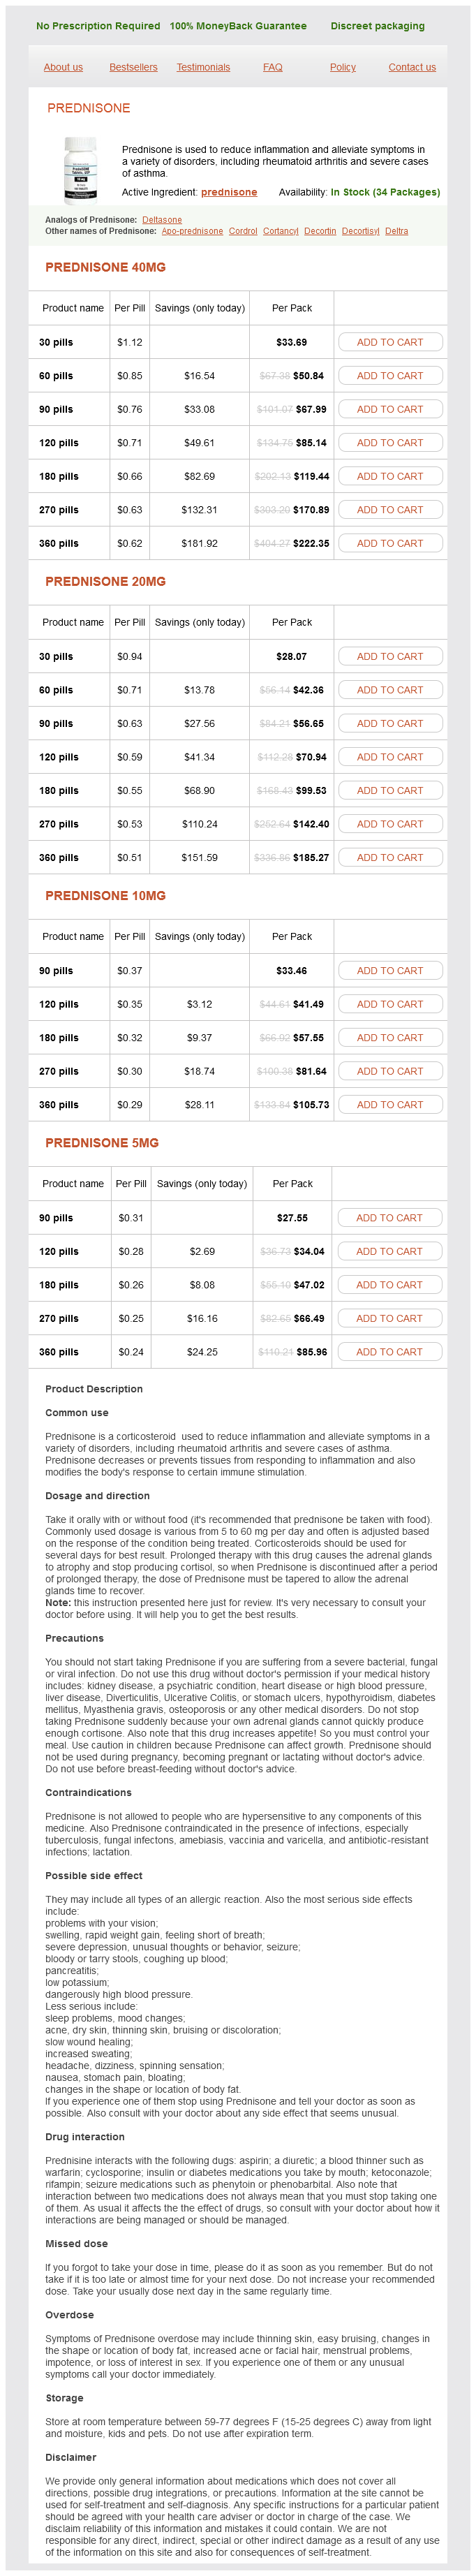
Prednisone
Prednisone 40mg
- 30 pills - $33.69
- 60 pills - $50.84
- 90 pills - $67.99
- 120 pills - $85.14
- 180 pills - $119.44
- 270 pills - $170.89
- 360 pills - $222.35
Prednisone 20mg
- 30 pills - $28.07
- 60 pills - $42.36
- 90 pills - $56.65
- 120 pills - $70.94
- 180 pills - $99.53
- 270 pills - $142.40
- 360 pills - $185.27
Prednisone 10mg
- 90 pills - $33.46
- 120 pills - $41.49
- 180 pills - $57.55
- 270 pills - $81.64
- 360 pills - $105.73
Prednisone 5mg
- 90 pills - $27.55
- 120 pills - $34.04
- 180 pills - $47.02
- 270 pills - $66.49
- 360 pills - $85.96
Prednisone dosages: 40 mg, 20 mg, 10 mg, 5 mg
Prednisone packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 643
Only $0,25 per item
Description
When reconstituted as directed penicillin allergy symptoms uk 40 mg prednisone generic with visa, Infuvite Adult contains not extra than 70 mcg/L of aluminum allergy x-ray 40 mg prednisone buy fast delivery. Pediatric: Each dose must be added to a minimal of a hundred mL of dextrose allergy medicine 7 year program buy cheap prednisone 20 mg line, saline allergy shots rush immunotherapy purchase 20 mg prednisone visa, or other suitable infusion answer. Pediatric accommodates not more than forty two mcg/L of aluminum, and Infuvite Pediatric accommodates not more than 30 mcg/L of aluminum; see Precautions. Storage: Before use, refrigerate at 2� to 8� C (36� to 46� F) protected against light. Once a pharmacy bulk vial has been penetrated, full dispensing inside 4 hours. Some manufacturers counsel that admixture or Y-site administration with vitamin solutions must be averted. A a quantity of vitamin answer containing fat-soluble and water-soluble vitamins in an aqueous answer. A day by day multivitamin maintenance supplement for patients receiving parenteral diet. Blood ranges of A, C, D, and folic acid might decline in patients receiving parenteral multivitamins as their sole source of nutritional vitamins for four to 6 months. Range is from vitamin needs may exceed those of nonpregnant ladies to security to be used in pregnancy not established; use provided that clearly needed. Range is from vitamin wants might exceed those of nonpregnant ladies to not recognized if secreted in breast milk; use warning if required throughout breast-feeding. Additional vitamin A supplementation could also be needed, especially in low-birth-weight infants. Rare when administered as beneficial: Agitation; allergic reactions together with anaphylaxis, angioedema, periorbital and digital edema, shortness of breath, urticaria, and wheezing; nervousness; diplopia; dizziness; erythema; fainting; headache; pruritus; rash. Vitamin A and vitamin D hypervitaminosis (symptomatology associated to hypercalcemia) may occur with extended use of great doses. With onset of any facet effect, discontinue administration immediately and notify physician. Rapid infusion will increase the risk of local opposed reactions such as phlebitis and thrombosis. Has a potent cytostatic effect on lymphocytes, inhibiting proliferation of both Band T-lymphocytes. Plasma concentrations of metabolites are elevated in sufferers with renal impairment. If contact happens, wash thoroughly with soap and water; rinse eyes with plain water. Appears to be related to the depth and duration of immunosuppression quite than to any specific agent. Reduction in immunosuppression must be considered for patients who develop proof of recent or reactivated viral infections. Physicians must also think about the chance that decreased ity to bacterial, viral, fungal, and protozoal infections, including opportunistic infections and viral reactiva tion of hepatitis B and C, which may lead to hospitalizations and fatal outcomes. Hemiparesis, apathy, confusion, cognitive deficiencies, and ataxia are essentially the most generally observed scientific indicators. Repeat weekly during the first month, twice monthly for the second and third months, then monthly thereafter for the first yr. Has been noticed most frequently within the interval from 31 to a hundred and eighty days posttransplant. May be as a end result of mycophenolate, concomitant medications, viral infections, or some mixture of these causes. Effective contraception should be used throughout therapy and for 6 weeks following cessation of therapy. Females with reproductive potential must be recommended regarding pregnancy prevention and planning. Avoid tasks that require alertness if somnolence, confusion, dizziness, tremor, or hypotension is experienced throughout remedy with mycophenolate. Avoid use of mycophenolate during being pregnant if safer remedy choices are available. Use during being pregnant provided that profit justifies danger; ought to being pregnant occur during treatment, talk about the desirability of constant the pregnancy. Women using mycophenolate at any time during pregnancy are encouraged to enroll within the National Transplantation Pregnancy Registry. Patients considering pregnancy should focus on with their doctor appropriate various immunosuppressants with much less potential for embryo-fetal toxicity. Consider age-related decreased organ function and/or further medical issues and drugs. Monitor levels closely when cyclosporine is added or faraway from a drug routine containing mycophenolate. Other reactions that occurred in at least 20% of patients throughout clinical trials included abdominal pain, asthenia, bone marrow suppression. Duration of remedy varies with the kind and severity of an infection and with the general condition of the patient; decide by the scientific and bacteriologic response. Usual period of therapy is no less than 14 days for extreme staphylococcal infections and longer (4 to 6 weeks) for endocarditis and osteomyelitis. Pediatric sufferers over 1 month of age: Moderate infections: one hundred to one hundred fifty mg/kg/day in equally divided doses each 6 hours (25 to 37. Severe infections: one hundred fifty to 200 mg/kg/24 hr in equally divided doses each 4 to 6 hours (25 to 33. Dose adjustment not required for sufferers with renal dysfunction, including those receiving hemodialysis. May be given through Y-site or with additive tubing or could additionally be added to bigger volume of compatible options. A semi-synthetic penicillinase-resistant penicillin, used for its bactericidal activity towards gram-positive organisms, primarily penicillinase-producing staphylococci (methicillin-susceptible isolates only). Readily distributes into most body fluids and tissues except the aqueous humor of the attention and spinal fluid. Mainly eradicated by hepatic inactivation and excretion in bile; a small quantity is excreted in urine. Known hypersensitivity to any penicillin or cephalosporin (not absolute); see Precautions. Prediluted solutions containing dextrose could also be contraindicated with identified allergies to corn merchandise. If susceptibility checks point out that an infection is as a outcome of of methicillin-resistant Staphylococcus species, remedy ought to be discontinued and various therapy supplied. Actual incidence of crossallergenicity not established however may be more widespread with first-generation cephalosporins. Consider in patients who current with diarrhea during or after therapy with nafcillin. In worsening hepatic operate, threat versus good thing about continued use ought to be re-evaluated. Larger doses may trigger neurologic adverse reactions, including convulsions, particularly with concomitant impaired hepatic insufficiency and renal dysfunction. Elevation of liver transaminases and/ or cholestasis could occur, specifically with greater doses. For extreme symptoms discontinue the drug, deal with hypersensitivity response (antihistamines, epinephrine, corticosteroids), and resuscitate as necessary. Titrate to a dose and interval that gives sufficient analgesia and minimizes opposed reactions; see Dose Adjustments. Manufacturer lists as incompatible with nafcillin (Nallpen) and ketorolac (Toradol). May produce the identical diploma of respiratory despair as an equianalgesic dose of morphine. Has potent opioid antagonist activity at doses equal to or decrease than its analgesic dose. Management of pain extreme enough to require an opioid analgesic and for which different therapies are inadequate. Respiratory melancholy could happen at any time, however danger is biggest throughout initiation of remedy or after a dose improve. To reduce the chance of respiratory melancholy, correct dosing and titration are essential.
Chinese Dodder (Dodder). Prednisone.
- Are there safety concerns?
- How does Dodder work?
- Bladder, liver, and spleen problems.
- What is Dodder?
- Dosing considerations for Dodder.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96067
Post-Marketing: Aggression cat allergy shots uk buy prednisone 5 mg low price, agitation allergy medicine zyrtec generic prednisone 40 mg buy discount on line, agranulocytosis allergy medicine 75 buy generic prednisone 40 mg on line, angioedema allergy testing tacoma prednisone 40 mg discount with visa, hallucinations, insomnia, new or worsening seizures, psychotic disorder, rash, Stevens-Johnson syndrome, poisonous epidermal necrolysis, urticaria. Some could not require intervention, and others might improve with a lowered dose or discontinuation of lacosamide; see Precautions and Side Effects. No particular antidote in overdose; nonetheless, hemodialysis will remove roughly 50% of a dose in 4 hours. All sufferers in the initial medical studies were treated with both antipyretics and antihistamines. Total ultimate quantity must be 100 mL for patients weighing less than or equal to 20 kg or 250 mL for patients weighing greater than 20 kg. The variety of vials needed is calculated by dividing the entire required dose in milliliters by 5 (the number of mL in a vial). Add the appropriate quantity of albumin and gently rotate the infusion bag to guarantee correct distribution of the albumin. Total Volume of Laronidase Infusion Volume of Albumin (Human) 5% to Be Added 2 mL 5 mL Volume of Albumin (Human) 25% to Be Added 0. Next, slowly withdraw the calculated volume of laronidase from the appropriate variety of vials (a total of 16 vials in the previous example) and slowly add it to the 0. Avoid all excessive agitation, as a end result of it may make the laronidase biologically inactive. Immediate use of the diluted solution is preferred but, if necessary, it might be refrigerated. No greater than 36 hours should elapse between preparation of the solution and completion of the infusion. For Patients Weighing More Than 20 kg Total Volume of Laronidase Infusion 5 250 mL 5 mL/hr three quarter-hour (10 mcg/kg/hr) 10 mL/hr three 15 minutes (20 mcg/kg/hr) 20 mL/hr 3 quarter-hour (50 mcg/kg/hr) 40 mL/hr three quarter-hour (100 mcg/kg/hr) 80 mL/hr 3 ~3 hours (200 mcg/kg/hr) Obtain vital indicators; if stable, then improve the rate to . Patients anaphylactic response happens, contemplate threat versus benefit before resuming therapy or contemplating further infusions. The most common infusion-related reactions embrace fever, flushing, headache, and rash. Abdominal ache, arthralgia, chills, cough, decreased oxygen saturation, diarrhea, dyspnea, hypertension, nausea, pruritus, urticaria, and vomiting have additionally occurred. Serious infusion-related hypersensitivity reactions have been reported and may embody anaphylaxis, angioedema, airway obstruction, bradycardia, bronchospasm, hypotension, hypoxia, respiratory misery or failure, stridor, and tachypnea. Other unwanted effects include injection site response or ache and higher respiratory tract an infection. Abscess, bilirubinemia, chest ache, corneal opacity, edema (dependent and facial), hyperreflexia, hypotension, paresthesia, thrombocytopenia, and vein disorders have been reported. If a gentle to moderate infusion or hypersensitivity reaction happens, scale back price or discontinue laronidase till symptoms subside. With additional premedication and/or a reduction in price of infusion, patients could possibly proceed treatment. Initiate between Day 0 and Day 28 posttransplantation (before or after engraftment) and proceed via Day one hundred posttransplantation. Available in single-dose vials containing 240 mg/12 mL or 480 mg/24 mL (both are 20 mg/mL). Primarily eliminated in feces (93%) as unchanged drug (70%) with minimal excretion in urine. Monitor: See Drug/Lab Interactions for specific monitoring requirements when letermovir is administered with other medication. Report the use of all prescription and nonprescription medications and herbal merchandise to a health care provider. Maternal/Child: Data on security for use in being pregnant not obtainable; benefit must justify potential dangers to fetus. The magnitude of letermovir drug interactions on coadministered medication could additionally be different when letermovir is coadministered with cyclosporine; see cyclosporine monograph. Antibiotics Nafcillin Concentration of letermovir decreased Anticoagulants Warfarin Concentration of warfarin decreased Anticonvulsants Carbamazepine Phenobarbital Phenytoin Concentration of letermovir decreased Concentration of letermovir decreased Concentration of letermovir decreased Concentration of phenytoin decreased Concentration of all three agents elevated Coadministration not beneficial. Antidiabetic Agents Glyburide, repaglinide, rosiglitazone, others Monitor glucose concentrations incessantly. Contraindicated if letermovir is coadministered with cyclosporine due to vital increases of concentrations of pitavastatin and simvastatin and threat of myopathy or rhabdomyolysis. Refer to the prescribing information for different statins for specific statin dosing recommendations. Monitor cyclosporine complete blood concentrations incessantly during therapy and after discontinuation of letermovir, and modify dose of cyclosporine accordingly. Monitor sirolimus entire blood concentrations regularly during remedy and after discontinuation of letermovir, and adjust dose of sirolimus accordingly. If letermovir is coadministered with cyclosporine and sirolimus, check with the sirolimus prescribing info for particular sirolimus dosing recommendations. A hypersensitivity reaction with related reasonable dyspnea occurred in one topic after the primary infusion of letermovir, leading to discontinuation. Monitor drug/drug interactions intently for threat of increased unwanted effects or reduced therapeutic effect. Repeat at 4-week intervals twice, then repeat every 28 to 35 days based on full recovery from toxic effects. Each 50-mg, 100-mg, or 350-mg vial ought to be diluted to a 10 mg/mL to 20 mg/mL answer. For whole doses less than 10 mg/M2, dilute with bacteriostatic water for injection (contains benzyl alcohol as a preservative). Storage: If prepared without a preservative, use immediately; steady up to 7 days with a preservative. Potent agent for neutralizing immediate toxic effects of methotrexate (and other folic acid antagonists) on the hematopoietic system. Preferentially rescues normal cells without reversing the oncolytic effect of methotrexate. Pernicious anemia and different megaloblastic anemias secondary to lack of vitamin B12. Elderly: Response just like that seen in younger sufferers; nonetheless, use caution; may have higher sensitivity to its poisonous effects. Methotrexate or fluorouracil might cause many severe and dose-limiting side effects; see particular person monographs. All indications: Monotherapy or adjunctive therapy: Initiate therapy with a daily dose of 1,000 mg/day, given as twice-daily dosing (500 mg twice daily). Dose could also be increased by 1,000 mg/day (500 mg twice daily) each 2 weeks to a maximum really helpful day by day dose of three,000 mg (1,500 mg twice daily). Myoclonic seizures in adults and adolescents 12 years of age and older with juvenile myoclonic epilepsy and primary generalized tonic-clonic seizures in adults sixteen years of age and older: the effectiveness of doses lower than 3,000 mg/day has not been adequately studied. Increase the every day dose each 2 weeks in increments of 14 mg/kg to the recommended day by day dose of forty two mg/kg (21 mg/kg twice daily). Increase the day by day dose every 2 weeks in increments of 20 mg/kg to the beneficial daily dose of fifty mg/kg (25 mg/kg twice daily). Increase the every day dose each 2 weeks in increments of 20 mg/kg to the recommended every day dose of 60 mg/kg (30 mg/kg twice daily). Primary generalized tonic-clonic seizures: 6 years to lower than sixteen years of age: Initiate treat- Myoclonic seizures in adolescents 12 years of age and older with juvenile myoclonic epilepsy: ment with a day by day dose of 20 mg/kg in 2 divided doses (10 mg/kg twice daily). The effectiveness of doses lower than 60 mg/kg/day has not been adequately studied. Levetiracetam Dose Adjustment in Adults With Impaired Renal Function Creatinine Clearance (mL/min/1. Pediatric patients: A smaller volume of infusion solution could additionally be required as a end result of limitations around the whole every day fluid consumption of the affected person. For example, a 1-year-old, 10-kg child beginning remedy for treatment of partial-onset seizures would initiate therapy at 20 mg/kg/day 5 200 mg/day 5 one hundred mg twice daily. In a fluid-restricted patient, the answer quantity could probably be decreased to as little as 5. In animal research it inhibited burst firing without affecting regular neuronal excitability, which means that it could selectively stop hypersynchronization of epileptiform burst firing and propagation of seizure exercise in human complicated partial seizures. Somnolence and fatigue and coordination difficulties occurred most frequently inside the first four weeks of treatment and resolved or improved with dose discount or discontinuation of levetiracetam. Median time to onset is 14 to 17 days, but improvement up to 4 months after initiation of remedy has been reported. If withdrawal is required due to a serious antagonistic reaction, rapid discontinuation can be considered.
Specifications/Details
In addition to the above allergy zinc purchase prednisone 20 mg without a prescription, immune-mediated encephalitis allergy bomb buy 20 mg prednisone with amex, nephritis allergy medicine good for high blood pressure prednisone 10 mg online buy cheap, pneumonitis allergy testing emedicine purchase 5 mg prednisone with amex, and renal dysfunction have been reported with single ipilimumab dosing and with combination dosing with nivolumab. Most, however not all, patients experienced partial or full decision of reactions following therapy; see Antidote. If it happens, contemplate repeating an infectious workup to exclude various etiologies. In symptomatic sufferers, rule out infectious etiologies and think about endoscopic evaluation for persistent or extreme signs. In sufferers with hepatotoxicity, rule out infectious or malignant causes and improve the frequency of liver perform check monitoring till resolution of symptoms. Unless an alternate etiology has been recognized, S/S of dermatitis ought to be thought-about immune mediated. Patients might present with fatigue, headache, mental status changes, abdominal pain, uncommon bowel habits, and hypotension. Unless an alternate etiology has been recognized, S/S of endocrinopathies ought to be considered immune mediated. Patient Education: Review Medication Guide earlier than every dose and promptly report any side effects noted on this guide. Use efficient contraception during remedy with ipilimumab and for three months after the last dose of ipilimumab. Women who turn into pregnant throughout ipilimumab treatment are inspired to enroll in a Pregnancy Safety Surveillance Study. The effects of ipilimumab are likely to be greater during the second and third trimesters of pregnancy. Use during pregnancy only if the potential profit justifies the potential danger to the fetus. In this age-group, exposure at a dose of 1 mg/kg or three mg/kg in pediatric and adult populations is comparable. In addition to these reactions, decreased urge for food, fever, headache, insomnia, nausea, vomiting, and weight reduction had been generally reported with the 10 mg/ kg dose. Severe to fatal immune-mediated reactions include dermatitis, endocrinopathy (adrenal insufficiency, hyperthyroidism, hypopituitarism, main hypothyroidism), enterocolitis (including intestinal perforation), eosinophilia, hepatotoxicity, meningitis, myocarditis, nephritis, neuropathy, pericarditis, pneumonitis, and uveitis. Other reported side effects include acute respiratory distress syndrome, encephalitis, esophagitis, listening to loss, infusion reaction, intestinal ulcer, myositis, ocular myositis, polymyositis, renal failure, sarcoidosis, and urticaria. Ipilimumab in combination with nivolumab: the most typical unwanted effects are stomach pain, arthralgia, cough, decreased appetite, diarrhea, dyspnea, fatigue, fever, musculoskeletal ache, nausea, pruritus, rash, and vomiting. Severe unwanted side effects had been much like ipilimumab as a single agent but in addition included type 1 diabetes mellitus (immune-mediated endocrinopathy) and immune-mediated encephalitis. Additional side effects embrace anemia, constipation, edema, hyperkalemia, hypocalcemia, hypomagnesemia, and lymphopenia. Permanently discontinue ipilimumab and provoke systemic high-dose corticosteroid remedy. With improvement to Grade 1 or less, initiate corticosteroid taper and continue to taper over a minimum of 1 month. Withhold ipilimumab dosing for reasonable enterocolitis; administer antidiarrheal remedy. Addition of another immunosuppressive agent to the corticosteroid remedy or substitute of the corticosteroid therapy ought to be thought of in corticosteroid-refractory immune-mediated colitis (if other causes are excluded). Mycophenolate (CellCept) may be thought of in patients with persistent, extreme hepatitis regardless of high-dose corticosteroids. Withhold ipilimumab dosing in sufferers with average hepatotoxicity, dermatitis, or neuropathy (neuropathy not interfering with every day activities). For delicate to reasonable dermatitis, similar to localized rash and pruritus, treat symptomatically. Administer topical or systemic steroids if no enchancment of symptoms inside 1 week. Withhold dosing in patients with symptomatic endocrinopathies and consider referral to an endocrinologist. Initiate systemic corticosteroids at a dose of 1 to 2 mg/kg/day of prednisone or equivalent, and provoke applicable hormone alternative remedy. Administer corticosteroid eye drops to sufferers who develop uveitis, iritis, or episcleritis. If uveitis happens in combination with different immunemediated opposed reactions, consider a Vogt-Koyanagi-Harada�like syndrome. Treatment with systemic steroids to cut back the chance of everlasting vision loss may be required. Withhold ipilimumab dosing for moderate to extreme S/S of pneumonitis, and administer corticosteroids at a dose of 1 to 2 mg/kg/day prednisone equivalents for reasonable (Grade 2) or extra extreme (Grade 3 or 4) pneumonitis, followed by corticosteroid taper. Withhold ipilimumab dosing in sufferers with moderate to extreme S/S of immune-mediated nephritis. If worsening or no enchancment occurs, increase dose of corticosteroids to 1 to 2 mg/kg/day prednisone equivalents. Permanently discontinue for life-threatening (Grade 4) elevated serum creatinine. Withhold ipilimumab in sufferers with new-onset moderate to extreme neurologic S/S and evaluate to rule out infections or other causes of reasonable to extreme neurologic deterioration. If different etiologies are ruled out, administer corticosteroids at 1 to 2 mg/kg/day prednisone equivalents for patients with immune-mediated encephalitis, followed by corticosteroid taper. Anticholinergic premedication: In addition, prophylactic or therapeutic atropine may be indicated in sufferers experiencing cholinergic symptoms. First-line therapy of colorectal cancer: Premedication as described above is recommended. Follow instantly with the dose of leucovorin calcium (see leucovorin calcium monograph). Follow the leucovorin instantly with the dose of fluorouracil (see fluorouracil monograph). Doses and modified dosing suggestions are outlined in the chart Combination-Agent Dosage Regimens and Dose Modifications. After adequate restoration, extra doses could additionally be repeated in an analogous cycle and continued indefinitely in patients who attain a response or in these whose disease remains stable. Subsequent doses could also be adjusted as little as 200 mg/M2 in 50 mg/M2 decrements depending upon individual affected person tolerance. Available data insufficient to recommend a dose for patients with bilirubin larger than 2 mg/dL. Subsequent dose modification should be based on individual affected person tolerance as outlined within the following charts. Heterozygous sufferers (patients who carry one variant allele) seem to tolerate normal beginning doses. Combination remedy: Decrease dose based on toxicity as described within the following chart. A new cycle of therapy also wants to not begin till the granulocyte count has recovered to $1,500/mm3 and the platelet count has recovered to $100,000/mm3. Treatment must be delayed 1 to 2 weeks to enable for recovery from treatment-related toxicities. If the affected person has not recovered after a 2-week delay, consideration ought to be given to discontinuing remedy. Delay dose till resolved to baseline, then give similar dose Omit dose until resolved to baseline, then (1 dose stage Omit dose till resolved to baseline, then (1 dose level Omit dose until resolved to baseline, then (2 dose ranges Maintain dose stage Maintain dose degree (1 dose degree (2 dose ranges Diarrhea 1 (2-3 stools/day. The most common causes for dose discount are late diarrhea, neutropenia, and leukopenia. If the patient has not recovered after a 2-week delay, consideration must be given to discontinuing irinotecan. Maintain dose stage (25 mg/M2 Omit dose till resolved to #Grade 2, then (25 mg/M2 Omit dose till resolved to #Grade 2, then (50 mg/M2 Maintain dose stage Maintain dose level (25 mg/M2 (50 mg/M2 Maintain dose degree Maintain dose stage (50 mg/M2 (50 mg/M2 Diarrhea 1 (2-3 stools/day. Conventional Irinotecan: Available in single-dose vials in 2-mL, 5-mL, and 15-mL sizes with a concentration of 20 mg/mL. Storage: Conventional irinotecan: Packaged in a blister pack to defend in opposition to unintentional breakage and leakage. However, if reconstitution and dilution are carried out beneath strict aseptic circumstances.
Syndromes
- Rapid heartbeat
- Size
- Extreme tiredness (lethargy)
- Problems with normal sexual intercourse
- For the 2-week period before surgery, you may be asked to stop taking medicines that make it harder for your blood to clot. These might cause increased bleeding during the surgery. Some of these medicines include aspirin, ibuprofen (Advil, Motrin), and naproxen (Aleve, Naprosyn).
- Runny nose
- Special enzymes to replace enzymes from the pancreas
- Hydralazine
Related Products
Additional information:
Usage: q.2h.
Tags: generic prednisone 10 mg mastercard, 10 mg prednisone generic fast delivery, order 10 mg prednisone free shipping, order 10 mg prednisone mastercard, generic prednisone 40 mg with amex, generic 20 mg prednisone free shipping, prednisone 5 mg order mastercard, 5 mg prednisone cheap with visa, generic prednisone 20 mg, prednisone 20 mg buy cheap on-line, buy generic prednisone 5 mg line, prednisone 20 mg buy otc, prednisone 40 mg buy mastercard, purchase prednisone 40 mg with mastercard, prednisone 20 mg order online, 40 mg prednisone discount overnight delivery
9 of 10
Votes: 222 votes
Total customer reviews: 222
Customer Reviews
Josh, 33 years: Major: Respiratory despair, seizures, ventricular ectopic rhythms, sudden dying. The most common unwanted facet effects noticed had been arthralgia, headache, hypotension, nausea, and vomiting. Amino acid formulations developed specifically for dietary assist of infants and other pediatric sufferers can be found.
Randall, 22 years: Use options containing potassium with warning in sufferers with cardiac illness, particularly within the presence of renal illness. Should a sudden or uncontrolled hypertensive state happen, discontinue levarterenol, notify the doctor, and if necessary, treat with an adrenergic blocking agent. Withhold or delay dosing till neutrophil depend is at or above Copyright � 2021 by Elsevier Inc.
Inog, 54 years: Therefore, there may be collateral injury to retinal structures following photoactivation. Follow with cisplatin 75 mg/M2 (one source suggests an infusion over 24 hours; another suggests 6 to 8 hours, which would allow for outpatient therapy). The most typical antagonistic reactions seen with olaratumab plus doxorubicin are belly pain, alopecia, decreased appetite, diarrhea, fatigue, headache, mucositis, musculoskeletal ache, nausea, neuropathy, and vomiting.
Gorok, 49 years: Rhinoscleroma impacts the nasal cavity and nasopharynx, and there are three distinct clinical phases. Tumors typically utterly replace the thyroid parenchyma and show extensive invasion beyond the thyroid gland into the perithyroidal tissues; thus all are stage pT4 by definition. Norepinephrine (Levarterenol), calcium chloride, or dopamine will reverse hypotension.