
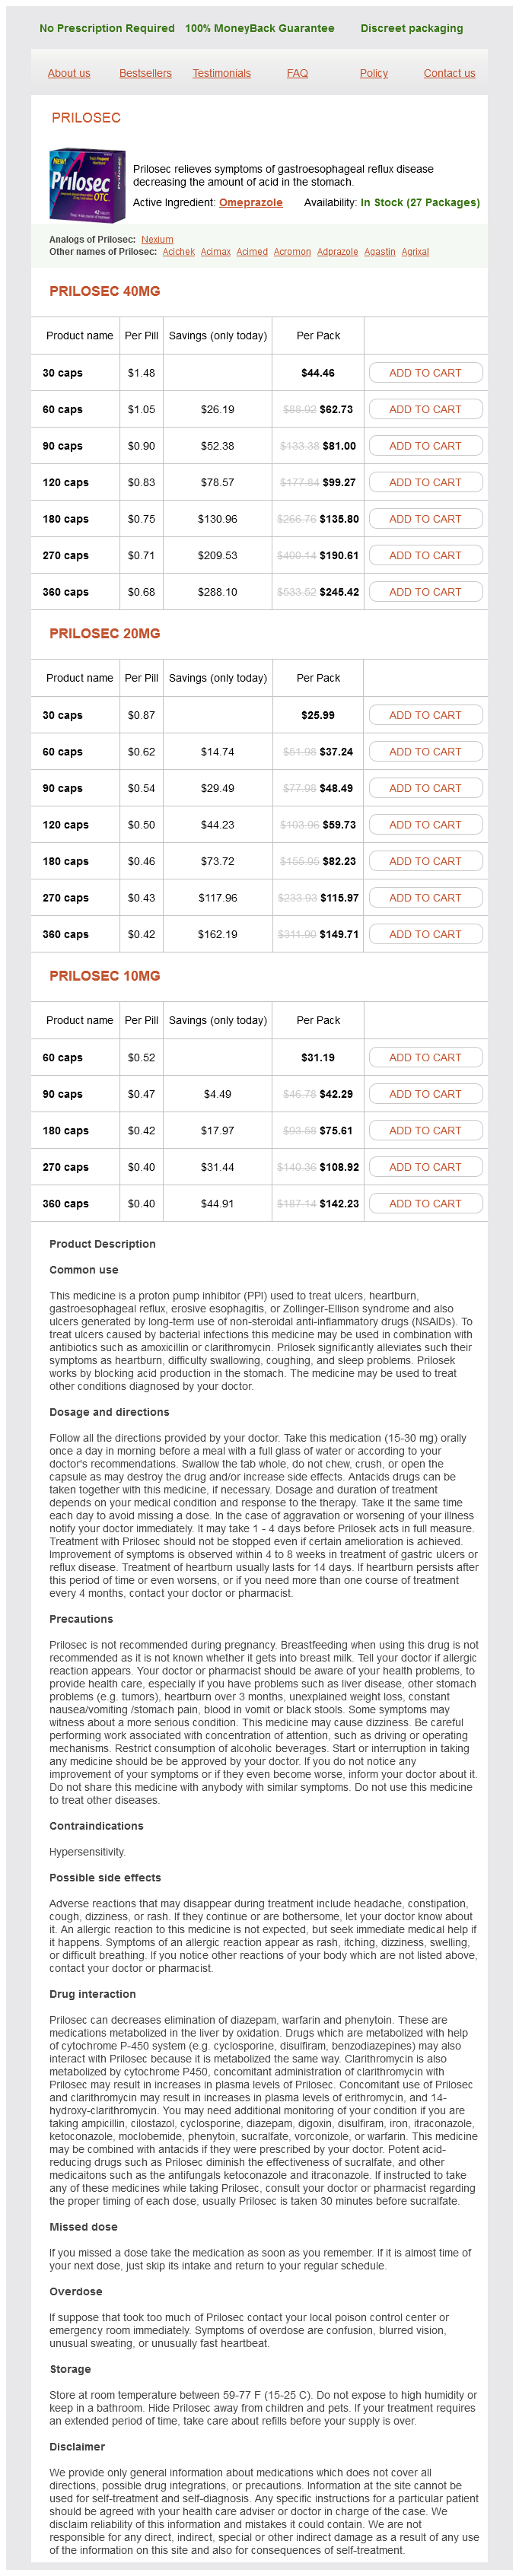
Prilosec
Prilosec 40mg
- 30 caps - $44.46
- 60 caps - $62.73
- 90 caps - $81.00
- 120 caps - $99.27
- 180 caps - $135.80
- 270 caps - $190.61
- 360 caps - $245.42
Prilosec 20mg
- 30 caps - $25.99
- 60 caps - $37.24
- 90 caps - $48.49
- 120 caps - $59.73
- 180 caps - $82.23
- 270 caps - $115.97
- 360 caps - $149.71
Prilosec 10mg
- 60 caps - $31.19
- 90 caps - $42.29
- 180 caps - $75.61
- 270 caps - $108.92
- 360 caps - $142.23
Prilosec dosages: 40 mg, 20 mg, 10 mg
Prilosec packs: 30 caps, 60 caps, 90 caps, 120 caps, 180 caps, 270 caps, 360 caps
In stock: 515
Only $0,42 per item
Description
The sympathetic system governs power needs of the physique; its exercise is evoked each time the request for oxygen increases healing gastritis with diet prilosec 40 mg generic, from physical activity to pathological circumstances gastritis water 10 mg prilosec with mastercard, and in case of annoying events or emergency gastritis dietz buy 20 mg prilosec with amex. The sympathetic stimulation primarily evokes the constriction of blood vessels (with consequent increase in blood pressure) and the increase in heart price and myocardial contractility gastritis diet bananas best 40 mg prilosec. Conversely, the parasympathetic system is most lively under restful situations, and it counteracts the sympathetic system after a stressful event for restoring the body to a restful state. Parasympathetic stimulation decreases the guts rate and causes blood vessel dilation. The parasympathetic nervous system the parasympathetic nervous system acts like the opposite of an emergency system. Increased exercise of this method is related to "vegetative" behaviors, similar to sleeping and digesting. Most of the nerves of the parasympathetic nervous system come from the mind stem and a few from sacral spinal cord. Acetylcholine is the chemical messenger launched from each the preganglionic and the postganglionic parasympathetic fibers. Acetylcholine binds to nicotinic receptors on the cell our bodies of the postganglionic nerves, whereas receptors within the goal organs are muscarinic. Stimulation of the vagus nerve will increase smooth muscle tone and secretion of abdomen acid and digestive hormones. Sympathetic element Cardiac sympathetic preganglionic fibers, sometimes all myelinated, emerge from the upper thoracic segments of the spinal twine (T1eT4). After traveling a short distance, they enter the sympathetic ganglia, located at the aspect of the vertebral column. Therefore, the efferent pathway of the sympathetic nervous system is the following. An electrical sign leaves the central nervous system on the spinal wire and runs quick through myelinated preganglion fibers to the paravertebral ganglia, figuring out the secretion of acetylcholine, on the synapse level. Then, from the ganglia, an electrical signal through the postganglionic fibers reaches the target tissues Baseline autonomic traits Chapter 14 169 of the cardiovascular system (heart and vessels), the place it causes the final release of catecholamines (norepinephrine or adrenaline). The specific effect of the sympathetic stimulation depends upon the chemical interaction between the transmitter and the receptors current on the target tissues. Into a goal tissue, the neurotransmitter might meet various sorts of receptors characterized by the potential of generating specific actions; for instance, in the vascular smooth muscle cells, there are a-receptors that evoke vasoconstrictions, while b-receptors evoke vasodilation (Table 14. The web response to agonists that, like adrenaline, stimulate both forms of receptors relies upon upon the relative significance of each receptor inhabitants [1,7,11e17]. In the cardiovascular system, the b1-receptors are mainly within the sinus atrial node, in atrioventricular node, and in each on atrial and ventricular myocytes. The activation of b1-receptors increases heart fee (via the sinus atrial node and atrioventricular node conduction) and myocardial contractility (as result of elevated intracellular calcium concentrations) [12]. The b2-adrenergic receptors are in a smooth muscle cell of peripheral and coronary circulation. Their activation causes vasodilatation, which, in flip, will increase blood perfusion particularly in the heart and skeletal muscle. In the cardiovascular system, a1- and a2-receptors are primarily in clean muscle cell of vessel wall [12]. Norepinephrine is also an agonist at b1-adrenoceptors, but, in contrast to adrenaline (which stimulates all kind of adrenoceptors), norepinephrine is a comparatively poor agonist at b2-receptors [12]. The concentration of adrenoceptors within the blood vessels varies from vascular bed to vascular bed, and the vascular tone results from the simultaneous activation of receptors that are differentially influenced in the completely different vascular areas by the transmitters popping out from the sympathetic nerve endings. The receptors, the activation of which more importantly contributes to the basal vascular tone, are these which are "innervated": the a1-adrenoceptors within the arterial vessels, the a1- and b1-adrenoceptors within the heart, and a2- and b2-adrenoceptors in the veins [12]. Sympathoadrenal system Some preganglionic fibers of the sympathetic nervous system finish immediately within the adrenal medulla. Additionally, activation of this receptor additionally induces renin release, which contributes to the ultimate blood stress, in addition to plasma sodium levels and blood quantity. There is proof that neurohormonal regulation performs a critical function in the pathogenesis and development of several cardiovascular ailments [19]. Therefore, opposing the impact of elevated adrenergic and/or angiotensin, renineangiotensinealdosterone signaling is the primary objective of several treatment strategies [20e23]. This occurs by two mechanisms: firstly, immediately, via preganglionic fibers that attain the parasympathetic ganglia placed into the myocardium and the vagal stimulation inhibits contraction of myocardial cells and secondly, indirectly by occupying acetylcholine receptors of sympathetic noradrenergic nerves within the myocardium [24e26]. The parasympathetic innervation originates predominantly in the nucleus ambiguus of the medulla oblongata. The efferent parasympathetic nerve fibers are carried to the center almost totally by the vagus (10th cranial) nerves. The pre- and postganglionic vagal fibers synapse in ganglia that lie on the epicardial surface or inside the cardiac tissue. Most of the vagal nerve fibers converge into a distinct fat pad positioned between the superior vena cava and the aorta on the pathway toward the sinus and atrioventricular nodes [27]. The sinoatrial and atrioventricular nodes and the atria are extra richly innervated by vagal fibers than are the ventricles and coronary vessels [24,25]. In addition, preganglionic fibers that travel in the right and left vagus nerves are distributed asymmetrically to the various buildings in the coronary heart. The proper vagus nerve has somewhat larger influence on the sinoatrial node than does the left vagus nerve, whereas the left vagus nerve has higher impact on the atrioventricular conduction system. In fact, proper vagus nerve stimulation tends to produce more sinus bradycardia, whereas the left vagus nerve stimulation tends to produce more atrioventricular nodal block [28,29]. The predominant neurotransmitter of the pre- and postganglionic vagus nerve terminals is acetylcholine. The main kind of cholinergic receptor on the membrane of cardiac effector cells is muscarinic. Therefore, nicotine-blocking brokers (such as hexamethonium) and muscarinic-blocking agents (such as atropine) can suppress parasympathetic transmission from the pre- to postganglionic neuron and from postganglionic fibers to the cardiac effector cells, respectively [24e26]. The biggest concentration of vagal fibers within the coronary heart is within the sinus node [31e34]. The sympathetic results are mediated primarily via stimulation of b-receptors [31e34]. However, over a quantity of stimulation frequency ranges, the chronotropic response acts paradoxically, and the cardiac cycle length decreases because the frequency of stimulation rises [35]. The principal influence of vagal activity on atrioventricular nodal conducting fibers is to hyperpolarize the cell membrane and to reduce the action potential upstroke velocity [36e38]. Therefore, vagal activity diminishes the velocity of impulse propagation via the atrioventricular node and prolongs the refractory interval of atrioventricular node fibers [24,36e38]. The medical penalties are, on one aspect, that intense vagal activity could induce even second- or third-degree atrioventricular block and, on the other facet, that rising vagal activity might interrupt episodes of reentrant tachycardia that embody the atrioventricular node within the reentry loop. Vagal exercise profoundly inhibits atrial contraction [24,25,39e43], and thus, it could attenuate the atrial contribution to ventricular filling [44]. There is evidence that even a single vagus stimulus can diminish atrial contraction by more than 50%, and a couple of or 3 stimuli in fast succession can cut back contraction by virtually 100 percent [41]. Because of nonhomogeneous vagal innervation to the atrium [45,46], intense vagal stimulation can produce dispersion of atrial refractoriness and, consequently, induction of atrial fibrillation [47,48]. The left ventricle is predominantly innervated by the leftsided sympathetic fibers. The first proof got here only in 1965, from research performed on dogs placed on complete heart bypass, so that there was whole control of heart price, preload, afterload, coronary perfusion strain, oxygen partial stress, and different variables that could have influenced the interpretation of the response to vagal stimulation [49]. When the center beats spontaneously, Baseline autonomic traits Chapter 14 171 the adjustments in ventricle contractility paralleled the modifications in heart rate, whereas when the center rate was artificially saved constant, the discount in ventricular contractility related on to the frequencies of vagal stimulation [49]. Vagal stimulation shifts ventricular operate in the instructions that denote depressed contractility [24,25]. There are data in maintaining with a special distribution of sympathetic and vagal fibers in the ventricular wall [50]. Specifically, sympathetic nerves traverse the ventricle in the subepicardium, sending branches deeply to the subendocardium. On the contrary, vagal nerves quickly after the atrioventricular groove penetrate from the subepicardium into the ventricular wall, from there dividing into a quantity of minor branches. Differences in innervation patterns between sympathetic and parasympathetic fibers are important in understanding mechanisms of arrhythmias following myocardial infarction [51e53]. Studies in people have advised that vagal exercise is decreased and sympathetic activity is enhanced following myocardial infarction and that this altered autonomic steadiness might partially modulate the incidence of sudden death and poor consequence following acute myocardial infarction [54e58]. The completely different spatial distribution could most likely account additionally for the difference within the sympathovagal steadiness between patients with spontaneous versus balloon-induced coronary occlusion; the former being characterised by elevated sympathetic exercise and the latter by enhanced parasympathetic activity [59].
Myrica heterophylla (Bayberry). Prilosec.
- What is Bayberry?
- How does Bayberry work?
- Colds, diarrhea, fevers, and nausea.
- Dosing considerations for Bayberry.
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96199
The sex variations within the autonomic responses to postural provocations have just lately been reported in a examine of a relatively large inhabitants of wholesome subjects of each sexes [14] diffuse gastritis definition prilosec 20 mg with amex. This article recapitulates that examine while also showing that the previously reported results are closely reproducible in different datasets gastritis fasting diet prilosec 10 mg buy discount. Body heights and weights of the subjects have been measured at screening of the source research chronic gastritis h pylori cheap prilosec 10 mg overnight delivery. Body mass index was calculated as w/h2 where w is the physique weight in kilograms and h is the physique peak in meters gastritis symptoms in puppies prilosec 40 mg without a prescription. The analysis of the first research investigated data of 175 and 176 wholesome females and males, aged 32. The second study was smaller and analytical knowledge were out there from 18 to 22 healthy females and males, aged 31. Postural provocations the postural provocations have been slightly different in both research. Per protocol of the primary study, drug-free recordings have been obtained at four completely different days within a 25-day period. At each of nowadays, the topics followed two different procedures of postural provocations. During the first procedure (test 1), 10-min strict supine place was adopted by 10-min unsupported sitting place, followed by 15-min unsupported standing position, followed by 10-min strict supine position. During the second procedure (test 2), the standing and sitting positions were reversed, i. Postural position changes were made actively by the examine topics with the preprotocol instruction to achieve the new body position in no more than 20 s. Investigations Investigated populations the available knowledge originated from two medical pharmacology studies carried out in healthy topics. In both studies, repeated 12-lead day-time Holter recordings were made in all study topics whereas they were on no remedy. All subjects had a normal screening electrocardiogram and normal clinical investigation usual in medical pharmacology studies [15]. The authentic studies have been appropriately ethically permitted, and all participants gave written informed consent. In the first subpopulation, every of the drug-free recordings contained two separate provocative procedures consisting of 10-min supine position, adopted by 10-min sitting, 10-min standing, and ultimate 10-min supine position. In the opposite subpopulation, every of the drug-free recordings additionally contained two separate provocative exams consisting of 10-min supine, followed by 10-min standing, 10-min sitting, and ultimate 10-min supine place. On each drug-free recording days of each studies, the provocative exams have been carried out in the afternoon separated by roughly 1-h gap. They have been allowed to drink water and/or zero-caloric noncaffeinated drinks between the lunch and the first check and between the exams. Because of the sizes of the populations, statistical analysis concentrated totally on the data of the first study. Where appropriate, graphic shows show data means with dual-sided 95% confidence intervals derived assuming regular distribution. Corresponding measurements in females and males have been in contrast utilizing standard t-tests assuming different commonplace deviations. Dependencies of electrocardiographic measurements on age and on underlying heart price were studied by the use of linear regressions calculated along with 95% confidence interval bands. Heart price and heart rate variability information Continuous 12-lead Holter recordings with electrodes in MasoneLikar positions have been obtained during the drug-free days of both studies. For the needs of tracking heart rate modifications, coronary heart fee was measured in 10-s windows that had been moved via the continuous recordings in 5-s steps. This eliminated the transition intervals throughout which the center fee was unstable because of postural adjustments. During each checks, the guts rate will increase from initial supine to the terminal a half of the standing period had been considerably unexpectedly massive and reached, on average, roughly 30 beats per minute (bpm) in each sex groups. In the second smaller study, heart fee changes were investigated in the first and second recordings of each drugfree day individually. The prime panels present the guts charges measured in females (in red), the underside panels the heart rates measured males (in blue). The bold strains present the mean heart rates, whereas the coloured areas show the bands of � commonplace deviation of heart rates. The panels on the left correspond to the postural take a look at 1, the panels on the right to the postural test 2. The prime panels show the intrasubject coronary heart price adjustments measured in females (in red), the underside panels the intrasubject heart fee adjustments measured in males (in blue). The daring lines present the mean coronary heart price modifications, while the coloured areas show the bands of � commonplace deviation of heart price changes. The panels of the left present the rate modifications during the first exams of the baseline days, the panels on the proper the rate adjustments through the repeated second tests during the baseline days. The high part of the figure shows the guts fee changes in the course of the supine / sitting / standing / supine take a look at, the bottom a half of the figure exhibits the heart price modifications during the supine / standing / sitting / supine take a look at. Autonomic responses to postural provocations Chapter 15 181 this was triggered purely by the smaller size of the inhabitants. In this second examine, coronary heart rate will increase in males were visibly bigger than in females however, in precept, the results agreed well between the 2 studies. Covariates As with the cumulative distributions, covariates of the observations have been investigated in the first study. Supine / standing heart fee change grew to become lower with advancing age in each females (P <. Although the figure exhibits that the slopes in females were steeper than in males, the distinction was not statistically vital. Contrary to the heart price modifications, the slopes had been significantly steeper in females in comparison with males (P �. The corresponding slopes were additionally significantly completely different between females and males (P �. The outcomes of research 2 were equivalent albeit with bigger variability due to smaller inhabitants sizes. The figure summarizes knowledge of the primary study since the second research was too small for related distribution comparisons. Interpretation the information of the 2 studies present that in healthy middleaged subjects, postural change from supine to unsupported sitting results in averaged heart rate increases of approximately 10 bpm, while the change from supine to unsupported standing will increase coronary heart fee on average by approximately 30 bpm. The knowledge are imply � commonplace deviation and for each 5-min windows, P-value (p) of the comparison between female and male topics is proven. The 5-min home windows of the standing position are shown in sequence as they occurred during the exams. In each panel, the left and right elements correspond to the postural tests 1 and 2, respectively. The positions are listed beneath the panels (the order of the two standing positions corresponds to their sequence inside the tests, see the text for details). The colored dots show the means of the sex-specific subpopulation, the error bars present the 95% confidence intervals of the means. In every panel, the left and right components correspond to the postural exams supine / sitting / standing / supine and supine / standing / sitting / supine, respectively. In each panel, the purple and blue strains correspond to female and male topics, respectively. The pink and blue panels correspond to female and male subpopulations, respectively. Light and dark shaded areas spotlight the shifts between supine and sitting positions and between the sitting and standing positions, respectively. Note that the extent of dark shaded areas is analogous between the sex teams for coronary heart fee however not for quasi-normalized high frequency heart price variability parts. Undoubtedly, postural changes lead to modifications within the autonomic standing with shifts in path of sympathetic dominance on standing. As already mentioned [14], sympathetic system of each human and other mammals is frequently characterised as answerable for "battle or flight" reactions whereas the vagal system has mainly calming function responsible for organism recuperation during relaxation [21]. Such sex-specific conduct is relevant for the protection of the social group and for offspring preservation. The feminine "tend-and-befriend" reactions have also been described as persistent maternal characteristics unrelated to mental stress [24]. The panels present the changes comparable to the positional modifications from supine to standing. The knowledge introduced are the changes of intrasubject averages of both postural checks; the info of the standing positions are taken from the final 5-min measurements.
Specifications/Details
Chapter fifty five Ventricular arrhythmias associated with structural changes Ljuba Bacharova International Laser Center gastritis flu like symptoms 10 mg prilosec cheap mastercard, Bratislava gastritis diet 600 prilosec 20 mg buy generic line, Slovak Republic Introduction Ventricular arrhythmias represent a group of scientific circumstances with irregular heart beat originated within the ventricles gastritis pediatric symptoms prilosec 40 mg buy cheap line. Arrhythmogenic substrate is a term comprising complicated changes in myocardium affecting energetic and passive electrical properties of myocardium and creating circumstances for triggering and sustaining arrhythmias gastritis from ibuprofen purchase prilosec 20 mg free shipping. Clinical and fundamental science research have shown important intercourse differences in cardiac structure and electrical characteristics that would consequently have an effect on the incidence of ventricular arrhythmias. These differences have been observed beneath physiological in addition to underneath pathological circumstances. The intercourse differences in structural remodeling interrelated with electrical reworking in cardiac pathology may be observed from the organ stage to tissue and mobile levels, ion channels and gene expressions, clinically. This article evaluations structural modifications of myocardium in the most common cardiac pathologies leading to ventricular arrhythmias with the concentrate on the sex differences from feminine perspective. Since the size of the right and left ventricles are smaller, consequently the end-diastolic and stroke volumes are smaller [10,11]. During the fertile interval, the sex variations in electrophysiological characteristic may be further modified by menstrual cycle. In the ovulation interval, the center price significantly increased as in comparability with menstruation interval, and the J-T peak is shorter [19]. It could be speculated that differences in myocardial repolarization modulated by intercourse hormones can contribute to the differential presentation of arrhythmias in men and women [20]. Women are much less vulnerable to arrhythmias throughout pregnancy [22], however the incidence of arrhythmias can enhance in ladies with preexisting heart disease or who had ventricular tachycardia before pregnancy [3,23,24]. Summarizing, sex-specific differences in anatomy, construction, and electrophysiology modulated by hormonal status are present already underneath physiological conditions and might interplay with pathological processes. Ventricular premature complexes the most common ventricular arrhythmia is ventricular premature complexesdectopic impulses originating from an area distal to the HisePurkinje system. During being pregnant, the variety of ventricular untimely beats can increase, but is benign in most patients [31]. Three primary mechanisms are involved in pathophysiology of life-threatening ventricular arrhythmias: increased automaticity, reentry, and triggered activity. Reentry is the mechanism underlying most ventricular arrhythmias related to structural changes, in combination with functional alteration of electrogenesis and electrophysiological heterogeneity. Women differ in the presence of conditions that may result in structural changes of ventricular myocardium. Women are more doubtless to be obese and have greater prevalence of the category 3 weight problems [42]. Coronary artery illness Coronary artery illness is probably the most frequent reason for ventricular arrhythmias and sudden cardiac demise [1,5]. The substrate for arrhythmia is created by the heterogeneity of the myocardial tissue. Advanced imaging strategies allow the assessment of structural adjustments in coronary artery disease, such as fibrotic scars, edema, microvascular obstructions, diffuse or regional fibrosis, and areas of necrosis with islands of viable cardiomyocytes particularly in the periphery of the infarcted space (periinfarct zones), leading to tissue heterogeneity. These regions create areas of altered activation propagation producing situations for the event of lethal reentrant arrhythmias [45e51]. Women develop coronary artery disease on average 7e10 years later compared to males [52], displaying a "female benefit" in the premenopausal ladies in contrast with age-matched males. On the opposite hand, women have a higher threat of torsade de pointes due to antiarrhythmic medicine [57]. Life-threatening arrhythmias the prevalence and incidence of the life-threatening ventricular arrhythmias and sudden cardiac demise are typically lower in girls than in males. It is related to higher coronary flow and higher endothelial shear stress [61]. Autopsy research showed that women have less in depth atherosclerotic burden in comparison with men [62e64]. It was found that girls have much less in depth coronary artery illness with fewer and more focal nonculprit lesions. Nonculprit lesions had significantly less plaque rupture, much less necrotic core, and dense calcium, fibrous, and fibrofatty tissue [65]. It has been advised that estrogen may retard plaque growth, stabilize present plaques, and stop their rupture in ladies [66]. It is possible that the useful alterations are related to structural adjustments not detectable with commonplace imaging strategies, similar to coronarography or echocardiography. Reduced blood provide leads to adjustments in the lively and passive electrical properties of the myocardium. The heterogeneity of electrophysiological properties together with structural modifications, such as fibrosis and irritation, create conditions for ventricular arrhythmias, for triggering impulse technology and initiating and sustaining reentry. Rest and stress relative uptake pictures, coronary move reserve, and coronary circulate capability map combining stress circulate (in mL/min/g) and coronary move reserve. However, contemplating the potential effect of coronary microvascular dysfunction, they are often reflections of the underlying processes affecting electrogenesis. The further factor contributing to sex variations is the interference with the effect of endogenous estrogen in premenopausal ladies and hormone substitute therapy in postmenopausal ladies [83e87]. Differences in coronary microvascular dysfunction might contribute to understanding these differences. Ectopic ventricular arrhythmias throughout train, defined as multiple ventricular untimely beats, ventricular bigeminy, nonsustained ventricular tachycardia, or sustained ventricular tachycardia, are extra frequent in obese subjects [93]. Obesity is related to a better danger of ventricular arrhythmias and sudden cardiac demise [94e96]. Women usually have a tendency to be obese and have larger prevalence of the class three obesity [90]; these findings distinction with the decrease occurrence of ventricular arrhythmias in girls compared to men. The fatty infiltration of myocardium impacts cardiomyocytes and interstitium, as nicely as the metabolism of the center. The proportion of the lively myocytes (the "free-fat mass") and adipose tissue is changed in favor of the adipose tissue [97]. The epicardial and pericardial adipose tissues play function in the secretion of adipokines and chemokines that can stimulate inflammation. It is related to the production of cytokines and chemokines that may affect electrical functions such because the presence of hole junctions [98]. Additional remote effect has the systemic secretion of adipokines, cytokines, and metabolites [99]. The effect of these factors is multiple, resulting in mitochondrial dysfunction, oxidative stress, autophagy, mitophagy, autonomic dysfunction, and cardiomyocyte death. Consequently, electrogenesis is altered and conditions for conduction block and aberrant electrical alerts are created. The ratio of fat-free myocardial mass and adipose mass differs between obese ladies and men. Women have more frequent a relative deficiency of fat-free mass and extra of adipose mass ("sarcopenic weight problems") [100,101]. It was advised that this distinction would possibly replicate differences in electrogenesis in obese ladies in preand postmenopausal durations. Obesity is incessantly related to other scientific circumstances, such as diabetes mellitus, metabolic syndrome, hypertension, and sleep apnea [97]. Associated comorbidities and resulting underlying processes can contribute to the elevated incidence of arrhythmias after menopause. In any of these measures, the normal values are intercourse specific, and the higher normal limits for girls are lower. At the tissue degree, the hypertrophic rebuilding of myocardium affects each cardiomyocytes and interstitium. As was proven in numerous research on people and animals, particular person cardiomyocytes are enlarged in diameter and length and contain elevated number of branching and linked cardiomyocytes, affecting consequently the electric impulse propagation [115e117]. Animal experiments and clinical research have demonstrated that the conduction velocity of hypertrophied myocardium is changed [120e122]. These changes create a stable basis for modifications in electrical impulse technology and propagation. Additionally, the disproportion between the elevated myocardial mass and coronary artery supply causes the underperfusion of hypertrophied myocardium creating additional areas of ischemic tissue. The heterogeneity of these adjustments and the mutual interaction of the concerned factors could cause deviations from the traditional ordered sample of the electrical impulse propagation and create conditions for reentry. Given equal valve severity, left ventricular hypertrophy appears extra maladaptive in men.
Syndromes
- Slow, labored breathing
- Surgical removal of burned skin (skin debridement)
- Spine x-ray
- Diet deficiency
- Bed rest, lying on your left side most or all of the time
- Clouding of the cornea
- Hepatitis may produce nausea, vomiting, fatigue, or other symptoms
- Facial palsy (weakness, drooping)
Related Products
Additional information:
Usage: q.2h.
Tags: purchase prilosec 10 mg online, buy generic prilosec 10 mg, 20 mg prilosec purchase overnight delivery, prilosec 10 mg buy low cost, cheap 40 mg prilosec mastercard, 10 mg prilosec order with mastercard, discount prilosec 10 mg, purchase prilosec 10 mg with mastercard, cheap prilosec 20 mg mastercard, purchase 10 mg prilosec overnight delivery, 20 mg prilosec cheap amex, prilosec 40 mg buy with visa, prilosec 20 mg buy with visa, prilosec 40 mg purchase with mastercard, 20 mg prilosec cheap otc, buy prilosec 40 mg free shipping
9 of 10
Votes: 57 votes
Total customer reviews: 57
Customer Reviews
Achmed, 45 years: Irrigated radiofrequency catheter ablation guided by electroanatomic mapping for recurrent ventricular tachycardia after myocardial infarction: the multicenter thermocool ventricular tachycardia ablation trial.
Kelvin, 60 years: There are more questions than answers concerning the underlying cause for the increased mortality in ladies.
Yespas, 50 years: Dopamine D3 receptor antagonists as potential therapeutics for the therapy of neurological diseases.
Chris, 52 years: Comparison of cryoablation with 3D mapping versus standard mapping for the treatment of atrioventricular re-entrant tachycardia and right-sided paraseptal accessory pathways.
Porgan, 21 years: There is a decreased incidence of heart problems in premenopausal women compared with men of a similar age, with a sharp increase following the menopause [65].