
Pristiq
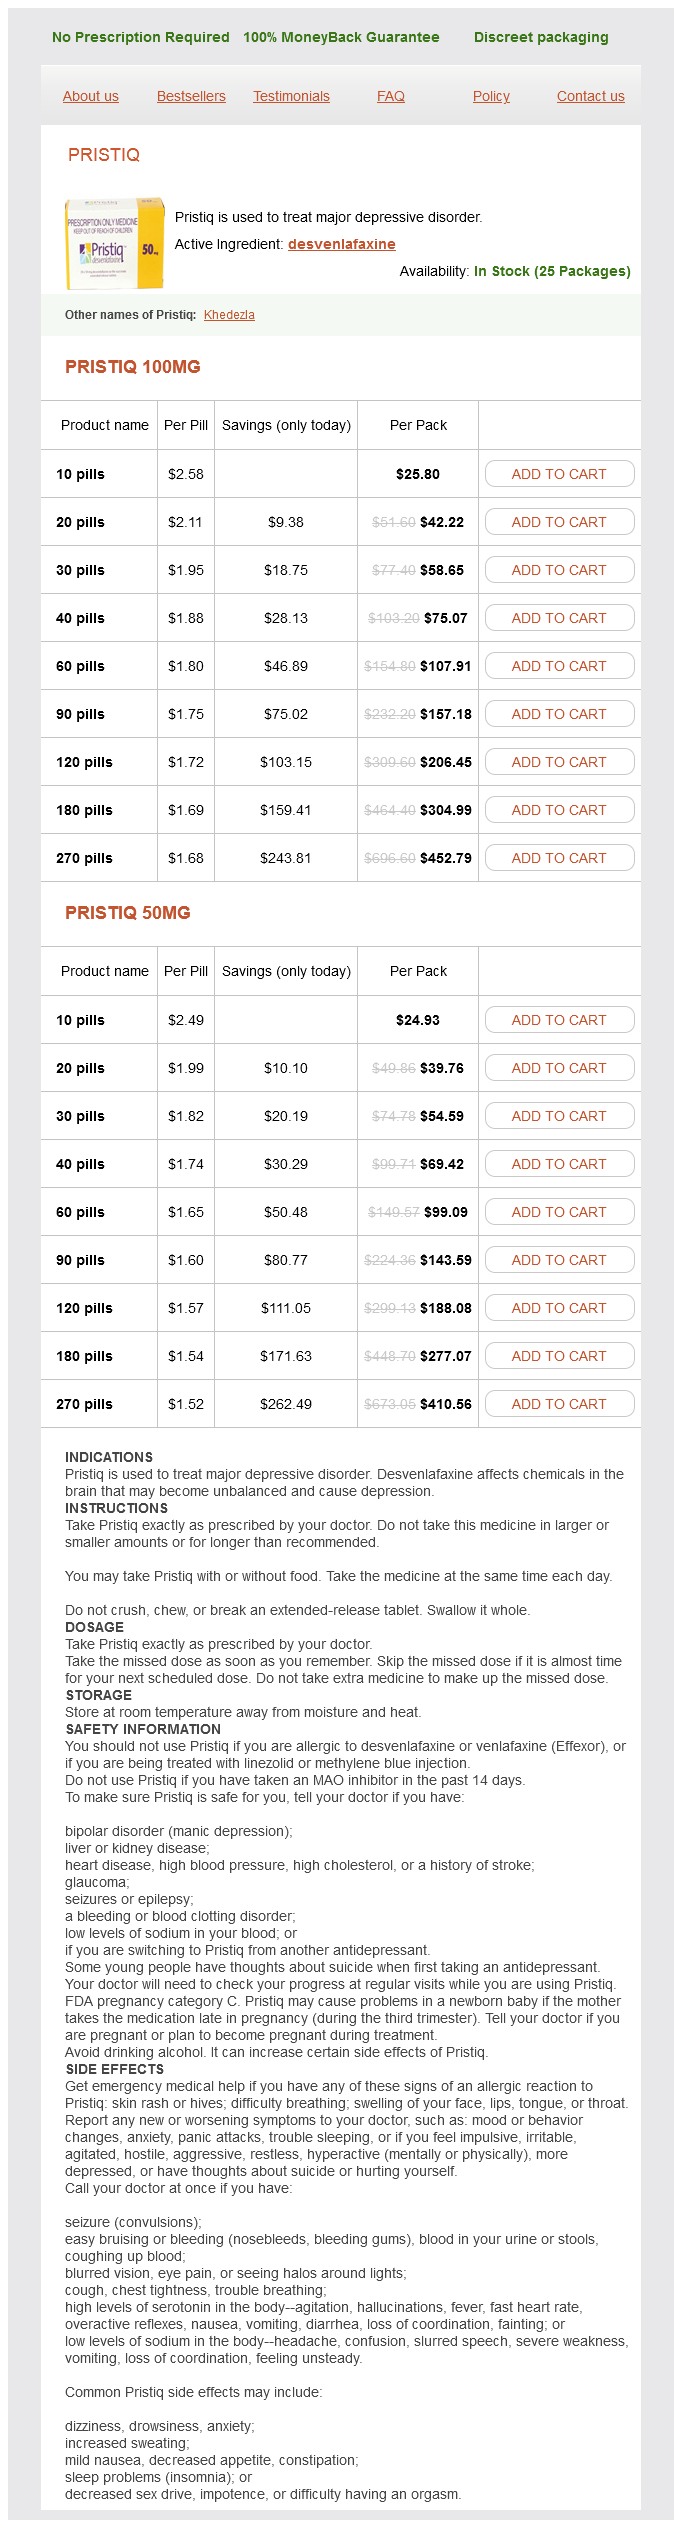
Pristiq 100mg
- 10 pills - $25.80
- 20 pills - $42.22
- 30 pills - $58.65
- 40 pills - $75.07
- 60 pills - $107.91
- 90 pills - $157.18
- 120 pills - $206.45
- 180 pills - $304.99
- 270 pills - $452.79
Pristiq 50mg
- 10 pills - $24.93
- 20 pills - $39.76
- 30 pills - $54.59
- 40 pills - $69.42
- 60 pills - $99.09
- 90 pills - $143.59
- 120 pills - $188.08
- 180 pills - $277.07
- 270 pills - $410.56
Pristiq dosages: 100 mg, 50 mg
Pristiq packs: 10 pills, 20 pills, 30 pills, 40 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills
In stock: 868
Only $1,62 per item
Description
A block-shaped defect will then be created within the adjoining vertebral our bodies for removing of sentimental and calcified disk materials away from the dura into the defect medicine in ancient egypt cheap pristiq 50 mg without prescription. Afterward, the rib head, which normally matches into the defect, is used for a monosegmental fusion process to be achieved by ventral instrumentation medicine cabinet shelves pristiq 50 mg cheap online. Technical and Operative Details A lateral fluoroscopic image is obtained to determine the extent of illness and the place of the 4 portals symptoms wisdom teeth cheap pristiq 50 mg line. After the approach has been made and all portals are put in the proper place, the spine is exposed by retraction of the lung with the fan-shaped retractor symptoms 1974 buy discount pristiq 100 mg online. However, the process consists of partial removal of the disk combined with a roughly prolonged bony defect on the adjacent vertebral bodies; distinct instability could be anticipated. After trap-door incision of the pleura over the identified disk space and the adjoining one, the segmental vessels of no less than the decrease adjacent vertebra are ready, ligated with clips, and transected. If mobilization of the aorta is required, the segmental vessels are ligated and dissected at multiple ranges. The capsular and ligamentous structures of the rib head are reduce with a Cobb elevator, and the rib head is mobilized. Following the course of the proximal rib, the pleura is opened over the rib, and the proximal 2 cm of the rib is resected. Partial corpectomy is carried out with a high-speed diamond bur or an osteotome, creating a well-defined, block-shaped central defect involving the higher and decrease thirds of the adjacent vertebral bodies. Once the base of the pedicle caudal to the intervertebral disk area is identified, the thickness can be lowered with a diamond bur to weaken the pedicle and to facilitate the transection with Kerrison rongeurs. Dickman12 recommends starting on the higher rim of the pedicle because of much less bleeding from the epidural venous plexus. Under direct endoscopic view of the dura, the posterior wall is then dissected off the dura and thoroughly pushed into the corpectomy website or thinned out with a high-speed diamond bur. Complete decompression of the dural sac across the vertebral physique to the extent of the contralateral pedicle is confirmed by direct endoscopic view and radiologically by fluoroscopy with use of a nerve hook in an anteroposterior projection. The corpectomy defect is reconstructed with the rib head harvested at step one. I routinely perform a monosegmental endoscopic anterior fixation with a constrained screw-plate system to achieve a strong bony fusion of the phase. The complication rate of the endoscopic procedure is of the same scale as that for open procedures, with clear advantages in terms of the decreased access morbidity related to the minimally invasive method. Development and scientific software of a thoracoscopic implantable body plate for the remedy of thoracolumbar fractures and instabilities. A minimally invasive approach to ventral administration of thoracolumbar fractures of the spine. Biomechanical compression tests with a new implant for thoracolumbar vertebral body substitute. Thoracic disc illness: experience with the transpedicular strategy in twenty consecutive patients. Present position of thoracoscopy within the prognosis and treatment of illnesses of the chest. Lateral extracavitary approach to the spine for thoracic disc herniation: report of 23 circumstances. Anterior decompression and stabilization using a microsurgical endoscopic approach for metastatic tumors of the thoracic backbone. Through the transdiaphragmatic strategy, it has been possible to open up the thoracolumbar junction, including the retroperitoneal segments of the backbone, by means of an endoscopic approach. With the extension of the approach to the retroperitoneal sections of the thoracolumbar junction, it grew to become attainable to increase the indication spectrum of the endoscopic approach considerably in order that it includes complete fracture therapy with vertebral body substitute and ventral instrumentation as properly as anterior decompression of the spinal canal in posttraumatic and degenera- Full references could be found on Expert Consult @ Sean Grady Skull defects and craniofacial bone abnormalities that require reconstruction are frequent in quite lots of neurosurgical procedures. Craniofacial reconstruction and cranioplasty have a protracted historical past, but new surgical techniques and a mess of material choices have just lately fueled advancement in this space. This chapter describes the clinical indications for cranioplasty, preoperative administration and timing of reconstruction, supplies, and operative strategies. When to perform cranioplasty inherently is decided by the nature and cause of the skull defect. One of the commonest indications for delayed cranioplasty is after hemicraniectomy for refractory intracranial hypertension. Before the autologous bone flap could additionally be changed, the overlying scalp should be nicely healed and vascularized, intracranial hypertension and neurological standing must be utterly stabilized, and infections (both systemic and cranial) have to be fully treated. Although cranioplasty is typically carried out approximately three months after traumatic mind damage, current reports point out that in choose, otherwise wholesome sufferers, early cranioplasty after 5 to 8 weeks may help restoration. Several stories point out that speaking hydrocephalus happens at a high incidence after decompressive hemicraniectomy. However, onlay synthetic dural substitutes, if used, may not have fashioned an adherence to the underlying native dura and can usually be inadvertently mirrored with the skin flap. Patients commonly exhibit hemispheric collapse on the facet of the calvarial defect, also recognized as syndrome of the trephined. Infection after cranial surgery is one other medical scenario during which the native bone generally should be discarded, and delayed cranioplasty is preferred. Several stories have indicated that cranioplasty may be averted after operative d�bridement of an contaminated bone flap. Conservative estimates have specified delay of reconstructive surgical procedure for six months to 1 12 months. Immediate cranioplasty is indicated after resection of bone neoplasm, corresponding to a meningioma, that has eroded via the skull. In the grownup population, use of artificial cranioplasty supplies corresponding to methyl methacrylate is preferred for giant skull defects (>10 cm) due to their ease of use for irregularly formed defects. For smaller defects, titanium mesh alone is enough to realize an excellent beauty result. In our follow, we defer cranioplasty if the patient has any energetic infection, including Clostridium difficile. In common, cranioplasty is an elective process and must be undertaken solely when these different medical issues have resolved. These bone flaps are normally either positioned into deep-freeze preservation or subcutaneously preserved in belly fat. Some stories point out that the preservation in subcutaneous tissue improves the bone viability, thereby reducing cranioplasty revision fee. B, Intraoperative photograph of autologous bone flap secured to native skull with plating system. The success and durability of the operation require cautious choice of a material tailored to the medical situation. The best materials is malleable, sterilizable, nonmagnetic, radiolucent, light-weight, and capable of be simply secured to present skull (Table 32-1). Although a multitude of different animal bones, metals, and even coconut shell have been utilized in cranioplasty, this discussion focuses on these materials used in modern neurosurgery. In an exothermic reaction, methyl methacrylate slowly cools from a paste-like substance into a translucent materials with power corresponding to that of native bone. Methyl methacrylate may be used for technically challenging areas of the skull, and reconstruction and development from the native bone edge adjoining to the prosthesis will safe it to the cranium. Disadvantages of methyl methacrylate embrace postoperative infection, at a fee of roughly 5% to 10%, and plate breakdown or fracture. Liquid methyl methacrylate could additionally be absorbed by tissues and has been reported to cause acute hypotension and hypersensitivity. It is a composite material of polymethyl methacrylate and barium sulfate, making a radiopaque bone cement. The mostly used calcium phosphate materials is hydroxyapatite, shown to be ideally suited to small craniofacial defects. Certain types of calcium phosphate prostheses, including hydroxyapatite, have the extra benefit of being osteoconductive, so it serves as scaffolding for development of recent bone. Titanium mesh, both alone or in combination with methyl methacrylate, is one other useful materials for cranioplasty. Several series have reported a low incidence of an infection whereas still attaining glorious cosmetic outcomes.
Smooth-Leaved Elm (Elm Bark). Pristiq.
- How does Elm Bark work?
- What is Elm Bark?
- Dosing considerations for Elm Bark.
- Digestive disorders, diarrhea, increasing urine production (diuretic), and wounds.
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96053
At epilepsy centers, as many as 20% to 30% of patients admitted with a prognosis of medically refractory seizures may actually have psychogenic nonepileptic seizures treatment 5th toe fracture 100 mg pristiq with mastercard. In many of those sufferers, invasive monitoring is critical for exact localization treatment wax discount pristiq 50 mg on-line. These photographs have proved helpful within the localization of extratemporal lobe epileptic foci (see Case Study 61-1) treatment yellow jacket sting pristiq 100 mg on line. This modality is used as a preoperative software to define the relationship of cortical functional anatomy and the epileptogenic zone treatment brachioradial pruritus discount 50 mg pristiq free shipping. It is beneficial in determining hemispheric language dominance and it correlates nicely with results obtained by the Wada check. Careful three-dimensional reconstructions of the cortical floor can reveal floor abnormalities related to developmental lesions. Interictally epileptogenic zones tend to be hypometabolic relative to regular cortex. When used in the ictal state and in contrast with the interictal state, it could show a significant seizure focus by which enhanced neuronal activity results in elevated blood circulate. Frontal lobe epilepsy patients with either preoperative or postoperative deficits have problem with mental flexibility, planning, and fluency (verbal fluency from the left frontal lobe and nonverbal fluency from the proper frontal lobe). Parietal lobe deficits are unusual except in sufferers with intensive parietal lesions. Distortion in copying a fancy figure representing distortion in conceptualization of spatial representation can be associated with parietal lobe lesions, proper more than left, and somatosensory tests generally show variations in these patients. Occipital lobe lesions may be manifested as visible field deficits, and if vital, they may intrude with cognitive visible tests. Establishing the aspect of language dominance is crucial, however, in planning frontal lobe and parietal lobe epilepsy surgery. To carry out evoked potential sensorimotor mapping, the median nerve on the hand is stimulated with a small electrical present, and somatosensory evoked potentials are recorded from the cortical surface over the suspected rolandic cortex. Phase reversal of the N20 median nerve somatosensory evoked potential from one strip electrode result in the subsequent defines the central sulcus, with the precentral motor space being anterior and the postcentral sensory area being posterior. An different methodology, which we frequently use, is asleep-awake-asleep anesthesia,277 by which the procedure is began with basic anesthesia and intubation to allow the routine neurosurgical craniotomy protocol, together with cranial fixation and image-guided surgical procedure. Only at the stage of the process when mapping is required is the patient allowed to emerge from basic anesthesia and subsequently extubated, with a small information left in place via the vocal cords. Electrical stimulation mapping or different affected person testing could be carried out throughout the resection if the resection is near functional processing zones. Intraoperative mapping may be especially important given the extensive variability within the location of language areas. To carry out electrocorticography, grid electrodes of assorted sizes and configurations or particular person electrodes are positioned instantly on the exposed cerebral cortex over suspected regions of epileptogenesis, and the electrical activity is recorded. General anesthesia can suppress spike frequency279; nonetheless, propofol sedation280 and dexmedetomidine sedation281,282 can be used during electrocorticography. Spike activity is usually taken as an indication of an epileptogenic zone, but sometimes extreme slowing of exercise can be thought-about. After tissue resection, electrocorticography could be carried out across the borders of the resection cavity to confirm the elimination of pathologic electrical exercise. For intraoperative language18 or sensory273 mapping, the affected person needs to be absolutely acutely aware and capable of cooperate. As mentioned earlier, extratemporal lobe epilepsy has a better prognosis for postoperative seizure control if a structural lesion may be recognized on imaging as the seizure focus. Preoperative functional scans, intraoperative mapping techniques, and subpial transections, when indicated, minimize the chance for neurological deficit that might outcome from resection in an area essential for a critical operate. With the appropriate instruments and careful multimodality evaluation at every stage, extratemporal lobe epilepsy surgical procedure provides an inexpensive chance of seizure management. Low-grade gliomas related to intractable epilepsy: seizure consequence utilizing electrocorticography during tumor resection. Management of low-grade gliomas: results of resections without electrocorticography. Delineating gray and white matter involvement in mind lesions: three-dimensional alignment of useful magnetic resonance and diffusion-tensor imaging. The added worth of magnetic source imaging in a big series of medically refractory partial epilepsy sufferers that are candidates for epilepsy surgery. Brain stimulation for the therapy of epilepsy: What is the evidence in people and animals [abstract 1W. Frameless stereotactic methods can information the surgeon on to the lesion and help decide the borders of the lesion based mostly on the imaging. Frameless stereotaxy has proved very useful in different epilepsy surgical procedures as well, together with corpus callosotomy129 and the location of intracranial electrodes. New Modalities in Development Novel intraoperative strategies are being developed that ought to show helpful in extratemporal lobe epilepsy surgery. This technology has undergone appreciable enchancment in being appropriate with the working room surroundings. With larger resections, particularly these involving a quantity of lobes, brain shift poses difficulties for traditional image-guided navigation. The key to successful extratemporal lobe epilepsy surgical procedure is use of the precise preoperative and intraoperative technologies available to outline a area where resection is important and sufficient to achieve seizure control with minimal neurological sequelae. Localization of a focal lesion responsible for the seizures is related to the most effective seizure control consequence if the entire lesion may be resected. Even if not resectable, a localized epilepsy focus might now be a candidate for one of many newer stimulation technologies. This procedure can also be used for different epileptic substrates (malformations of cortical improvement, cavernomas, neoplasms, and other focal epileptogenic lesions) involving the temporal lobe. By this time, Penfield and his companion William Cone had been performing surgical procedure for epilepsy since Penfield arrived in 1928. The second phase within the growth of the trendy surgical technique to deal with temporal lobe seizures happened in the 1950s as the position of the mesial temporal lobe constructions within the pathogenesis of the epilepsy became better understood. This occurred as a quantity of scientists started to check the connections of the mesial temporal lobe to the relaxation of the mind and through using stimulation studies to reproduce seizure semiology in animals and humans. Falconer in a report in 1953 recognized a reference to febrile seizures and introduced a modification permitting for en bloc resection of the hippocampus, which allowed the pathologists to check the tissue. Despite these modifications, the operation developed and introduced by innovative neurosurgeons within the early twentieth century remains one of the successful operations for the treatment of epilepsy today. The exact definition of an sufficient anticonvulsant trial is open to interpretation, but a research by Kwan and Brodie produced helpful data concerning the efficacy of anticonvulsant therapy in newly diagnosed epilepsy. Consider additionally the paper by Wiebe and associates, comparing temporal lobectomy to optimum medical remedy in a gaggle of patients with temporal lobe epilepsy. These papers lend credence to the concept sufferers with ongoing epilepsy despite a trial with a number of anticonvulsants ought to be expeditiously evaluated for attainable epilepsy surgery. Many clues to the potential etiology and the localization of the epileptogenic region could be elicited from the historical past. One must all the time carefully research the remainder of the temporal lobe as a end result of twin pathology happens in about 10% to 30% of mesial temporal sclerosis circumstances. It provides a wonderful overview of the approximate location and extent of the epileptogenic space. In addition, video recordings and analyses allow the characterization of the seizure semiology which may be helpful in the localization and lateralization of the ictal onset zone. The presence of postictal speech difficulties could assist in lateralizing the seizure onset zone to the dominant hemisphere for language. Neuropsychological data is essential as a result of the temporal lobes play a role in emotion, language, and reminiscence. Despite a few years of experience in temporal lobe surgery, our understanding of function and prediction of neuropsychological deficits is still somewhat poor. This is achieved with standardized neuropsychological testing, which is then repeated 6 months after surgery. This danger relies on baseline preoperative functioning and the person substrate of the epilepsy.
Specifications/Details
Porous polyethylene implants are composed of high-density polyethylene microspheres that create interconnected pores, permitting ingrowth of native bone medications safe during pregnancy pristiq 50 mg buy fast delivery. This distinctive implant structure rapidly incorporates fibrovascular tissue from the affected person and decreases the an infection fee of the implant treatment walking pneumonia 100 mg pristiq buy otc. Porous polyethylene implants may be formed to cowl a big number of skull defects and secured with titanium screws to native bone medicine vicodin 50 mg pristiq order with visa. The whole plastic sleeve is placed over the cranium defect, pulled taut, and pressed firmly onto the edge of the native cranium symptoms flu trusted 100 mg pristiq. Methyl methacrylate will undergo the exothermic reaction; nevertheless, the salinesoaked cotton balls shield the underlying cortex. When the perimeters of the plate turn into extra clear, the methyl methacrylate prosthesis should be faraway from the plastic sleeve and soaked briefly in chilly saline. In a research of 611 cranioplasty procedures using porous polyethylene, all patients achieved glorious beauty outcomes with no postoperative infections. Hydroxyapatite cement is able to be impregnated with quite a lot of antibiotics intraoperatively. Studies have demonstrated a predictable concentration and sustained launch of tobramycin from hydroxyapatite cement for roughly 10 days. Joint arthroplasty procedures have more extensively used antibiotic-eluting materials, with some combined success in reducing infection. Because each cranioplasty material has its personal advantages and downsides, research have examined hydroxyapatite�polymethyl methacrylate composites. Conversely, methyl methacrylate is simpler to form and is stronger, but it has comparatively poor osteoconductivity. The incision follows the prior incision, with care taken to stay directly on the scar to avoid necrosis of scalp. Reflection of the scalp flap is commonly troublesome as a result of the normal tissue planes are often distorted. Great effort must be taken to identify the aircraft between the galea and dura mater. A periosteal elevator or Bovie may be used to dissect these layers fastidiously through the reflection of the scalp. In addition, specific care must be taken in the area of the temporalis muscle as a outcome of the entirety of the muscle must be mirrored with the scalp flap. Failure to reflect the temporalis muscle, either independently or with the scalp, will result in a less than optimal beauty end result. When the entirety of the cranium defect is exposed and the perimeters of bone are clear of remaining delicate tissue, the cranioplasty flap could additionally be both fashioned or replaced if it is autologous. The key technical difference in the exposure throughout autologous cranioplasty is that the dura must be freed from the internal desk of the native cranium. In distinction, when methyl methacrylate is used, exposure of the outer cortex only is preferred, because it permits a thinner cranioplasty for use and helps with proper contouring. In formation of the methyl methacrylate prosthesis, shaping of the plate to realize a superb cosmetic outcome requires careful planning. Large saline-soaked cotton balls are placed into the cranium defect above the dura and molded till they form the appropriate contour. When the At this level, the cotton balls are eliminated, and the autologous bone graft or synthetic prosthesis is secured to the native skull with standard titanium plates and screws. In some situations, a central dural tack-up or dural drain could additionally be necessary to stop formation of postoperative epidural fluid collection. Dural tack-up sutures around the edges of the skull defect may also help prevent epidural hematomas, although the proof for this is anecdotal. In addition, small perforations in either the autologous bone graft or methyl methacrylate plate may help forestall formation of a fluid collection beneath the prosthesis. In some cases, the scalp has retracted, and closure of the skin edges over the new bone requires careful placement of galeal sutures and vertical mattress sutures to reapproximate the scalp. Use of a subgaleal drain is beneficial after each methyl methacrylate and autologous cranioplasty as a result of it prevents the in depth facial swelling which will occur after these operations. Finally, a firm and secure head wrap dressing may also assist with management of scalp edema. Some surgeons routinely place patients in an intensive care setting for a minimum of one evening to watch neurological standing more carefully. However, for a routine cranioplasty, we acquire a postoperative computed tomographic scan and then place the patient in a non�intensive care setting. In addition, placement of titanium mesh under the acrylic plate can enhance the energy of the construct. Some reviews have indicated that resorption of autologous bone happens extra regularly in children and is associated with the scale of the skull defect. A 12 month in vivo examine on the response of bone to a hydroxyapatite-polymethylmethacrylate cranioplasty composite. Cranioplasty: indications, technique, and early results of autogenous cut up cranium cranial vault reconstruction. Long-term experience with methylmethacrylate cranioplasty in craniofacial surgical procedure. Similarly, the ventricles might enhance in size after cranioplasty, both from brain atrophy or from manifesting true hydrocephalus. In addition, what is considered an acceptable cosmetic result after cranioplasty will proceed to become more rigorously scrutinized. Although the strategies described in this chapter will yield excellent synthetic prostheses, use of the computer-generated bone flaps from computed tomographic knowledge will likely replace Full references could be discovered on Expert Consult @ Na+ entry into choroid plexus epithelium is downhill (gradient-wise) from plasma throughout the basolateral membrane. This industrious secretory epithelium provides a gradual fluid output that has an influence on the biochemical and biophysical integrity of the mind. Directionally, the fluxes are mainly from interstitium to parenchyma to ventricles. Such transfers occur by stepwise and parallel processes described within the following sections. Two main focusing on websites or methods try and modulate choroid plexus secretory operate: (1) manipulation of the concentrations of neurotransmitter and neuropeptide ligands which have receptors on choroid epithelial membranes that interface with the extracellular fluid and (2) use of diuretic-type brokers to interfere with membrane-bound transporter proteins that impact ion-water fluxes. Dual apical transporter targets are the Na+ pump and the Na+-K+-Cl- cotransporter. This cyclic ahead and backward fluid motion, as generally monitored in the aqueduct, is a rhythmic passive response to arterial pulsations and mind compliance. Various methods have been employed for measurement of hyperdynamic pulsatile flow within the aqueduct, the most common being average flow price (in milliliters per minute) and stroke quantity. Although early research using aqueductal stroke quantity as the flow measure reported favorable outcome from shunt surgery. Analyses of hydrodynamic and hemodynamic relationships present differentials in disease diagnosis. Following this sequence of circulate distributions in systole, there are successive reverse phases during diastole to refill the aqueduct. More data is required to verify the medical impression that the cervical-aqueductal stroke quantity ratio decreases with age. With disease-induced variations in compliance, specifically intracranial compartments, it could be clinically instructive to assess distorted cervical-aqueductal stroke volumes. In each animal and human models, late-onset idiopathic aqueductal stenosis has been linked to venous malfunctions: elevated venous stress and higher collateral move. This units up a focus gradient for macromolecules and parenchymal catabolites, directed from brain interstitial fluid into ventricles and subarachnoid area. Serotonergic ependymal fibres in rat and monkey: light and electron microscopic immunocytochemical study. Increased concentration of atrial natriuretic issue in the cerebrospinal fluid of sufferers with aneurysmal subarachnoid hemorrhage and raised intracranial stress. Effect of vasopressin on manufacturing of cerebrospinal fluid: possible role of vasopressin (V1)�receptors. Choroid plexus Na+/K+-activated adenosine triphosphatase and cerebrospinal fluid formation. Relationship of senescence of cerebrospinal fluid circulatory system to dementias of the aged. Intracranial stress waves: characterization of a pulsation absorber with notch filter properties utilizing systems evaluation: laboratory investigation. Pickard Diagnosis and management of grownup sufferers with hydrocephalus continue to be challenging. Too typically, management of hydrocephalus has been restricted to serious about drainage of a balloon-the cerebral mantle is equally essential and much much less forgiving.
Syndromes
- You may also see a massage therapist, and someone who performs acupuncture. Sometimes a few visits will help your back or neck pain.
- Bronchiectasis
- Numbness in parts of the body
- Skin abscess
- Tests and cultures on sputum to identify the Legionella bacteria
- Traumatic brain injury
- Treatment may be considered with a level as low as 20 micrograms/dL.
- Walking aids and foot support devices
Related Products
Additional information:
Usage: q.2h.
Tags: 50 mg pristiq, order 50 mg pristiq fast delivery, pristiq 50 mg mastercard, 50 mg pristiq generic with mastercard, pristiq 50 mg buy otc, pristiq 100 mg purchase amex, pristiq 100 mg discount line, pristiq 100 mg buy on line, 100 mg pristiq generic otc, pristiq 100 mg low price, pristiq 50 mg discount overnight delivery, pristiq 100 mg order fast delivery, cheap 50 mg pristiq fast delivery, pristiq 100 mg on line, order pristiq 50 mg online, discount pristiq 50 mg with mastercard
10 of 10
Votes: 152 votes
Total customer reviews: 152
Customer Reviews
Hanson, 22 years: Instruments required for tumor resection are anticipated and should embrace special transsphenoidal or skull base instrument sets, endoscopic tools, and the Cavitron ultrasonic aspirator. At the time of osteotomy closure and correction, the circulating nurse and an assistant will elevate the legs onto further pillows, thereby rising hip extension and serving to to realize correction.
Asam, 62 years: The following points should be thought of rigorously when a cognitive task is designed: (1) factors of interest and nuisance elements, (2) timing of stimulus delivery and response, (3) technology and recording of the timing signal, (4) order of stimulus presentation or response, and (5) number of trials. In the limited number of sequence on schizencephalic lesions, surgery has been proven to be notably efficient, especially when the resection was tailor-made to the seizure focus and not just the schizencephalic region.
Fedor, 52 years: Hyperintensities which are affected by fats suppression strategies have additionally been noted within intervertebral disks and are regarded as associated to ossification with lipid marrow formation in severely degenerated or fused disks. A language crucial area is identified if the patient is unable to speak (speech arrest) when the positioning is being stimulated or if the affected person can speak however is unable to name objects.
Seruk, 55 years: This strip will guide itself alongside the sphenoid and ultimately place contacts near the parahippocampal gyrus. Compression of the nerve roots or wire may result in neuronal injury, ischemia, or edema.
Sugut, 59 years: Lesions of the cerebral hemisphere (cortex or white matter) scale back alertness only if current bilaterally. Central retinal vein occlusion27 and department retinal vein occlusion28 trigger marked retinal hemorrhages that are impressive and difficult to miss initially.
Arakos, 47 years: In our apply, we defer cranioplasty if the patient has any energetic an infection, together with Clostridium difficile. Theoretical and experimental evaluation of the cerebrospinal fluid system [PhD thesis].