
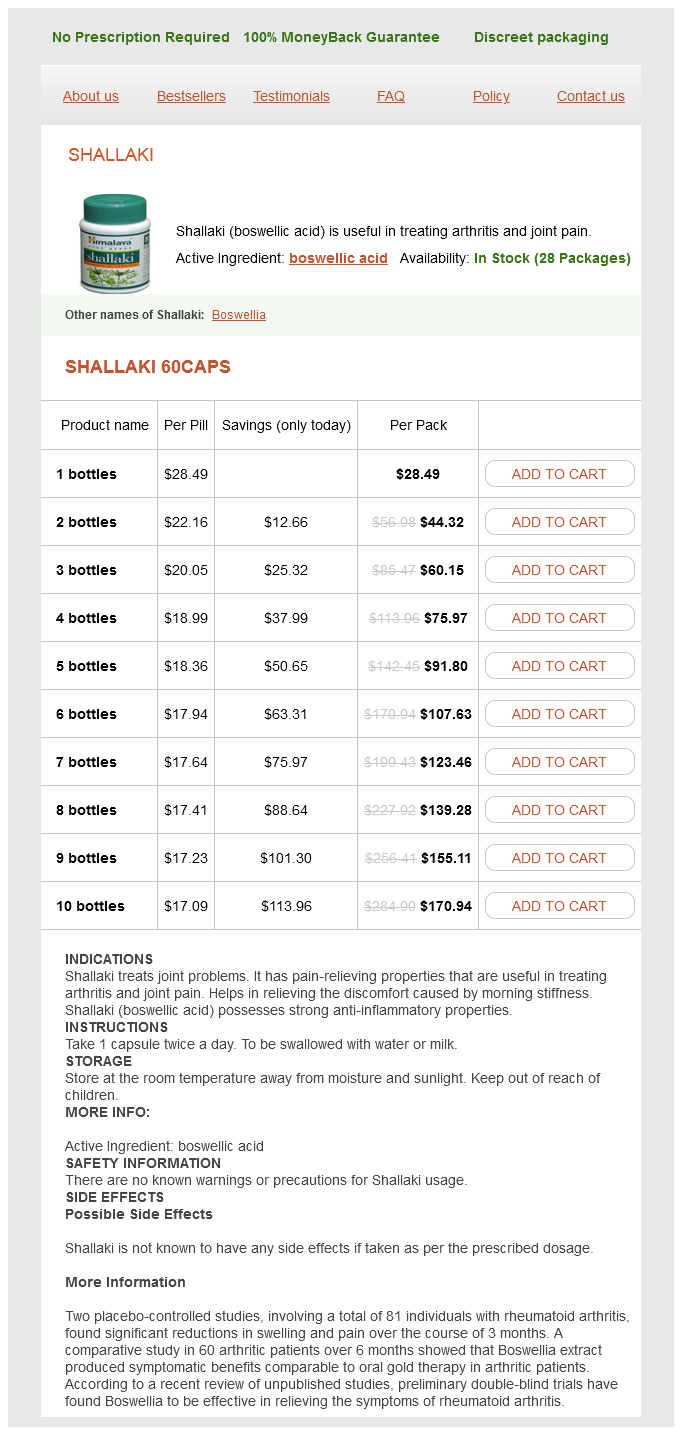
Shallaki
Shallaki 60caps
- 1 bottles - $28.49
- 2 bottles - $44.32
- 3 bottles - $60.15
- 4 bottles - $75.97
- 5 bottles - $91.80
- 6 bottles - $107.63
- 7 bottles - $123.46
- 8 bottles - $139.28
- 9 bottles - $155.11
- 10 bottles - $170.94
Shallaki dosages: 60 caps
Shallaki packs: 1 bottles, 2 bottles, 3 bottles, 4 bottles, 5 bottles, 6 bottles, 7 bottles, 8 bottles, 9 bottles, 10 bottles
In stock: 946
Only $18,16 per item
Description
Auriculotemporal Nerve arises from two roots that encircle the middle meningeal artery spasms under left breastbone 60 caps shallaki safe. It lies anterior to the inferior alveolar nerve on the medial pterygoid muscle spasms that cause shortness of breath buy shallaki 60 caps without a prescription, deep to the ramus of the mandible back spasms 36 weeks pregnant 60 caps shallaki buy with mastercard. It crosses lateral to the styloglossus and hyoglossus muscles spasms from dehydration discount 60 caps shallaki fast delivery, passes deep to the mylohyoid muscle, and descends lateral to and loops underneath the submandibular duct. It additionally carries the postganglionic fibres from the submandibular ganglion to supply the submandibular and sublingual salivary gland. Inferior Alveolar Nerve passes deep to the lateral pterygoid muscle and then between the sphenomandibular ligament and the ramus of the mandible. It enters the mandibular canal through the mandibular foramen and provides the tissues of the chin and lower tooth and gum. It provides rise to the next branches: Mylohyoid nerve, which innervates the mylohyoid and the anterior belly of the digastric muscle; inferior dental branch, which innervates lower enamel; psychological nerve, which innervates the pores and skin over the chin; incisive department, which innervates the canine and incisor tooth. Head and Neck Branches of the mandibular nerve From major trunk Nerve spinosus (meningeal branch) Nerve to medial pterygoid From anterior division From posterior division Masseteric nerve Auriculotemporal nerve Deep temporal nerves Lingual nerve Nerve to lateral pterygoid Inferior alveolar nerve Nerve to lateral pterygoid Inferior alveolar nerve Buccal nerve N. Mandibular division of trigeminal nerve Palatine division of maxillary nerve Anterior nasal division of maxillary nerve Infraorbital branch of maxillary nerve 7. Mandibular nerve � � � � � � � � � Meningeal department (nervus spinosus) arise from the principle trunk of mandibular nerve. Upper (Maxillary) teeth are supplied by the superior alveolar nerves that are three in quantity. There are three superior alveolar arteries by the names-anterior, posterior and middle, all given by the maxillary artery. Middle superior alveolar nerve supplies the palatal enamel on the maxilla and therefore may be acknowledged because the palatal department of maxillary nerve. It is given by the infra-orbital nerve, while operating within the infra-orbital groove. Superior alveolar nerves (branch of maxillary nerve provide the higher (maxillary) enamel, whereas decrease (mandibular) tooth are provided by the inferior alveolar nerve (branch of mandibular nerve). Superior alveolar nerves are three in number and make superior dental plexus to supply the higher tooth: Posterior, center and anterior. Posterior superior alveolar nerve is a branch of maxillary nerve, whereas center and anterior are given by the infra-orbital nerve (branch of maxillary nerve). Trigeminal nerve has 3 branches: ophthalmic, maxillary and mandibular, the lesions leads to sensory loss on face. Partial deafness to low pitched sound because of paralysis of tensor tympani muscle is also noticed. Maxillary nerve enters the inferior orbital fissure to proceed as infraorbital nerve, which runs on the ground of orbit. Posterior superior alveolar nerve is a direct department of maxillary nerve given in the pterygopalatine fossa to provide the upper molar tooth. It carries sensation from the face by three branches, certainly one of them being the maxillary nerve. Skin on the mandible (except the angle) is provided by the mandibular division of trigeminal nerve. It is shaped by the evagination of the meningeal layer of the dura mater by two roots of the trigeminal nerve, below the superior petrosal sinus, over the trigeminal impression on the anterior surface of the petrous temporal bone close to its apex. It is equipped by a branch of major trunk, which additionally supplies the two tensors (tensor tympani and tensor palati). Medial pterygoid High Yield Point � Artery supply to trigeminal ganglion is by cavernous a half of inner carotid artery. Facial Nerve 370 Facial nerve has two elements: motor to facial expression muscles and nervus intermedius. The fibres come up from the motor nucleus of facial nerve (pons), loop around the abducent nucleus (internal genu), elevating facial colliculus (at floor of fourth ventricle), exit the brainstem on the ponto-medullary junction. Next the fibres enter the internal auditory meatus, pass via the facial canal in the center ear cavity, give a department to stapedius muscle, exit the skull through the stylomastoid foramen. Upon reaching the facial canal, it joins with the motor root of the facial nerve at the geniculate ganglion. It carries fibres for style, salivation, lacrimation, and basic sensation (from the external ear). The first-order sensory neurons are found in the geniculate ganglion within the temporal bone. Superior salivatory nucleus accommodates the cell bodies of parasympathetic axons throughout the nervus intermedius. These secretomotor fibres attain the geniculate ganglion, pass by way of it with out synapse and attain pterygopalatine ganglion to synapse, which further cross on the fibres to lacrimal, nasal and palatine glands. The sensory part of the nervus intermedius carries input about sensation from the pores and skin of the external auditory meatus, mucous membranes of the nasopharynx and nostril, and style from the anterior two-thirds of the tongue, flooring of the mouth, and the palate. The sensory info kind the mucous membranes of the nasopharynx and palate is carried alongside the greater petrosal nerve, while the chorda tympani nerve (and lingual nerve) carries style enter from the anterior two thirds of the tongue, ground of mouth, and palate. Lacrimal pathway-Secretomotor fibres pass via the nervus intermedius and greater petrosal nerves to the pterygopalatine (spheno-palatine. Submandibular pathway-Secretomotor fibres cross via the nervus intermedius and chorda tympani to the submandibular ganglion to innervate the submandibular and sublingual salivary glands. Greater petrosal nerve is a branch of the facial nerve that arises distal to the geniculate ganglion, inside the facial canal, in middle ear cavity. It enters the center cranial fossa via the hiatus for the larger (superficial) petrosal nerve (on the anterior surface of the petrous temporal bone). It proceeds in the course of the foramen lacerum, where it joins the deep petrosal nerve (sympathetic) to kind the vidian nerve of the pterygoid canal, which passes via the pterygoid canal to reach the pterygopalatine ganglion. The higher (superficial) petrosal nerve carries gustatory (taste) and parasympathetic fibres. Postganglionic parasympathetic fibres from pterygopalatine ganglion supply lacrimal gland and the mucosal glands of the nose, palate, and pharynx. The gustatory fibres of palate carried by this nerve, attain the geniculate ganglion and next run in facial nerve to attain eventually the nucleus tractus solitarius in medulla oblongata. Vidian nerve: Sympathetic fibres across the inside carotid artery type the deep petrosal nerve, which joins the higher petrosal nerve (parasympathetic fibres) to kind the vidian nerve of pterygoid canal. Facial nerve comes out via the stylomastoid foramen and appears posterior to the parotid gland, enters the parotid gland to give rise to five terminal branches-the temporal, zygomatic, buccal, mandibular, and cervical branches that radiate ahead in the face. The fibres innervate the muscles of facial expression and send the posterior auricular branch to the muscles of the auricle and the occipitalis muscle. Chorda tympani nerve is given within the middle ear cavity, runs medial to the tympanic membrane and malleus. It carries pre-ganglionic fibres and is joined by lingual nerve (a department of mandibular nerve), which carries post-ganglionic parasympathetic fibres to reach the submandibular and sublingual salivary glands. Cortical (upper motor neuron) or brainstem (lower motor neruron) lesions have different clinical presentation. Crocodile tears syndrome (Bogorad syndrome) is spontaneous lacrimation during eating caused by a lesion of the facial It follows facial paralysis and is as a outcome of of misdirection of regenerating parasympathetic fibers, which formerly innervated the salivary (submandibular and sublingual) glands, to the lacrimal glands. A patient with crocodile tears syndrome has spontaneous lacrimation throughout consuming as a outcome of misdirection of regenerating autonomic nerve fibers. A patient presents with hyperacusis, loss of lacrimation and lack of style sensation within the anterior 2/3rd of the tongue. Chorda tympani carries pre-ganglionic (and not post-ganglionic) para-sympathetic fibres. Chorda tympani nerve is a department of facial nerve given in the facial canal (middle ear cavity) and carries secretomotor fibres to provide the sub-lingual and sub-mandibular salivary glands. It is joined by lingual nerve (branch of mandibular, trigeminal) in the infra-temporal fossa. Carries post-ganglionic parasympathetic fibres 375 Self Assessment and Review of Anatomy 5. Facial nerve proximal to the geniculate ganglion � � Crocodile tears syndrome (Bogorad syndrome) is spontaneous lacrimation during eating caused by a lesion of the facial nerve proximal to the geniculate ganglion. It follows facial paralysis and is because of misdirection of regenerating parasympathetic fibers, which formerly innervated the salivary (submandibular and sublingual) glands, to the lacrimal glands. Vidian nerve is shaped at the ground of foramen lacerum and runs anteriorly in pterygoid canal to reach the pterygopalatine ganglion.
Medhika (Fenugreek). Shallaki.
- What is Fenugreek?
- Diabetes, high cholesterol, high triglycerides, stomach upset, decreased appetite, constipation, hardening of the arteries (atherosclerosis), gout, sexual problems (impotence), fever, baldness, and other conditions.
- How does Fenugreek work?
- Are there safety concerns?
- Dosing considerations for Fenugreek.
- Are there any interactions with medications?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96717
The presence of pus in any of the perianal and perirectal areas could additionally be confirmed with needle aspiration spasms mid back cheap shallaki 60 caps on line. An examination underneath common anesthesia could also be necessary to muscle relaxer 800 mg shallaki 60 caps buy lowest price affirm the diagnosis muscle relaxant lyrics generic shallaki 60 caps with mastercard. For example spasms 1983 movie discount shallaki 60 caps without prescription, the traditional "horseshoe" abscess originates in an infected gland within the posterior midline extending through the intersphincteric and deep postanal areas to one or each of the ischiorectal areas. A situation known as "floating anus" might happen with circumanal unfold of intersphincteric, supralevator, or ischiorectal collections. It is tough to precisely assess the incidence of various abscesses because of the quite a few classifications and referral patterns mirrored in massive sequence. A massive ischiorectal abscess frequently represents a horseshoe extension (see later). In this example, an examination beneath general anesthesia is warranted to determine the abscess. This area is troublesome to evaluate clinically, making these the second sort of hidden abscess. Possibilities include appendicitis, diverticulitis, pelvic inflammatory illness, or ruptured viscus. A horseshoe abscess is the end result of a direct extension of a postanal abscess into the ischiorectal space (see part Ischiorectal Abscess). The patient often presents with complaints of intermittent or persistent purulent or serosanguineous drainage from an exterior opening in the perianal space. Symptoms classically include a buildup of pain, slight fever, and ache on defecation adopted by mucopurulent drainage and abatement of the pain. Pruritic symptoms could also be current due to skin irritation associated with the continual discharge. Physical Examination Fistula tracts are fibrous inflammatory tubes with a diameter of three to 7 mm. Essential points that should be obtained from a scientific examination were described almost one hundred years in the past by Goodsall and Miles11; they embody the identification of the exterior and internal openings, the course of the first and any secondary tracts, the tone of anal sphincters and an evaluation for the presence of an underlying complicating illness. Using an anoscope, systematic inspection and palpation can outline most of these traits. The mild use of a quantity of malleable anorectal probes and crypt hooks can help to delineate the fistula by trying to move these instruments through the internal or exterior opening. It is important not to drive the passage of the probe because the event of false tracts can complicate evaluation and administration. Secondary tracts could additionally be current when induration is palpated or asymmetry is famous between the proper and left sides of the anorectum. In some circumstances, corresponding to recurrent, intensive, or complex fistulas, the use of refined imaging methods might yield further data to information profitable remedy. The exterior opening is identified as a small pit surrounded by scar or granulation tissue. Intersphincteric tracts normally open externally near the anal verge; transsphincteric and other difficult tracts open farther away. Occasionally the external opening may be localized inside the anal canal or on the distal finish of a fissure. The internal opening may be felt as an indurated nodule, most often on the dentate line. There is a high extension of the fistula between the inner sphincter and the longitudinal muscle of the higher anal canal. The infection spreads as much as reach the true pelvic cavity lying above the levator musculature. This fistula outcomes from the spread of pelvic collections by way of the intersphincteric aircraft. The higher tract extension might go to the apex of the ischiorectal fossa or extend higher through the levator musculature into the pelvic cavity. The tract then passes above the extent of the puborectalis muscle and continues downward by way of the ischiorectal fossa to the perianal space. This fistula could additionally be a consequence of an extension of a transsphincteric fistula or secondary to trauma, anorectal disease, or pelvic inflammation. The use of saline, milk, dye, or dilute hydrogen peroxide as an injection into the exterior fistula opening has been made in an attempt to localize the internal opening. Note quite a few fistula tracts (arrows) extending anteriorly to scrotum, bilaterally to ischiorectal fossas, and posterior perianal areas. Posterior such as neoplasms, inflammatory bowel illness, or associated secondary tracts within the rectum, have to be sought. With this method, the exterior opening is cannulated with a small-caliber tube and contrast material is injected underneath minimal stress while movies are taken in a number of projections. Fistulography could also be useful in figuring out unsuspected pathology, planning surgical administration, and demonstrating anatomic relationships. However, a research by Kuijpers and Schulpen14 discovered fistulography to be unreliable in contrast with operative findings. They observed a prohibitively high incidence of false-positive results that could lead to pointless and harmful surgical exploration. Anorectal Ultrasonography Transanal ultrasound can delineate the muscular anatomy of the anal sphincters in relation to an abscess or a fistula. Although typically accurate in the localization of abscesses and fistula tracts, primary superficial, extrasphincteric, and suprasphincteric tracts or secondary supralevator or infralevator tracts could also be missed. If the external opening is posterior to this line, the interior opening will most probably be positioned within the posterior midline with the tract following a curved route to reach its supply. Exceptions to this rule include anterior openings greater than three cm from the anal verge and the presence of a quantity of exterior openings. However, the predictive accuracy of Goodsall rule has been challenged, particularly with anterior exterior openings12 or when Crohn illness or carcinoma is present. Anorectal Manometry Anorectal manometry is an objective technique for finding out the contribution of the anorectal sphincter to the physiologic strategy of defecation. Manometry can assist in identifying patients at the best threat for postoperative incontinence. Surgical administration could be tailored accordingly, improving medical and functional end result. The selective use of anorectal manometry is very warranted in sufferers with suspected sphincter impairment; patients suspected of needing substantial parts of the external sphincter divided for fistula remedy; and ladies with a historical past of multiparity, forceps delivery, third-degree perineal tear, high birthweight, or prolonged second stage of labor. However, 5% to 15% of complicated fistulas are sometimes related to recurrent fistulas and fistulas related to underlying Crohn illness. Hydrogen peroxide enhancement allowed for a extra precise delineation of the tracts in addition to a right-sided extension of the tract. Fistuloscopy Anorectal fistuloscopy using versatile ureteroscopes has been described. This is a probably useful intraoperative approach used to identify main fistula openings, a quantity of or complicated tracts, and iatrogenic tracts. We look forward to their evolution as a result of they represent a novel diagnostic and therapeutic tool which will significantly enhance the outcomes of complicated fistula diagnosis and remedy. Treatment delay might lead to continual infection and tissue destruction with fibrosis and long-term impairment of perform. Antibiotics ought to be used as adjunctive therapy in special circumstances solely; these embody sufferers with valvular coronary heart disease excluding mitral valve prolapse,23 immunosuppression, extensive related cellulitis, and diabetes. A cruciate incision is made over probably the most tender or fluctuant point as close to the anal verge as possible. If a fistula develops, the exterior opening will be close to the verge, so a fistulotomy would require division of the least amount of muscle. Continued drainage of enormous cavities may be achieved with the utilization of a 3- to 5-mm de Pezzer or comparable catheter left in situ till drainage subsides. Here a de Pezzer catheter may be used to enhance the drainage of enormous cavities. Intersphincteric Abscess An intersphincteric abscess is drained by laying open the internal sphincter (sphincterotomy) overlying the cavity. By definition, a fistulotomy is performed by destruction of the inciting anal gland. Submucosal Abscess Submucosal abscesses are drained internally by incising the mucosa over the abscess. Supralevator Abscess Anatomic localization of the septic origin is of paramount significance within the administration of supralevator collections. Collections that outcome from abdominopelvic disease may be drained transrectally or transabdominally.
Specifications/Details
Transducers are a vital part of the water-perfusion system spasms pelvic area shallaki 60 caps buy, where the mechanical water pressure is changed to electrical alerts within the transducer muscle relaxant for children 60 caps shallaki quality. Each perfusion channel has a aspect channel that connects to a transducer muscle relaxant triazolam purchase shallaki 60 caps with visa, and when water is perfused via the aspect channels muscle relaxant vecuronium purchase shallaki 60 caps line, it additionally transmits pressures back to particular person transducers. In the water perfusion method, the water-perfusion machine is an integral part. The water is pushed via each of the individual facet channels in the tube at a selected price; because the water flows via the holes close to the tip pressure changes are measured. A monitor is attached to observe the tracings because the procedure is carried out, and specialised software shows the results by way of charts, tables, and graphical printouts. However, the internal sphincter and the external sphincter could additionally be individually analyzed based mostly on the pressures represented by the resting tone and the squeeze stress. The resting strain reflects the interior sphincter function, as this muscle contributes between 55% and 85% of resting stress, and the squeeze stress reflects external sphincter perform. Rectal sensation could be altered by pathologies corresponding to irritation or radiation remedy, which decrease rectal compliance and tolerated volumes. Increased tolerable volumes could be found in problems similar to megarectum or neurogenic abnormalities. Rectal sensory threshold has been proven to be useful for determining whether biofeedback might be profitable. This reflex is absent in Hirschsprung illness and immediately postoperatively following a low anterior resection or coloanal anastomosis. In the presence of a megarectum, a higher volume of rectal distention is required to elicit the reflex, which can lead to false-negative outcomes. The balloon expulsion test is usually carried out using a 50-mL water-filled balloon and offers a easy baseline Resting common (mm Hg) Right Post 60cm 70 53 sixty one 50cm 69 59 40cm 62 sixty five 30cm 70 sixty nine 20cm 98 fifty five 10cm 87 Anter. In sphincter damage, when muscle is changed by scar tissue, no insertional activity is encountered. The authors advocate the take a look at in conjunction with other research for one of the best diagnostic picture. The center anal canal has each the hypoechoic exterior sphincter and hyperechoic internal sphincter muscular tissues. Studies are restricted but have demonstrated that the sensitivity of detecting both inside and exterior sphincter defects is comparable between the 2D and 3D research, however intraobserver variation is decreased and diagnostic accuracy is elevated with the 3D imaging. The radiographs can be taken through the screen for this research whereas the patient performs the aforementioned acts of defecation. Measurements can embrace the anorectal angle (the angle between the longitudinal axis of the anal canal and the posterior wall of the decrease a half of the rectum), the power to fully empty the rectum, the degree of perineal descent, rectoceles, enteroceles, sigmoidoceles, anismus, and intussusception. As defecography facilitates visualization of the mechanism of defecation, it aids identifying outlet obstruction disorders of defecation, corresponding to nonrelaxing puborectalis, intussusception, or a big rectocele, enterocele, or sigmoidocele. The fast-phase sequences permit for quick analysis with elevated patient consolation, decreased complexity, and decreased invasiveness. The photographs additional permit measurement of the anorectal angle on straining, which can be used to diagnose paradoxical contraction of the puborectalis muscle (anismus). Transit Studies the mean transit time through the entire colon has been shown to be 31 hours in males and 39 hours in girls. There are many protocols used to carry out the study, but all essentially evaluate the number of markers that stay on easy abdominal radiographs 5 days after marker ingestion. The sort of constipation can be ascertained by the pattern of marker distribution the place sufferers with slow transit constipation will have more than 20% of ingested markers retained but scattered all through the colon on day 5, while these with outlet obstruction constipation could have the overwhelming majority of markers moved successfully to rectum and rectosigmoid area by day 5 however are unable to evacuate them. Patients with pelvic ground dysfunction can have coexisting gradual transit constipation, and a few authors have famous normalization in the transit time with correction of outflow problems. Scintigraphy Scintigraphy is an option to assess the mobility of the entire gastrointestinal system. Transit occasions obtained via scintigraphy are generated following consumption of a radiolabeled egg sandwich, and particular person instances are generated for the stomach, small bowel, and colon. This preliminary step permits clarification of signs and bodily findings and allows tailored investigational planning. Not all sufferers will be surgical candidates; nevertheless, a thoughtful work-up might increase the chance of symptomatic improvement after surgical procedure. The prevalence of pelvic flooring disorders and their relationship to gender, age, parity and mode of delivery. Prevalence of pelvic flooring issues within the female population and the impression of age, mode of supply, and parity. Fecal Incontinence Quality of Life Scale: high quality of life instrument for sufferers with fecal incontinence. A constipation scoring system to simplify analysis and administration of constipated patients. Defecation frequency and timing, and stool kind in the basic population: a prospective study. Adoption of the pelvic organ prolapse quantification system in peer-reviewed literature. American Gastroenterological Association: medical place assertion on anorectal testing methods. Predictive worth of the balloon expulsion test for excluding the analysis of pelvic flooring dyssynergia in constipation. Balloon expulsion test facilitates prognosis of pelvic flooring outlet obstruction because of nonrelaxing puborectalis muscle. Preoperative improve in neuromuscular jitter and outcome following surgical procedure for faecal incontinence. Slowed conduction within the pudendal nerves in idiopathic (neurogenic) faecal incontinence. Pudendal nerve terminal motor latency testing: assessing the educational learning curve: can we train our personal Endosonography of the anal sphincters: regular anatomy and comparison with manometry. Prospective research of the extent of internal anal sphincter division throughout lateral sphincterotomy. Threedimensional anal endosonography might enhance diagnostic confidence of detecting injury to the anal sphincter complicated. Dynamic transperineal ultrasound within the analysis of pelvic floor issues: pilot research. Dynamic pelvic magnetic resonance imaging and cystocolpoproctography alter surgical administration of pelvic flooring problems. Cinedefecography and electromyography in the diagnosis of nonrelaxing puborectalis syndrome. Magnetic resonance imaging of anatomic and dynamic defects of the pelvic floor in defecatory issues. External anal sphincter atrophy on endoanal magnetic resonance imaging adversely affects continence after sphincteroplasty. Not only are they unusual, however the technical features of restore along side managing etiology appropriately current a multidisciplinary problem to even the most skilled surgeon. Not solely do they present particular points with respect to quality of life, but also difficult management of septic issues, administration of radiated tissue, and the difficult dance of staged repair. They are uncommon, comprising approximately 5% of all anorectal fistulas, but present a major challenge for each the affected person and the surgeon. These are sometimes related to a protracted second stage of labor resulting in ischemic necrosis of the rectovaginal septum. A multidisciplinary strategy, including medical administration to guarantee quiescent anorectal illness, is crucial. Spontaneous delayed presentation of pouch vaginal fistula is usually a manifestation of beforehand unsuspected Crohn disease. This fee was as high as 18% in sufferers who acquired exterior beam radiotherapy utilizing older radiation sources along with interstitial brachytherapy for superior gynecologic malignancy. This is usually misdiagnosed as fecal incontinence or attributed to vaginal an infection. Diagnosis is often easy, however management of these circumstances is difficult by numerous elements, corresponding to radiated tissue, septic problems, comorbidities, and the need for coordination amongst multiple specialists.
Syndromes
- Skeletal x-ray
- Have been on long-term kidney dialysis
- Loss of feeling
- Worrisome behavioral changes
- All ICDs have a built-in pacemaker. Your heart may need pacing if it is beating too slowly or too fast, or if you have had a shock from the ICD.
- Birth control pills or progesterone only pills
- Knee swelling
- Liver cancer
- Surgical removal of burned skin (skin debridement)
- Phoratoxin
Related Products
Additional information:
Usage: q._h.
Tags: shallaki 60 caps fast delivery, shallaki 60 caps generic with visa, discount 60 caps shallaki mastercard, shallaki 60 caps buy otc, shallaki 60 caps purchase overnight delivery, shallaki 60 caps generic visa, cheap shallaki 60 caps, shallaki 60 caps generic otc, shallaki 60 caps cheap with mastercard, shallaki 60 caps purchase with amex, discount shallaki 60 caps free shipping, discount shallaki 60 caps mastercard, generic 60 caps shallaki mastercard, 60 caps shallaki purchase with amex, shallaki 60 caps purchase free shipping, discount shallaki 60 caps amex
8 of 10
Votes: 27 votes
Total customer reviews: 27
Customer Reviews
Mojok, 22 years: As such, it may be very important distinguish these syndromes to assign more precise threat stratification.
Riordian, 56 years: In European countries, tumors with the distal edge positioned inside the last 15 cm of the massive bowel are categorized as rectal cancer; in the United States, the limit is 12 cm.
Gancka, 32 years: Growth exercise is negligible here � Metaphysis is the epiphyseal end of the diaphysis.
Killian, 52 years: Combination of oral non-absorbable and intravenous antibiotics versus intravenous antibiotics alone in the prevention of surgical site infections after colorectal surgical procedure: a meta-analysis of randomized controlled trials.