
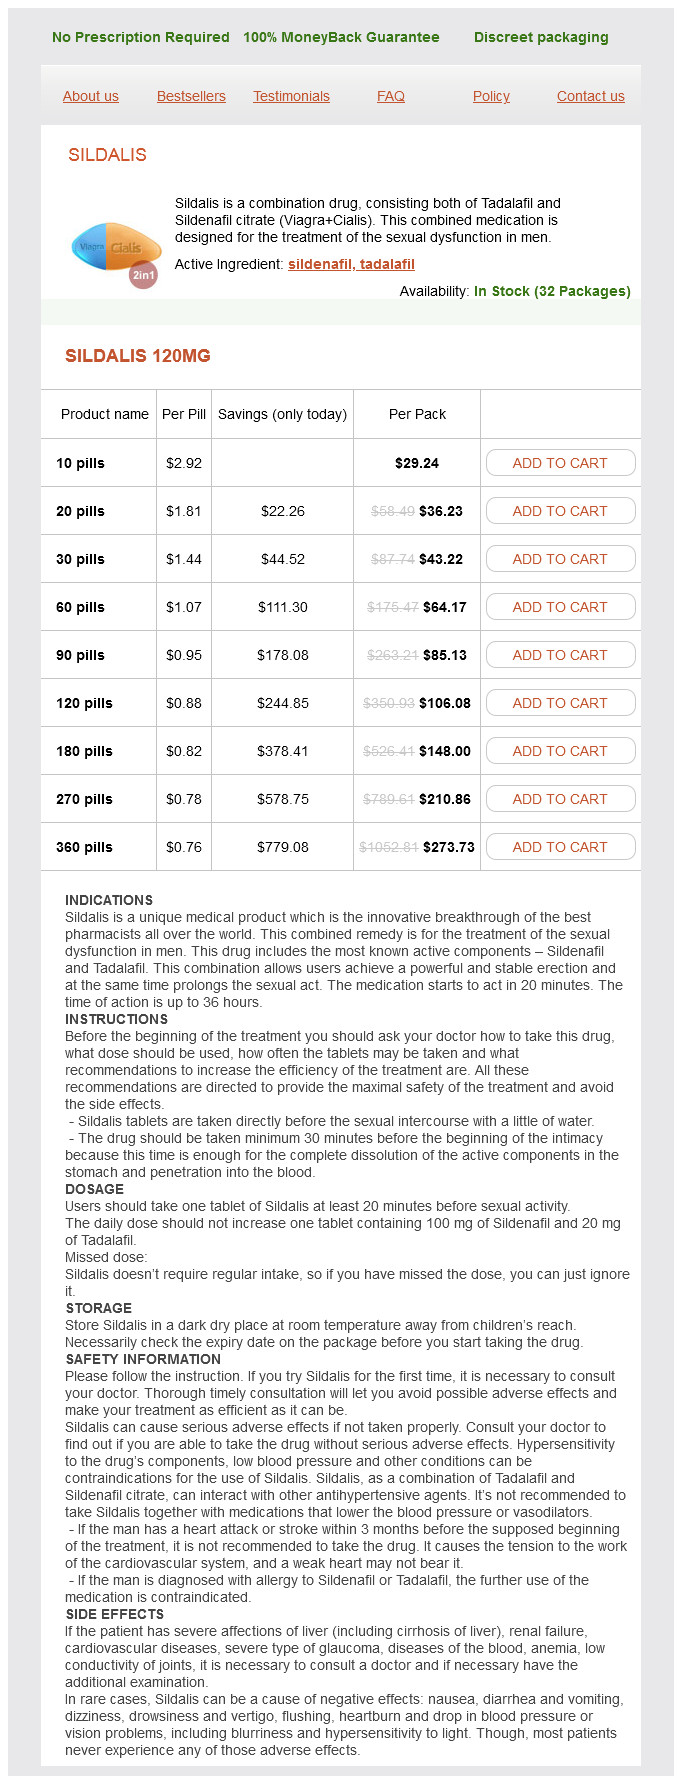
Sildalis
Sildalis 120mg
- 10 pills - $29.24
- 20 pills - $36.23
- 30 pills - $43.22
- 60 pills - $64.17
- 90 pills - $85.13
- 120 pills - $106.08
- 180 pills - $148.00
- 270 pills - $210.86
- 360 pills - $273.73
Sildalis dosages: 120 mg
Sildalis packs: 10 pills, 20 pills, 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 873
Only $0,81 per item
Description
Cartilage is current from the trachea to the smallest bronchi erectile dysfunction doctors huntsville al generic sildalis 120 mg on line, but is absent (by definition) from bronchioles erectile dysfunction treatment orlando sildalis 120 mg quality. Intrapulmonary bronchi include discontinuous plates or islands of hyaline cartilage in their walls erectile dysfunction drugs available in india sildalis 120 mg order. Tracheal cartilages Each of the 16�20 tracheal cartilages measures about four mm in top and 1 mm in thickness impotence natural home remedies sildalis 120 mg with visa, showing thicker within the center half; their external floor is flat while the inner aspect is barely convex. Cartilage loses elasticity and calcifies in older age, and adjacent cartilages could variously fuse. Bronchial cartilages Cartilaginous plates mainly surround the dorsal side of the lobar bronchi. They turn into more irregular and form progressively much less of the bronchial partitions in intrapulmonary bronchi, and disappear within the bronchioles. Inhaled air is humidified mainly within the higher respiratory tract, where it passes, with some turbulence, over the nasal and buccopharyngeal mucosae. The secretions of the assorted glands of the bronchial tree additionally assist to forestall desiccation. Goblet cells secrete sulphated acid mucosubstances; cells in mucous glands beneath the epithelial floor contain mainly carboxylated mucosubstances, significantly these associated with sialic acid, though sulphated teams additionally occur; cells of serous glands include neutral mucosubstances. Goblet cells respond primarily to local irritation, while tubular glands, each mucous and serous, are mainly under neural and hormonal management. Cilia sweep the fluid overlying the surfaces of bronchioles, bronchi and trachea upwards at 1 cm/min, and far of the inhaled matter trapped within the viscous fluid may be eliminated in this way. Particles small enough to attain the alveoli may be removed by alveolar phagocytes. Alveolar epithelium has limited powers of regeneration however normally is continually replaced. The lifespan of alveolar squamous cells is roughly 3 weeks, and that of alveolar phagocytes is four days. Numerous lymphoid nodules happen in the bronchial lining, providing foci for the manufacturing of lymphocytes and giving native immunological safety against infection each by cell-mediated (T-cell) actions, and by the production of immunoglobulins (mainly IgA) from B cells, which are passed on to gland cells for secretion to the epithelial floor. Bronchial veins Usually two on each side, the bronchial veins drain blood from bigger bronchi and hilar structures. Deep bronchial veins commence as intrapulmonary bronchiolar plexuses that talk freely with the pulmonary veins and finally join a single trunk that ends in a major pulmonary vein or within the left atrium. Superficial bronchial veins drain extrapulmonary bronchi, visceral pleura and the hilar lymph nodes. They also communicate with the pulmonary veins and finish in the azygos vein on the right, and within the left superior intercostal or the accessory hemiazygos vein on the left. The major bronchial arteries and veins run on the dorsal side of the extrapulmonary bronchi. The trachea is innervated by branches of the vagi, recurrent laryngeal nerves and sympathetic trunks; the nerves enter the lung as networks that travel alongside branches of the bronchi and pulmonary and bronchial vessels so far as Pleura, lungs, trachea and bronchi the predominant contractile innervation of airway clean muscle is parasympathetic and cholinergic in nature, whereas the primary relaxant innervation of the airways is non-cholinergic (parasympathetic nerves containing nitric oxide synthase and vasoactive intestinal peptide). These parasympathetic nerves are anatomically and physiologically distinct from one another and differentially regulated by reflexes. Sympathetic-adrenergic nerves play little, if any, function in immediately regulating smooth muscle tone within the human airways. Activation of airway afferent nerves (rapidly adapting receptors, C fibres) can evoke will increase in airway smooth muscle parasympathetic nerve activity, or decreases in parasympathetic nerve exercise (via activation of slowly adapting receptors). Extrapulmonary afferents could modulate neurally mediated regulation of airway clean muscle tone (Canning 2001a). Stimulation of cholinergic nerves causes not solely bronchoconstriction but also mucus secretion and bronchial vasodilation. Brush cells Brush cells are slender, non-ciliated cells with characteristically lengthy, stiff apical microvilli, from which they derive their name. They are involved with afferent nerve fibres basally and are presumed to have a sensory receptor perform. Neuroendocrine cells, additionally termed dense-core or small granule (Kulchitsky) cells, are found mainly in the basal a half of the epithelium. They have a rounded form and the cytoplasm basal to their nuclei accommodates quite a few small, dense-cored vesicles, approximately 150 nm in diameter. Neuroendocrine cells are most quite a few in fetal lungs and their number decreases dramatically after delivery. There seems to be little further change of their frequency during grownup life, although they might proliferate in certain pulmonary diseases. Neuroendocrine cells Epithelium the epithelia of the trachea, bronchi and bronchioles are, in general, much like one another, with graded variations within the numbers of different cell varieties. There are fewer cilia in terminal and respiratory bronchioles, and the cells are reduced in top to low columnar or cuboidal. The epithelium within the respiratory bronchioles progressively reduces in height in course of the alveoli, and is ultimately composed of cuboidal, non-ciliated cells. Respiratory bronchioles have lateral pouches of their walls, that are lined with squamous cells, so offering an adjunct respiratory floor. Lymphocytes and mast cells migrate into the epithelium from the underlying connective tissue. Clusters of lymphocytes sometimes lie beneath nonciliated epithelial cells of the microfold (M-cell) type. They resemble connective tissue mast cells, and their cytoplasmic histaminecontaining granules are released in response to irritants, including inhaled allergens. Submucosal glands Tubuloacinar, seromucous glands are present within the submucosa of the trachea and bronchi and, to a lesser extent, within the larger bronchioles. They include separate mucous and serous cells and are an essential supply of the mucus at the surface of the ciliated respiratory epithelium. Their secretions embrace mucins; bacteriostatic substances corresponding to lysozyme and lactoferrin; secretory antibodies (immunoglobulin A (IgA)) produced by plasma cells in the submucosal connective tissue; and protease inhibitors. Deficiency of 1-antitrypsin causes continual obstructive pulmonary disease, by inducing panacinar emphysema and bronchiectasis. The secretory acini and tubules are surrounded by myoepithelial cells, that are innervated by autonomic fibres (see above). Ciliated columnar cells Goblet cells Goblet cells are present from the trachea (6000�7000 per mm2) distal to the smaller bronchi, but are usually absent from bronchioles. They comprise an apical region full of enormous secretory vacuoles filled with mucinogen. Clara cells Clara cells are cuboidal, non-ciliated cells with apices that bulge into the lumen. Basal cells contact the basal lamina and are most frequent within the bigger conducting passages. The cilia lengthen into a watery fluid secreted by serous cells of the submucosal glands, but their ideas are in contact with a extra superficial layer of thicker mucus secreted by floor goblet cells and mucous cells in the submucosal glands. The price of ciliary beating is normally 12�16 per second; mechanical stimulation of the epithelial floor and inflammatory mediators improve the rate. In addition to tight junctions, which seal the apical intercellular house from the airway lumen, the ciliated cells are coupled by hole junctions, which allow a change in fee of beating to unfold from stimulated cells to their neighbours (probably through calcium signalling) in order that their metachronal coordination stays intact. This elastic framework is a crucial mechanical factor of the lung and is answerable for elastic recoil during expiration. Along the whole intrapulmonary bronchial tree, easy muscle varieties two opposed helical tracts, which turn into thinner and finally disappear at the level of the alveoli. The tone of these muscle fibres is beneath nervous and hormonal management; teams of muscle cells are coupled by gap junctions to spread excitation within fascicles. Muscle cell contraction narrows the airway, while rest permits bronchodilation. Some tone normally exists within the muscular bands, which loosen up barely during inspiration and contract throughout expiration, thereby helping the tidal flow of air. Numerous mast cells are current within the connective tissue of the respiratory tree, particularly in direction of the bronchioles. Seromucous submucosal glands (S) are concentrated in this area and between adjoining cartilages. It enhances clearance of secretions and particulates from the airways and protects from aspiration of foreign materials (occurring as a consequence of aspiration or inhalation of particulate matter, pathogens, accrued secretions, postnasal drip, irritation and mediators related to inflammation).
Zhi Qiao (Bitter Orange). Sildalis.
- Weight loss, nasal congestion, intestinal gas, cancer, stomach and intestinal upset, intestinal ulcers, regulating cholesterol, diabetes, chronic fatigue syndrome (CFS), liver and gallbladder problems, stimulation of the heart and circulation, eye swelling, colds, headaches, nerve and muscle pain, bruises, stimulating appetite, mild sleep problems (insomnia), and other conditions.
- What is Bitter Orange?
- Are there any interactions with medications?
- Dosing considerations for Bitter Orange.
- How does Bitter Orange work?
- What other names is Bitter Orange known by?
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96937
The tendons of extensor digitorum are seen and palpable on the dorsal hand with the fingers totally prolonged impotence drugs for men purchase 120 mg sildalis with amex. Note the course of the terminal branches of the superficial radial nerve and the lateral cutaneous nerve of the forearm best erectile dysfunction vacuum pump 120 mg sildalis fast delivery. A evaluation of the surface and intra-articular anatomy of the wrist erectile dysfunction or gay order sildalis 120 mg otc, the method of building a secure portal and the particular uses of the radiocarpal erectile dysfunction testosterone injections discount 120 mg sildalis fast delivery, metacarpal and special-use portals. A chapter describing the various ways during which surgeons and others can injure the peripheral nerves of the body. Costa H, Pinto A, Zenha H 2007 the posterior interosseous flap � a prime technique in hand reconstruction. Echigo A, Aok M, Ishiai S et al 2008 the excursion of the median nerve during nerve gliding exercise: an remark with high-resolution ultrasonography. Kretschmer T, Antoniadis G, Richter H-P et al 2009 Avoiding iatrogenic nerve harm in endoscopic carpal tunnel release. An anatomical examine of 12 cadaver arms which demonstrates quite a lot of vascular anastomoses around the scaphoid. Petrie S, Collins J, Solomonow M et al 1997 Mechanoreceptors in the palmar wrist ligaments. The closed traction lesion of the supraclavicular brachial plexus is amongst the worst of all peripheral nerve injuries due to the frequent affiliation with injury to the spinal cord and the standard complication of extreme ache. There is one widespread element: the violent distraction of the forequarter from the head, neck and chest so that the angle between the head and the shoulder is opened. These are sometimes accidents of great violence and motor cyclists in high-speed accidents are particularly at risk. Associated accidents to the top, backbone, chest, abdomen, pelvis, lengthy bones and subclavian artery are frequent. The most typical website of nerve lesion lies inside the spinal canal, affecting the intradural segments of the spinal nerves. These injuries are known as preganglionic as a result of the lesion lies between the dorsal root ganglion and the spinal wire. This idea of pre- and postganglionic damage, launched by Bonney in 1954, is key to diagnosis and treatment. The preganglionic injury is the commonest lesion as a result of the union of the ventral and dorsal roots is the weakest hyperlink in the lengthy chain between the central nervous system and the periphery. In one sequence of 200 sufferers operated on between the years 2000 and 2004, 429 spinal nerves sustained preganglionic rupture, 223 have been postganglionic ruptures and the remaining 298 spinal nerves were intact or recovering. The fifth and sixth cervical nerves are somewhat protected by proximal branches to such nerves because the phrenic and lengthy thoracic, and also by the transverse radicular ligaments. The vulnerability of C8 and T1 is enhanced by the increasing obliquity of the roots in the spinal canal and the angulated course of T1. The abrasion on the tip of the shoulder marks the purpose of impact in opposition to a roadside kerb. The nerve tissue on the web site of the rupture confirmed no central nervous system options. The tip is covered by organized blood clot and erythrocytes that interweave with fibrin strands. Note the dorsal root ganglion, the dural sleeve merging into the epineurium, and the spinal nerve itself. The small pieces of tissue on the proximal ends of the dorsal rootlets (below) are in all probability portions of the spinal twine. A, A traction lesion of the brachial plexus accompanied by rupture of the subclavian artery; there was a weak pulse. At operation, 54 hours after damage, stimulation of the avulsed ventral roots of C7, 8 and T1 evoked sturdy contraction in the related muscular tissues distally. This showed that there was neither crucial ischaemia throughout the limb nor a second, extra distal, lesion. B, Strong somatosensory evoked potentials were recorded through electrodes placed over the scalp, by stimulation of the postganglionic ruptured stumps of C5 and C6 (1). The dorsal root ganglia of C7, 8 and T1 (2) and their ventral roots (3) are shown. Intraoperative research of motor and sensory conduction are important in emergency or urgent exploration of the brachial plexus. Diagnosis It is necessary all the time to search for occult accidents to the head, chest and backbone. Note the intact dorsal root ganglion cell, with healthy axons in the indifferent elements of the roots, and the degeneration of the efferent fibre within the ventral root. Analysis, historical past and exact clinical examination often permit an correct prognosis of the extent and the level of the neurological damage. History An understanding of the axis of utility of drive to the injured limb is very important. A description from witnesses or the patient of the shoulder being violently arrested by an object � stone, tree, kerb or automobile � while the body is flying by way of the air confirms that there was violent stretching of the constructions within the posterior triangle of the neck. Pain Severe ache inside a paralysed and anaesthetic limb indicates very severe injury to the spinal nerves. It may be fixed, described as crushing, burning or intense pins and needles, and is usually felt in the forearm and hand. Two-thirds of acutely aware patients who developed such ache did so on the day of injury. More than one-half of aware patients experienced this pain on the day of damage (Birch 2011b). Inspection Inspection of the limb could reveal linear cuts and abrasions passing from the face to the shoulder, indicating distraction of the limb when harm was sustained. Deep bruising is an important sign of tearing of prevertebral muscle or even of the subclavian artery. Increasing swelling in the posterior triangle signifies a group of spinal fluid, either from nerves avulsed from the spinal cord or from an expanding haematoma, or each. A degenerate efferent myelinated fibre (right) compared to a non-degenerate afferent myelinated fibre (left). C4 innervates the pores and skin of the outer facet of the shoulder; T2 innervates the pores and skin of the inside facet of the arm. When these lengthen down the outer arm and proximal forearm, then rupture of C5 is probably going. When they prolong to the lateral aspect of the forearm and thumb, then a similar lesion of C6 may be anticipated. Percussion over a rupture of C7 evokes sensations into the dorsum of the hand; that over a rupture of the lower trunk evokes sensations in the inner aspect of the forearm and little fingers. It is necessary to advise the Investigations Radiological and imaging studies affirm or modify the clinical analysis, but they could additionally affirm or reveal related injuries to the spinal column, the spinal wire and the chest. Plain radiographs verify elevation of the ipsilateral hemidiaphragm and should present tilting of the cervical spine away from the side of damage, which is commonly associated with fracture or dislocation of the first rib. However, the incidence of injury to the subclavian artery within the operated circumstances stays steady over this time at about 10%. Complete lesions accounted for 141 of the cases; fifty two patients sustained preganglionic injury to all five spinal nerves. Over the years, there was a modest Treatment the direct object of treatment is rehabilitation. The return of fluid and coordinated muscle action, and of the biceps tendon jerk, suggests some regeneration into the deep afferent pathway, perhaps through myelinated afferent fibres in the ventral root. Pain aid One of essentially the most pleasing elements of surgical endeavour has been the finding that reinnervation of muscle is frequently successful in improving pain and this may be a robust indication for securing reinnervation of a limb, regardless of how limited, in even essentially the most extreme accidents (Berman et al 1996, Berman et al 1998, Kato et al 2006; see Birch 2011a, Birch 2011b, Birch 2011c). Function is proven at ninety six months after restore: wrist extension was regained by switch of flexor carpi ulnaris to extensor carpi radialis brevis. Function is proven at the shoulder and elbow eleven years after reimplantation of the ventral roots of C5, C6 and C7. Bonney G 1954 the worth of axon responses in figuring out the positioning of lesion in traction lesions of the brachial plexus.
Specifications/Details
An accent component to the collateral ligament arises in continuity with the principle ligament and passes in a volar path to attach to the volar plate erectile dysfunction treatment side effects buy generic sildalis 120 mg on-line. Factors sustaining stability Stability is conferred by the articular contours of the joint surfaces and the collateral ligaments erectile dysfunction zoloft generic sildalis 120 mg line. The flexor and extensor tendons and retinacular ligaments provide secondary stabilization erectile dysfunction at age 26 discount 120 mg sildalis visa. Extensions from the extensor expansion erectile dysfunction age group sildalis 120 mg cheap on line, each collateral ligament and the palmar ligament all pass into the joint cavity and supply a major enhance to the articular surface space of the phalangeal base; their deformable nature improves joint congruence. Joint actions Active actions at the interphalangeal joints are flexion and extension, and are greater in vary on the proximal joints. Flexion is appreciable, whereas extension is restricted by pressure of the digital flexors and terminated by pressure within the palmar ligaments and non-articular compression. Flexion and extension are accompanied by slight rotation; during flexion, this turns the digital pulps slightly laterally, i. Accessory movements Accessory actions are limited rotation, abduction, adduction and anteroposterior translation. They permit the fingers to adapt to the shapes of gripped objects and assist to protect in opposition to stresses and strains. Nutrient branches of the digital Muscles producing actions the muscles producing actions at the interphalangeal joints are as follows. Flexion Flexion is produced at the proximal interphalangeal joints by the flexors digitorum superficialis and profundus; at distal interphalangeal joints, by flexor digitorum profundus; and at the thumb interphalangeal joint, by flexor pollicis longus. Extension Extension is produced by extensors digitorum, digiti minimi and pollicis longus, in association with abductor pollicis longus and extensor pollicis brevis. Simultaneous flexion at the metacarpophalangeal joints and extension on the interphalangeal joints of a digit are important for the fine actions of writing, drawing, threading a needle, and so forth. The lumbricals and interossei are primary agents in flexing the metacarpophalangeal joints and also in extending the interphalangeal joints through their attachments to the dorsal digital expansions. The blood vessel supplying the flexor tendons by way of the vincula brevum is proven; the mesentery forming the vinculum has been omitted. The radiocarpal joint is equipped by branches of the anterior interosseous artery, anterior and posterior carpal branches of the radial and ulnar arteries, palmar and dorsal metacarpal arteries, and recurrent rami of the deep palmar arch. The carpal joints are equipped by the posterior carpal branches of the radial and ulnar arteries, and by the anterior interosseous artery. The carpometacarpal joint of the thumb receives its blood provide from the radial artery and its first dorsal metacarpal branch. The second to fifth carpometacarpal joints are provided by the posterior carpal branches of the radial and ulnar arteries, by twigs from Wrist and hand the ulnar collateral ligament of the metacarpophalangeal joint of the thumb could additionally be avulsed from its distal attachment to the bottom of the proximal phalanx by a combination of compelled extension and radial deviation of the joint. The ulnar collateral ligament is generally coated by the aponeurotic insertion of the tendon of adductor pollicis. Following avulsion, the proximal finish can become superficially displaced across the proximal free edge of the aponeurotic insertion of the adductor. This gentle tissue interposition prevents the ends of the avulsed ligament from therapeutic. Surgical restore requires division of the aponeurotic insertion of adductor pollicis, adopted by bony reattachment of the avulsed ligament and repair of the aponeurosis. The comparable injury to the radial collateral ligament is much less widespread and constitutes solely 10�42% of collateral ligament injuries (Edelstein et al 2008). It is attributable to sudden, forced adduction of the metacarpophalangeal joint as the results of a fall or during ball games. The ligament may be ruptured in its mid-substance or avulsed from both bony attachment. Early identification is crucial as a outcome of the proximal phalanx of the thumb will subluxate ulnarwards and may rotate, leading to degeneration of the articular floor. Interposition of the torn or avulsed portion is unusual because the adductor aponeurosis lies over the radial collateral ligament. The affected person is unable to lengthen the terminal phalanx actively, though the distal interphalangeal joint could be extended passively. Swan neck deformity entails hyperextension of the proximal interphalangeal joint, together with distal interphalangeal joint flexion, attributable to relative overactivity of the extensors performing on the proximal interphalangeal joint compared with the flexors. Boutonni�re deformity is a flexion deformity of the proximal interphalangeal joint following either division or laxity in the central slip of the extensor tendon (which usually inserts into the bottom of the center phalanx). The deformity often happens as a result of both trauma or rheumatoid arthritis, inflicting the lateral bands of the extensor tendon to migrate in a volar course and the head of the proximal phalanx to migrate dorsally. Initially, the deformity is passively correctable, however, with time, the soft tissues across the joint contract and a exhausting and fast deformity results. The metacarpophalangeal joints obtain their blood provide from the dorsal and palmar metacarpal arteries, the arteria princeps pollicis, and the arteria radialis indicis. The interphalangeal joints are provided by branches from the palmar digital arteries. During flexion, the cruciate fibres turn into oriented more transversely in the digits, and the sides of adjoining anular pulleys approximate in order that they kind, in full flexion, a steady tunnel of transversely oriented fibres. Surgically, the most important pulleys that prevent bowstringing of the flexor tendons are the A2 and A4 pulleys. The oblique pulley is situated over the mid-portion of the proximal phalanx and its fibres pass from the ulnar facet proximally to the radial side dorsally. The A2 pulley is thinner than the A1 pulley and is located just proximal to the interphalangeal joint. The oblique pulley is an important pulley within the thumb for sustaining the action of flexor pollicis longus. Two synovial sheaths envelop the flexor tendons as they traverse the carpal tunnel: one for flexors digitorum superficialis and profundus, the opposite for flexor pollicis longus. The sheath is extended across the tendons to the little finger and is normally steady with their digital synovial sheath. The parietal layer strains the flexor retinaculum and the floor of the carpal tunnel, and is reflected laterally because the visceral layer over the tendons of flexor digitorum superficialis ventrally and flexor digitorum profundus dorsally. Medially, a recess fashioned by the visceral layer of the sheath insinuates between the 2 groups of tendons and passes laterally for a variable distance. The sheath of flexor pollicis longus, which is usually separate, is continued along the thumb so far as the insertion of the tendon. The anterior interosseous nerve and posterior interosseous nerve innervate the central two-thirds of the anterior and posterior wrist joint capsule, together with the radiocarpal joint. These appear to be pure afferent nerve fibres with mechanoreceptor endings, of which there are an average of 10 in each dorsal radiocarpal ligament (Tomita et al 2007). In the palmar radiocarpal ligaments, however, Golgi organs, Pacinian corpuscles, Ruffini endings and free nerve endings are discovered (Petrie et al 1997). An uneven distribution of these throughout the ligaments would counsel specific functional adaptation however the exact nature of that is unclear. The carpometacarpal joint of the thumb is innervated by articular twigs from the posterior interosseous nerve and the superficial department of the radial nerve. The second to fifth carpometacarpal joints are innervated by branches of the ulnar nerve, the anterior interosseous, and the superficial radial and dorsal ulnar nerves. The metacarpophalangeal joints are innervated by twigs from the palmar digital branches of the median and ulnar nerve, the deep terminal department of the ulnar nerve, and the posterior interosseous nerve. The interphalangeal joints are innervated by the palmar digital branches of the median nerve (to the thumb, index, middle and ring fingers), and the ulnar nerve (to the ring and little fingers). Vincula Flexor tendon sheaths the fibrous sheaths of the flexor tendons are specialised components of the palmar fascia. Each finger has an osseo-aponeurotic tunnel that extends from midpalm to the distal phalanx. The thumb has a tunnel for flexor pollicis longus that extends from the metacarpal to the distal phalanx. The proximal border is, to some extent, a matter of definition as a result of the transverse fibres of the palmar aponeurosis could additionally be thought-about to be a part of the pulley system. The sheath consists of arcuate fibres that arch anteriorly over bone, tendons (where the sheath is required to be stiff) and the centres of joints (where a bucket-handle of arcuate fibres is a mechanically favourable arrangement). In distinction, the place the sheath is required to fold to permit joint flexion, it consists of cruciate fibres. These fibrous sheaths are lined by a thin synovial membrane that gives a sealed lubrication system containing synovial fluid.
Syndromes
- Fluids by IV
- Daily medications to prevent repeat episodes
- Coma
- Medicines for depression and visits to a therapist or counselor
- Any food prepared by someone who did not wash their hands properly
- Visual acuity testing
- Anticonvulsant therapy for seizures
- Deficiency of factor II that is present at birth (congenital)
- Blood clot in an artery in the lung
Related Products
Additional information:
Usage: q.h.
Tags: sildalis 120 mg discount fast delivery, generic sildalis 120 mg line, purchase sildalis 120 mg online, 120 mg sildalis proven, sildalis 120 mg order line, 120 mg sildalis cheap overnight delivery, 120 mg sildalis visa, cheap sildalis 120 mg without prescription, buy 120 mg sildalis fast delivery, 120 mg sildalis cheap with mastercard, buy sildalis 120 mg on line, generic sildalis 120 mg fast delivery, cheap sildalis 120 mg fast delivery, sildalis 120 mg purchase amex, sildalis 120 mg purchase with mastercard, sildalis 120 mg discount without prescription
10 of 10
Votes: 261 votes
Total customer reviews: 261
Customer Reviews
Sven, 64 years: Each posterior intercostal artery has dorsal, collateral, muscular and cutaneous branches. Joint movements Except at initiation, flexion is accompanied by medial rotation, and medial rotation involves flexion. The left ventricular cavity is slim and conical, and its tip occupies the cardiac apex.
Mannig, 59 years: The posterior facet of the thoracic pores and skin is equipped by the medial and lateral dorsal cutaneous branches of the posterior intercostal arteries (via erector spinae and latissimus dorsi); musculocutaneous perforating branches from the superficial cervical, transverse cervical and dorsal scapular arteries (via trapezius); musculocutaneous perforating branches from the thoracodorsal artery and the intercostal arteries (via latissimus dorsi); and direct cutaneous branches from the circumflex scapular artery. The broad tendon of flexor carpi ulnaris is easily palpated passing to the pisiform on the ulnar side of the anterior wrist; the ulnar nerve, artery and venae comitantes lie alongside its lateral (radial) edge. During surgical procedure, the pure adhesions between the transverse mesocolon and greater omentum may be divided, and the greater omentum may be indifferent from the transverse colon and mesocolon if required.
Peratur, 23 years: The skeletal framework of the thoracic wall offers intensive attachment sites for muscular tissues associated functionally with the neck, stomach, back and upper limbs. Sensory the ilioinguinal nerve supplies sensory fibres to transversus abdominis and inside indirect. The proper border is a gently curved line, convex to the proper, running from the third to the sixth right costal cartilages, usually 1�2 cm lateral to the sternal edge.
Harek, 52 years: Muscularis externa the muscularis externa has outer longitudinal and inside circular layers of easy muscle. When the flap valve remains to be capable of overlap the rims, the communication is of no functional significance so long as left atrial strain is greater than proper, which is often the case. The anterolateral surface is bounded by the anterior and lateral borders, and is easy and featureless in its higher part, which is roofed by deltoid.
Shawn, 55 years: Such juxta-arterial defects are doubly dedicated, in that they open beneath the orifices of both aortic and pulmonary valves. Refer to the text for additional named recesses of the overall serous pericardial cavity and its transverse sinus. There is some evidence that the appendix acts as a reservoir for normal gut flora, enabling the large bowel flora to recover more rapidly after extreme fuel troenteritis (Randal Bollinger et al 2007).
Goose, 26 years: It lies medial to the superior costotransverse ligament, and is separated from it by the dorsal ramus of a thoracic spinal nerve and accompanying vessels. Only a small proportion of the anomalies are immediately attributable to genetic or environmental factors and the majority are the result of multifactorial events. The flooring of the foramen is the preliminary phase of the superior part of the duodenum, its posterior wall is the peritoneum covering the immediately subhepatic a half of the inferior vena cava, and its roof the peritonealized caudate process of the liver.