
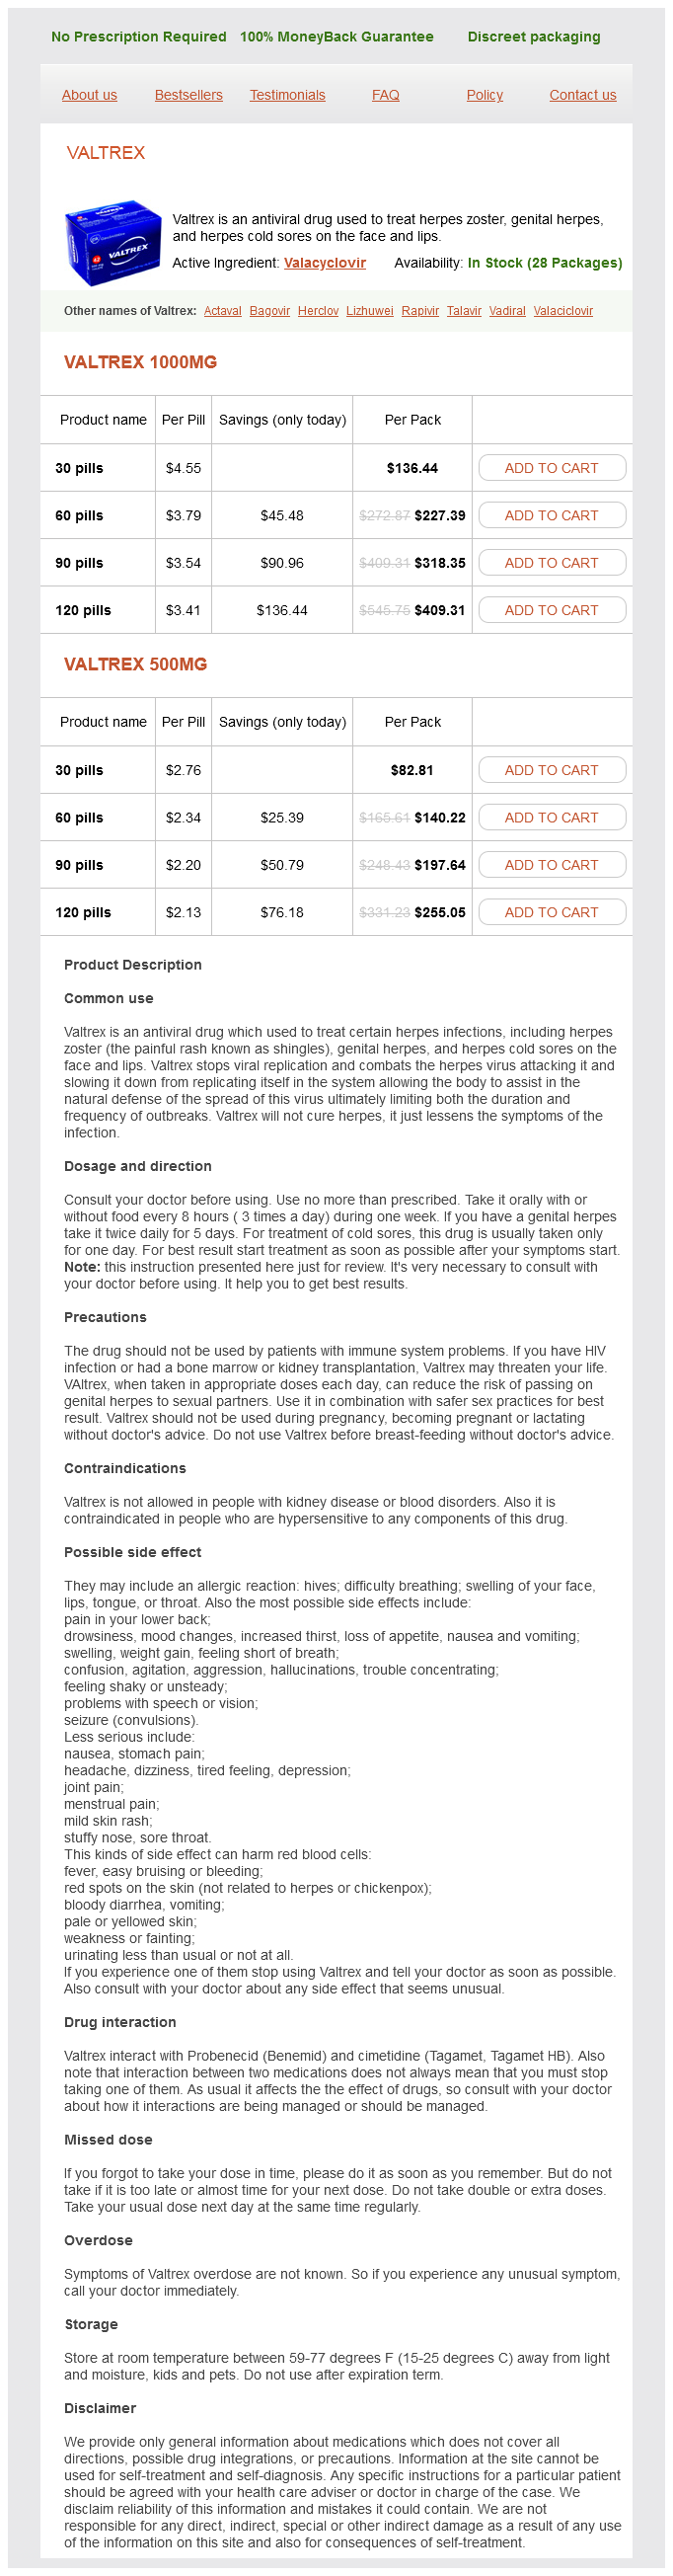
Valtrex
Valtrex 1000mg
- 30 pills - $136.44
- 60 pills - $227.39
- 90 pills - $318.35
- 120 pills - $409.31
Valtrex 500mg
- 30 pills - $82.81
- 60 pills - $140.22
- 90 pills - $197.64
- 120 pills - $255.05
Valtrex dosages: 1000 mg, 500 mg
Valtrex packs: 30 pills, 60 pills, 90 pills, 120 pills
In stock: 602
Only $2,26 per item
Description
These cells are highly concentrated at the fovea (the portion of the retina that corresponds to fixation) hiv infection duration order 1000 mg valtrex with mastercard. These cells give rise to the retinohypothalamic and retinotectal tracts and function as anatomical substrates for circadian rhythms four early symptoms hiv infection purchase valtrex 500 mg fast delivery, suppression of melatonin secretion hiv infection menstrual cycle valtrex 1000 mg order visa, and the pupillary light reflex hiv infection rates in african countries purchase 500 mg valtrex otc. As a consequence of this arrangement and the distribution of the photoreceptors (the cones are concentrated within the foveal space and the rods are dispersed more peripherally), vision is most acute centrally not only by way of acuity but in addition by means of colour imaginative and prescient and contrast sensitivity. A giant variety of ganglion cells mirror this excessive density of photoreceptors on the fovea and kind a bundle of axons that project directly to the temporal aspect of the optic disk. This papillomacular nerve fiber bundle is distinct from other axons, which reach the optic nerve head by a more arcuate course. The superior and inferior bands of axons by no means cross an imaginary horizontal midline that divides the retina into higher and decrease halves. The nerve fiber layer maintains a certain degree of retinotopy as it traverses the retina after which turns 901 posteriorly via the optic disk into the optic nerve. This retinotopy seems to turn into tighter as one proceeds posteriorly, but the fibers become disorganized once more close to the optic chiasm. Optic Nerve Head the optic nerve head, or papilla, constitutes the start of the optic nerve. Funduscopically, this appears as a yelloworange disk that always has a small empty space centrally, termed the optic cup. It is located approximately three mm nasal to the fovea and therefore produces a blind spot approximately 151 temporal to center. The retinal nerve fibers should flip 901 whereas progressing posteriorly into the optic nerve. As they do so, they move by way of stacks of perforated collagen plates termed the lamina cribrosa. This seal is maintained by specialized glial cells that encompass the columns of axons as they pierce via the fenestrations of the collagen plates. More posteriorly, these bundles of nerve fibers are separated by well-defined collagen septae. Immediately behind the lamina cribrosa, the axons that constitute the optic nerve become myelinated. The dura mater is the outer meningeal cowl of the optic nerve and it blends into the scleral masking of the attention. In distinction, the arachnoid and the pia mater of the optic nerve cease on the level of the posterior lamina cribrosa, leading to a cul-de-sac for the subarachnoid area. The optic nerve fibers type roughly 1000 bundles with approximately one thousand axons in every bundle. The sclera, which supplies the structural assist for the attention, blends into the dura mater as the outer meningeal cover of the optic nerve. The portion designated the optic nerve thus has anatomical, but not physiological, that means. The intraorbital segment is free to move loosely in a bed of fat and runs for about 25 mm. The intracanalicular optic nerve is roughly 9 mm lengthy and runs by way of a bony canal, sharing area with its blood supply, the ophthalmic artery. The intracranial optic nerve is approximately sixteen mm lengthy and ends at the optic chiasm. These septae, in addition to the robust surrounding meninges, present supple but robust assist to the optic nerve, which must stay flexible in the orbit. The optic nerve head has a quantity of anatomical and physiological options that make it weak to injury. Anterior ischemic optic neuropathy is a consequence of reduced blood circulate throughout the tight confines of the scleral canal. Finally, this slack allows for approximately 7 or eight mm of proptosis earlier than injury occurs to the nerve or the back of the globe. However, ailments which will affect any portion of the optic nerve, similar to optic neuritis, happen here as nicely. The intracanalicular phase is weak because of its position in the optic nerve canal. Fractures of the sphenoid bone cause direct crush or sheer injury (traumatic optic neuropathy). The intracranial optic nerve may be subject to compressive damage from masses within the parasellar area, together with pituitary adenomas or aneurysms of the ophthalmic artery. The ophthalmic artery derives from the carotid artery at the anterior end of the carotid siphon. It slips into an infranasal place and runs alongside the optic nerve in its intracranial, intracanalicular, and intraorbital course. A variety of small penetrating vessels originate from the ophthalmic artery and be part of the pial circulation of the nerve. Approximately 12 mm posterior to the globe, the main portion of the ophthalmic artery traverses the subarachnoid house and enters the inferior side of the optic nerve. It then turns anteriorly and, together with the central retinal vein, runs into the attention via the center of the optic nerve head, turning into the central retinal artery. Blunt trauma could injure the intracanalicular portion of the nerve, both immediately or by sheering branches of the ophthalmic artery that join the pial blood vessels. The dural covering of the optic nerve fuses with the periostium of the optic canal. The optic nerve partially decussates on the optic chiasm and joins the ipsilateral fibers from the other side to type the optic tract. However, simply posterior to the optic chiasm, some fibers emanate from the tracts superiorly to enter one of the three nuclei of the hypothalamus: the supraoptic, paraventricular, or suprachiasmatic nuclei. More posteriorly, a fascicle of axons branches off the optic tract to type the brachium of the superior colliculus, terminating in the optic tectum and pretectal nuclei. Anatomical separation of fibers has a physiological counterpart, with M-cells relating extra to high contrast sensitivity, low spatial frequency, and motion stereopsis, and P-cells subserving low contrast sensitivity, excessive spatial frequency, colour, and high spatial decision. The ganglion cells project axons via the lamina cribosa, a fenestrated sheet of connective tissue, to kind the optic disk and optic nerve. The ganglion cells course inside the nerve fiber layer in an arcuate sample towards the optic disk. The fibers from the ganglion cells decussate in the optic chiasm and terminate in the lateral geniculate nuclei. The central retinal artery and vein emerge from the disk, and the retinal vascular arcades start to branch quickly after. The color of the optic disk is derived from the peripapillary capillaries and nerve fiber layer, in addition to the lamina cribosa. The appearance of the optic disk is decided by the size of the globe, the scale of the scleral canal, how the nerve inserts into the globe, and axon density. There are particular person variations within the size of the scleral canal and configuration of the lamina cribosa, largely depending on the size of the globe. All of these axons are dependent on sluggish and fast axoplasmic transport for viability of the axon, synapses, and cell physique. The blood provide to the retina and optic nerve originates from the ophthalmic artery. The internal two-third of the retina is served by the central retinal artery, which travels inside the optic nerve for a short distance behind the disk, then branches out to provide the four quadrants of the retina. Optic Neuropathy Optic Disk Swelling and Optic Atrophy Optic neuropathy refers to dysfunction of the optic nerve because of tissue harm. Optic disk swelling from any trigger in the end results from blockage of sluggish and quick axoplasmic transport, with subsequent axoplasmic backflow. It is impossible to decide, on the basis of fundus examination alone, the specific etiology of a swollen optic disk. Indeed, in many circumstances, resolution of disk swelling simply indicates demise of axons, somewhat than efficacy of any therapies applied. Papilledema signifies optic disk swelling secondary to elevated intracranial pressure. The fundus examination could additionally be equivalent for all causes of intracranial hypertension.
Arthritica (Cowslip). Valtrex.
- Inflamed nasal passages or sinusitis when taken with gentian root, European elder flower, verbena, and cowslip flower (SinuComp, Sinupret).
- Are there safety concerns?
- What other names is Cowslip known by?
- Dosing considerations for Cowslip.
- Bronchitis, in combination with thyme; cough; whooping cough; insomnia; nervous excitability; headache; hysteria; nerve pain; tremors; fluid retention; spasms; asthma; gout; neurologic complaints; and other conditions.
- What is Cowslip?
- How does Cowslip work?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96202
Autonomic preganglionic neurons additionally give rise to axons that leave the twine through ventral roots antiviral brand names order 500 mg valtrex amex. Cell bodies of preganglionic parasympathetic neurons are positioned in the intermediolateral column of spinal wire segments S2 antiviral treatment cfs purchase valtrex 1000 mg with visa, S3 hiv infection after 5 years valtrex 1000 mg generic mastercard, and S4 hiv infection blood cheap valtrex 500 mg fast delivery. Axons of those neurons project to the postganglionic parasympathetic neurons situated in the viscera. The axons of these cells project to targets at various distances within the spinal cord proper. Those located medially project to alpha motor neurons over multiple segments, generally traversing the complete size of the cord, and their axons cross over to the alternative aspect and are thus concerned with upkeep of Spinal Cord Anatomy 261 posture. Certain neurons of the dorsal horn gray matter send axons rostrally to the brain and may be known as projection neurons. Rexed separated the spinal gray matter into 10 laminae, numbered utilizing Roman numerals. Some bigger neurons in the dorsal horn, called projection neurons, project to the mind. Additional afferents to these laminae come from secondary branches of thinly myelinated and unmyelinated fibers subserving noxious and thermal stimuli. Convergence of somatic and visceral nociceptors on neuron cell our bodies in this lamina is an accepted principle relating to referred pain. Most of the ventral horn is anxious with efferent mechanisms that management movements. It accommodates a wide range of neurons that might be localized with variable precision. These regions house preganglionic sympathetic and parasympathetic neurons, respectively. The preganglionic sympathetic neurons project to sympathetic ganglia via the ventral nerve roots, innervating cardiac muscle in addition to smooth muscle and glands throughout the body. These cells receive collaterals of axons of proprioceptive afferents from muscle and tendon and from endings in and round joint capsules. The axons of those cells represent the dorsal spinocerebellar tract, which initiatives to the spinocerebellum through the inferior cerebellar peduncle, carrying information about unconscious proprioception. This area receives a rich synaptic input from collaterals of large-diameter muscle, cutaneous, and deep tissue receptors. Some have contralaterally projecting axons which would possibly be essential in coordinating motor actions within the two halves of the cord. The somatotopic organization of the alpha motor neurons innervating completely different teams of muscular tissues in the extremities, from medial to lateral and ventral to dorsal, has already been described. Motoneurons that innervate a selected muscle are collected into an elongated grouping that occupies a predictable location, with little overlap with other motor nuclei. Alpha and gamma motoneurons belonging to a single muscle are intermingled within its motor nucleus. Functional Considerations of Spinal Cord Anatomy From a physiological perspective, the spinal cord has been intensively studied because its afferent inputs and motoneuronal outputs have clearly understood functions. It performs the first stages of knowledge processing in each somatic and visceral sensation and the ultimate stages of computation within the control of movement. In spite of those shortcomings, clinicians discover systematic application of the present overall data of anatomy and physiology of the spinal cord of considerable assist in localizing lesions of the spinal wire, with nice precision within the great majority of sufferers with spinal cord illness. Diseases of the spinal wire are quite common and these embody trauma, tumors (extradural metastatic tumors much more widespread than major intramedullary), multiple sclerosis, motor neuron ailments Vertebrate Nervous System, Development of the Further Reading Brodal A (2010) the Central Nervous System Structure and Function, 4th edn. Gilman S (2002) Joint position sense and vibration sense: Anatomical organization and evaluation. Introduction the spinal wire is a highly organized and delicate conduit linking the central nervous system to the peripheral nervous system. Ascending and descending fibers run alongside one another in pathways which comprise the outer white matter of the spinal twine. In cross-section, these white matter pathways encompass a butterfly-shaped central area containing gray matter. The decrease motor neuron axons exit anteriorly to innervate their targets via the peripheral nerves. The spinothalamic tract incorporates the ascending ache and temperature pathways and is situated within the ventrolateral portion of the spinal cord. This pathway originates from small, largely unmyelinated afferent peripheral nerve fibers. These fibers enter the dorsal horn of the grey matter, synapse, and at the same level crossover within the anterior portion of the spinal twine within the ventral commissure to form the lateral spinothalamic tract, which ascends on the contralateral side. It conveys ascending vibratory and proprioception sensation from the legs (fasciculus gracilis, positioned medially) and the arms (fasciculus cuneatus, situated laterally). Unlike the spinothalamic tract, the posterior columns comprise uncrossed sensory fibers (these fibers cross only when they reach the brainstem). The fibers answerable for vibration and proprioception sensation from the proper leg, for example, journey within the spinal cord to the brainstem in the best posterior column, whereas fibers responsible for ache and temperature sensation from the right leg travel on the left facet of the spinal cord. This anatomical relationship has essential clinical significance, which shall be mentioned additional. The lateral white matter of the spinal twine also incorporates the ascending spinocerebellar tracts, which convey data from the muscles to the cerebellum and are necessary in permitting precisely coordinated movements. Blood provide to the spinal twine is via the 2 posterior spinal arteries, which supply the posterior columns, and the one anterior spinal artery, which provides the anterior two-thirds of the spinal twine. The anterior and posterior spinal artery blood supply is augmented by a quantity of blood vessels throughout the length of the spinal cord. The largest is the artery of Adamkiewicz, which arises within the thoracolumbar region and provides the anterior spinal artery, thereby contributing to the circulation in the lumbar, sacral, and decrease thoracic spinal wire. The affected person usually has ache and radicular symptoms on the level of the lesion as a end result of compression of local nerve roots. Compression of the posterior columns results in a lack of vibration and proprioception below the level of the lesion. Below the level of the lesion, the affected person might have ipsilateral spasticity and weak point (from compression of the corticospinal tracts), ipsilateral loss of vibration and proprioception (from compression of the dorsal columns), and contralateral loss of ache and temperature sensation (due to compression of the lateral spinothalamic tracts which contain crossed fibers). Less common causes of spinal twine compression embody meningioma, neurofibroma, metastatic cancer (especially lung, breast, melanoma, lymphoma, and renal cell carcinoma), epidural hemorrhage or abscess, and spinal arteriovenous malformation. Metastatic spinal wire compression usually presents as native or radicular ache, adopted by a myelopathy with motor weak point, sensory loss, and lack of bowel and bladder management. Metastatic spinal cord compression ought to be treated with high-dose intravenous steroids, radiation, and presumably surgery. Acute Spinal Cord Trauma Most instances of acute spinal wire trauma are as a end result of motor vehicle accidents, with leisure accidents similar to soccer and diving and penetrating wound injuries comprising the 264 Encyclopedia of the Neurological Sciences, Volume 4 doi:10. The spinal twine is most susceptible to trauma at areas of mobility which may be around areas of stability. These regions are primarily the atlantoaxial joint, low cervical spinal wire, thoracolumbar, and lumbosacral areas. After acceptable neuroimaging, high-dose intravenous steroids should be given, if throughout the first 6 h of presentation. Occasionally, spinal surgery is required, for instance, if there are bony fragments that compress the cord. Treatment is directed primarily towards the underlying tumor as well as reduction of production or clearance of the offensive antibodies. Transverse Myelitis and Inflammatory Myelopathy Transverse myelitis refers to an acute inflammation of the spinal cord leading to spinal wire dysfunction. The cytokine-mediated inflammatory process results in demyelination and in the end to axonal loss. Unlike most compressive myelopathies as a outcome of spinal stenosis or disk herniation, transverse myelitis is more prone to contain the thoracic twine. Symptoms develop rapidly over hours, with the utmost deficit usually noted within 24 h. Acutely, however, patients may have spinal cord shock with lack of reflexes and flaccid weak point.
Specifications/Details
Replication in motor neurons of the spinal cord and native dorsal root ganglia and speedy ascent to mind Dorsal root ganglion Sensory nerves to pores and skin Skeletal muscle four antiviral blu ray review valtrex 500 mg buy generic on-line. Virus travels within axons in peripheral nerves through retrograde fast axonal transport 2 hiv infection and aids an overview valtrex 1000 mg without a prescription. Serum-neutralizing antibodies in opposition to rabies virus might not appear for several days after the onset of neurological sickness anti muslim viral video order 1000 mg valtrex free shipping, and they is in all probability not found earlier than dying hiv infection stages discount valtrex 1000 mg. Rabies virus antigen detection in skin biopsies taken from the nape of the neck is useful for an antemortem prognosis of rabies. Brain biopsies are solely performed sometimes and brain tissue may show attribute pathologic changes with cytoplasmic inclusions called Negri bodies, rabies virus antigen in neurons, and infectious rabies virus that may be cultured. Most rabies survivors have been immunized against rabies virus earlier than the onset of their neurological illness. Local wound cleansing is important so as to inactivate infectious rabies virus at the site of entry. Cleaning with soap and water is very helpful and using virocidal agents is important for deeper wounds. A mixture of energetic and passive immunization ought to be utilized in beforehand unimmunized people after a rabies publicity. Four doses (recently decreased from five doses) of rabies vaccine (human diploid cell vaccine or purified chick embryo cell vaccine) must be given intramuscularly in the deltoid muscle on days zero, three, 7, and 14. Radiculopathy the time period radiculopathy refers to problems involving the spinal nerve roots. Although the potential causes of injury to spinal nerve roots are quite a few, the overwhelming majority are due to spondylosis, a time period that signifies age-related degenerative modifications within the intervertebral disk, the vertebral body, the aspect joints, and factors the place they arrive into contact with each other within the backbone. Such pathological changes might outcome from the normal aging process however could also be accelerated in some individuals because of familial tendencies. In other circumstances, acute or chronic trauma could either immediately cause spinal injury to nerve roots or the spinal twine, or cause a change in alignment of the spine that accelerates the normal spondylotic adjustments of getting older. Anatomy the spinal column consists of seven cervical vertebral our bodies, 12 thoracic vertebral bodies, 5 lumbar vertebral our bodies, the sacrum (which is composed of five paired sacral neural foramina), and the coccyx. The first cervical vertebral physique (the atlas) is a ring of bone with no physique, and the second (the axis) has a bony process (the odontoid) that extends upward and round which the axis rotates. Through the neural foramina pass the spinal nerve roots, recurrent meningeal nerves, and radicular blood vessels. In whole, there are 31 pairs of spinal nerve roots: 8 cervical, 12 thoracic, 5 lumbar, 5 sacral, and 1 coccygeal. In the extraspinal region, simply distal to the intervertebral foramen, the nerve root divides into (1) a small posterior primary ramus that provides innervation to the paraspinal muscular tissues and skin of the neck and trunk and (2) a large anterior major ramus that provides innervation to the limbs and trunk, together with intercostal and belly wall muscles. Nerve roots are numbered based on their segmental location in the spinal cord, whereas neural foramina are numbered based on the 2 vertebral our bodies that body them from above and beneath. As a end result, all thoracic, lumbar, and sacral roots exit under the vertebral body of the identical quantity. Historical Aspects the affiliation of limb ache with disk protrusion and spondylosis was not clear before the middle of the 20th century. Arm ache was attributed to situations corresponding to neuritis, fibrositis, and scalenus anticus syndrome. Leg ache was attributed to disorders such as piriformis syndrome, sacral iliits, and sciatic neuropathy. In 1934, Mixter and Barr reported disk herniation as the purpose for sciatica in the lumbar region, but it was not until 1943 that Semmes and Murphey reported cervical disk herniation as the cause for radiculopathy in the absence of myelopathy. However, even into the 1950s, it was commonplace for patients to bear intersection of the scalenus anticus for remedy of signs that may now be acknowledged as basic cervical radiculopathy. Ligamentum flavum Dorsal root ganglion Dorsal ramus Ventral ramus Dura Arachnoid Pia Superior articular aspect Risk Factors and Epidemiology of Radiculopathy Posterior lengthy lig. Research concerning risk factors in low again pain is far more plentiful than for acute neck ache. Factors associated with acute neck pain include heavy lifting at work, cigarette Encyclopedia of the Neurological Sciences, Volume 3 doi:10. Risk elements for sluggish restoration from whiplash have been studied and embrace feminine gender, older age, having dependants, and not having full-time employment. Motor automobile accidents were liable for radiculopathy because of spinal fracture but not because of disk protrusion. Pathophysiology of Radiculopathy Nerve root fibers are vulnerable to the identical kinds of harm as other peripheral nerves: entrapment, compression, infiltration, necrosis, and transection. Damage could lead to focal demyelination resulting in conduction block of impulse transmission from the spinal cord to the peripheral nerves in the limb. Axon loss at the root degree leads to Wallerian degeneration along the whole course of affected nerve fibers. Both demyelinating conduction block and axon loss produce signs and neurological deficits if a enough number of nerve fibers are affected. Damage to spinal nerve roots occurs as the outcomes of degenerative change at three main points: the disk, the uncovertebral joints, and the zygapophyseal (facet) joints. Resulting bony overgrowth (osteophytes) or disk herniation at these factors may immediately impinge on spinal nerve roots or the spinal cord, or their impact may be primarily to produce instability and malalignment of the backbone that in turn produces ache and neurological sequela. One faculty of thought means that the cascade of spondylotic modifications is led by degenerative change within the nucleus pulposus of the disk. Later, cracks develop in the disk, and deposits of gas and calcification could kind. Age-related modifications also happen in the annulus fibrosus, which turns into more fibrotic and fewer elastic. As the disk shrinks and the intervertebral disk space narrows, the annulus tends to buckle out. As the disk degenerates, adjustments are seen on the vertebral physique endplates adjoining to the disk. Osteophyte production seems to slow as advancing spondylosis results in reducing spinal motion. Facet joint degeneration will not be as directly related to the beforehand talked about spondylotic adjustments, nevertheless it usually coexists. One study suggested that disk degeneration predominates at the decrease cervical ranges, whereas side joint change predominates at the higher levels. With unnatural movement of the backbone, the synovial joint bears extra structural burdens, degenerates, and develops osteophytes. Disk protrusion can give rise to different anatomical ranges of nerve root compression relying on the orientation of spinal nerve roots as they exit from the spinal wire. At the cervical ranges, spinal nerve roots exit from the spinal twine and take a comparatively straight course laterally to their neural foramina. Paramedian and lateral disk protrusions will have an result on the nerve root with the number designation of the vertebral physique slightly below the protruded disk. The roots then course down the canal as the cauda equina until they exit at their respective neural foramina. The analysis of cervical radiculopathy is supported by the presence of a history of radicular ache emanating from the neck or shoulder, with extension into the arm (sometimes in a particular dermatomal distribution). The diagnosis of lumbosacral radiculopathy is supported by radicular ache that begins within the again or buttock with radiation into the leg or foot. The diagnosis is additional supported when the symptoms are exacerbated by Valsalva maneuvers (cough, sneeze, or strain), indicating stretching of the dura at an intraspinal level of compression. Patients with lumbosacral radiculopathy may report the presence of a self-induced straight leg elevating signal: radicular symptoms within the leg occurring when sitting up straight with the legs prolonged or even when mendacity supine if the symptoms are extreme. Paresthesia and numbness are present less usually than pain and are normally nonspecific and subsequently not of great localizing worth. However, such signs are seldom present with nonradicular causes of neck and back pain. If the patient describes spinal or radicular tingling, or shock-like paresthesia with neck flexion, this provides support for dysfunction of the posterior columns of the spinal wire, not only as a result of spondylotic wire compression but additionally probably as a end result of intraspinal mass lesions or intramedullary processes corresponding to a quantity of sclerosis. The presence of bowel or bladder urgency, incontinence, new constipation, or urinary retention ensuing from cervical spinal cord compression may coexist with a quantity of cervical radiculopathies within the setting of severe cervical spondylosis. The patient might present essential information regarding the underlying cause of the symptoms. Recent or remote trauma should be explored, together with whiplash incidents, falls, and injuries throughout contact sports activities.
Syndromes
- Nausea
- Rickets
- Heart defects
- Pain in the throat
- Vomiting
- Acute viral infections
- Examine and test the child for other physical abnormalities of the kidneys, bones of the face, skull, and facial nerve
Related Products
Additional information:
Usage: t.i.d.
Tags: valtrex 500 mg buy low price, effective valtrex 1000 mg, valtrex 500 mg buy without prescription, order 1000 mg valtrex with visa, purchase valtrex 1000 mg on-line, valtrex 500 mg purchase, valtrex 1000 mg without prescription, valtrex 1000 mg buy line, buy valtrex 1000 mg line, cheap 500 mg valtrex with mastercard, 500 mg valtrex cheap with amex, valtrex 500 mg generic line, 500 mg valtrex purchase visa, 1000 mg valtrex purchase overnight delivery, 1000 mg valtrex buy with mastercard, 500 mg valtrex quality
10 of 10
Votes: 28 votes
Total customer reviews: 28
Customer Reviews
Agenak, 59 years: All these presynaptic and postsynaptic olfactory networks function collectively to form the spatial and temporal patterns of activity as olfactory input is transmitted to greater mind areas.
Fadi, 25 years: Aerobic workouts (low-resistance dynamic exercise using large muscle teams, with cardiopulmonary coaching effect) can reduce the risk of secondary ailments, psychological distress, poor sleep high quality, and lack of bone density.
Abbas, 23 years: The injection of native anesthetics or steroids in the epidural house can even ameliorate symptomatology.
Tamkosch, 39 years: Spinal wire harm or illness is another essential explanation for incontinence and is usually associated with an intact however weak external anal sphincter.
Candela, 64 years: Additional elements could precipitate hypotension in sufferers with autonomic failure.
Dargoth, 53 years: However, oblique bypass is seldom used in this setting, because the sudden lack of blood circulate is best compensated by the immediate replacement of flow.
Gonzales, 49 years: Cobalt-60 decays by way of a process referred to as beta decay to a secure isotope of nickel-60.