
Viagra Professional
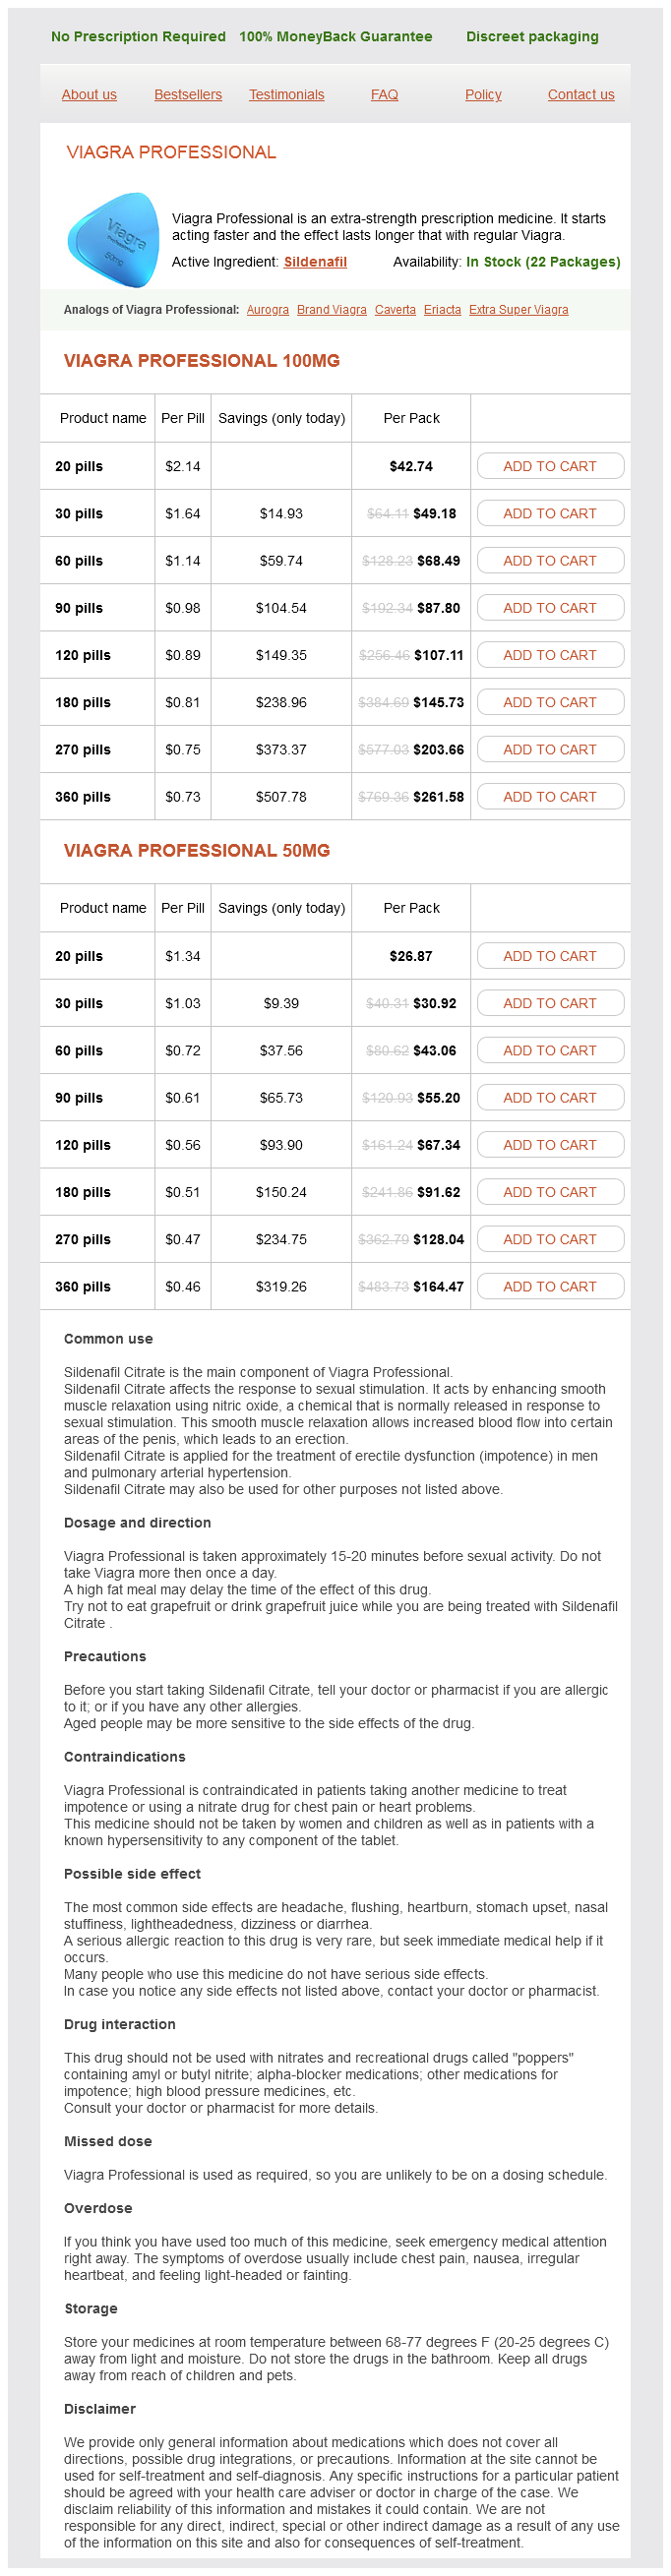
Viagra Professional 100mg
- 20 pills - $42.74
- 30 pills - $49.18
- 60 pills - $68.49
- 90 pills - $87.80
- 120 pills - $107.11
- 180 pills - $145.73
- 270 pills - $203.66
- 360 pills - $261.58
Viagra Professional 50mg
- 20 pills - $26.87
- 30 pills - $30.92
- 60 pills - $43.06
- 90 pills - $55.20
- 120 pills - $67.34
- 180 pills - $91.62
- 270 pills - $128.04
- 360 pills - $164.47
Viagra Professional dosages: 100 mg, 50 mg
Viagra Professional packs: 20 pills, 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 963
Only $0,49 per item
Description
On the opposite hand xarelto impotence viagra professional 50 mg generic online, extra-axial/ compressive tumors and certain erectile dysfunction age 50 proven 100 mg viagra professional, noninfiltrative intraaxial tumors only displace the adjoining pathways erectile dysfunction in young age purchase viagra professional 100 mg fast delivery, hence these may be preserved throughout removal of the lesion erectile dysfunction quick fix buy discount viagra professional 50 mg online. A, Coronal T2-weighted picture demonstrates a big hyperintense mass in the best frontal lobe, with associated hyperintense vasogenic edema and mass effect. A smaller mass lesion with similar signal characteristics is present on the gray/white junction in the left frontal lobe. Note surrounding rim of hypointensity, indicating hemosiderin deposition within these hemorrhagic metastases. B, On gradient echo, hypointense blood degradation merchandise are properly seen throughout the metastases. The technological advances allowing for speedy acquisition of data have led to 4D imaging, the place full 3D information sets of the brain are serially obtained over very brief time intervals, allowing for larger temporal and spatial resolutions in brain perfusion studies of acute ischemic stroke sufferers. Blurring of the contours of the deep grey matter structures is of similar significance. In people, the hyperintense sign indicating restriction of diffusion is detected within minutes after onset (Hossmann and HoehnBerlage, 1995). There is hypodensity in the corresponding area of the left hemisphere, demonstrating the evolving ischemic infarct. A, On diffusion-weighted imaging, a hyperintense area of restricted diffusion is seen in the proper medial frontal lobe, involving the territory of the anterior cerebral artery. A, On diffusion-weighted imaging, a hyperintense area of restricted diffusion is seen in the territory of the left middle cerebral artery. Note evolving mass effect on the sulci and left lateral ventricle and the mild midline shift. B, On apparent diffusion coefficient map, corresponding hypointensity is seen in the same area. A, On diffusion-weighted imaging, a hyperintense area of restricted diffusion is seen in the left medial occipital lobe, involving the territory of the posterior cerebral artery. These sequences together verify the diagnosis of ischemia, decide its extent, and permit for an approximate estimation of the time of onset (Srinivasan et al. This reaches a nadir at 3 to 5 days but remains significantly low till the seventh day after onset. After this time, the values improve (the sign will get increasingly hyperintense) and return to the baseline values in 1 to 4 weeks (usually in 7 to 10 days). On diffusion-weighted imaging, a hyperintense area of restricted diffusion is seen within the left frontal lobe, involving the watershed zone between the anterior and center cerebral artery. In a analysis setting, computing the numerical values of hyperintensity in infarcted tissue on serial T2-weighted scans can show a consistent sharp signal enhance after 36 hours, distinguishing lesions younger or older than 36 hours. If the extent of diffusion and perfusion abnormalities is similar or the same, the tissue is assumed to be irreversibly injured, with no penumbra, and due to this fact the potential profit from reperfusion therapy is most likely not high enough to justify the risk of hemorrhage related to thrombolytic treatment. Cytotoxic edema is normally maximal 2 to 3 days after onset, however within the case of malignant center cerebral artery strokes, it might keep increasing till day 5. A, Diffusion-weighted picture reveals a small, circumscribed space of restricted diffusion in the paraventricular region of the proper centrum semiovale (arrow). B, Magnetic resonance perfusionweighted picture demonstrates a much bigger perfusion deficit, as revealed by elevated mean transit time, indicated in purple. The perfusion deficit (red) outside the small space of restricted diffusion (arrow, A) represents the ischemic penumbra. Reperfusion often occurs at this stage and may be related to petechial hemorrhages or even frank hemorrhage throughout the infarcted tissue. Diagnostic analysis and treatment of a patient with stroke, as properly as secondary stroke prevention, is often dependent upon structural imaging. Other Cerebrovascular Occlusive Disease Microvascular Ischemic White Matter Lesions, "White Matter Disease," Binswanger Disease. The terms microvascular ischemic changes or persistent small vessel disease are frequently used to describe these lesions on imaging research. Certain hyperintense signal modifications are thought-about normal incidental findings, with no clinical relevance. A uniformly skinny, linear, T2 hyperintensity that has a smooth outer border alongside the border of the physique of the lateral ventricles is commonly seen within the aged population and sure represents fluid or gliotic modifications within the subependymal zone. It tends to be extra pronounced at the suggestions of the frontal horns (ependymitis granularis). This discovering is thought potentially to be due to focal loss of the ependymal lining with gliosis and/or influx of interstitial fluid into these regions. Patchy sign adjustments inside the white matter of the cerebral hemispheres beyond a relatively low threshold (generally, one white matter hyperintensity per decade of life is felt to fall within the normal range) are pathological and are mostly of ischemic origin. According to the most accepted hypothesis, these hyperintensities are the results of gradual narrowing or occlusion of the small vessels of the white matter, the diameters of that are lower than 200 micrometers (hence the terms microvascular lesions or small vessel disease). The lumen of the concerned vessels is slim or occluded; their partitions could exhibit arteriosclerotic changes and generally amyloid deposits. They are typically associated with a point of central atrophy, which tends to worsen with larger lesion hundreds. The distribution of these lesions adjustments only very gradually on serial scans, often displaying minimal to no significant distinction on research spaced several years apart. [newline]While age by itself can cause such adjustments, and the incidence of those lesions increases with age in folks forty years or older, there are several other danger factors that can make them extra quite a few. Indeed, patients with these medical issues usually tend to have an elevated variety of ischemic white matter lesions. It is feasible that only lesions visible on T1-weighted images may be clinically vital. As the infarcted tissue is disintegrating and resorbed, the T1 hypointensity and T2 hyperintensity of the lesion turn into extra marked. Gray matter enhancement (which in the case of infarcted cortex has a gyriform pattern) is intense throughout this stage. Tissue within the margins of the cavitary lesion, and sometimes in different areas of the mind as nicely, may have undergone intensive neuronal loss ensuing only in atrophy however not in signal depth changes, even on T2-weighted pictures (partial infarction). Besides sign modifications, persistent ischemic infarcts result in secondary changes in the mind. Later, the hyperintensity could resolve, however the lack of pathways may lead to quantity lack of the structures they cross by way of. Areas of gliosis seem as faint zones of hypointensity (for the image, see on-line model of this chapter). Watershed ischemic stroke entails the border zones between the vascular territories of the main cerebral arteries. Deep border zone infarcts develop between the superficial and deep branches of a cerebral artery. Bilateral, roughly symmetrical watershed infarcts end result from global cerebral hypoperfusion brought on by heart failure, hypoxia or hypoglycemia. Thromboembolic stroke outcomes from occlusion of one or more major cerebral arteries or their branches by a blood clot. The occlusion may be as a result of in situ thrombus formation or embolization from a distant source. Emboli can be of cardiac origin, however they could also be the outcome of artery-to-artery embolization, generally as a outcome of carotid or aortic arch atherosclerotic disease. Unilateral anterior strokes are sometimes because of embolization from the proximal inside carotid artery, a preferential website for atherosclerotic plaque formation. Likewise, unilateral embolic stroke in the posterior circulation necessitates analysis of the vertebrobasilar system. Multiple, especially bilateral, cortical ischemic strokes virtually at all times suggest an embolic origin. In addition, there are intensive hyperintense sign adjustments in the hemispheric white matter. Some of those are confluent, near the ventricular borders, others involve the external capsules or are scattered in different regions of the white matter. Reperfusion harm is a common phenomenon in embolism, and in this stroke sort, hemorrhagic transformation of varying degree is commonly seen. Lacunar ischemic strokes represent 20% to 25% of all strokes and are usually seen in patients with hypertension and diabetes. This stroke type is assumed to be due to narrowing and in situ thrombosis of the small, deep-penetrating arteries such as the lenticulostriate arteries.
SPLEEN POLYPEPTIDES (Spleen Extract). Viagra Professional.
- Dosing considerations for Spleen Extract.
- Infections, enhancing immune function, skin conditions, kidney disease, and rheumatoid arthritis.
- How does Spleen Extract work?
- What is Spleen Extract?
- Are there safety concerns?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96976
This syndrome has also been described as "pure akinesia" and "primary progressive freezing of gait erectile dysfunction vacuum pump medicare viagra professional 50 mg cheap on-line. Follow-up research point out this can be one expression of progressive supranuclear palsy (Riley et al impotence 60 years old cheap 100 mg viagra professional with mastercard. Others complain of a lack of the traditional fluency of stepping when walking and a conscious effort is required to maintain a traditional stepping rhythm and step dimension erectile dysfunction doctors in louisville ky viagra professional 50 mg with amex. These signs could also be associated with refined dysequilibrium erectile dysfunction medication side effects viagra professional 50 mg buy without a prescription, manifesting as a few transient staggering steps to one side or a couple of steps of retropulsion after standing up, turning shortly, or making different fast adjustments in physique place. Finally, some aged patients expertise severe walking difficulties that resemble those described in frontal lobe illness. The historical past in these syndromes is one of gradual onset, without stroke-like episodes or identifiable structural or vascular lesions of the frontal lobes or cerebral white matter on imaging. Falls lead to a marked lack of confidence when strolling and a cautious or protected gait. A cautious gait is a traditional response to the notion of impaired or threatened stability and a concern of falling. They may be unable to walk with out support, holding onto furnishings, leaning on walls, and avoiding crowded or open areas because of a fear of falling. Accordingly, a cautious gait should be interpreted as compensatory and never specific for any degree of the gait classification. A formal program of gait retraining might assist restore confidence and enhance the ability to stroll. Such signs are related to the development of phobic avoidance behavior and the syndrome of phobic postural vertigo (Brandt, 1996). Prolonged illusory swaying and unsteadiness after sea or air travel is referred to because the mal de d�barquement syndrome. These signs have to be distinguished from the physiological "vertigo" and unsteadiness accompanying visual-vestibular mismatch or battle when observing shifting objects, focusing on distant objects in a large panorama, or wanting upward at a moving object. The slower speed of strolling is related to shorter and shallower steps with lowered excursion at decrease limb joints. In addition, stance width could also be barely wider than regular, and synergistic associated arm and trunk actions are less vigorous. Factors contributing to a general decline in mobility of the aged embody degenerative joint disease, lowering vary of limb movement, and decreased cardiovascular health, limiting exercise capability. These modifications in the elderly gait sample provide a more secure base to compensate for a refined age-related deterioration in stability. In unselected aged populations, a extra pronounced deterioration in gait and postural management could also be seen. Walking speed is slower, steps are shorter, stride size is decreased, stance section of strolling is elevated, and variability in stride time is elevated. Elderly sufferers with an insecure gait characterised by sluggish short steps, en bloc turns, and falls typically have signs of a number of neurological deficits, such as (1) gentle proximal weak spot of neuromuscular origin, (2) subtle sensory loss (mild distal mild touch and proprioceptive loss, blunted vestibular or visible function), (3) gentle spastic paraparesis as a end result of cervical myelopathy, and (4) impaired truncal control as mentioned earlier with none one lesion being extreme enough to clarify the walking difficulty. The cumulative effect of these multiple deficits could account for perceived instability and dysequilibrium. Musculoskeletal problems, postural hypotension, and loss of confidence (especially after falls) are further elements contributing to a cautious gait pattern. In this situation, mind imaging is efficacious to look for frontal and periventricular white-matter ischemic lesions that correlate with imbalance, increased physique sway, falls, and cognitive decline (Baezner et al. Such patients make inappropriate actions of the ft and trunk when sitting or standing with out due warning or monitoring of physique posture. The most hanging examples occur in frontal dementias such as progressive supranuclear palsy and frontotemporal dementias in which impulsivity and a failure to adapt to the precarious steadiness are part of the cognitive decline. The typical gait patterns encountered embrace: transient fluctuations in posture whereas strolling, knee buckling without falls, excessive slowness and hesitancy, a crouched, stooped or different irregular posture of the trunk, 5. GaitDisorders 261 the extra acrobatic hysterical issues of gait indicate the extent to which the nervous system is functioning normally and capable of high-level coordinated motor expertise and postural control to perform complex maneuvers. Suggestibility, variability, improvement with distraction, and a historical past of sudden onset or a rapid, dramatic, and full restoration are common options of psychogenic gait (and movement) disorders normally. A classical discrepancy is illustrated by the Hoover signal within the patient with an apparently paralyzed leg when examined supine. As the affected person lifts the conventional leg, the examiner places a hand underneath the "paralyzed" leg and feels the presence (and strength) of synergistic hip extension. The general neurological exam typically reveals a big selection of different indicators suggestive of psychogenic origin corresponding to "give means weak spot" and nonphysiological sensory disturbances. One have to be cautious in accepting a prognosis of hysteria, nonetheless, as a result of a weird gait could additionally be a presenting characteristic of primary torsion dystonia, and unusual truncal and leg postures could also be encountered in truncal and leg tremors. Finally, higher stage gait problems usually have a disconnect between the standard neurological exam and the gait sample. Lumbosacral vertebral abnormalities (spina bifida), bony foot deformities, and a cutaneous hairy patch over the lumbosacral area are clues to the prognosis. In grownup life, spinal dysraphism (diastematomyelia with a tethered cord) could first turn out to be symptomatic after a again injury, with the event of walking difficulties, leg and lower again ache, neurogenic bladder disturbances, and sensory loss in a leg. Limitation of the range of joint movement at the hip, knee, or ankle to cut back ache results in quick steps with a fixed leg posture. Hip disease causes a wide range of gait changes; it is necessary to look at the range of hip movements (while supine) and any related pain during passive movements of the hip in a patient with a gait dysfunction. Pain as a outcome of intermittent claudication of the cauda equina is most commonly brought on by lumbar spondylosis and, rarely, by a spinal tumor. It may be troublesome to distinguish this syndrome from calf muscle claudication secondary to peripheral vascular disease. Examination after train could resolve the problem by revealing a depressed ankle jerk or radicular sensory loss, with preservation of arterial pulses within the leg. Other painful situations affecting the backbone, lower limbs, and delicate tissue, similar to plantar fasciitis, can have an effect on gait. Leg shortening with limping in childhood could be the presenting feature of hemiatrophy because of a cerebral or spinal lesion or spinal dysraphism. Examination of the legs may reveal decrease motor neuron signs, sensory loss with trophic ulcers of the feet, and occasionally, higher motor neuron indicators such as a brisk knee GaitDisorders 261. Assessing the temporal relationship between cognition and gait: slow gait predicts cognitive decline in the Mayo Clinic examine of getting older. Executive function and falls in older adults: New findings from a five-year prospective study link fall threat to cognition. The syndrome of "pure akinesia" and its relationship to progressive supranuclear palsy. Integrating sensory info into the planning stage, neurons of the premotor cortex project broadly to targets including motor cortex, prefrontal cortex, parietal cortex, supplementary motor cortex space, basal ganglia, thalamus, and spinal twine. Output from the primary motor cortex descends through the interior capsule to the brainstem and spinal cord because the pyramidal tract. Pyramidal Tract Pyramidal tract axons turn into the corticobulbar and corticospinal tracts. Most of the descending axons cross in the brainstem to activate contralateral cranial nerve nuclei or descend into the spinal cord in the lateral corticospinal tract. A minority of the motor axons descend in the spinal twine uncrossed in the anterior corticospinal tract where a few of these axons cross before they provide contralateral motoneurons. Descending corticospinal pathways via the interior capsule are topographically organized although not as precisely as within the motor cortex. Within the inner capsule, the corticospinal tracts are generally in the posterior limb, with the face and arm axons anteriorly and the leg axons posteriorly. As the corticospinal axons descend via the spinal wire, the presence of crossed and uncrossed axons makes for complicated effects of lesions on motor function. Hemiplegia and monoplegia are more probably to be because of discrete focal lesions than diffuse lesions, so these presentations are especially suited to clinical-anatomic localization. Similarly, imaging research are likely to be revealing with hemiplegia or monoplegia but the focus of imaging have to be directed by scientific suspicion. Hemiplegia and monoplegia are motor symptoms and signs, but related sensory abnormalities are important to localization, so these are discussed when applicable. Differentiation is made among the many following distributions: � � � � Generalized weak point Monoplegia Hemiplegia Paraplegia.
Specifications/Details
As a results of advances in laboratory know-how impotence psychological viagra professional 50 mg discount free shipping, genetic erectile dysfunction jelqing cheap viagra professional 50 mg amex, immunological erectile dysfunction doctors mcallen texas buy viagra professional 100 mg low price, and other blood exams are expanding the ability of clinicians to confirm the prognosis of an growing number of neurological issues erectile dysfunction injections trimix 50 mg viagra professional buy with amex, obviating extra invasive studies. In general, older, more invasive tests are now used for remedy somewhat than diagnostics. The neurologist must know enough about each laboratory test to request it appropriately and to interpret the outcomes intelligently. Tests ought to be used to diagnose and treat disease, not to protect in opposition to litigation. When used judiciously, laboratory investigations serve both purposes; when ordered indiscriminately, they serve neither. The doctor should present full clinical data and highlight the questions for which solutions are being sought from the investigations. The electrophysiologist will look extra fastidiously for evidence of denervation in a sure myotome if the patient has a syndrome suggesting herniation of that disk. The neuroradiologist will obtain extra views to seek for evidence of a posterior speaking artery aneurysm if the neurologist reviews a 3rd nerve palsy in a affected person with subarachnoid hemorrhage. It also is necessary to know the characteristics of the normal inhabitants used to standardize a laboratory take a look at. Ranges that have been normalized using adults are virtually by no means right for newborns and children. Ranges normalized utilizing a hospitalized inhabitants may not be correct for ambulatory folks. In most situations, the actual imaging research must be reviewed along with the report, and when acceptable, the neuroradiologist should participate. Similarly, for neurologists skilled in pathology, biopsy findings may be reviewed with the neuropathologist. The neurologist who is aware of the patient may be of nice assist in interpreting imaging or pathological studies. The diagnostic capability of two tests will not be similar, and the costlier check is probably not better. The price of a take a look at have to be thought of within the context of the entire cost of the sickness. The selection of laboratory tests and the sequence by which carried out are essential parts of good medical apply. Risk-to-Benefit Analysis the neurologist makes judgments concerning the risk-to-benefit ratio of checks every single day. The following examples may help make clear the ideas used in making these choices. In the case of an increasing infratentorial lesion, it might trigger the cerebellar tonsils to herniate through the foramen magnum and compress the cervicomedullary junction (see Chapter 62). These embrace thrombosis of the artery at the web site of puncture, dissection of the vessel wall, allergic reactions to distinction, and cerebral infarction from thrombosis, embolism, or dissection. The likelihood that a affected person being thought of for cerebral arteriography will expertise a particular complication is influenced by patient-specific components including age and the presence of arteriosclerosis and other diseases. These patient-specific possibilities of threat must be balanced towards the potential advantages the angiographic info may provide, specifically the chance of demonstrating a treatable situation. The chance of risk additionally varies with the ability, experience, and judgment of the doctor performing these procedures. As such, the neurologist requesting invasive procedures ought to have an accurate estimate of the physician-specific risk elements. The final determination might want to consider the combined threat probabilities, together with each patient- and physician-specific elements. Carotid Doppler ultrasound and transcranial Doppler research may be as reliable as angiography for demonstrating extracranial occlusive illness. The general health of the patient is a vital consideration in the choice process for noninvasive versus invasive strategies. The four main conditions during which a brain biopsy could also be thought of are intraparenchymal brain tumor, intraparenchymal infectious lesion, cerebral vasculitis, and in particular circumstances, cerebral degenerative illness. The risk-to-benefit evaluation is influenced by the provision of computerassisted stereotactic know-how to get hold of a biopsy via a burr hole, lowering the danger of acquiring tissue for pathological and bacteriological research. Hemorrhage, infection, post-biopsy epileptic seizures, and the manufacturing of a neurological deficit are the primary dangers related to the process. The risk of a everlasting neurological deficit is reduced if the biopsy specimen is from certain areas of the brain, such as the Cerebral Arteriography the question of whether or not to request percutaneous cerebral arteriography (see Chapter 40) entails evaluation of the risks and advantages for every affected person. In a patient with cerebrovascular disease, the study might present thrombotic or embolic occlusion of arteries and abnormalities of the arterial wall, including arteriosclerotic plaques, fibromuscular hyperplasia, medial dissection, and arteritis. Considerations within the differential prognosis included Alzheimer disease, Creutzfeldt�Jakob illness, cerebral vasculitis, and cryptococcal meningitis. The evaluation suggests that arteriography is justified to look for a vasculitis, but the lumbar puncture revealed cryptococcal meningitis before angiography was performed. The process carries a excessive risk of worsening the neurological deficit (unless that deficit is already total) if the lesion is positioned within the sensorimotor cortex, the Broca speech space, the internal capsule, or optic radiations. The treatability of the attainable reason for the disease is the crucial profit to contemplate within the risk-to-benefit evaluation. If the neuroimaging examine suggests a malignant glioma, for which remedy is prone to be ineffective, biopsy alone is in all probability not considered justified, though resection and tissue prognosis could be. If it suggests a main lymphoma of the brain, which is prone to respond to radiotherapy, then confirmatory biopsy alone could additionally be recommended. Cost-to-Benefit Analysis Cost-to-benefit evaluation usually presents the doctor with an ethical dilemma. Where solely restricted funding is available for well being care, the money must be used to buy essentially the most cost-effective look after the best number of folks. Clearly, physicians ought to acquaint themselves with the prices of the tests they order and follow cost-effective medication. For instance, a patient on a statin treatment who experiences gradual-onset muscle weak point and myalgias would be higher served by stopping the drug and observing whether or not the muscle symptoms resolve, rather than immediately performing a muscle biopsy. If a check may be very delicate but has poor specificity, it is probably not useful for diagnosis. The acetylcholine receptor antibody titer is raised in solely about 60% of sufferers with myasthenia gravis, for example, but very hardly ever in normal individuals or those with other circumstances. The specificity and sensitivity can be helpful to quantitate the extent to which a check outcome makes a diagnosis of the disease kind of probably. Once the institutional review board provides permission for a analysis project, it continues to monitor the research to be positive that the research conforms to the protocol. In a educating hospital, the attending or advisor doctor is legally and ethically liable for the care supplied to a patient by physicians in training. The attending neurologist must ensure that every investigation is justified for diagnostic and management purposes. All physicians are legally and ethically certain to be sure that the patient understands the reason for every investigation and gives informed consent. The neurologist in training must learn to use tests judiciously and never perform them merely for curiosity or training. The two-way discussion with more senior neurologists about the rationale, risk-to-benefit ratio, and cost-to-benefit ratio of every investigation is a vital a part of the training process. Results of such checks should be stored separate from the remainder of the chart to maintain strict confidentiality for the patient. When possible, due to this fact, laboratory investigations are used to measure the response of the illness to therapy. Laboratory investigations often are quantitative and could also be helpful in managing illness. Generally, abnormal laboratory values return toward normal as a disease resolves or become more and more abnormal because it worsens. The important capacity in a patient with Guillain� Barr� syndrome is an instance of a measurement that improves as the disease improves. Other limitations on the utilization of laboratory tests to monitor illness progression embrace sampling errors and check sensitivity and specificity. They could be as easy as visual acuity measurement, what number of serial numbers from 1 to 100 a affected person can depend on a single breath, or the frequency and severity of headaches every month. Alternatively, they can be refined measurements such because the force of most voluntary muscle contraction or the temperature perception threshold for an area of skin. Quantitative measures of neurological perform permit much better evaluation of the response of a illness to remedy than does the routine neurological examination.
Syndromes
- Bulging tissue through the surgical cut, called an incisional hernia
- You have hepatitis C and develop symptoms of cryoglobulinemia
- Infant cereals and other iron-fortified cereals
- Hyperkalemia
- Skin contact
- Headache
Related Products
Additional information:
Usage: p.r.n.
Tags: viagra professional 50 mg cheap with amex, order viagra professional 100 mg overnight delivery, effective 50 mg viagra professional, viagra professional 50 mg cheap with mastercard, discount viagra professional 50 mg visa, buy viagra professional 100 mg free shipping, buy viagra professional 50 mg with amex, cheap viagra professional 50 mg fast delivery, buy viagra professional 100 mg low cost, cheap viagra professional 100 mg with amex, viagra professional 100 mg online buy cheap, purchase 100 mg viagra professional, generic viagra professional 50 mg overnight delivery, buy 100 mg viagra professional visa, viagra professional 50 mg purchase with visa, viagra professional 100 mg discount online
8 of 10
Votes: 82 votes
Total customer reviews: 82
Customer Reviews
Grim, 36 years: Differential prognosis of parkinsonian syndromes utilizing F-18 fluorodeoxyglucose positron emission tomography.
Makas, 40 years: Some essential points within the differential analysis with such displays are considered subsequent.
Masil, 62 years: In patients youthful than 45 years of age, the most common etiological disorder is disk disease.