
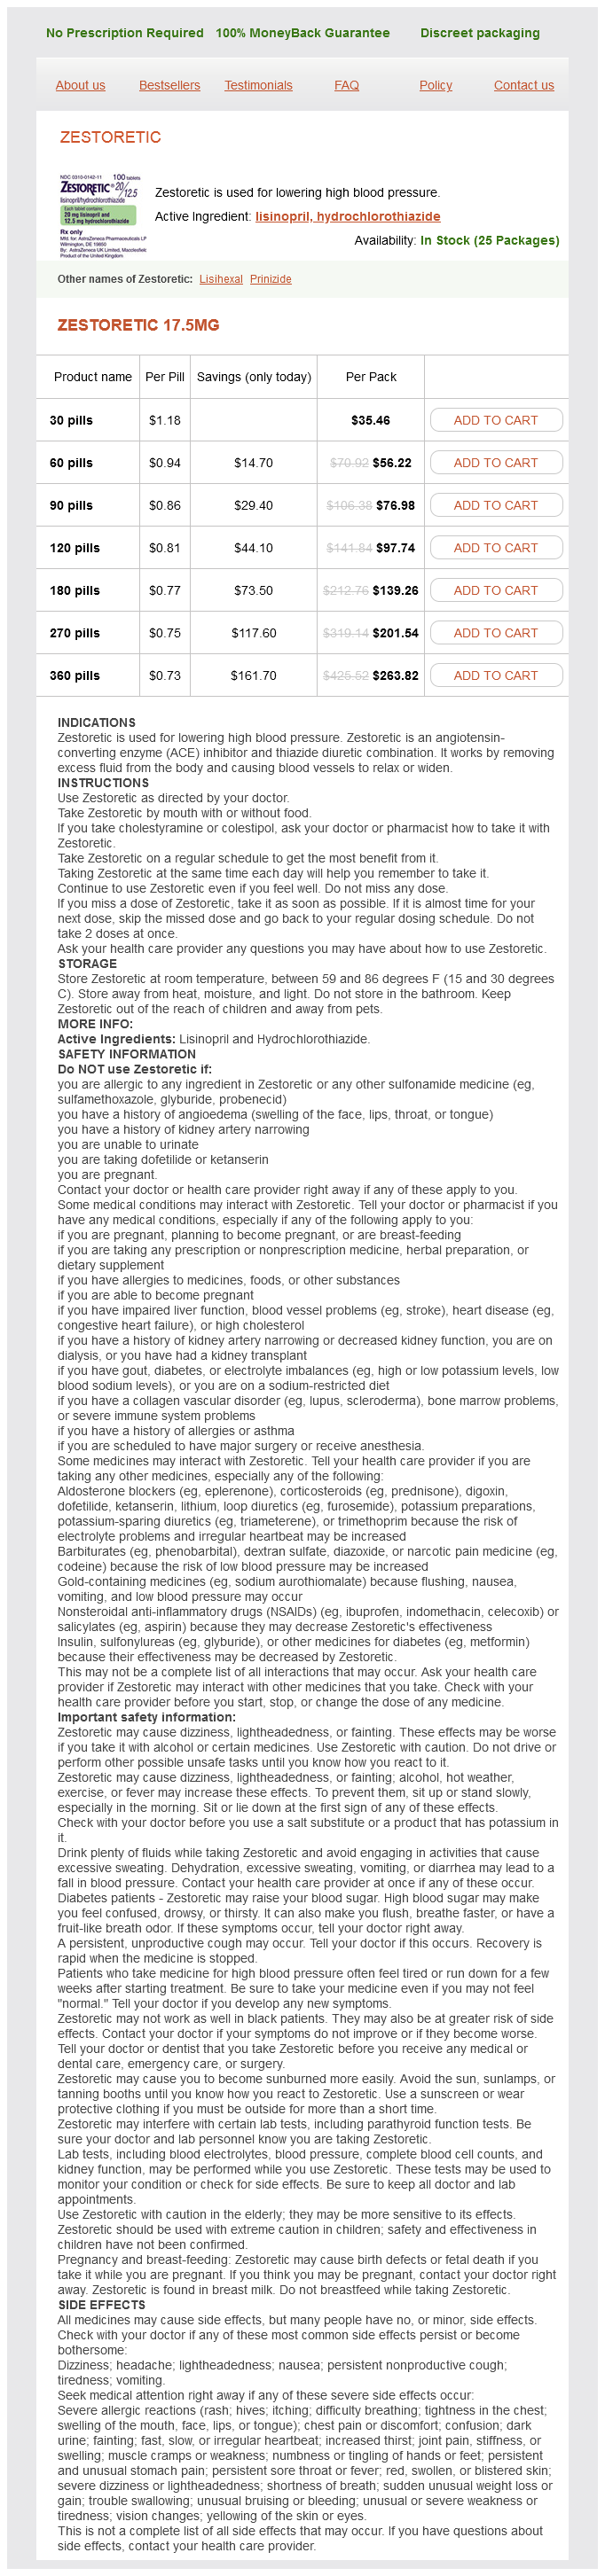
Zestoretic
Zestoretic 17.5mg
- 30 pills - $35.46
- 60 pills - $56.22
- 90 pills - $76.98
- 120 pills - $97.74
- 180 pills - $139.26
- 270 pills - $201.54
- 360 pills - $263.82
Zestoretic dosages: 17.5 mg
Zestoretic packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 532
Only $0,78 per item
Description
Other much less common associations with transposition of the nice vessels embrace tricuspid atresia and straddling atrioventricular valves prehypertension birth control pills generic zestoretic 17.5 mg on-line. If undiagnosed hypertension erectile dysfunction buy zestoretic 17.5 mg with mastercard, these sufferers may present later with overt coronary heart failure caused by pulmonary overcirculation high blood pressure medication and xanax discount zestoretic 17.5 mg online. Patients with significant subpulmonary obstruction could have physiology more much like arteria facialis buy cheap zestoretic 17.5 mg online that of tetralogy of Fallot and present with varying degrees of cyanosis. Finally, patients with coarctation or arch obstruction may current with acidosis, shock, and reverse differential cyanosis. This often consists of the initiation of prostaglandins and a balloon atrial septostomy. For unstable patients, restricted echocardiography ought to be carried out to verify the analysis of transposition and evaluate the atrial septum to decide whether a restrictive atrial septum is current. Beyond these initial requirements, a whole echocardiogram should focus on delineating the conotruncal anatomy, defining the coronary origins and proximal course, the patency, dimension and shunting of the ductus arteriosus, the presence and sort of a ventricular septal defect, the presence of subarterial (usually subpulmonary) obstruction, and the aortic arch. In addition to defining the coronary anatomy, the precise relationship between the aorta and pulmonary artery ought to be delineated, as a extra aspect by aspect relationship of the nice vessels could make a Lecompte maneuver less desirable. Any questions left unanswered after full echocardiography may be obtained by cardiac magnetic resonance imaging. Imaging Techniques and Findings Radiography the basic radiographic findings of transposition of the good arteries include a narrow superior mediastinum (socalled egg on a string) caused by the anteroposterior orientation of the great vessels and inapparent thymus, elevated pulmonary vascular markings, and cardiomegaly. Patients with an intact ventricular septum will usually present with profound cyanosis in the first few hours to days of life because the ductus arteriosus closes and mixing is restricted to the patent foramen, which is commonly restrictive. If the foramen ovale is restrictive, these sufferers may require a balloon septostomy to enhance left to proper shunting. Ultrasound Echocardiography can typically readily identify all of the pertinent anatomic findings to manage sufferers with transposition of the great arteries. Subcostal imaging can readily establish the pulmonary artery arising from the left ventricle and the aorta arising from the best ventricle. The aorta can normally be identified by the coronaries and by its lengthy size before branching. Note that the pulmonary arteries are draped over the aorta and, on this case, the right pulmonary artery is mildly stretched and narrowed. The pulmonary arteries are usually brought anteriorly and draped over the aorta. The coronary arteries are transferred separately with buttons of tissue from the aorta to avoid ostial stenosis. Cine and velocity mapping can be used successfully to outline regions of stenosis and quantify the diploma of acceleration. Three-dimensional gadolinium sequences may also be useful to define stenoses and their relationships to different buildings. Unilateral or sometimes bilateral branch pulmonary artery stenosis might happen from stretching the branch pulmonary arteries after the Lecompte maneuver. Through-plane velocity mapping can be utilized to quantify the diploma of insufficiency of the valves exactly. Furthermore, shortaxis cine volume sets can quantify the ventricular measurement, ejection, and wall movement abnormalities to screen for the effects of valve regurgitation or coronary abnormalities. Whole heart sequences can be used to evaluate for ostial stenosis of the transferred coronaries. Gadolinium perfusion imaging is usually performed at relaxation and through adenosine administration. Adenosine administration causes coronary vasodilation and accentuates perfusion abnormalities by "stealing" flow from areas of marginal coronary perfusion. Stenosis of the left pulmonary artery is widespread and, hardly ever, isolation of the pulmonary artery contralateral to the aortic arch could happen. Manifestations of Disease Clinical Presentation the presentation of these sufferers largely is determined by the degree of outflow tract obstruction. Patients with extreme obstruction present in the newborn interval with profound cyanosis. Moderate obstruction could lead to a relatively balanced circulation and, if not recognized prenatally, could additionally be observed during routine evaluation for a murmur. Patients with solely gentle outflow obstruction will current with a big left to proper shunt, pulmonary overcirculation, and heart failure. Patients with moderate obstruction could also be at risk for hypercyanotic spells ("tet spells"), that are brought on by dynamic will increase in the diploma of right ventricular outflow tract obstruction, changes in the ratio of pulmonary to systemic vascular resistance, or a combination of the 2. Imaging Indications and Algorithm Cyanotic newborns suspected of getting tetralogy of Fallot ought to have prostaglandins initiated. A transient confirmatory echocardiogram may be obtained while that is being done, if available. As soon because the affected person is stable, a complete echocardiogram should present the information needed for initial management and surgical planning. Prevalence and Epidemiology the incidence of tetralogy of Fallot is roughly 4 in 10,000 stay births, accounting for about 7% to 10% of circumstances of congenital coronary heart disease. It happens generally in association with genetic defects, including Down syndrome, DiGeorge syndrome (22q11 microdeletion), and Alagille syndrome (Jag1 mutation). Other findings may range from a standard coronary heart size and decreased pulmonary blood flow to an increased coronary heart size and elevated pulmonary blood move, depending on the degree of obstruction. Certain related situations could additionally be essential to the administration of tetralogy of Fallot. Gadolinium angiography can additionally be helpful to define aortopulmonary collaterals, and has been shown to be as efficient as conventional angiography. In addition, left ventricular efficiency might decline, probably secondary to interactions with the left ventricle. This view is used to help in setting up the short-axis stack to define the basal and apical slices. Angiography Angiography performs a limited position within the routine evaluation of tetralogy of Fallot. Selective aortic or coronary angiography may be useful for choose patients with major aortopulmonary collaterals or uncommon coronary patterns when the noninvasive photographs are inadequate. There are two major classification schemes in use- these of Collett and Edwards14 and Van Praagh. The following are the definitions used within the Van Praagh classification with its differences and similarities with the Collett and Edwards classification noted; the Van Praagh classification takes into consideration aortic arch anomalies. A complete axial stack can precisely quantify ventricular volumes, mass, and ejection to assist in the timing of valve substitute. Time Type 1A-proximal single arterial trunk with a distal main pulmonary artery segment, which is similar to Collett and Edwards kind I. Type 2A-left and proper branch pulmonary arteries originate from the trunk individually, with no main pulmonary phase present. Type 3A-the origin of one pulmonary branch artery is truncal and the contralateral artery is ductal or aortic in origin, or that lung is provided entirely by collaterals. Type 4A-large ductus arteriosus supplying the descending aorta, with a coexisting hypoplastic or interrupted aortic arch (usually type B) supplying the innominate arteries. The DiGeorge syndrome and patients with microdeletion of chromosome 22 have a excessive incidence of getting truncus arteriosus. The truncus is often divided into the aorta and pulmonary artery by two ridges that appear within the 4- to 5-week-old embryo and that grow toward the midline. Cells from the neural crest instantly contribute to this septation; one of many leading theories is that this malformation is a disruption in neural crest migration. Van Praagh and Van Praagh, nevertheless, believed this to be a type of tetralogy of Fallot. Manual or automated strategies can be utilized to segment out solely the pulmonary artery cross section. The flows in every pixel throughout the vessel are then summed to get hold of the move for that picture. The whole reverse and complete forward flows can thereby be calculated, and the regurgitant fraction decided by dividing the reverse move by the forward circulate (35% on this example). The pulmonary arteries are not often obstructed, so the pulmonary vascular mattress is immediately uncovered to systemic arterial stage pressures just like these of a big isolated ventricular septal defect with left to right shunting. However, in contrast to the ventricular septal defect, the pulmonary mattress is uncovered to systemic diastolic pressures as properly, rising the left to proper shunt and appearing as a runoff lesion just like that of a patent ductus arteriosus. The valve could have a variable variety of leaflets, although the most typical is trileaflet; quadricuspid valves have been reported in 9% to 24% and bicuspid valves have been reported in 6% to 23%.
Filipendula (Meadowsweet). Zestoretic.
- Bronchitis, heartburn, upset stomach, ulcers, gout, joint problems, bladder infections, and other conditions.
- What is Meadowsweet?
- How does Meadowsweet work?
- Are there safety concerns?
- Are there any interactions with medications?
- Dosing considerations for Meadowsweet.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96150
Incomplete double aortic arch with atresia of the distal left arch: distinctive imaging look arteria epigastrica cranialis superficialis zestoretic 17.5 mg buy with amex. Innominate artery compression of the trachea: prognosis and remedy by anterior suspension arteriovascular malformation 17.5 mg zestoretic purchase with visa. Use of imaging for assessing anatomical relationships of tracheobronchial anomalies related to left pulmonary artery sling arrhythmia 200 bpm 17.5 mg zestoretic cheap amex. Magnetic Resonance Imaging of the Aorta and Left Ventricular Function in Inherited and Congenital Aortic Disease Heynric B blood pressure study zestoretic 17.5 mg cheap amex. Passing blood from the heart to the limbs and main organs is one functional side of the aorta; of equal importance is its capacity to distend and to recoil in response to pulsatile move, thereby reducing afterload for the left ventricle and facilitating diastolic perfusion of the coronary arteries. The elastic lamina of the aortic media provides structural help and elasticity to the aorta. In sufferers with a standard tricuspid valve (A), fibrillin 1 microfibrils tether clean muscle cells to adjoining elastin and collagen matrix components. In patients with bicuspid aortic valve (B), deficient microfibrillar components result in easy muscle cell detachment, matrix metalloproteinase release, matrix disruption, cell death, and lack of structural assist and elasticity. Both decreased elasticity and dilation of the aorta have a detrimental effect on aortic valve function, particularly if the aortic valve is already structurally malformed by being bicuspid or quadricuspid. This results in increased systolic blood strain and pulse strain, Pathophysiology and Follow-up Aortic dilation is the most typical cause of morbidity and mortality in patients with Marfan syndrome as dilation of the sinus of Valsalva is found in 60% to 80% of grownup sufferers. Dilation of the mid ascending aorta is mostly present (70%) and is associated with aortic valve stenosis, suggesting a post-stenotic causative mechanism. Note the mix of the slitlike bicuspid aortic valve with slit flow (A, B) and post-stenotic dilation that measured 4. Shaded floor full quantity rendering show image (A) and chosen volume rendering show image (B). Flow speed was significantly elevated on the degree of stenosis at residual coarctation or recoarctation (arrow, A, B). This signifies move decrease from the proximal to the distal descending thoracic aorta that excludes hemodynamically significant collateral circulate. The affected person has slight aortic regurgitation (9%) and reasonable biventricular operate. First, elevated blood circulate from both ventricles to the overriding aorta before surgical repair is thought to be an underlying pathogenic mechanism, posing increased stress on the aortic wall. Note the origin of the principle coronary artery and the anterior place of the pulmonary artery (P) to the aorta. Aortic Anatomy and Dimensions An axial stack of black blood turbo spin-echo pictures is acquired to generally define cardiac and noncardiac anatomy. Aortic root dimensions may be assessed by double indirect transverse photographs perpendicular to the aorta, on the ranges of the annulus of the aortic valve, the sinus of Valsalva, the sinotubular junction, and the ascending aorta at the crossing of the right pulmonary artery. Both reduced elasticity and dilation of the aorta have a detrimental effect on aortic valve function. Reduced aortic elasticity offers rise to elevated left ventricular afterload and is therefore associated with increased myocardial oxygen demand, impaired coronary perfusion, and the presence of coronary artery disease. Note the difference in place of the aortic root in each images due to cardiac motion. An aortic move curve-in a part contrast study-and the corresponding lumen areas at the stage of the sinotubular junction throughout the cardiac cycle of a wholesome management are depicted in C. The minimal aortic lumen space (to be anticipated early within the cardiac cycle during the isovolumetric contraction phase) and the maximal aortic lumen area (to be anticipated when the height of aortic move passes by way of the ascending aorta) of the sinotubular junction are acquired to calculate distensibility (mm Hg-1) by the next formula: (Amax - Amin)/Amin � (Pmax - Pmin), with Amax and Amin as maximal and minimal lumen area (mm2) and Pmax and Pmin as systolic and diastolic blood strain (mm Hg). The gated steady-state free precession pictures of D and E present the minimal and maximal aortic lumen areas, respectively. Coarctation of the aorta from fetus to grownup: curable situation or lifelong disease process Repaired coarctation: a "cost-effective" strategy to establish issues in adults. Histologic modifications within the normal growing older aorta: implications for dissecting aortic aneurysm. Size and distensibility of the aortic root and aortic valve function after totally different techniques of the Ross procedure. Elastic properties of the ascending aorta in younger children after profitable coarctoplasty in infancy. Dilation of the ascending aorta in pediatric sufferers with bicuspid aortic valve: frequency, rate of progression and danger elements. Predictors of ascending aortic dilatation with bicuspid aortic valve: a large spectrum of disease expression. Reduced aortic elasticity and dilatation are associated with aortic regurgitation and left ventricular hypertrophy in nonstenotic bicuspid aortic valve sufferers. Predicting the risk of early atherosclerotic illness improvement in youngsters after restore of aortic coarctation. Impaired elastic properties of the ascending aorta in newborns earlier than and early after successful coarctation restore: proof of a systemic vascular disease of the prestenotic arteries Increased stiffness and persistent narrowing of the aorta after profitable restore of coarctation of the aorta: relationship to left ventricular mass and blood strain at relaxation and with train. Left ventricular diastolic dysfunction late after coarctation repair in childhood: influence of left ventricular hypertrophy. Magnetic resonance imaging� guided balloon angioplasty of coarctation of the aorta: a pilot examine. Central and peripheral arterial stiffness in patients after surgical repair of tetralogy of Fallot: implications for aortic root dilatation. Massive aortic aneurysm and dissection in repaired tetralogy of Fallot; analysis by cardiovascular magnetic resonance imaging. Mid-term follow-up of neoaortic regurgitation after the arterial switch operation for transposition of the nice arteries. Growth of the aortic anastomosis, annulus, and root after the arterial change procedure carried out in infancy. Long-term survival and useful follow-up in patients after the arterial change operation. Aortic root dysfunctioning and its impact on left ventricular function in Ross procedure sufferers assessed with magnetic resonance imaging. Patients, particularly sufferers with small or isolated defects, are usually asymptomatic via the first three many years of life, though greater than 70% turn out to be impaired by the fifth decade. Although it normally consists of a single defect, fenestrated defects have also been reported. It can be related to a "cleft" anterior mitral valve leaflet, which leads to mitral regurgitation, or defects within the atrioventricular or membranous interventricular septum. The patent foramen ovale usually results from abnormal resorption of the septum primum during the formation of the foramen secundum. An abnormally giant foramen ovale can occur on account of faulty improvement of the septum secundum. The defect lies immediately adjoining to the atrioventricular valves, both of which can be deformed and incompetent. These defects generally lie excessive within the atrial septum near the entry of the superior vena cava, and are generally related to anomalous right upper pulmonary venous return. An unusual inferior kind is associated with partial anomalous return of the proper lower pulmonary vein. Anomalous drainage could be into the best atrium, the superior vena cava, or the inferior vena cava. Coronary sinus opacification, which precedes right atrial opacification, confirms the prognosis. Larger defects are associated with substantial shunting, which can result in quantity overload of the proper atrium, right ventricle, and pulmonary arteries. If left untreated, the left-to-right shunting may end in pulmonary hypertension, right ventricular failure, decreased proper ventricular compliance, and doubtlessly right-to-left shunting (Eisenmenger syndrome). Cardiac auscultation reveals a standard S1, fastened splitting of S2, and a systolic outflow murmur as a end result of the increased circulate into the principle pulmonary artery. The improvement of pulmonary hypertension leads to narrowing of the splitting of S2 and accentuation of the pulmonary closure part. The pulmonic systolic murmur decreases in intensity, and a diastolic pulmonic regurgitation murmur might seem. The commonest manifestations of this condition are growth of fatigue, dyspnea on exertion, and train intolerance usually through the third and fourth many years. The improvement of palpitations associated to supraventricular arrhythmia is the most typical symptom in adults. Occasionally, sufferers could present with paradoxical embolization or recurrent respiratory an infection. Over time, pulmonary strain will increase because of increased pulmonary resistance, and Imaging Technique and Findings Radiography A plain chest radiograph.
Specifications/Details
Global left ventricular structure and performance: enddiastolic volume blood pressure 5030 zestoretic 17.5 mg order free shipping, end-systolic volume prehypertension education zestoretic 17.5 mg order fast delivery, stroke quantity heart attack facts zestoretic 17.5 mg without a prescription, ejection fraction hypertension pulmonary generic zestoretic 17.5 mg free shipping, corresponding values corrected for physique dimension (body surface area listed values) 2. Global proper ventricular construction and performance: enddiastolic volume, end-systolic quantity, stroke volume, ejection fraction, corresponding values corrected for physique size (body surface area listed values) three. Regional wall movement abnormalities: comment on synchrony of contraction of the proper and left ventricles four. Myocardial sign abnormalities: areas of T1 high sign that may correspond to fat 5. Gadolinium hyperenhancement areas: restricted to right ventricle versus left ventricle 6. Although proper ventricular disarticulation was used prior to now, this procedure has been deserted. Cardiac transplantation is a final resort measure within the wake of associated high morbidity and mortality and restricted availability of donors. Genetics of arrhythmogenic proper ventricular cardiomyopathy-status quo and future perspectives. Magnetic resonance and computed tomography imaging of arrhythmogenic right ventricular dysplasia. The molecular genetics of arrhythmogenic right ventricular dysplasia-cardiomyopathy. Clinical and genetic characterization of families with arrhythmogenic proper ventricular dysplasia/cardiomyopathy supplies novel insights into patterns of disease expression. Arrhythmogenic right ventricular dysplasia/cardiomyopathy: screening, analysis, and remedy. Clinical profile and long-term followup of 37 families with arrhythmogenic right ventricular cardiomyopathy. Frequency of supraventricular tachyarrhythmias in arrhythmogenic proper ventricular dysplasia. Desmoplakin disease in arrhythmogenic right ventricular cardiomyopathy: early genotypephenotype research. Prospective evaluation of family members for familial arrhythmogenic proper ventricular cardiomyopathy/dysplasia reveals a must broaden diagnostic standards. Electrocardiographic options of arrhythmogenic proper ventricular dysplasia/cardiomyopathy based on illness severity: a have to broaden diagnostic criteria. Left ventricular involvement in arrhythmogenic proper ventricular cardiomyopathy-a scintigraphic and echocardiographic study. Echocardiographic findings in patients assembly task force standards for arrhythmogenic proper ventricular dysplasia: new insights from the multidisciplinary study of right ventricular dysplasia. Utility of tissue Doppler and strain echocardiography in arrhythmogenic proper ventricular dysplasia/cardiomyopathy. Feasibility and variability of three dimensional echocardiography in arrhythmogenic right ventricular dysplasia/cardiomyopathy. Usefulness of electron-beam computed tomography in arrhythmogenic right ventricular dysplasia: relationship to electrophysiological abnormalities and left ventricular involvement. Clinical utility and safety of a protocol for noncardiac and cardiac magnetic resonance imaging of sufferers with everlasting pacemakers and implantablecardioverter defibrillators at 1. Quantification of fatty tissue mass by magnetic resonance imaging in arrhythmogenic right ventricular dysplasia. Magnetic resonance imaging of arrhythmogenic proper ventricular dysplasia: sensitivity, specificity, and observer variability of fat detection versus functional analysis of the best ventricle. Regional variations in systolic and diastolic perform in arrhythmogenic right ventricular dysplasia/ cardiomyopathy using magnetic resonance imaging. Arrhythmogenic right ventricular cardiomyopathies: medical varieties and primary differential diagnoses. Myocarditis 66 Etiology and Pathophysiology Infections are a significant cause of myocarditis. Viruses, corresponding to coxsackieviruses A and B and other enteroviruses, adenovirus, influenza virus, and Epstein-Barr virus, are the most important causes of myocarditis within the United States. Various medicines, corresponding to doxorubicin (Adriamycin) and sulfonamides, and toxins, corresponding to cocaine, have also been related to myocarditis. Large-vessel vasculitis, such as Takayasu arteritis, and autoimmune diseases, such as systemic lupus erythematosus, sarcoidosis, and Wegener granulomatosis, are additionally important but uncommon causes of myocarditis. Krishnam Myocarditis-acute inflammatory syndrome of myocardium-is a uncommon cause of acute chest pain and an necessary cause of dilated cardiomyopathy. The affected person presents acutely with chest pain and dyspnea or, hardly ever, hemodynamic compromise of the fulminant type. Chronic myocarditis often is manifested with signs and signs of dilated cardiomyopathy. Clinical displays, biochemistry, and echocardiographic findings might overlap with those of myocardial infarction or ischemic coronary heart illness. Cardiac transplantation may be considered for patients with deteriorating cardiac function in dilated cardiomyopathy. Manifestations of Disease Clinical Presentation the clinical manifestation of myocarditis is variable, starting from progressive dyspnea and weakness to left ventricular failure to sudden demise. Patients might present with influenza-like signs, corresponding to fever, fatigue, malaise, and arthralgia. A nodular focus of non-subendocardial delayed hyperenhancement can also be famous within the lateral myocardial wall of the left ventricle (arrow). C, Vertical long-axis view of delayed postcontrast T1-weighted gradient-echo sequence shows a well-defined oval focus of subepicardial delayed hyperenhancement (arrow) and subendocardial sparing (arrowhead). Imaging Technique and Findings Radiography Chest radiographs may be completely normal in patients with myocarditis, particularly acutely. Alternatively, cardiomegaly, interstitial or alveolar pulmonary edema, pleural effusions, and pericardial effusion may be detected as a end result of left ventricular failure. However, the quantity of iodinated contrast materials administered should be considered in patients who may have already undergone conventional coronary arteriography. On delayed enhanced images, nodular, patchy, bandlike enhancement of the mid and epicardial layer of the left ventricular wall may be seen in sufferers with myocarditis. By identifying inflammatory lesions in the myocardium, it helps information endomyocardial biopsy for histopathologic affirmation of prognosis. It can also be a superb modality for subsequent evaluation of pure regression of inflammation or treatment response in patients already identified with myocarditis. Horizontal long-axis view of T2-weighted darkish blood double-inversion recovery sequence shows foci of hyperintensity throughout the mid-myocardium, extra distinguished within the lateral myocardium (arrow), according to focal irritation related to myocarditis. T1-weighted delayed postcontrast pictures confirmed corresponding hyperenhancement of left ventricular myocardium and in addition pericardial enhancement consistent with myopericarditis. C, Short-axis view of delayed postcontrast T1-weighted gradient-echo sequence performed after 2 months shows interval decrease in the area of delayed hyperenhancement (arrow), in keeping with resolving myocarditis. Postcontrast T1-weighted gradient-echo pictures sometimes show ovoid or nodular, patchy, epicardial and mid-wall delayed hyperenhancement of myocardium in a nonsegmental vascular territory. Focal delayed hyperenhancement might become diffuse later within the disease process but with eventual regression. Persistent inflammation could result in myocardial fibrosis and scar formation, resulting in myocardial thinning and dilated cardiomyopathy in some patients. A giant research showed that areas of delayed hyperenhancement are associated with active irritation defined by histopathologic examination. A potential research confirmed that every one the patients with acute myocardial infarction had a segmental early subendocardial defect on first-pass perfusion and corresponding segmental subendocardial or transmural delayed hyperenhancement in a predominantly anteroseptal or inferior vascular distribution. All however considered one of 24 patients with myocarditis had no early perfusion defect and focal or diffuse nonsegmental non-subendocardial delayed hyperenhancement predominantly within the inferolateral location. Because myocarditis often leads to world, as a substitute of focal, excessive T2 sign abnormality, the sign intensity of the myocardium is compared with that of skeletal muscle. Classic Signs Radiography Findings on radiography are regular, but cardiomegaly and interstitial edema could additionally be seen. Typically, ovoid or nodular epicardial and mid-wall delayed hyperenhancement areas of left ventricular myocardium which might be unrelated to arterial distribution may be demonstrated. Cardiac sarcoidosis and idiopathic or ischemic dilated cardiomyopathy ought to be thought-about in patients with continual myocarditis presenting with progressive shortness of breath. Nuclear Medicine/Positron Emission Tomography Gallium Ga 67, an agent used for evaluation of irritation, has been used to distinguish acute myocarditis from acute myocardial infarction and to identify myocarditis in children with Kawasaki disease.
Syndromes
- Is it better if you use an elastic wrap?
- Use railings.
- Bone tumor or cancer
- Severe respiratory infections that keep coming back (recurring)
- Psychological complications
- Shortness of breath
- Vegetables such as Brussels sprouts, broccoli, cauliflower, and cabbage
- Myelodysplasia
- The child has unusual raised ridges on the scalp
- The needle is removed, the area is cleaned, and a bandage is placed over the needle site. The person is often asked to lie down for a short time after the test.
Related Products
Additional information:
Usage: b.i.d.
Tags: zestoretic 17.5 mg generic overnight delivery, zestoretic 17.5 mg buy generic online, zestoretic 17.5 mg order online, 17.5 mg zestoretic visa, 17.5 mg zestoretic discount otc, cheap zestoretic 17.5 mg on-line, 17.5 mg zestoretic buy with mastercard, 17.5 mg zestoretic discount amex, buy zestoretic 17.5 mg without prescription, buy 17.5 mg zestoretic, zestoretic 17.5 mg effective, 17.5 mg zestoretic buy mastercard, quality zestoretic 17.5 mg, purchase zestoretic 17.5 mg, buy generic zestoretic 17.5 mg on line, 17.5 mg zestoretic order with visa
8 of 10
Votes: 88 votes
Total customer reviews: 88
Customer Reviews
Ernesto, 47 years: Relative contraindications embody decreased life expectancy related to other medical points.
Trano, 36 years: These orientations are initially obtained from the axial plane, where a line transecting the apex and the midline of the bottom of the left ventricle yields a regular two-chamber view.
Rocko, 37 years: Gadolinium Contrast Agents with Macromolecular Structures Examples of gadolinium-based blood pool agents with macromolecular constructions are P792 (Vistarem, Guebert) and Gadomer-17 (Bayer Healthcare).