
Zithromax
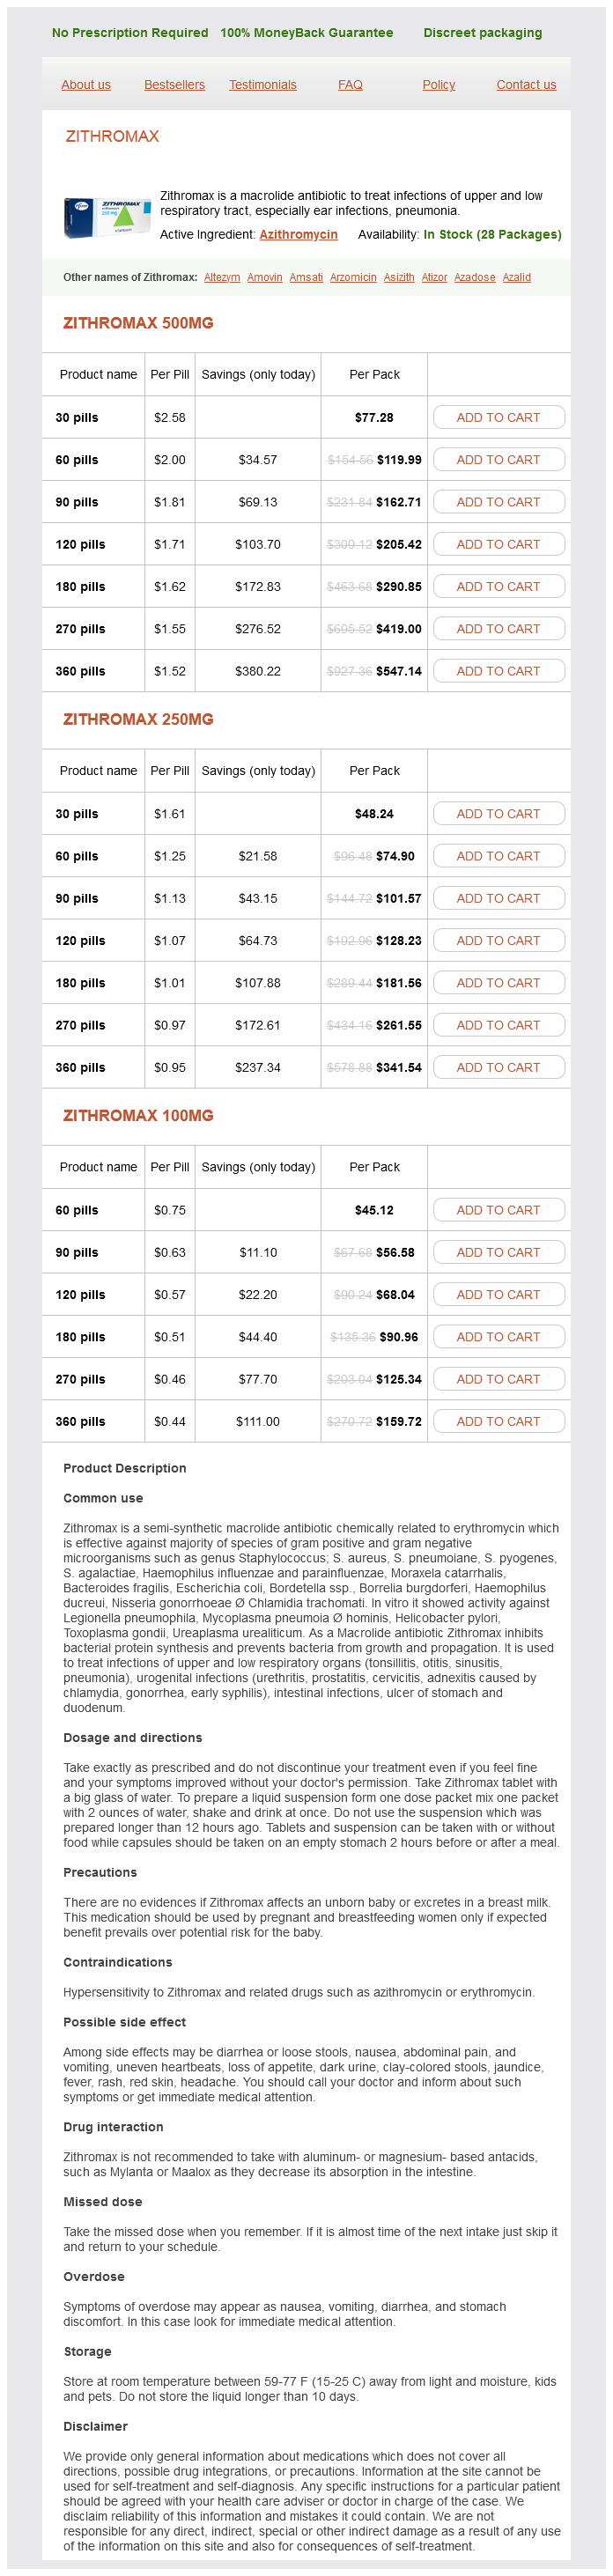
Zithromax 500mg
- 30 pills - $77.28
- 60 pills - $119.99
- 90 pills - $162.71
- 120 pills - $205.42
- 180 pills - $290.85
- 270 pills - $419.00
- 360 pills - $547.14
Zithromax 250mg
- 30 pills - $48.24
- 60 pills - $74.90
- 90 pills - $101.57
- 120 pills - $128.23
- 180 pills - $181.56
- 270 pills - $261.55
- 360 pills - $341.54
Zithromax 100mg
- 60 pills - $45.12
- 90 pills - $56.58
- 120 pills - $68.04
- 180 pills - $90.96
- 270 pills - $125.34
- 360 pills - $159.72
Zithromax dosages: 500 mg, 250 mg, 100 mg
Zithromax packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
In stock: 744
Only $0,34 per item
Description
We have already described at length the role of the renin-angiotensin vasoconstrictor system to provide a the role of the kidneys in long-term management of arterial stress antibiotics japan over counter 100 mg zithromax purchase amex. Yet treatment for dogs broken leg order 250 mg zithromax, it eventually develops a suggestions acquire for control of arterial pressure practically equal to infinity infection specialist buy zithromax 250 mg lowest price. This means that this mechanism can ultimately return the arterial strain nearly all the greatest way back antibiotics used to treat mrsa 100 mg zithromax cheap with mastercard, not merely partway again, to the strain level that provides normal output of salt and water by the kidneys. By now, the reader should be familiar with this concept, which has been the main point of this chapter. Many components can have an effect on the pressure-regulating stage of the renal�body fluid mechanism. A lower in arterial pressure leads within minutes to a rise in aldosterone secretion, and over the subsequent hour or days, this impact plays an essential role in modifying the pressure management characteristics of the renal�body fluid mechanism. Especially essential is interplay of the reninangiotensin system with the aldosterone and renal fluid mechanisms. We have seen in this chapter that salt intake can decrease to as little as one-tenth normal or can increase to 10 to 15 times normal and yet the regulated degree of the mean arterial strain will change only a few mm Hg if the renin-angiotensinaldosterone system is absolutely operative. Thus, arterial stress control begins with the lifesaving measures of the nervous strain controls, then continues with the sustaining characteristics of the intermediate pressure controls, and, lastly, is stabilized at the long-term stress stage by the renal�body fluid mechanism. This long-term mechanism, in flip, has multiple interactions with the renin-angiotensin-aldosterone system, the nervous system, and several other components that present particular blood strain control capabilities for special purposes. Seventh Report of the Joint National Committeeonprevention,detection,analysis,andtreatmentof highbloodpressure. Venous return is the quantity of blood flowing from the veins into the proper atrium every minute. The venous return and the cardiac output must equal one another except for a few heartbeats at a time when blood is quickly stored in or removed from the heart and lungs. The cardiac index rises quickly to a level higher than 4 L/min/m2 at age 10 years and declines to about 2. We clarify later within the chapter that the cardiac output is regulated throughout life almost instantly in proportion to total metabolic activity. Therefore, the declining cardiac index is indicative of declining activity or declining muscle mass with age. When one considers the issue of age as well- because with increasing age, physique exercise and mass of some tissues. Cardiac Index Experiments have proven that the cardiac output will increase approximately in proportion to the surface area of the physique. Therefore, cardiac output is frequently acknowledged by means of the cardiac index, which is the cardiac output per square meter of physique surface area. The common human being who weighs 70 kilograms has a body floor space of about 1. Cardiacindexforthehumanbeing(cardiacoutputper square meter of floor area) at totally different ages. Therefore, it follows that cardiac output regulation is the sum of all of the native blood move laws. Note that at each increasing level of work output during train, oxygen consumption and cardiac output improve in parallel to each other. To summarize, cardiac output is normally decided by the sum of all the various factors throughout the physique that control local blood flow. All the native blood flows summate to kind the venous return, and the guts automatically pumps this returning blood back into the arteries to circulate around the system once more. It is repeated here to illustrate a particularly important principle in cardiac output control: Under many circumstances, the long-term cardiac output degree varies reciprocally with changes in total peripheral vascular resistance, as lengthy as the arterial pressure is unchanged. Then, when the entire Oxygen consumption (L/min) the primary cause peripheral components are usually so essential in controlling cardiac output is that the guts has a built-in mechanism that normally permits it to pump routinely no matter quantity of blood that flows into the best atrium from the veins. This mechanism, known as the Frank-Starling regulation of the heart, was discussed in Chapter 9. Basically, this law states that when increased quantities of blood flow into the heart, the elevated blood stretches the walls of the center chambers. As a results of the stretch, the cardiac muscle contracts with elevated drive, and this motion empties the extra blood that has entered from the systemic circulation. Therefore, the blood that flows into the center is routinely pumped without delay into the aorta and flows once more by way of the circulation. Another essential issue, mentioned in Chapter 10, is that stretching the guts causes the center to pump faster, resulting in an elevated heart price. That is, stretch of the sinus node in the wall of the proper atrium has a direct impact on the rhythmicity of the node to enhance the heart fee as much as 10 to 15 p.c. In addition, the stretched proper atrium initiates a nervous reflex known as the Bainbridge reflex, passing first to the vasomotor center of the brain after which back to the heart by way of the sympathetic nerves and vagi, also to improve the guts fee. Under most traditional unstressed conditions, the cardiac output is controlled mainly by peripheral factors that determine venous return. However, as shall be mentioned later in the chapter, if the returning blood does become more than the heart can pump, then the heart turns into the limiting issue that determines cardiac output. Cardiac output is equal to venous return and is the sum of tissue and organ blood flows. Chronic effect of different ranges of complete peripheral resistance on cardiac output, showing a reciprocal relationship between complete peripheral resistance and cardiac output. The lowermost curves are for hypoeffective hearts that are pumping at ranges below normal. Factors That Cause a Hypereffective Heart Two kinds of components that may make the heart a greater pump than normal are (1) nervous stimulation and (2) hypertrophy of the heart muscle. In Thus, any time the long-term stage of whole peripheral resistance adjustments (but no other features of the circulation change), the cardiac output adjustments quantitatively in precisely the incorrect way. Note that the plateau degree of this normal cardiac output curve is about thirteen L/min, 2. This implies that the traditional human coronary heart, functioning with none particular stimulation, can pump a venous return as much as about 2. The uppermost curves are for hypereffective hearts which are Chapter 9, we saw that a mixture of (1) sympathetic stimulation and (2) parasympathetic inhibition does two issues to enhance the pumping effectiveness of the center: (1) It greatly increases the guts rate-sometimes, in young individuals, from the traditional level of seventy two beats/min as much as a hundred and eighty to 200 beats/min-and (2) it increases the strength of heart contraction (which is known as increased "contractility") to twice its normal power. A long-term increased workload, but not so much extra load that it damages the heart, causes the center muscle to enhance in mass and contractile power in the identical way that heavy train causes skeletal muscle tissue to hypertrophy. This factor will increase the plateau level of the cardiac output curve, sometimes 60 to one hundred pc, and subsequently permits the center to pump much higher than ordinary quantities of cardiac output. With nervous management mechanisms intact, dilating all of the peripheral blood vessels triggered virtually no change in arterial stress but elevated the cardiac output nearly fourfold. However, after autonomic management of the nervous system had been blocked, vasodilation of the vessels with dinitrophenol (dashed curves) then brought on a profound fall in arterial strain to about one-half normal, and the cardiac output rose only one. Thus, upkeep of a normal arterial strain by the nervous reflexes, by mechanisms defined in Chapter 18, is crucial to achieve excessive cardiac outputs when the peripheral tissues dilate their vessels to increase the venous return. Obviously, this greatly decreases the total peripheral resistance, which normally would decrease the arterial stress as properly. The same brain activity that sends motor indicators to the muscle tissue sends simultaneous signals into the autonomic nervous centers of the brain to excite circulatory exercise, inflicting massive vein constriction, increased coronary heart fee, and increased contractility of the center. All these changes appearing collectively increase the arterial stress above normal, which in turn forces nonetheless more blood move through the active muscular tissues. In summary, when local tissue blood vessels dilate and increase venous return and cardiac output above regular, the nervous system plays a key position in preventing the arterial strain from falling to disastrously low ranges. In fact, during train, the nervous system goes even further, offering additional indicators to raise the arterial pressure above regular, which serves to enhance the cardiac output an extra 30 to 100%. Pathologically High or Low Cardiac Outputs In wholesome humans, the common cardiac outputs are surprisingly fixed from one individual to another. However, a quantity of scientific abnormalities may cause either excessive or low cardiac outputs. One of the distinguishing options of these situations is that they all result from chronically lowered complete peripheral resistance. Notethatwithpressurecontrol,themetabolic stimulant dinitrophenol will increase cardiac output significantly; with out pressure management, the arterial pressure falls and the cardiac output risesverylittle. Let us take a look at a variety of the circumstances that may lower the peripheral resistance and at the same time increase the cardiac output to above regular. This illness is caused by inadequate amount of the vitamin thiamine (vitamin B1) in the diet. Lack of this vitamin causes diminished capability of the tissues to use some mobile nutrients, and the local tissue blood flow mechanisms in turn cause marked compensatory peripheral vasodilation.
Lasuna (Garlic). Zithromax.
- What other names is Garlic known by?
- Are there any interactions with medications?
- Breast cancer.
- Dosing considerations for Garlic.
- What is Garlic?
- Diabetes.
- Preventing tick bites.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96322
They become absorbed into the posterior wall of the sinus the ureters open immediately and individually into the urogenital sinus above the mesonephric ducts antibiotic resistance mechanisms generic 250 mg zithromax with mastercard. The openings of the mesonephric ducts descend; their walls are integrated into the urogenital sinus bacteria 4 in urinalysis 500 mg zithromax discount free shipping, forming the trigone of the bladder D Urachus Urinary bladder E Ureter Ureteric opening Region of trigone Region of trigone Uterovaginal duct from fused paramesonephric duct Mesonephric duct Urethra In the female the fused paramesonephric ducts kind the uterovaginal duct antibiotics for uti levaquin order zithromax 100 mg without a prescription. Kallikrein has been demonstrated in rat fetal kidney antibiotic birth control trusted zithromax 100 mg, and prostaglandins have been demonstrated in the renal medulla and renal tubule. Renal dopamine is produced (mainly) by the enzymatic conversion of Ldopa to dopamine in the early segments of the proximal convoluted tubule, and is also sourced domestically from dopaminergic nerves. Other renal hormones embody an antihyperten sive lipid, which is produced in the interstitial cells of the renal medulla, and, presumably, histamine and serotonin. Growth components produced by human embryonic kidney cells include erythropoietin and interleukin (which stimulate megakaryocyte maturation) and reworking progress issue. As the ureteric outgrowth lengthens, it becomes positioned increasingly more cranially. The metanephric pelvis lies on a stage with the second lumbar vertebra when the embryo reaches a length of about thirteen mm. During this period the ascending kidney receives its blood supply sequentially from arter ies in its quick neighbourhood, i. It arises from the most caudal of the three suprarenal arteries, all of which symbolize persistent meso nephric or lateral splanchnic arteries. Additional renal arteries are relatively common, and will enter at the hilum or on the upper or lower pole of the gland � they also characterize persistent mesonephric arteries. Both of these processes start in intermediate portions of the ureter and proceed cranially and caudally. Two fusiform enlargements appear at the lumbar and pelvic levels of the ureter at 5 and 9 months, respectively (the pelvic enlargement is inconstant). As a outcome, the ureter reveals a constriction at its proximal end (pelviureteric region) and another as it crosses the pelvic brim. A third narrowing is at all times current at its distal end and is expounded to the growth of the bladder wall. At first, the distal end of the ureter is linked to the dorsomedial side of the mesonephric duct but, as a result of differential development, this connection comes to lie lateral to the duct. The ureters develop as branches of the mesonephric ducts, which attain their very own entry to the growing bladder, and their orifices open separately into the bladder on the lateral aspect of the opening of the mesonephric ducts. Part of the left wall of the cloaca, together with the left mesonephric duct, has been removed, along with the adjoining portions of the partitions of the growing bladder and rectum. E, the caudal finish of a feminine human fetus, eight 12�9 weeks, from the left-hand aspect, showing structures in and near the median plane. F, Part of the vesico-urethral portion of the endodermal cloaca of a feminine human fetus, eight 12 �9 weeks. The sinus tubercle is the elevation on the posterior wall of the urogenital sinus, caused by the fusion with the paramesonephric ducts. For many years, it was believed that the absorption of the mesone phric ducts into the urogenital sinus contributed a mesodermal epithe lium into the endodermal bladder, restricted to the trigone and the dorsal wall of the proximal half of the prostatic urethra to the opening of the prostatic utricle and ejaculatory ducts, or its feminine homologue, the whole feminine urethral dorsal wall. Antibody labelling and studies on transgenic mice have now demonstrated that the region of the com bined ducts near the urogenital sinus, referred to because the frequent nephric duct, undergoes local apoptosis as part of the traditional develop ment of the trigone area of the bladder and the institution of separate entry points for the ureters and mesonephric ducts (Mendel sohn 2009). Retinoic acid is required for ureter insertion into the uro genital sinus (Batourina et al 2005). This is additional supported by the observations that tissue combination of fetal urogenital sinus mes enchyme with epithelial mesoderm or endoderm produces completely different outcomes. Tissue recombinant with endoderm gives rise to prostatic epithelium, whereas the same mesenchyme mixed with epithelial mesoderm forms seminal vesicle epithelium. Trigone epithelium dif ferentiates into prostatic epithelium, confirming an endoderm lineage (Tanaka et al 2010). The earlier mechanism for trigone development additionally instructed that the muscle in that area derived from the ureter and contributed to the valvelike entry level that forestalls urinary reflux. Studies have now shown that the ureter passes through a tunnel within the bladder wall in parallel with blood vessels. Study of easy muscle progenitors exhibits that the bulk of the trigone derives from bladder muscle (detru sor), with a limited contribution from ureteral longitudinal smooth muscle fibres on the lateral edges. Bladder filling and emptying cycles are required for regular bladder remodelling throughout fetal growth; in this process, detrusor easy muscle cells bear cyclical apoptosis and proliferation. At 20 weeks, the kidneys are greatest visualized in a bit of the abdomen caudal to that used for abdominal circumference estimation. The diameter of the renal pelvis is reported within the anterior posterior view; 7 mm or less is considered normal at midgestation (To and Periera 2015). Urinary obstruction is considered an abnormality, but transient modest obstruc tion is taken into account normal throughout canalization of the urinary tract, and has been reported in 10�20% of fetuses in the third trimester. A delay in canalization, or within the rupture of the cloacal membrane, can produce a dilation. Similarly, the closure of the urachus at 32 weeks could additionally be related to highresistance outflow for the system, which once more produces transient obstruction. Distension of the fetal bladder, which may indicate lower urinary tract obstruction, impacts 2. Over half of such cases are attributable to the development of posterior urethral valves (a congenitally obstructing posterior urethral membrane); there may be a dilated posterior urethra and thickened bladder wall. Addition of new cortical nephrons continues within the first few months of postnatal life, after which basic progress of the glomeruli and tubules results in the disappear ance of lobulation. The renal blood circulate is decrease in the neonate; grownup values are attained by the top of the first yr. The glomerular filtration fee at start is roughly 30% of the adult value, which is attained by 3�5 months of age. Although described as an belly organ, almost onehalf of the neonatal bladder lies below a line drawn from the promontory of the sacrum to the higher edge of the pubic symphysis, i. From the bladder neck, the bladder extends anteriorly and barely upwards in shut contact with the pubis, until it reaches the anterior abdominal wall. The apex of the contracted bladder lies at a point halfway between the pubis and the umbilicus. When the bladder is full of urine, the apex may lengthen up to the level of the umbilicus. It is therefore possible to get hold of urine by inserting a needle, linked to a syringe, into the bladder through the abdominal wall about 2 cm above the pubic symphysis, after which aspirating the con tents into the sterile syringe. The success fee of the process is variable and depends on the bladder being full; a a lot higher success rate has been reported by using an ultrasound scanner to find the bladder and make sure that it incorporates urine prior to insertion of the needle. Because the apex of the bladder is comparatively high, pressure on the decrease stomach wall will specific urine from an infant bladder. The elongated shape of the bladder in neonates signifies that the ureters are correspondingly lowered in length they usually lack a pelvic portion. They operate early in growth and produce the amniotic fluid that surrounds the fetus. The lobulated appearance of fetal kidneys remains to be Congenital anomalies of the kidney and urinary tract are relatively widespread (3�6% of live births) (Yosypiv 2012). In unilateral renal agenesis, the stay ing kidney reveals compensatory hypertrophy and produces a nearly normal functional mass of renal tissue. Atresia of the ureter during improvement causes a nonfunctional multicystic dysplastic kidney, thought to be secondary to urinary obstruction being current whereas the tubules are still forming. Misalignment of the genital tubercle and urogenital swellings with the urogenital membrane during early growth ends in subsequent malposition of the bladder, urethra and associated sphincters. The disappearance of the urogenital membrane exposes the posterior wall of the bladder, and the urethral opening is on the superior aspect of the penis or clitoris. Less common is infantile cystic renal illness, inherited as a recessive trait, during which the proximal and distal tubules are dilated to a point however the collecting ducts are grossly affected. There is proof that infants born small for gestational date retain smaller kidneys throughout childhood. A causal relationship between low start weight and later chronic kidney disease is speculated, in addition to susceptibility to hypertension in grownup life (White et al 2009). In this situation, the urorectal septum (internal) is associated with the genital tubercle (external), which implies that the urogenital and anal membranes are broadly separated. When the urogenital mem brane involutes, the posterior floor of the bladder is exposed to the anterior abdominal wall. The decrease a half of the abdominal wall is, subsequently, occupied by an irregularly oval area, lined with mucous membrane, on which the 2 ureters open. The periphery of this extro verted area, which is covered by urothelium, becomes continuous with the pores and skin.
Specifications/Details
The thick tendon of adductor magnus can be palpated on the distal medial thigh antibiotic guidelines 2014 buy zithromax 100 mg overnight delivery, deep within the indentation fashioned between vastus medialis anteriorly and gracilis and sartorius posteriorly infection 2010 discount 250 mg zithromax with mastercard. During ankle inversion and extension of the toes antibiotics yellow teeth zithromax 500 mg cheap online, the distinguished tendon of tibialis anterior is seen on the medial facet of the dorsal foot antibiotic resistance and meat zithromax 100 mg discount overnight delivery, passing inferiorly and medially to the medial cuneiform. The tendon of extensor hallucis longus could be recognized laterally; the tendons of extensor digitorum longus and fibularis tertius are further lateral as they pass deep 1330 Surface anatomy to the inferior extensor retinaculum and instantly anterior to the lateral a part of the distal tibia. More distally, the tendons of extensor digitorum longus and fibularis tertius diverge and could also be traced to their insertions. The tendon is seen and palpable posterior to the malleolus when the foot is forcibly plantar flexed and inverted. The tendon of flexor digitorum longus lies immediately posterolateral to that of tibialis posterior. It curves forwards inferior to tibialis posterior and lies on the medial side of the sustentaculum tali. From there, it passes anteriorly and laterally to the centre of the plantar foot, the place it divides into 4 tendons that pass to the lateral 4 toes. The tendon of flexor hallucis longus lies inferior to , and grooves, the sustentaculum tali. As it passes in the direction of the great toe, it crosses the line of the flexor digitorum longus reverse the interval between the sustentaculum tali and the tuberosity of the navicular. Abductor hallucis could additionally be seen in some subjects as a fleshy mass alongside the medial border of the foot, passing from the medial calcaneal tubercle to the first metatarsophalangeal joint. When the toes are maximally dorsiflexed, the plantar aponeurosis is easily palpated alongside the medial border of the foot, from just distal to the heel pad as far as the first metatarsophalangeal joint. It originates from the calcaneal tubercles, which may be palpable through the anterior side of the heel pad. It is a typical website for catheter insertion for radiological examinations similar to cardiac angiography and for arterial puncture for blood gas evaluation. Popliteal artery the coronary heart beat of the popliteal artery is probably the most troublesome of the peripheral pulses to really feel as a outcome of the artery lies deep within the popliteal fossa. It is best examined with the subject mendacity supine or inclined, with the knee flexed so as to relax the tense popliteal fascia that roofs the popliteal fossa. The popliteal pulse is then felt over the midline of the fossa by deep strain towards the popliteal floor of the femur. Posterior tibial artery the pulse of the posterior tibial artery can be felt by mild palpation posterior to the medial malleolus because the artery lies between the tendons of flexor hallucis longus and flexor digitorum longus, roughly one-third of the finest way alongside a line connecting the posterior border of the medial malleolus to the calcaneal tendon. Dorsalispedisartery the dorsalis pedis arterial pulse is found by palpation in opposition to the underlying tarsals, instantly lateral to the tendon of extensor hallucis longus, from the midpoint between the malleoli to the proximal end of the first intermetatarsal house. While femoral vein puncture is comparatively simple and supplies ready access to the best atrium, the use of this method is relatively unpopular for long-term cannulation due to a greater incidence of thrombosis and sepsis. For femoral vein cannulation, the pores and skin puncture website is roughly 1 cm medial to the femoral artery and just inferior to the inguinal ligament. The lengthy saphenous vein arises from the medial end of the arch, and the brief saphenous vein arises from the lateral finish. From here, the vein ascends the thigh to the saphenous opening, the place it passes deep to enter the femoral vein. The midinguinal level is halfway between the anterior superior iliac backbone and the pubic symphysis. The artery normally passes instantly anterior to the hip joint; its course may be represented by the higher two-thirds of a line joining its entry point into the thigh with the adductor tubercle, when the thigh is flexed, slightly kidnapped and rotated laterally. It travels deep to sartorius from the apex of the femoral triangle to the adductor hiatus. The profunda femoris artery (deep artery of the thigh) usually arises from the lateral side of the femoral artery, 6. The popliteal artery could also be represented by a line extending from the junction of the center and lower thirds of the thigh, 2. It passes on to the dorsal foot lateral to the tendon of extensor hallucis longus, as the dorsalis pedis artery. The latter offers off a medial department that travels towards the first intermetatarsal area. At first, the nerve lies lateral to the popliteal artery but progressively crosses the vessel to gain its medial aspect. Nerves In the proximal femoral triangle, the femoral nerve is positioned instantly lateral to the femoral artery pulse. The surface marking for the course of the saphenous nerve within the leg matches that of the lengthy saphenous vein (see above). The nerve is vulnerable to damage during anterolateral surgical approaches to the hip. The course of the sciatic nerve may be represented by a curved line that begins at a point zero. It then continues vertically and inferiorly in the midline of the posterior side of the FemoralarteryThe pulsations of the femoral artery could be felt at its entry point into the proximal femoral triangle, the place it can be compressed in opposition to either the superior pubic ramus or the hip joint. The floor marking for the course of the tibial nerve within the leg matches that of the posterior tibial artery (see above). The frequent fibular nerve is palpable medial and distal to the tendon of biceps femoris and over the neck of the fibula, although right here it turns into much less distinct because it passes deep to the origin of fibularis longus. At the neck of the fibula, the nerve is at explicit risk of damage both from a tightly utilized plaster solid or from a fracture. The superficial fibular nerve also begins on the lateral side of the neck of the fibula. It descends to a degree on the anterior border of fibularis longus, at the junction of the middle and decrease thirds of the leg, the place it pierces the deep fascia and divides into intermediate and medial dorsal cutaneous branches. These superficial nerves are in danger from surgery within the anterior ankle region (especially during arthroscopy). With the affected person supine and the knee prolonged, the needle is introduced at the degree of the superior border of the patella and guided in course of the suprapatellar bursa. Popliteal fossa Sciatic nerve blocks at the popliteal fossa in infants and youngsters could be successfully performed above the popliteal pores and skin crease by correcting the grownup landmark of 10 cm by the ratio of the calculated baby femoral shaft size over the adult femoral shaft size (Berni�re et al 2008). Ankle the anterior method entails introducing the needle between the tendons of tibialis anterior and extensor hallucis longus with the foot partially plantar flexed. Arthroscopyportals the placement of portals for arthroscopy is necessary for maximizing surgical entry for visualization and for surgical devices, and likewise for avoiding harm to constructions similar to nerves and blood vessels. The anterolateral portal is sited on the pores and skin roughly 4 cm lateral to the femoral artery pulse and four cm inferior to the inguinal ligament. Under fluoroscopy, a needle traversing the skin 30�45 levels proximally is advanced into the joint. Other more lateral portals can be used; the lateral femoral cutaneous nerve and the sciatic nerve are probably at risk. Small incisions may be made within the apices of these triangular areas at in regards to the degree of the inferior pole of the patella for the anterolateral portal, and slightly lower for the anteromedial portal. These portals will allow passage of an arthroscope and instruments, with good access to many of the joint. The patellar ligament and the infrapatellar branch of the saphenous nerve are at risk from the pores and skin incisions. The nerve is much less susceptible than the ligament; its place is variable however it often lies beneath the suitable portal sites. In the times of open meniscal surgical procedure, the nerve was often divided and painful neuroma formation was not uncommon. Posteromedial and posterolateral portals are useful when higher entry to the posterior knee is required. The saphenous and customary fibular nerves, respectively, are at risk with these approaches, and anatomical knowledge is significant to guarantee protected portal placement. Laterally, the incision should be anterior to the tendon of biceps femoris, which can easily be palpated. It is essential that sharp incision consists of the pores and skin only, and that dissection right down to the joint capsule is undertaken bluntly. If the medial meniscus is sutured, the capsule have to be uncovered before tying off sutures to avoid ensnaring the nerve. Common injection websites for the lower limb are around the hip for thigh and knee ache, and across the ankle for foot surgical procedure. For the deeper nerves around the hip, using a nerve stimulator may be very useful in localizing the goal nerve exactly before infiltration of local anaesthetic.
Syndromes
- Urine creatinine
- Arrhythmias
- Hydrogen peroxide
- Surgical removal of burned skin (skin debridement)
- Liver disease
- Is there any family history of early death?
- Attending parties and other social occasions
- Speech difficulties
Related Products
Additional information:
Usage: q.i.d.
Tags: buy discount zithromax 250 mg online, zithromax 250 mg order otc, 500 mg zithromax cheap with visa, generic zithromax 250 mg with mastercard, generic zithromax 100 mg on-line, zithromax 250 mg order amex, generic 500 mg zithromax overnight delivery, zithromax 100 mg proven, order zithromax 100 mg with visa, zithromax 500 mg order line, 250 mg zithromax cheap overnight delivery, quality 250 mg zithromax, zithromax 100 mg otc, 250 mg zithromax purchase overnight delivery, zithromax 500 mg cheap on-line, buy zithromax 100 mg visa
9 of 10
Votes: 300 votes
Total customer reviews: 300
Customer Reviews
Julio, 21 years: It runs forwards below the internal pudendal artery and accompanies the perineal artery, dividing into posterior scrotal or labial and muscular branches. Cardiac Index Experiments have shown that the cardiac output will increase roughly in proportion to the floor space of the body. Cutaneous lymphatic drainage is initially to the superficial inguinal nodes, probably additionally to the popliteal nodes, after which to the deep inguinal nodes. Bismuth argued that classification of the lateral part of the left hemiliver was significantly problematic.
Abe, 39 years: Postganglionic fibres cross from these ganglia through gray rami communicantes to the femoral nerve, which carries them to the femoral artery and its branches. Severe traction lesions may produce longitudinal injuries affecting a long segment of the frequent fibular nerve. Therefore, the distinction between these two pressures known as the pressure gradient for venous return. It originates from the calcaneal tubercles, which can be palpable via the anterior aspect of the heel pad.
Zakosh, 55 years: Actions Pubococcygeus and puborectalis pull the pelvic and perineal structures ventrally and cranially, occluding the levator hiatus. The decreased afferent arteriolar resis tance in the kidneys causes the glomerular capillary stress to rise, with resultant enhance in filtration of fluid into the kidney tubules. The cavity is full of longitudinal columns coated with a thick layer of cornified, stratified, squamous epithelium. It then broadens and descends deep to semitendinosus and the long head of biceps femoris.
Arokkh, 51 years: Because the apex of the bladder is comparatively high, pressure on the lower belly wall will express urine from an infant bladder. It is terminated by a series of distinct physical occasions called mitosis that cause division of the cell into two new daughter cells. The basic mechanism for transport of a substance by way of a cellular sheet is (1) lively transport via the cell membrane on one facet of the transporting cells within the sheet, and then (2) both easy diffusion or facilitated diffusion via the membrane on the opposite facet of the cell. Peak blood flows as excessive as 400 ml/min/100 g of muscle have been reported in thigh muscles of endurance-trained athletes.